
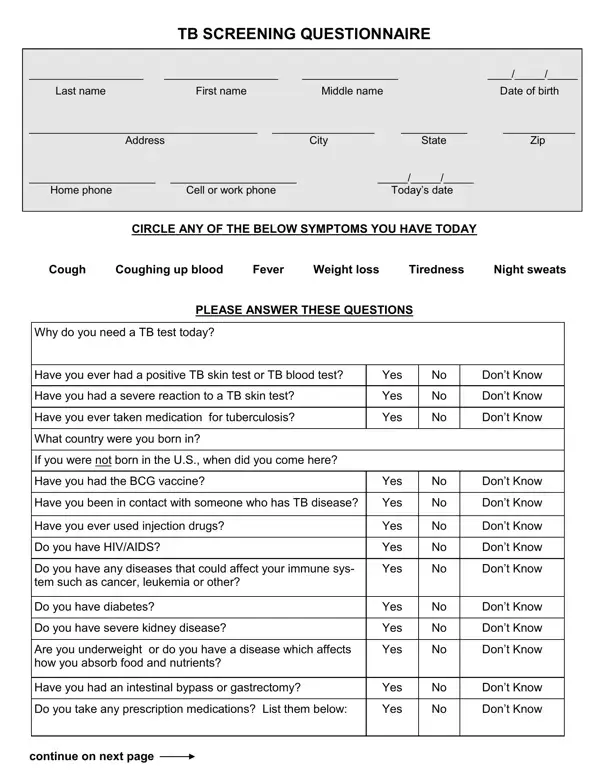

TB Screening Questionnaire at a glance
What it is: The TB Screening Questionnaire: circle any symptoms you have today and answer these questions.
Who signs: Sign on the Signature line and write the Date under: I understand the risks and benefits of the TB skin test and request that the test be given to me. I understand that if I am symptomatic for TB or if the TB skin test is positive, results may be communicated to the physician with whom I will follow-up if medical care is needed. Do not complete the part marked FOR NURSE.
A filled-in TB Screening Questionnaire example: a patient fills in the name, address and phone boxes
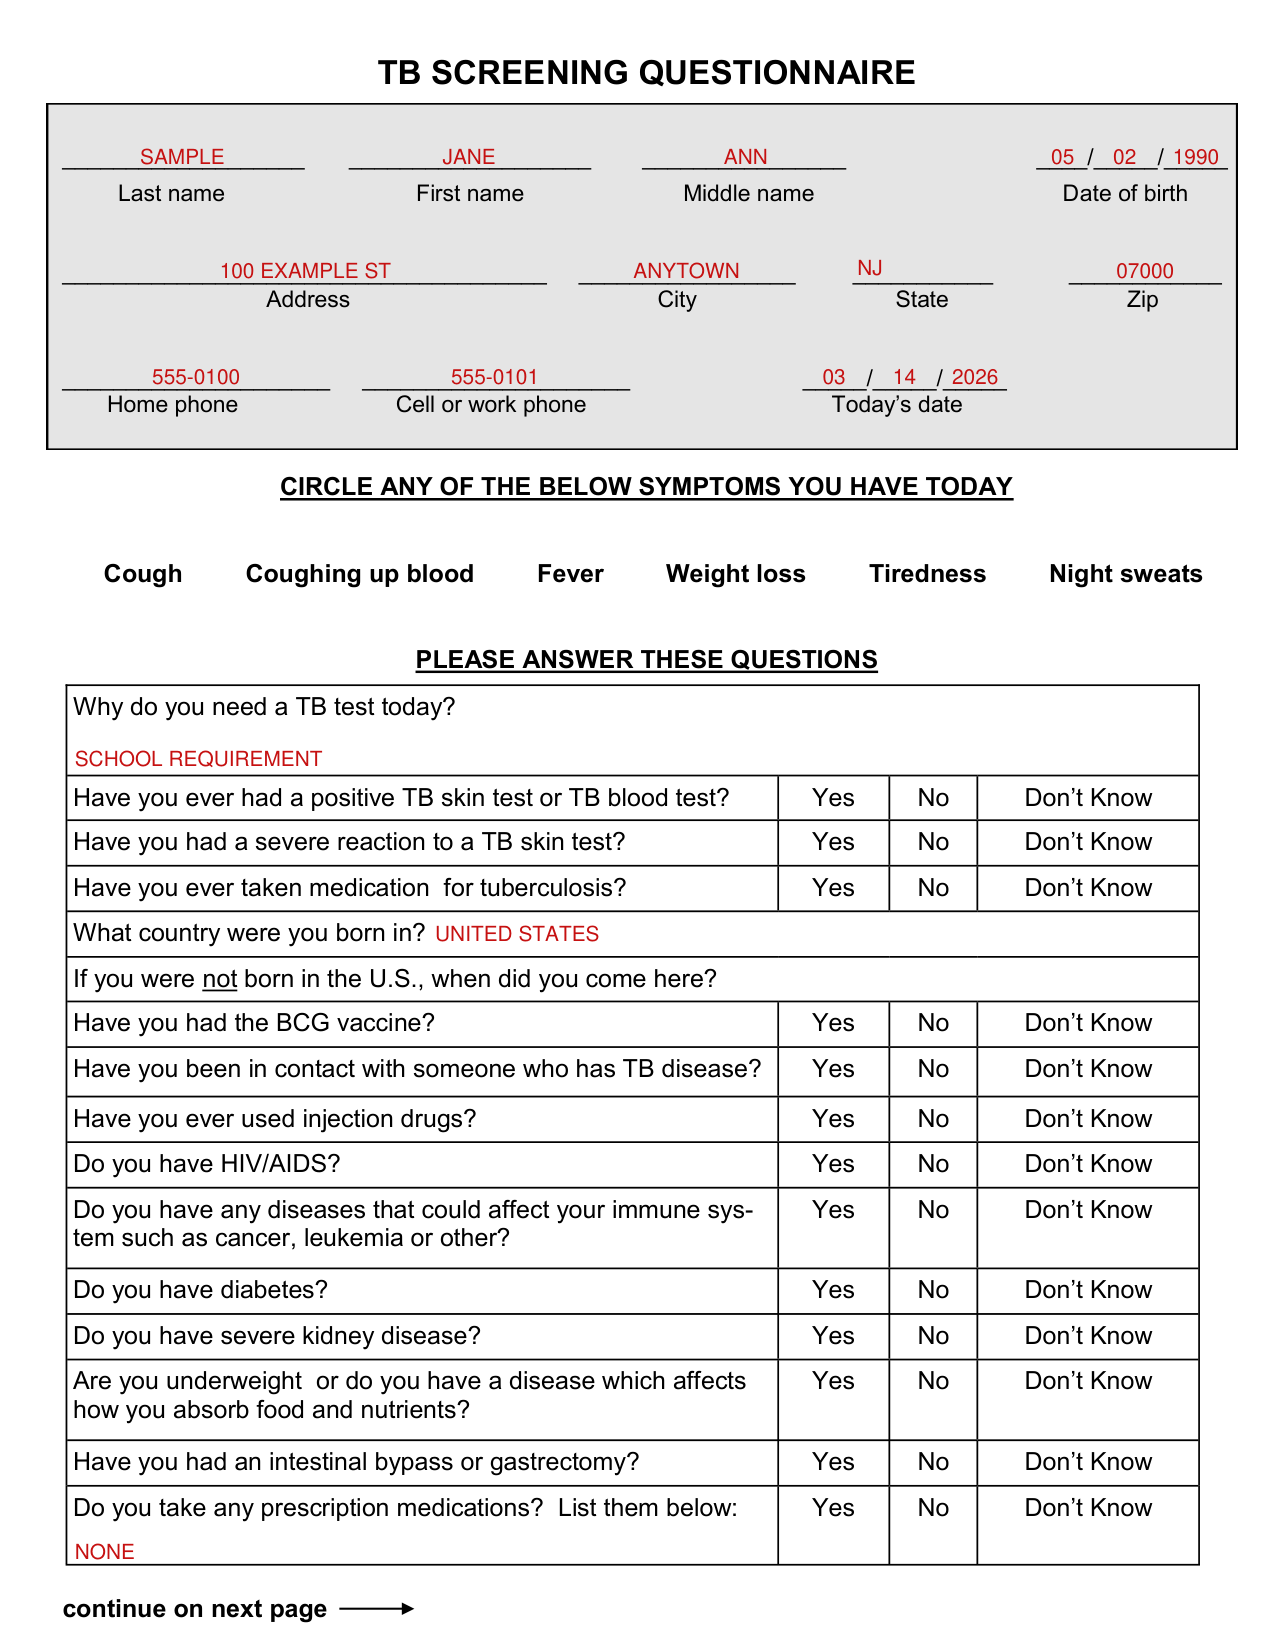
How to fill out TB Screening Questionnaire, box by box
Last name, First name, Middle name and Date of birth

Enter your Last name, First name, Middle name and Date of birth.
Address, City, State and Zip

Enter your Address, City, State and Zip.
Home phone, Cell or work phone and Today's date

Enter your Home phone, your Cell or work phone, and Today's date.
Symptoms and why you need a TB test today

Circle any of the symptoms you have today: Cough, Coughing up blood, Fever, Weight loss, Tiredness, Night sweats.
Enter: Why do you need a TB test today?
What country you were born in and when you come here

Write the country you were born in. If you were not born in the U.S., write when you did come here.
Prescription medications

For Do you take any prescription medications? mark Yes, No or Don't Know and list them in the box.
Consent to testing

Enter your Name, Last and First, before CONSENT TO TESTING.
Under CONSENT TO TESTING: I have received information about the TB skin test. I had a chance to ask questions which were answered to my satisfaction.
I agree to return in 48-72 hours to have the test read.
More rules for TB Screening Questionnaire
Mark Yes, No or Don't Know: Have you ever had a positive TB skin test or TB blood test? Have you had a severe reaction to a TB skin test? Have you ever taken medication for tuberculosis? Have you had the BCG vaccine? Have you been in contact with someone who has TB disease? Have you ever used injection drugs? Do you have HIV/AIDS? Do you have any diseases that could affect your immune system such as cancer, leukemia or other? Do you have diabetes? Do you have severe kidney disease? Are you underweight or do you have a disease which affects how you absorb food and nutrients? Have you had an intestinal bypass or gastrectomy?
Sources
[1] TB Screening Questionnaire (the Official source link on this page).