
W-488X PDF Details

When applying for HASA Admission Determination requiring Home Care Services, submit the M-11q.

Reason(s) for Referral: Services (Case Management), Benefits (PA/MA/FS), Housing or Other (check all that apply).

Household Composition: Individual (Adults only in H/H) or Family (Children Under Age 18 in H/H).

Medical Information: primary, secondary and additional diagnoses, each with a date of diagnosis, and TB Status.

Physician: Name (Print), Phone #, License # and Signature.

Social/Case Worker: Name (Print), Phone # and Agency or Institution.

QuestionAnswer
Form NameW-488X
Form Length1 page
Fillable?Yes
Fillable fields47
Avg. time to fill out8 min
EditionRev 01/08/2021
Issuing agencyThe City of New York Human Resources Administration
Other namesW-488X, W488X, 488X, HASA W-488X, HASA form, Request for Program Admission
Official sourceW-488X (Rev 01/08/2021), City of New York Human Resources Administration

How to Fill Out Form W-488X

Form W-488X at a glance

What it is: Form W-488X is the Request for Program Admission of the Human Resources Administration of The City of New York.

Who signs: Under 5. Physician, the Physician enters Name (Print), Phone #, License # and signs on the Signature line.

When applying for HASA Admission Determination, submit the HIV/AIDS Services Administration (HASA) Request for Program Admission form # W-488X. When applying for HASA Admission Determination requiring Home Care Services, submit the M-11q.

A filled-in Form W-488X example: a patient applies for HASA admission

Form W-488X example filled out, example: a patient applies for HASA admission
Jane Q. Sample, a patient, applies for HASA admission on Form W-488X. She lives in a private apartment, is HIV positive, and her household is adults only. The picture shows the filled form; all its values are invented. Private Apt. is the only Address Type ticked, so the other Address Type boxes stay empty. The SSA Name is not different from the chosen name, so SSA Name stays empty. Primary Diagnosis is the only diagnosis entered, so Secondary Diagnosis and Additional Diagnosis stay empty. No History is the only TB Status ticked, so the other TB Status boxes stay empty. Medication(s) has one line entered, so the other two lines stay empty. Services (Case Management) and Benefits (PA/MA/FS) are the only Reason(s) for Referral ticked, so Housing and Other stay empty. Nothing goes in Family because the household is adults only.

How to fill out Form W-488X, box by box

Patient's Chosen Name, SSA Name and Date of Birth

Form W-488X example filled out, patient's Chosen Name, SSA Name and Date of Birth

Enter the Patient's Chosen Name (Print), Gender, Pronoun, Race and Ethnicity.

Enter the SSA Name (If different from chosen name), Social Security # and Date of Birth.

Permanent Address and Address Type

Form W-488X example filled out, permanent Address and Address Type

Enter the Permanent Address: No. and Street, Borough, Zip Code and Telephone #.

Mark the Address Type: Private House, Emergency Housing, Supportive Housing, Private Apt., NYCHA Apt. or DHS Shelter.

Medical Information

Form W-488X example filled out, medical Information

Under 1. Medical Information, enter the Primary Diagnosis (explain: e.g., HIV Positive, Symptomatic AIDS) and its Date of Diagnosis.

Enter the Secondary Diagnosis and the Additional Diagnosis, each with its Date of Diagnosis.

TB Status: mark No History, PPD+, History Treatment Complete, Active Non-Infectious or Directly Observed Therapy.

Medication(s)

Form W-488X example filled out, medication(s)

Enter the Medication(s).

Reason(s) for Referral and Household Composition

Form W-488X example filled out, reason(s) for Referral and Household Composition

Under 3. Reason(s) for Referral, check all that apply: Services (Case Management), Benefits (PA/MA/FS), Housing or Other.

Under 4. Household Composition, mark Individual (Adults only in H/H) or Family (Children Under Age 18 in H/H).

Physician and Social/Case Worker

Form W-488X example filled out, physician and Social/Case Worker

Under 5. Physician, the Physician enters Name (Print), Phone #, License # and signs on the Signature line.

Under 6. Social/Case Worker, enter Name (Print), Phone # and Agency or Institution.

Request for Admission package completion date
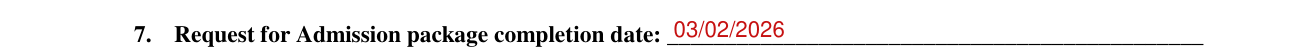
Form W-488X example filled out, request for Admission package completion date

Enter the Request for Admission package completion date.

Sources

[1] Form W-488X (Rev. 01/08/2021), Request for Program Admission, The City of New York Human Resources Administration (the Official source link on this page).