

Form F00098 at a glance
What it is: The Wheelchair/Scooter/Stroller Seating Assessment Form is an 8-page form for CCP/Home Health Services.
Who signs: Physician/Therapist's signature and Date, and QRP Signature and Date; Measurer's Signature and Date, and QRP Signature and Date.
A current wheelchair/scooter/stroller seating assessment conducted by a physician or a physical or occupational therapist must be completed for purchase of or major modifications (including new seating systems) to a wheeled mobility system.
A Qualified Rehabilitation Professional (QRP) must be present and participate in the seating assessment for all wheeled mobility systems and major modifications.
What to bring and attach to Form F00098
Attach manufacturer information, descriptions, and an itemized list of retail prices of all additions that are not included in base model price.
A filled-in Form F00098 example: a therapist starts a seating assessment
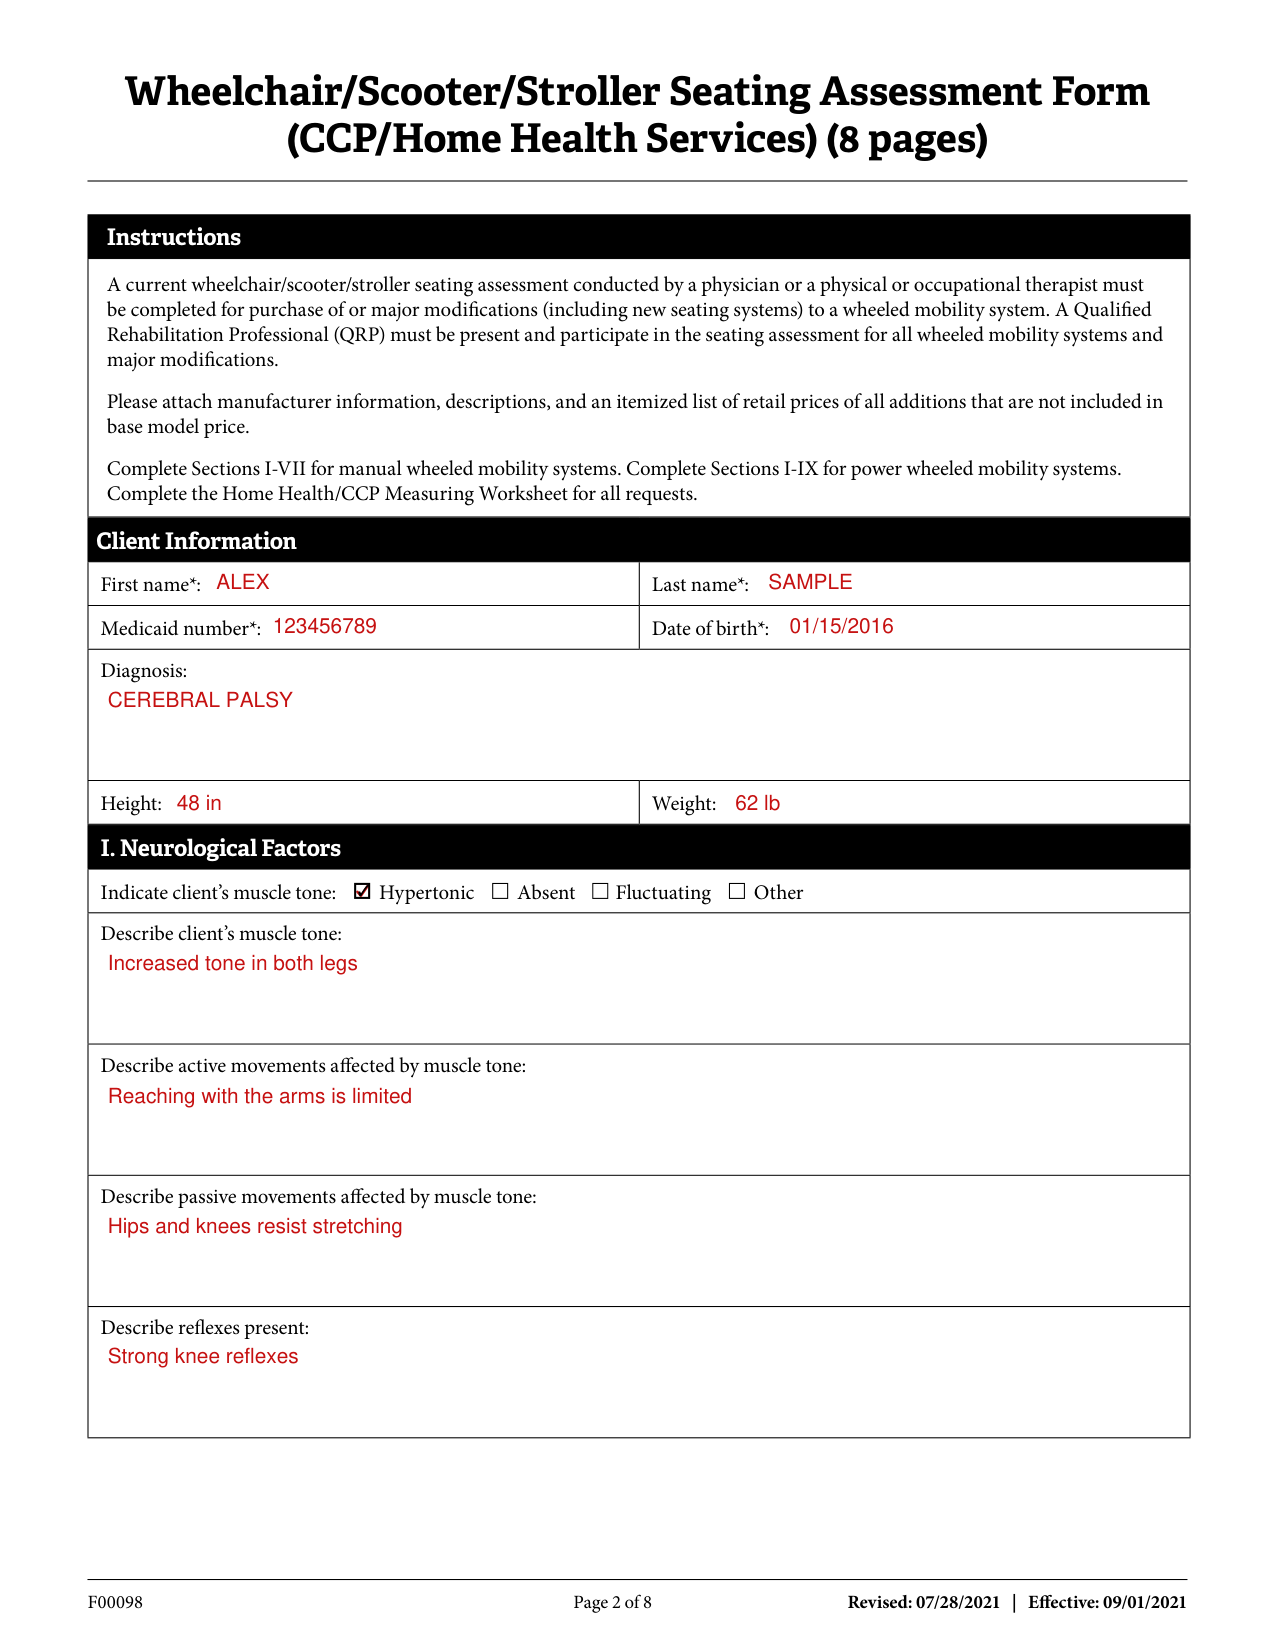
How to fill out Form F00098, box by box
Prior Authorization Request Submitter Certification Statement

If any portion of this form is incomplete, it may result in your prior authorization request being pended for additional information.
Certify and affirm that you are either the Provider, or have been specifically authorized by the Provider to submit this prior authorization request.
Check the box to certify that the Provider and the Prior Authorization Request Submitter have read and understand the Prior Authorization Agreement requirements and agree and consent to the Certification and to the TMHP Terms and Conditions.
Any false claims, statements or documents, concealment of a material fact, or omitting relevant or pertinent information may constitute fraud and may be prosecuted under applicable federal and/or State laws. Failure to provide true and accurate information, omit information, or provide notice of changes to the information previously provided may result in termination of the provider's Medicaid enrollment and/or personal exclusion from Texas Medicaid.
Client Information
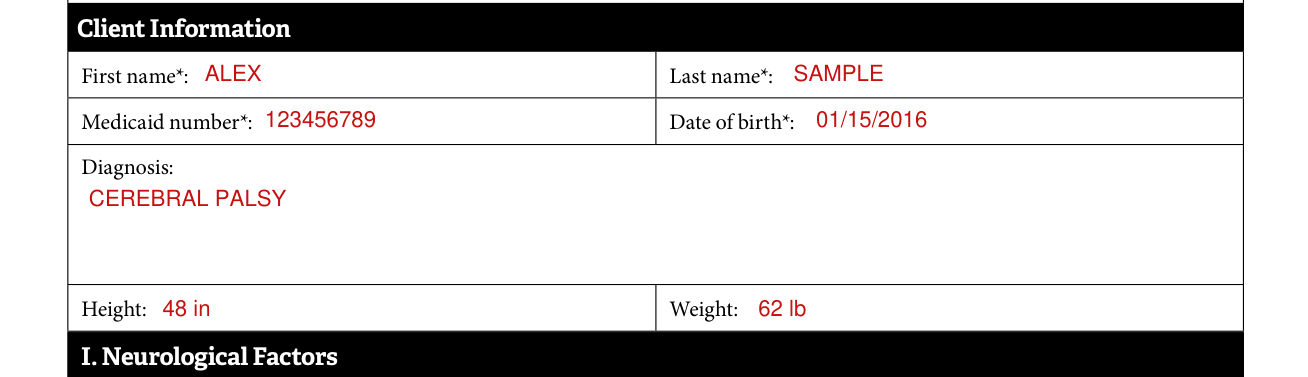
Fill in the Client First name*, Client Last name*, Medicaid number*, Date of birth*, Diagnosis, Height and Weight.
I. Neurological Factors
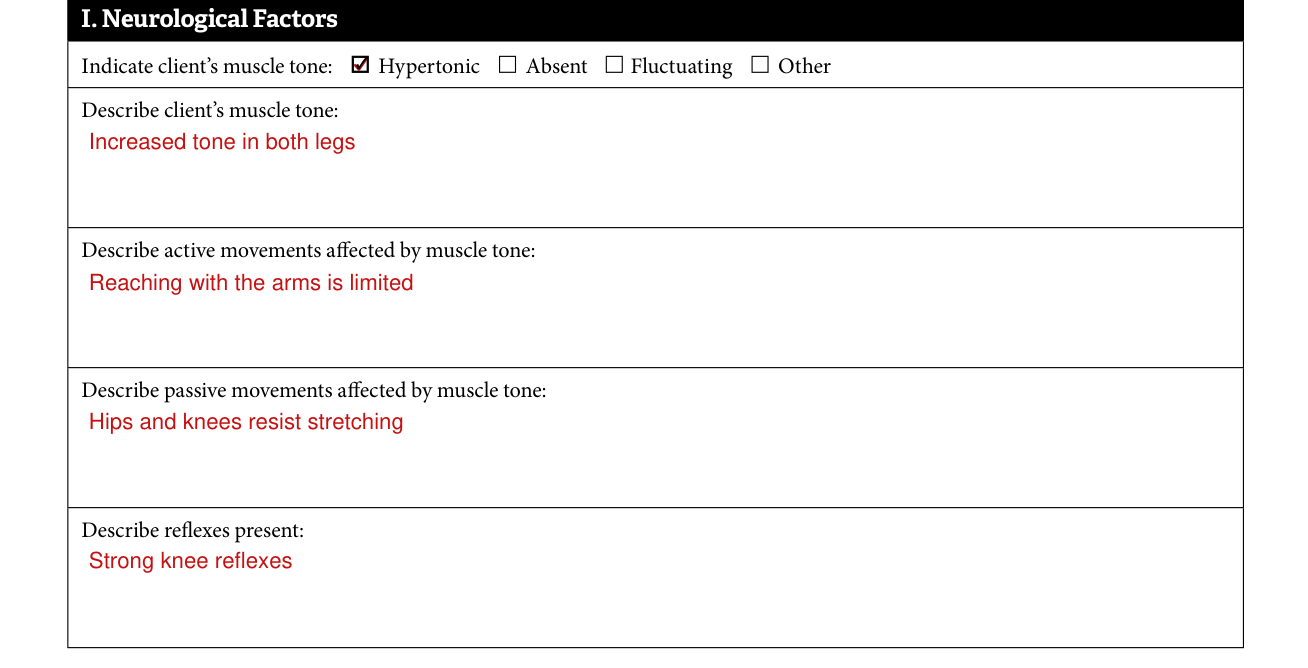
Indicate the client's muscle tone: Hypertonic, Absent, Fluctuating or Other.
Describe the client's muscle tone, the active movements affected by muscle tone, the passive movements affected by muscle tone and the reflexes present.
More rules for Form F00098
II. Postural Control: Head control, Trunk control, Upper extremities and Lower extremities: Good Fair Poor None.
III. Medical/Surgical History And Plans: Is there history of decubitis/skin breakdown? Yes or No. If yes, please explain.
Describe orthopedic conditions and/or range of motion limitations requiring special consideration (i.e., contractures, degree of spinal curvature, etc.), other physical limitations or concerns (i.e., respiratory), and any recent or expected changes in medical/physical/functional status. If surgery is anticipated, indicate the procedure and expected date.
IV. Functional Assessment, Ambulatory status: Nonambulatory, With assistance, Short distances only or Community ambulatory.
Indicate the client's ambulation potential: Expected within 1 year, Not expected, or Expected in future within the number of years entered on the line.
IV. Functional Assessment, Wheelchair Ambulation: Is client totally dependent upon wheelchair? Yes or No. If no, please explain.
Indicate the client's transfer capabilities: Maximum assistance, Moderate assistance, Minimum assistance or Independent.
Is the client tube fed? Yes or No. If yes, please explain.
Feeding and Dressing: Maximum assistance, Moderate assistance, Minimum assistance or Independent.
Describe other activities performed while in wheelchair.
V. Environmental Assessment: Describe where client resides.
Is the home accessible to the wheelchair? Yes or No. Are ramps available in the home setting? Yes or No.
Describe the client's educational/vocational setting. Is the school accessible to the wheelchair? Yes or No.
V. Environmental Assessment: Are there ramps available in the school setting? Yes or No.
If client is in school, has a school therapist been involved in the assessment? Yes or No. Name of school therapist, Name of school and School therapist's telephone number.
Describe how the wheelchair will be transported, where the wheelchair will be stored (home and/or school), and other types of equipment which will interface with the wheelchair.
VI. Requested Equipment: Describe client's current seating system, including the mobility base and the age of the seating system, why current seating system is not meeting client's needs, and the equipment requested.
VI. Requested Equipment: Describe the medical necessity for mobility base and seating system requested, the growth potential of equipment requested in number of years, and any anticipated modifications/changes to the equipment within the next three years.
VIII. Power Wheelchairs (Complete if a power wheelchair is being requested): Describe the medical necessity for power vs. manual wheelchair (justify any accessories such as power tilt or recline). Is client unable to operate a manual chair even when adapted? Yes or No.
VIII. Power Wheelchairs: Is self propulsion possible but activity is extremely labored? Yes or No. If yes, please explain. Is self propulsion possible but contrary to treatment regimen? Yes or No. If yes, please explain.
How will the power wheelchair be operated (hand, chin, etc.)? Has the client been evaluated with the proposed drive controls? Does the client have any condition that will necessitate possible change in access or drive controls within the next five years?
Is the client physically and mentally capable of operating a power wheelchair safely and with respect to others? Yes or No. Is the caregiver capable of caring for a power wheelchair and understanding how it operates? Yes or No. How will training for the power equipment be accomplished?
Complete the Home Health/CCP Measuring Worksheet for all requests.
Home Health/CCP Measuring Worksheet: Enter the Client's name*, Date of birth*, Client's Medicaid number*, Height, Date when measured and Weight.
Enter 1 to 12: Top of head to bottom of buttocks; Top of shoulder to bottom of buttocks; Arm pit to bottom of buttocks; Elbow to bottom of buttocks; Back of buttocks to back of knee; Foot length; Head width; Shoulder width; Arm pit to arm pit; Hip width; Distance to bottom of left leg (popliteal to heel); Distance to bottom of right leg (popliteal to heel). Add Additional Comments.
If your situation is different
Manual wheeled mobility systems
Complete Sections I-VII for manual wheeled mobility systems.
Power wheeled mobility systems
Complete Sections I-IX for power wheeled mobility systems.
Common questions about Form F00098
Who signs it?
VII: Signatures of Therapist/Physician and Qualified Rehabilitation Professional (QRP): Enter the Physician/Therapist's name*, title, signature, Date, telephone number, employer (name) and address (work or employer address). VII: Enter the QRP Name, QRP NPI, QRP Signature and Date. IX: Signatures of Therapist/Physician and Qualified Rehabilitation Professional (QRP): Enter the Physician/Therapist's name*, title, signature, Date, telephone number, employer (name) and address (work or employer address), then the QRP Name, QRP NPI, QRP Signature and Date. Signatures of Measurer and Qualified Rehabilitation Professional (QRP): Enter the Measurer's Name, Telephone number, Signature and Date, and the QRP Name, Signature and Date.
Where do I file it?
Submit the prior authorization using TMHP's PA on the Portal, or by fax to 512-514-4212. Fax requests must be scanned and data entered before the PA Department receives them, which can take up to 24 hours.
Sources
[1] Form F00098 (Rev. 07/28/2021), Wheelchair/Scooter/Stroller Seating Assessment Form (CCP/Home Health Services), Texas Medicaid & Healthcare Partnership (the Official source link on this page).