


DOH 3122 at a glance
What it is: DOH 3122 is the New York State Department of Health Assisted Living Residence Medical Evaluation.
Who signs: Name/Title of individual completing form, Date, Physician Signature and Date.
A filled-in DOH 3122 example: a pre-admission medical evaluation

How to fill out DOH 3122, box by box
Resident, exam and present home address

Enter the Resident's Name, Date of Exam, Facility Name, Date of Birth, Sex and Present Home Address (Street, City, State, Zip).
Reason for evaluation

Reason for evaluation: Pre-Admission, 12 month, Acute change in condition or Other.
Medical review findings

Vital Signs: BP, Pulse, Resp, T, Height in ft and in. and Weight.
Enter the Primary Diagnosis(s) and the Secondary Diagnosis(s).
Allergies: None or list Known Allergies.
Diet: Regular, No Added Salt, No Concentrated Sweets or Other.
Immunizations: Influenza (Date) and Pneumococcal Vaccine (Date).
TB screening

TB SCREENING (performed within 30 days prior to initial admission unless medically contraindicated)
Test is contraindicated, or Test: TST1, TST2 or TB Blood Test (Type) with Date and Result.
TST1: Date placed, Date Read and mm. TST2: Date placed, Date Read and mm.
The patient IS or IS NOT exhibiting signs or symptoms suggestive of communicable disease that could be transmitted through casual contact.
Continence

CONTINENCE Bladder: Yes or No. If no, is incontinence managed? Yes or No. Bowel: Yes or No. If no, is incontinence managed? Yes or No. If no, recommendations for management.
Laboratory services

LABORATORY SERVICES: None, or Lab Test and Reason/Frequency.
Activities of daily living (ADL's)
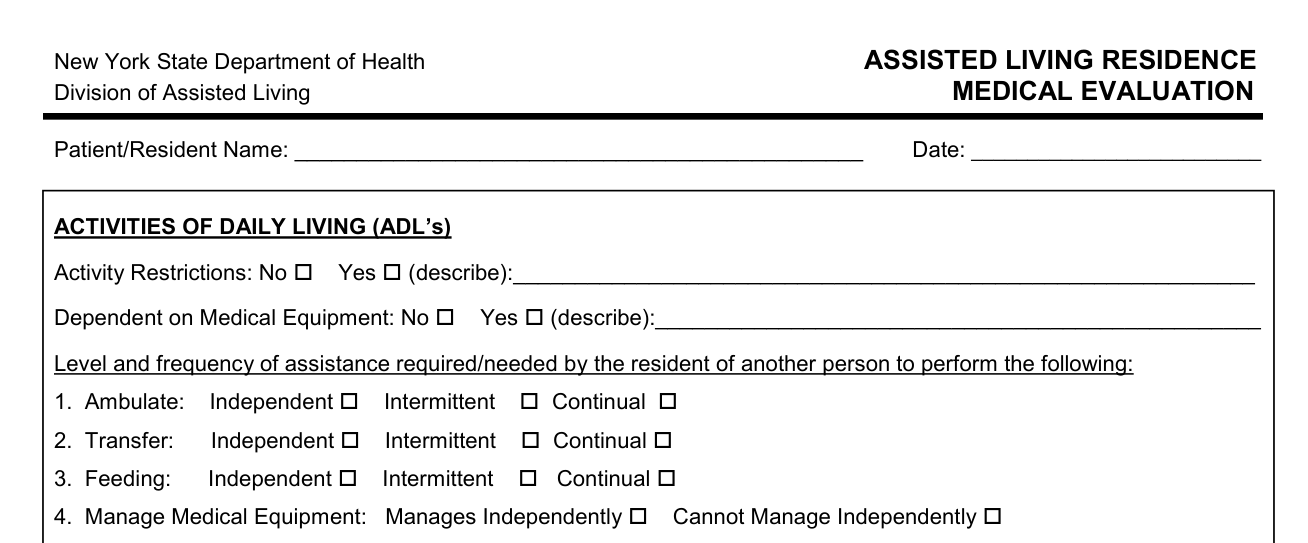
Patient/Resident Name and Date.
Activity Restrictions: No or Yes (describe).
Dependent on Medical Equipment: No or Yes (describe).
Level and frequency of assistance required/needed by the resident of another person to perform the following: Ambulate, Transfer and Feeding, each Independent, Intermittent or Continual.
Manage Medical Equipment: Manages Independently or Cannot Manage Independently.
Additional services if indicated by resident need

Pertinent medical/mental findings requiring follow-up by facility (e.g. skin conditions/acute or chronic pain issues) or any additional recommendations for follow-up: None or if yes, describe.
Therapies: None or Yes (specify): Physical Therapy, Speech Therapy or Occupational Therapy.
Home Care: None or Yes (specify), and Other (Specify).
Is Palliative Care Appropriate/Recommended: No or Yes. If yes, describe services.
Cognitive impairment/memory loss (including dementia)

Does the patient have/show signs of dementia or other cognitive impairment? No or Yes. If yes, do you recommended testing be performed? No or Yes. If yes, referral to.
If testing has already been performed, date/place of testing if known.
Mental health assessment (non-dementia)

Does the patient have a history of or a current mental disability? No or Yes. Has the patient ever been hospitalized for a mental health condition? No or Yes. If yes, describe.
Based on your examination, would you recommend the patient seek a mental health evaluation? (If yes, provide referral) No or Yes. Describe.
Medications
The patient is NOT capable of self-administration of medication if he/she needs assistance to properly carry out ONE OR MORE of the following tasks: Correctly read the label on a medication container, Correctly follow instructions as the route, time dosage and frequency, Correctly ingest, inject or apply the medication, Measure or prepare medications, including mixing, shaking and filling, Open the container, Safely store the medication and Correctly interpret the label.
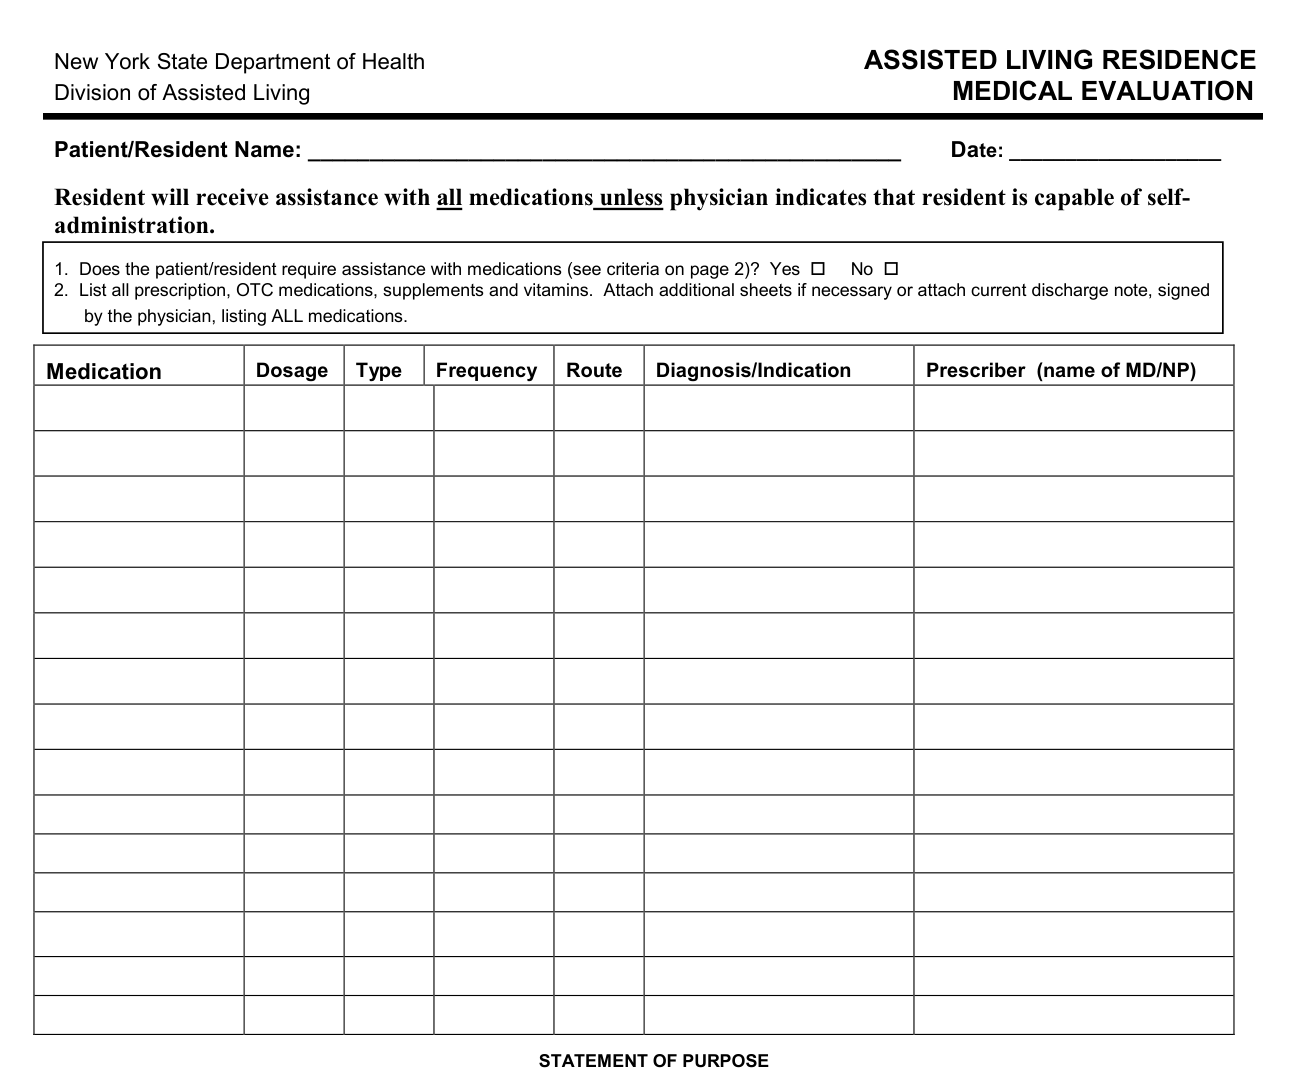
Patient/Resident Name and Date. Resident will receive assistance with all medications unless physician indicates that resident is capable of self-administration. Does the patient/resident require assistance with medications (see criteria on page 2)? Yes or No.
List all prescription, OTC medications, supplements and vitamins: Medication, Dosage, Type, Frequency, Route, Diagnosis/Indication and Prescriber (name of MD/NP).
Attach additional sheets if necessary or attach current discharge note, signed by the physician, listing ALL medications.
Physician certification

PHYSICIAN CERTIFICATION I certify that I have physically examined this patient and have accurately described the individual's medical condition, medication regimen and need for skilled and/or personal care services.
Based on this examination and my knowledge of the patient, this individual (see Statement of Purpose): Yes or No, Is mentally suited for care in an Adult Home/Enriched Housing Program/Assisted Living Residence/ Enhanced Assisted Living Residence (EALR)/Special Needs Assisted Living Residence (SNALR). Yes or No, Is medically suited for care in an Adult Home or Enriched Housing Program/Assisted Living Residence / Enhanced Assisted Living Residence (EALR)/Special Needs Assisted Living Residence (SNALR). Yes or No, Is not in need of continual acute or long term medical or nursing care, including 24-hour skilled nursing care or supervision, which would require placement in a hospital or nursing home.
Name/Title of individual completing form, Date, Physician Signature and Date.
More rules for DOH 3122
All spaces must be filled out.
Common questions about DOH 3122
What is 3122?
DOH 3122 is the New York State Department of Health Assisted Living Residence Medical Evaluation. Persons who, by reason of age and/or physical and/or mental limitations who are in need of assistance with activities of daily living, can be cared for in adult residential care settings, or if applicable, an EALR or SNALR.
When is this form not the right one?
Adult Homes, Enriched Housing Programs, Residences for Adults, Assisted Living Residences, Enhanced Assisted Living Residences and Special Needs Assisted Living Residences are not appropriate for persons in need of constant medical care and medical supervision, and these persons should not be admitted or retained in these settings because the facility lacks the staff and expertise to provide needed services.
Sources
[1] DOH 3122 (3/09) Rev. 5/12, Assisted Living Residence Medical Evaluation, New York State Department of Health (the Official source link on this page).