

Medical Benefits Request (GC-7-42) at a glance
What it is: Medical Benefits Request, Mail to: Aetna Life Insurance Company, with Medical Benefits - Claim Instructions.
Who signs: Be certain to sign the authorization to release information in block twenty-seven (27).
A filled-in Medical Benefits Request (GC-7-42) example: a member claims for a student daughter
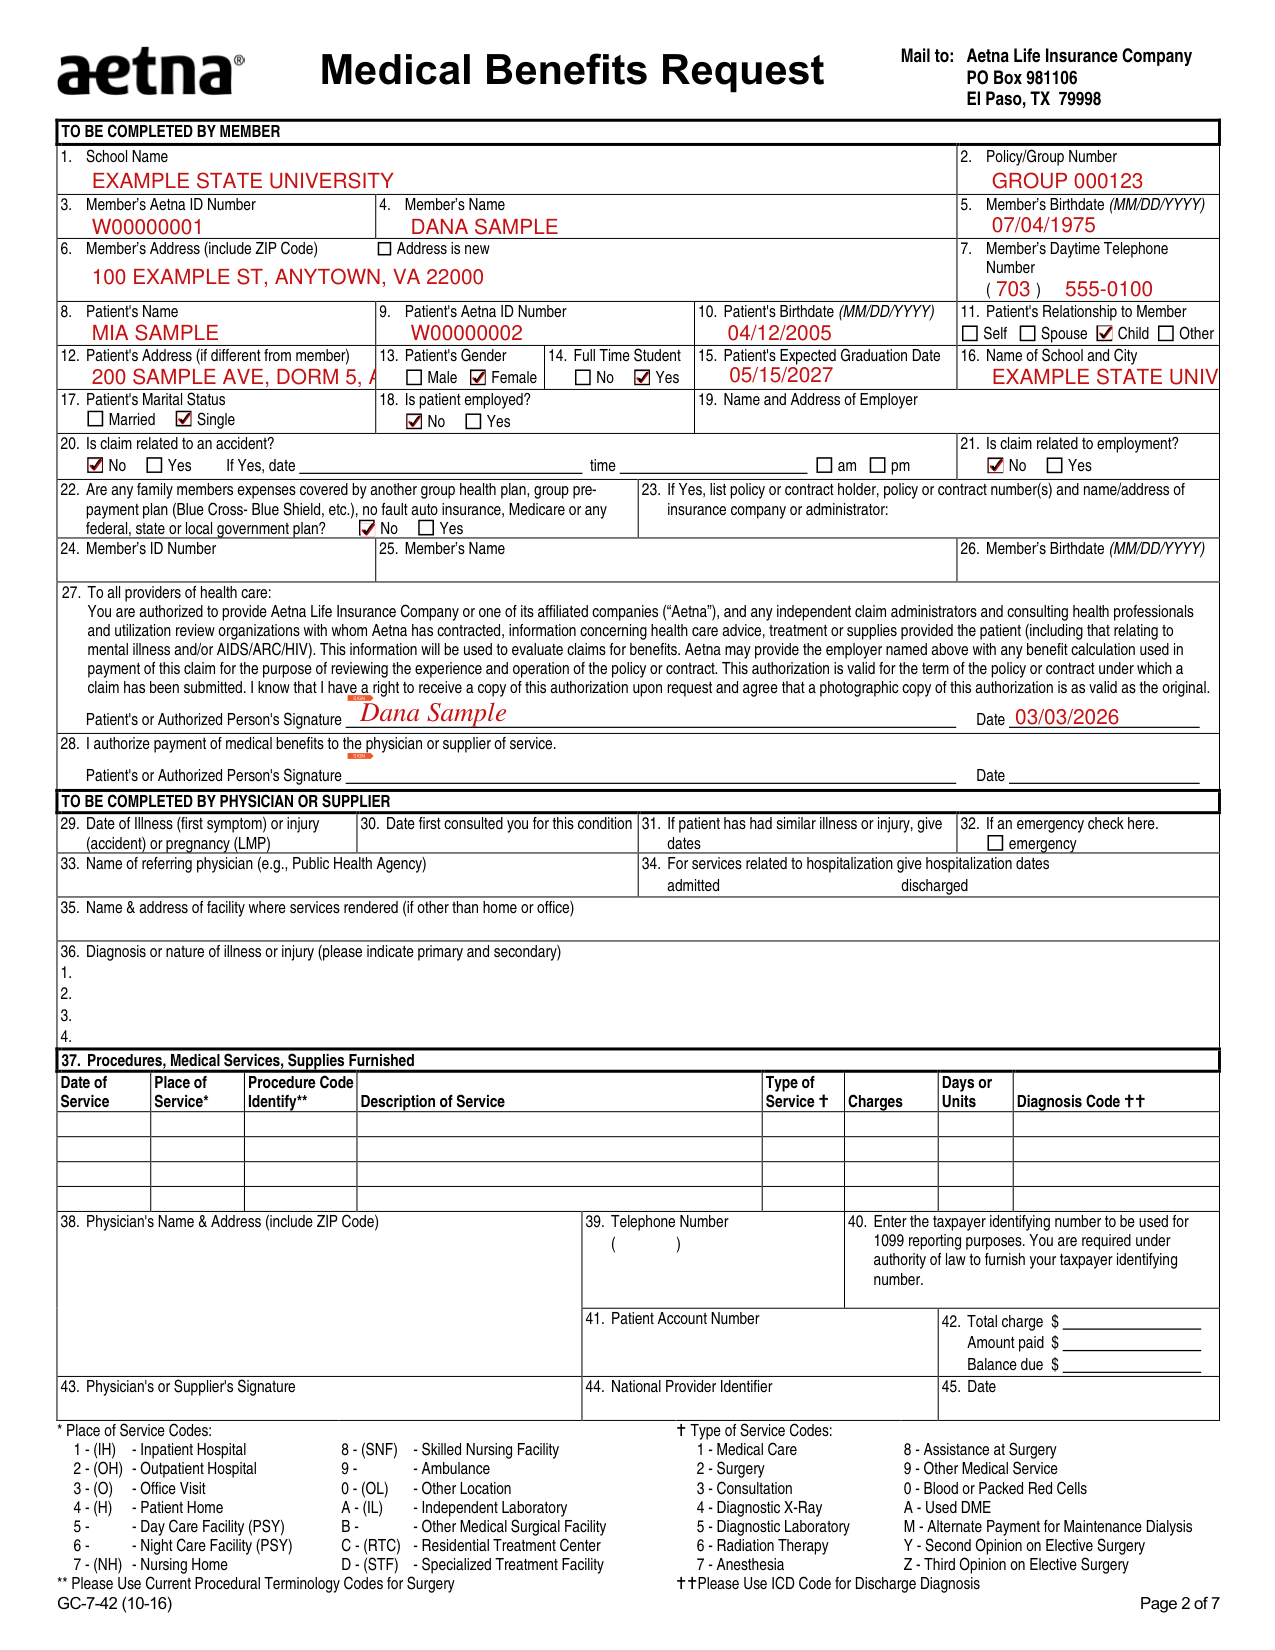
How to fill out Medical Benefits Request (GC-7-42), box by box
Member and school

Complete items one (1) through twenty-one (21) in full.
Under TO BE COMPLETED BY MEMBER, enter the School Name, the Policy/Group Number, the Member's Aetna ID Number and the Member's Name.
Enter the Member's Birthdate (MM/DD/YYYY), the Member's Address (include ZIP Code) with Address is new, and the Member's Daytime Telephone Number.
Patient, birthdate and relationship to member

Enter the Patient's Name, the Patient's Aetna ID Number and the Patient's Birthdate (MM/DD/YYYY).
Mark the Patient's Relationship to Member: Self, Spouse, Child or Other.
Patient's address, gender, student and school

Enter the Patient's Address (if different from member).
Mark the Patient's Gender: Male or Female, and Full Time Student: No or Yes.
Enter the Patient's Expected Graduation Date and the Name of School and City.
Marital status and employment

Mark the Patient's Marital Status: Married or Single.
Mark Is patient employed? No or Yes, and enter the Name and Address of Employer.
Is claim related to an accident or employment?
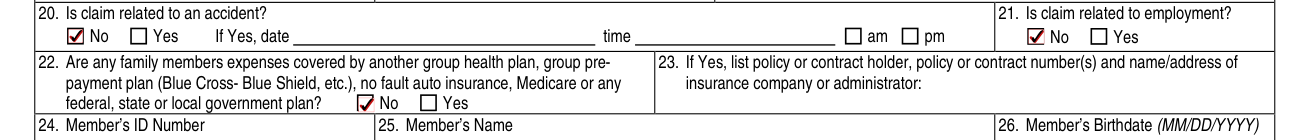
Mark Is claim related to an accident? No or Yes. If Yes, enter the date and time and mark am or pm.
Mark Is claim related to employment? No or Yes.
Other medical coverage

Complete items twenty-two (22) through twenty-six (26) only if other medical coverage exists.
Mark No or Yes: Are any family members expenses covered by another group health plan, group pre-payment plan (Blue Cross-Blue Shield, etc.), no fault auto insurance, Medicare or any federal, state or local government plan?
If Yes, list policy or contract holder, policy or contract number(s) and name/address of insurance company or administrator.
Enter the Member's ID Number, the Member's Name and the Member's Birthdate (MM/DD/YYYY).
If you have submitted a request for benefits to another plan, including Medicare, attach a copy of the bills you submitted to the other plan and the explanation of benefits you received from the other plan.
Authorization to release information

Be certain to sign the authorization to release information in block twenty-seven (27).
You are authorized to provide Aetna Life Insurance Company or one of its affiliated companies (“Aetna”), and any independent claim administrators and consulting health professionals and utilization review organizations with whom Aetna has contracted, information concerning health care advice, treatment or supplies provided the patient.
This information will be used to evaluate claims for benefits.
This authorization is valid for the term of the policy or contract under which a claim has been submitted.
Sign as the Patient's or Authorized Person's Signature and enter the Date.
Payment to the physician or supplier

If you wish to have your benefits for this claim paid directly to your physician or supplier, sign block twenty-eight (28).
I authorize payment of medical benefits to the physician or supplier of service.
More rules for Medical Benefits Request (GC-7-42)
Attach itemized bills or ask your health care provider to complete the applicable section.
Patient's name, condition being treated, type of service(s) rendered, date(s) of service(s) and relationship to member: if this information is missing, write it on the bill and sign your name.
If prescription drugs are covered under your plan, submit receipts or a Prescription Drug Record form.
Retain copies of your bills for your record.
Incomplete claim forms will be returned to you for missing information, which will delay the processing of the claim.
Aetna may provide the employer with any benefit calculation used in payment of this claim for the purpose of reviewing the experience and operation of the policy or contract.
Common questions about Medical Benefits Request (GC-7-42)
Where do I file it?
Send the completed benefits request and the bills to: Aetna Life Insurance Company PO Box 981106 El Paso, TX 79998.
Is there a penalty?
Any person who knowingly and with intent to injure, defraud or deceive any insurance company or other person files an application for insurance or statement of claim containing any materially false information or conceals, for the purpose of misleading, information concerning any fact material thereto commits a fraudulent insurance act, which is a crime and subjects such person to criminal and civil penalties.
Sources
[1] Medical Benefits Request, form GC-7-42 (10-16), Aetna Life Insurance Company (the Official source link on this page).