


AHCA Form 3110-1023 at a glance
What it is: Resident Health Assessment for Adult Family-Care Homes (AFCH): enter the Name, D.O.B., Known Allergies, Height and Weight.
Who signs: The examiner signs on the Signature of Examiner line.
A filled-in AHCA Form 3110-1023 example: a resident health assessment

How to fill out AHCA Form 3110-1023, box by box
Name, D.O.B., known allergies, height and weight

Resident Health Assessment for Adult Family-Care Homes (AFCH): enter the Name, D.O.B., Known Allergies, Height and Weight.
Health assessment
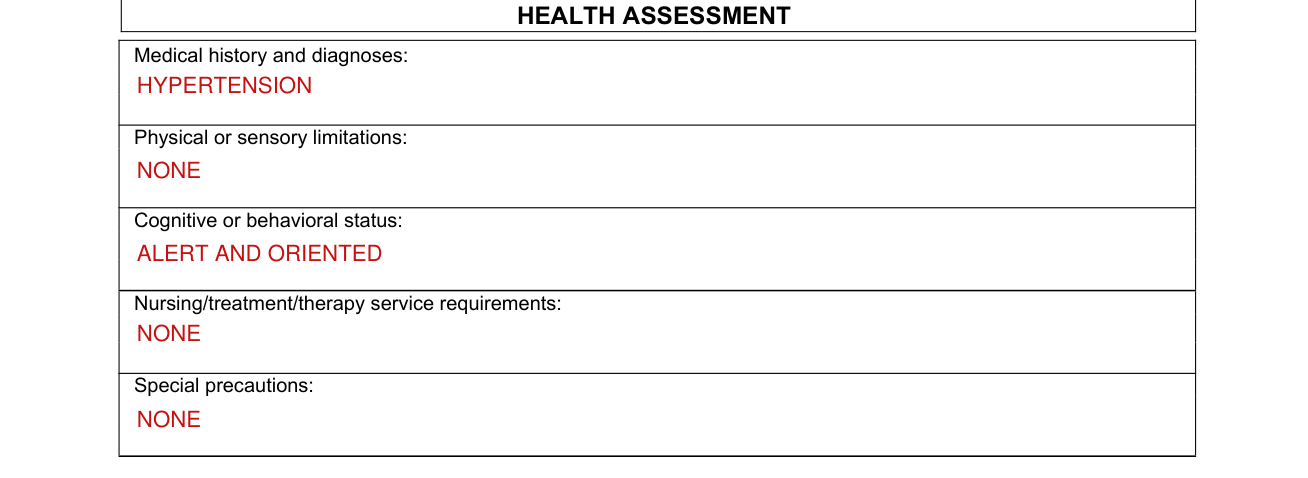
Under Health Assessment, fill in Medical history and diagnoses, Physical or sensory limitations, Cognitive or behavioral status, Nursing/treatment/therapy service requirements and Special precautions.
A: supervision or assistance

Under A, check the appropriate areas for the extent to which the individual needs supervision or assistance with Ambulation, Bathing, Dressing, Toileting, Eating, Grooming and Transferring. Use Comments if additional page is necessary.
B: other self-care tasks

Under B, check the appropriate box for the extent to which the individual is able to perform other self-care tasks such as preparing meals, shopping, or making phone calls: Independent, Needs Supervision, Needs Assistance or Needs Total Assistance.
C: general oversight

Under C, check the appropriate box for the extent to which the individual needs general oversight such as observing the individual's well-being and whereabouts and reminding the individual of important tasks: Independent, Weekly Oversight, Daily Oversight or Other. For Other, please describe.
D: special diet
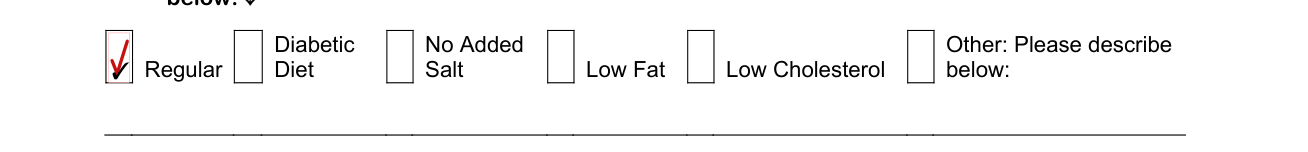
Under D, check the appropriate box if the individual requires special diet instructions: Regular, Diabetic Diet, No Added Salt, Low Fat, Low Cholesterol or Other. For Other, please describe. Under E, list all current medications prescribed (additional pages may be attached).
E: medications
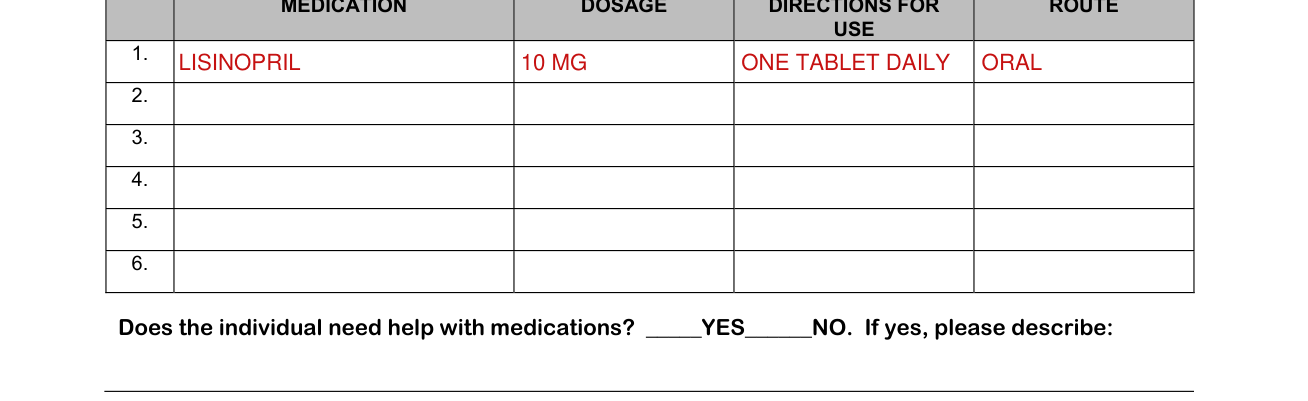
Enter the Medication, Dosage, Directions for Use and Route.
Does the individual need help with medications? Mark YES or NO. If yes, please describe.
F: conditions or requirements
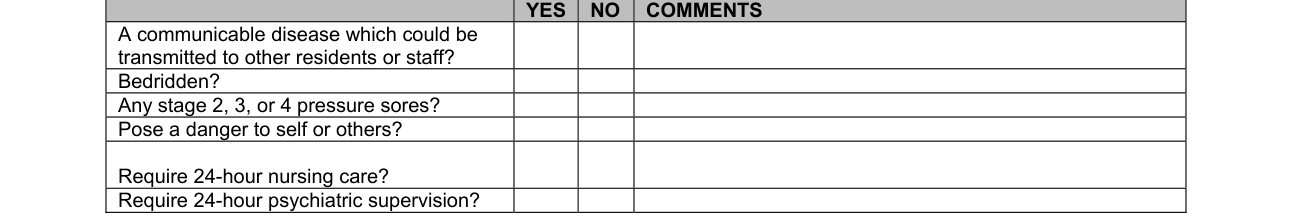
Under F, does the individual have any of the following conditions or requirements? Check the appropriate boxes YES or NO and add COMMENTS. First: a communicable disease which could be transmitted to other residents or staff?
Also under F, check YES or NO for: Bedridden, Any stage 2, 3, or 4 pressure sores, Pose a danger to self or others, Require 24-hour nursing care and Require 24-hour psychiatric supervision.
G and H: your professional opinion

Under G, in your professional opinion, can this individual's needs be met in a residential facility (Adult Family Care Home) that is not a medical, nursing or psychiatric facility? Mark YES or NO. Use Comments if additional page is necessary.
Under H, in your professional opinion, based on this individual's medical profile, can this individual be left without supervision at the adult family care home for up to two hours per twenty-four (24) hour period without compromising his or her health, safety, security or well-being? Mark YES or NO.
The examiner
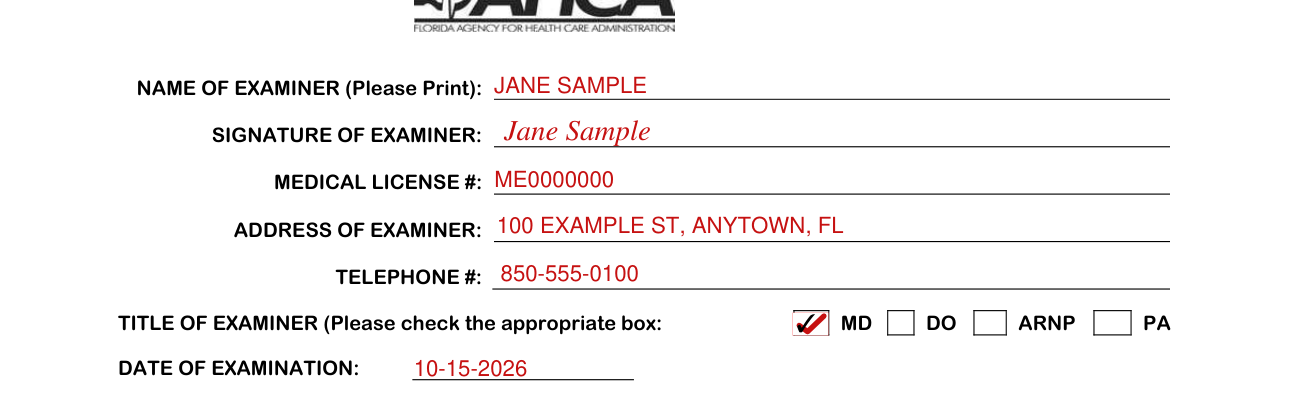
Print the Name of Examiner, then enter the Medical License #, the Address of Examiner and the Telephone #.
Check the appropriate box for the Title of Examiner: MD, DO, ARNP or PA. Enter the Date of Examination.
Return the completed form to
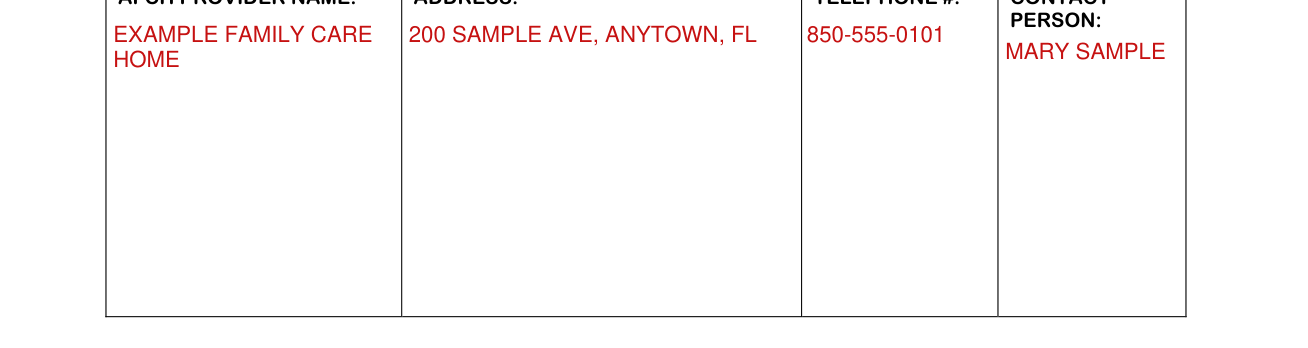
Please return the completed form to the AFCH Provider Name, with the Address, Telephone # and Contact Person.
Sources
[1] AHCA Form 3110-1023 (AFCH-1110) 01/08, Resident Health Assessment for Adult Family-Care Homes (AFCH), Agency for Health Care Administration (the Official source link on this page).