

WCC Form 2 at a glance
What it is: WCC Form 2 is the State of Alabama Employer's First Report of Injury or Occupational Disease.
The employer: WCC Form 2 is the State of Alabama Employer's First Report of Injury or Occupational Disease, and the use of this form is required under the provisions of the Alabama Workmen's Compensation Law.
A filled-in WCC Form 2 example: an employer reports a roofer's fall

How to fill out WCC Form 2, box by box
Claim reference and employer
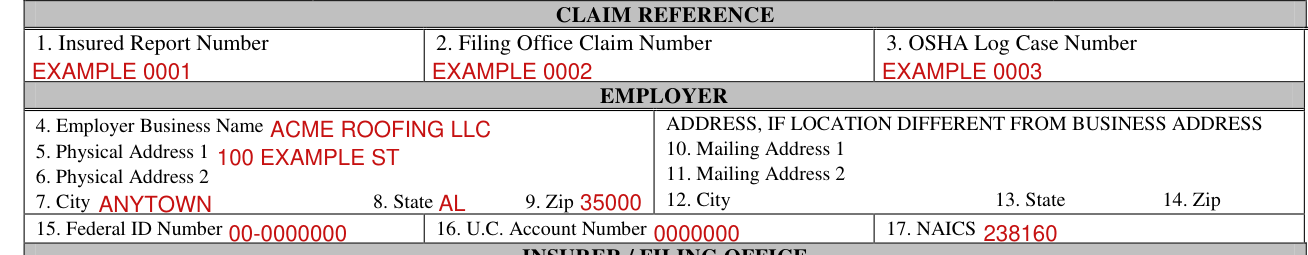
Enter the Insured Report Number in Box 1, the Filing Office Claim Number in Box 2 and the OSHA Log Case Number in Box 3.
Under EMPLOYER, enter the Employer Business Name in Box 4, the Physical Address in Boxes 5 and 6, and the City, State and Zip in Boxes 7, 8 and 9.
If the location is different from the business address, enter the Mailing Address in Boxes 10 and 11, and the City, State and Zip in Boxes 12, 13 and 14.
Enter the Federal ID Number in Box 15, the U.C. Account Number in Box 16 and the NAICS in Box 17.
Insurer / filing office

Under INSURER / FILING OFFICE, enter the Insurer Name in Box 18 and the Insurer Federal ID Number in Box 19, and in Box 20 mark the Type Insurer: Ins Co, Self-Insurer or Group Fund.
Enter the Filing Office Name in Box 21, the Mailing Address in Boxes 22 and 23 (Box 23 is Mailing Address 2 or Telephone Number), the City, State and Zip in Boxes 24, 25 and 26, and the Filing Office Federal ID Number in Box 27.
Employee / wages
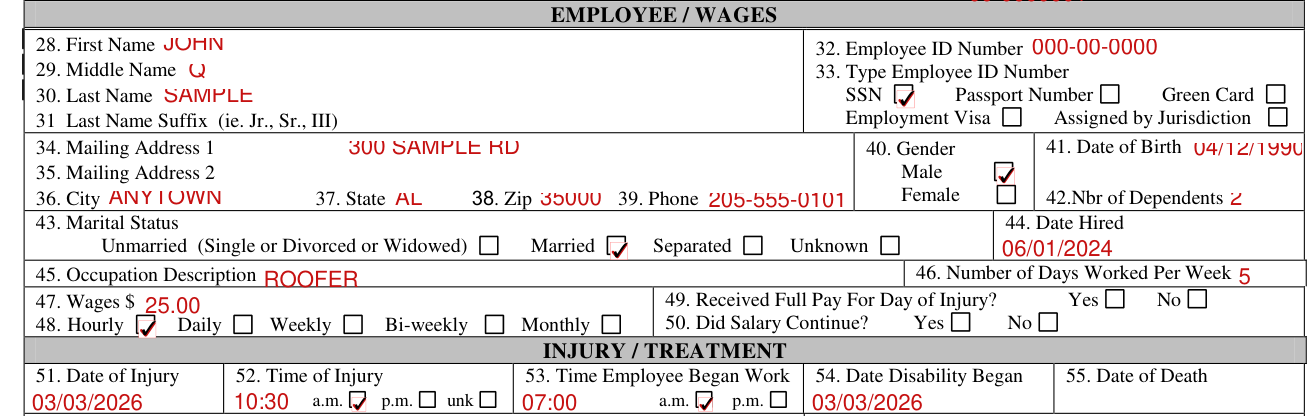
Under EMPLOYEE / WAGES, enter the First Name in Box 28, the Middle Name in Box 29, the Last Name in Box 30 and the Last Name Suffix (ie. Jr., Sr., III) in Box 31.
Enter the Employee ID Number in Box 32, and in Box 33 mark the Type Employee ID Number: SSN, Passport Number, Green Card, Employment Visa or Assigned by Jurisdiction.
Enter the Mailing Address in Boxes 34 and 35, the City, State and Zip in Boxes 36, 37 and 38, and the Phone in Box 39.
In Box 40 mark the Gender, Male or Female; enter the Date of Birth in Box 41 and the Nbr of Dependents in Box 42; and in Box 43 mark the Marital Status: Unmarried (Single or Divorced or Widowed), Married, Separated or Unknown.
Enter the Date Hired in Box 44, the Occupation Description in Box 45, the Number of Days Worked Per Week in Box 46 and the Wages $ in Box 47, and in Box 48 mark Hourly, Daily, Weekly, Bi-weekly or Monthly.
Injury / treatment

In Box 49 mark Yes or No for Received Full Pay For Day of Injury?, in Box 50 mark Yes or No for Did Salary Continue?, and enter the Date of Injury in Box 51.
In Box 52, enter the Time of Injury and mark a.m., p.m. or unk.
In Box 53, enter the Time Employee Began Work and mark a.m. or p.m.
Enter the Date Disability Began in Box 54.
Enter the Date of Death in Box 55.
Place of accident, injury, or exposure

Under PLACE OF ACCIDENT, INJURY, OR EXPOSURE, enter the Site Address in Box 56, the City in Box 57, the State in Box 58, the Zip in Box 59 and the County in Box 60.
In Box 61 mark Yes or No for Injury Occurred on Employer's Premises?, and enter the Date Employer Notified in Box 62.
In Box 63, describe what the employee was doing just before the incident and how the injury occurred, as in the example: While climbing a ladder and carrying roofing materials, ladder slipped on wet floor causing worker to fall 20 feet.
Provide description codes and initial treatment
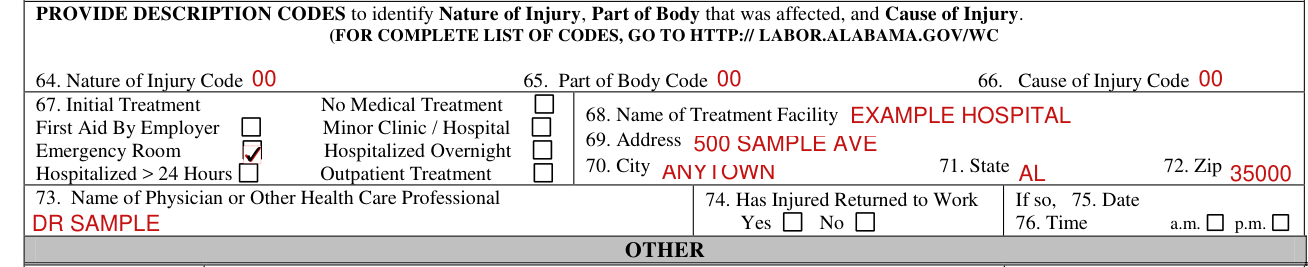
Provide Description Codes to identify Nature of Injury, Part of Body that was affected, and Cause of Injury: enter the Nature of Injury Code in Box 64, the Part of Body Code in Box 65 and the Cause of Injury Code in Box 66. For the complete list of codes, go to HTTP:// LABOR.ALABAMA.GOV/WC.
In Box 67, the Initial Treatment, mark No Medical Treatment, First Aid By Employer, Minor Clinic / Hospital, Emergency Room, Hospitalized Overnight, Hospitalized > 24 Hours or Outpatient Treatment.
Enter the Name of Treatment Facility in Box 68, the Address in Box 69, the City in Box 70, the State in Box 71 and the Zip in Box 72.
Enter the Name of Physician or Other Health Care Professional in Box 73.
Has Injured Returned to Work

In Box 74 mark Yes or No for Has Injured Returned to Work; if so, enter the Date in Box 75 and the Time in Box 76, a.m. or p.m.
Date Prepared and Preparer

Enter the Date Prepared in Box 77, then the Preparer's First Name in Box 78, the Last Name in Box 79 and the Title in Box 80.
Enter the Preparer's Telephone Number in Box 81.
Sources
[1] WCC Form 2 (Rev. 10/2012), Employer's First Report of Injury or Occupational Disease, Alabama Department of Labor (the Official source link on this page).
