


CFS 602 at a glance
What it is: CFS 602 is the State of Illinois Department of Children and Family Services Medical Report on an Adult in a Child Care Facility.
Who signs: The physician signs at Physician's Signature.
A filled-in CFS 602 example: a physician reports on a child care staff member

How to fill out CFS 602, box by box
Name of Person Examined, Birth Date and Position

It includes employees and volunteers in DCFS licensed child care facilities, operators of day care/group day care homes and other adult members of their households.
Enter the Name of Person Examined.
Enter the Birth Date, then check one Position: Day Care/Group Day Care Home Caregiver, Food Handler (See Section B), Child Care Staff, Child Care Facility Driver (See Section B), Other Staff in a Child Care Facility, Volunteer in a Child Care Facility or Member of Household.
Name of Licensee/applicant for License or Licensed Facility, Address and I. TESTS

Enter the Name of Licensee/applicant for License or Licensed Facility where individual is employed/volunteers, and the Address: Street, City, Zip Code, County. Under I. TESTS, enter the Date and Results of the Tuberculin test (by the Mantoux method or chest X-ray in a positive reactor) and of Other (specify). Required in initial examination only. Physician to determine need for test in subsequent examinations.
II. IMMUNIZATIONS

Under II. IMMUNIZATIONS, mark Yes or No for: I have discussed the importance of immunizations for adult child care providers with this individual and recommend the following immunizations; if this individual is employed in a child care facility that cares for children age 6 and under, please check two of the following: This individual has received: 1 dose of the Tdap vaccine, 2 doses of the MMR vaccine or is immune to MMR. This individual is not medically indicated for: 1 dose of the Tdap vaccine, 2 doses of the MMR vaccinations.
A. Findings

Under III. FINDINGS AND RECOMMENDATIONS, A. Findings, enter a summary of medical or emotional problems or conditions, if any, which may affect the individual's ability to work, volunteer or reside in a facility caring for children.
B. Any conditions which contraindicate a person serving as a Food Handler or Child Care Facility Driver? and C. Recommendations

B. Any conditions which contraindicate a person serving as a Food Handler or Child Care Facility Driver? Mark Yes or No. If yes, please specify.
C. Recommendations: mark Yes or No. The individual was found free from symptoms of communicable disease and is otherwise medically and emotionally fit to work, volunteer or reside in a facility caring for children. Explain "No".
In my opinion, the individual could meet the strength and mobility challenges required for caring for a child in one or more of the age groups checked: 0-2 years of age, 2-6 years of age, 7-12 years of age, 12-18 years of age.
Date of Examination, Physician's Name, Signature and Address
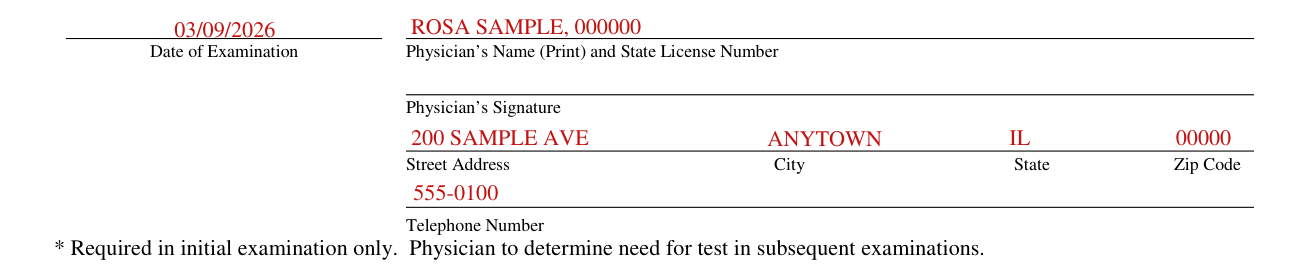
Enter the Date of Examination, the Physician's Name (Print) and State License Number, and the Street Address, City, State, Zip Code.
The physician signs at Physician's Signature.
REEXAMINATIONS

Under REEXAMINATIONS, enter the Date of Examination and the Physician's Name (Print) and State License Number.
Sources
[1] CFS 602 Rev. 03/2016, Medical Report on an Adult in a Child Care Facility, State of Illinois Department of Children and Family Services (the Official source link on this page).