
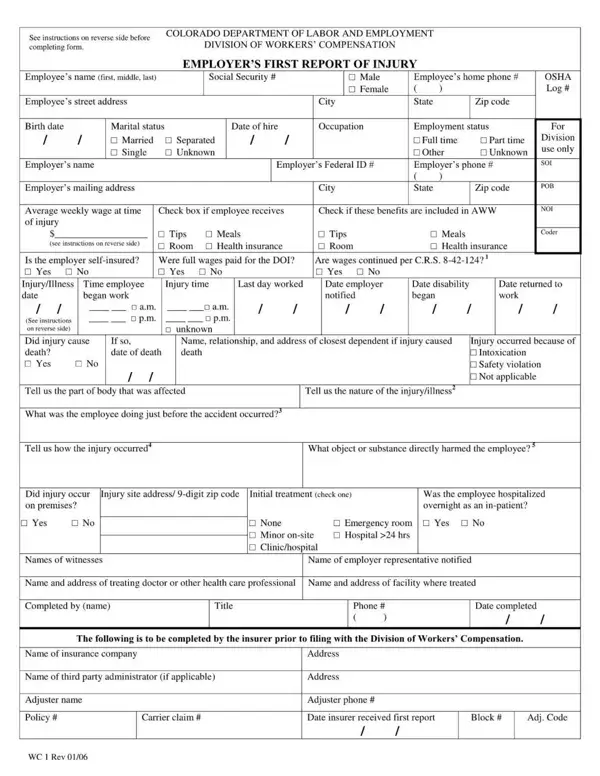

Colorado WC 1 at a glance
What it is: The Colorado Division of Workers' Compensation Employer's First Report of Injury contains all items requested on OSHA Form No. 301, "Injuries & Illnesses Incident Report".
A filled-in Colorado WC 1 example: an employer reports a back strain
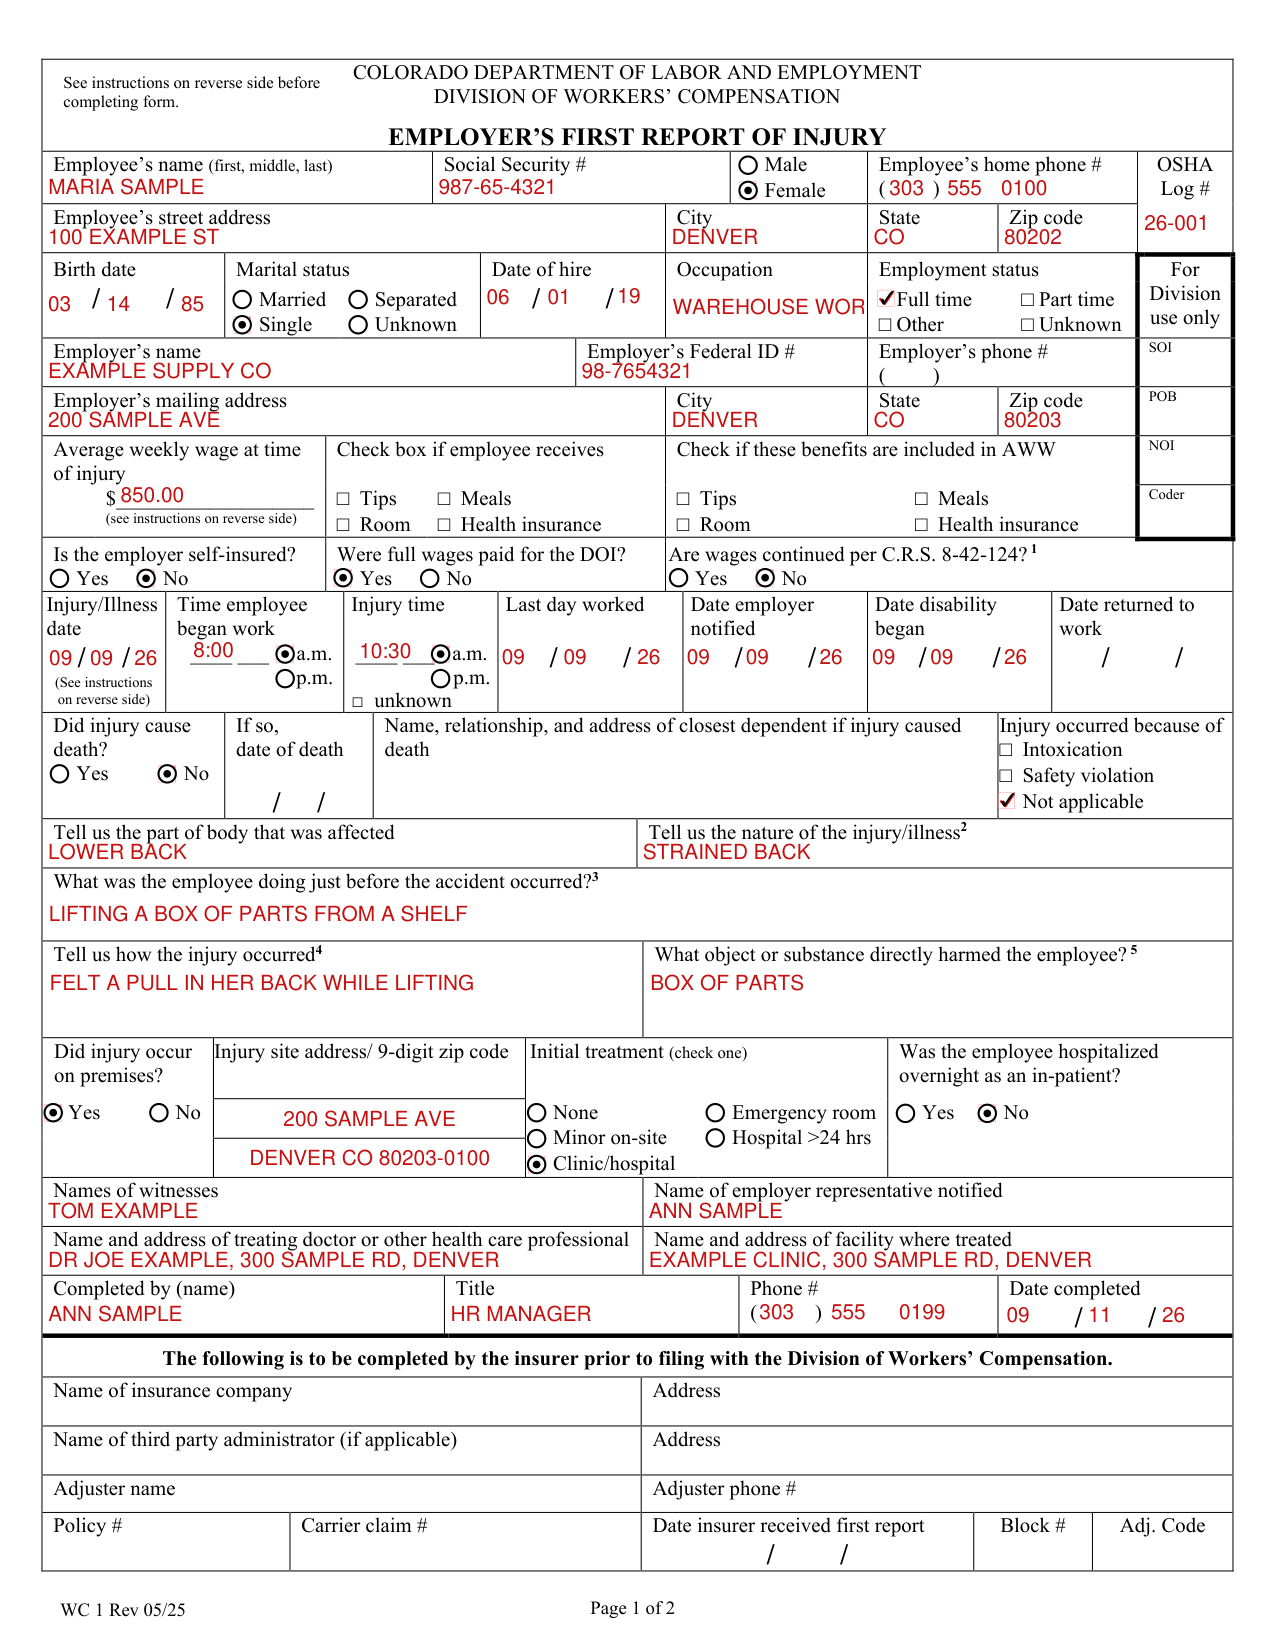
How to fill out Colorado WC 1, box by box
Employee's name, Social Security #, home phone and address

Enter the Employee's name (first, middle, last), Social Security # and Employee's home phone #, and mark Male or Female.
Enter the OSHA Log #, the Employee's street address, City, State and Zip code.
Birth date, Marital status, Date of hire, Occupation and Employment status

Enter the Birth date and the Date of hire.
Under Marital status, mark Married, Separated, Single or Unknown.
Enter the Occupation. Under Employment status, mark Full time, Part time, Other or Unknown.
Employer's name, Federal ID #, phone # and mailing address

Enter the Employer's name, Employer's Federal ID #, Employer's phone # and Employer's mailing address with City, State and Zip code.
Average weekly wage at time of injury
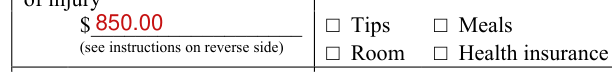
Enter the Average weekly wage at time of injury (see instructions on reverse side).
Calculation of Average Weekly Wage: Determine the weekly wage rate.
Add the average weekly amount of any overtime wages, tips or commissions.
Add the average weekly value of any board, rent, housing, or lodging provided by the employer if the employer will not be paying such benefit during the period of disability.
If the employee is covered by group health insurance and the employer does not continue the employee's health insurance coverage during the period of disability, add the employee's cost of conversion to a similar or lesser insurance plan and include this cost in the average weekly wage computation.
Compute the total from these categories and insert in the Average weekly wage at time of injury field.
Check box if employee receives and Check if these benefits are included in AWW

Check box if employee receives: Tips, Meals, Room, Health insurance.
Check if these benefits are included in AWW: Tips, Meals, Room, Health insurance.
Self-insured, full wages paid and wages continued
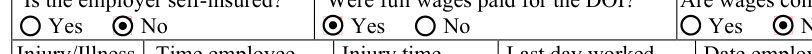
Is the employer self-insured? Mark Yes or No.
Were full wages paid for the DOI? Mark Yes or No.
Are wages continued per C.R.S. 8-42-124? Mark Yes or No.
Injury/Illness date, Time employee began work and Injury time
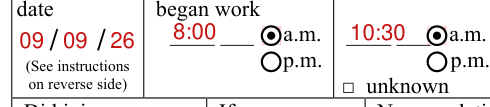
Enter the Injury/Illness date.
In the case of an occupational disease, use the date of the last injurious exposure.
Enter the Time employee began work and the Injury time.
Last day worked, Date employer notified, Date disability began and Date returned to work

Enter the Last day worked, the Date employer notified, the Date disability began and the Date returned to work if the employee has returned to work.
Did injury cause death? and the closest dependent

Did injury cause death? Mark Yes or No. If so, enter the date of death and the Name, relationship, and address of closest dependent if injury caused death.
Injury occurred because of

Injury occurred because of: Intoxication, Safety violation or Not applicable.
Injury description: part of body, nature, activity, how and object
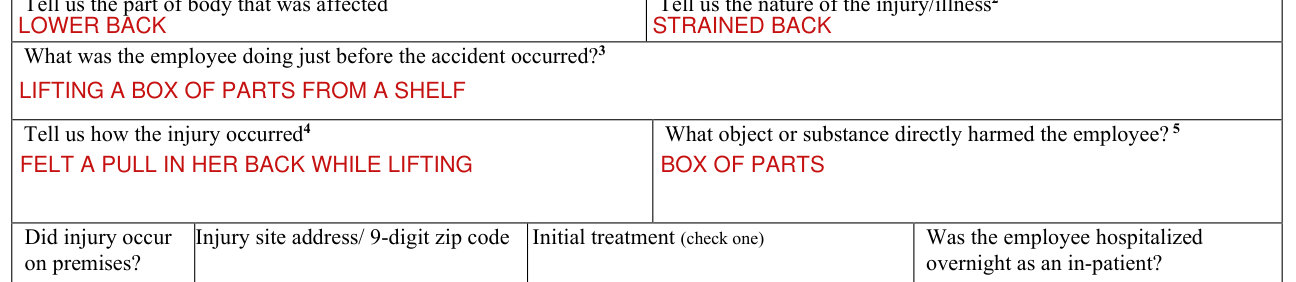
The part of body that was affected.
The nature of the injury/illness.
Examples: "strained back"; "chemical burn, hand"; "carpal tunnel syndrome."
What was the employee doing just before the accident occurred?3 Describe the activity, as well as the tools, equipment or material the employee was using. Be specific.
Examples: "climbing a ladder while carrying roofing materials"; "spraying chlorine from hand sprayer"; or "daily computer key-entry."
How the injury occurred.4
Examples: "When ladder slipped on wet floor, worker fell 20 feet"; "Worker was sprayed with chlorine when gasket broke during replacement"; "Worker developed soreness in wrist over time."
What object or substance directly harmed the employee?5 Examples: "concrete floor"; "chlorine"; "radial arm saw."
Did injury occur on premises?, Injury site address and Initial treatment
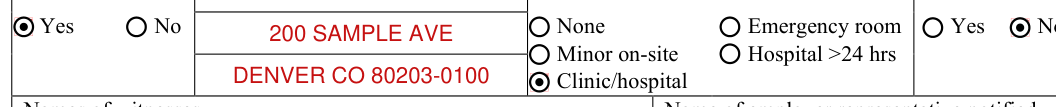
Did injury occur on premises? Mark Yes or No.
Enter the Injury site address/ 9-digit zip code.
Initial treatment (check one): None, Emergency room, Minor on-site, Hospital >24 hrs or Clinic/hospital.
Was the employee hospitalized overnight as an in-patient? Mark Yes or No.
Names of witnesses and Name of employer representative notified

Enter the Names of witnesses and the Name of employer representative notified.
Name and address of treating doctor and of facility where treated

Enter the Name and address of treating doctor or other health care professional and the Name and address of facility where treated.
The employer has the right in the first instance, to select the physician who attends the injured employee.
Completed by (name), Title, Phone # and Date completed

Enter Completed by (name), Title, Phone # and Date completed.
For Division use only
For Division use only.
To be completed by the insurer
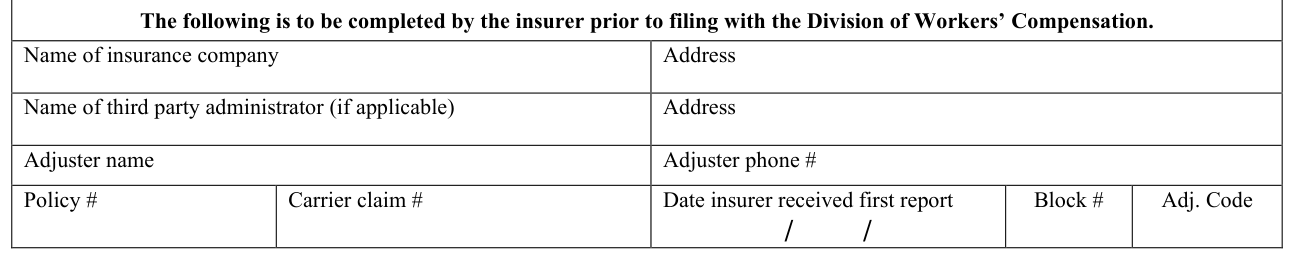
The following is to be completed by the insurer prior to filing with the Division of Workers' Compensation.
More rules for Colorado WC 1
Forms should be typed or printed legibly.
All questions must be answered completely to meet requirements of the Colorado Workers' Compensation Act and to conform to the OSHA requirements for Form No. 301.
Fatalities must be reported to your insurance carrier immediately.
All injuries no matter how trivial must be reported to your insurance company.
Section 10-1-128 states: "It is unlawful to knowingly provide false, incomplete, or misleading facts or information to an insurance company for the purposes of defrauding or attempting to defraud the company.
Penalties may include imprisonment, fines, denial of insurance, and civil damages.
Common questions about Colorado WC 1
Is there a deadline?
All injuries or occupational diseases which result in lost time from work in excess of three shifts or calendar days, or in permanent physical impairment, must be reported to your insurance carrier on this form within ten days after notice or knowledge of the injury or disease.
Sources
[1] Colorado WC 1 (Rev 05/25), Employer's First Report of Injury, Colorado Division of Workers' Compensation (the Official source link on this page).