Contact Lense Prescription Form PDF Details

Fulfilling a need for vision correction, the Illinois Department of Healthcare and Family Services presents a structured approach through its Optical Prescription Order form, ensuring detailed information from healthcare providers is captured efficiently. This document, pivotal for accurately dispensing corrective lenses, demands comprehensive data ranging from provider details, patient identification, to intricate specifications of the prescribed contact lenses. It highlights the provider's name and National Provider Identifier (NPI), alongside the date of service (DOS) and contact information, ensuring a clear linkage between the prescription and the medical professional. The form delves into the heart of optical correction by detailing patient-specific requirements such as power, prism, pupillary distance, and base curve for both eyes, thereby tailoring the prescription to individual needs. Further, it accommodates choices in lens and frame materials, with options like glass, plastic, and polycarbonate, and frames made from plastic or metal, considering the wearer's comfort and lifestyle. Notable also is the call for a signature from the provider, a testament to the accuracy and completeness of the information provided, underscoring the commitment to comply with state and federal guidelines in healthcare provision. This document, therefore, not only facilitates the precise creation and dispensing of eyewear but also adheres to regulatory standards aimed at protecting patient welfare in the realm of vision care.

QuestionAnswer
Form NameContact Lense Prescription Form
Form Length1 pages
Fillable?No
Fillable fields0
Avg. time to fill out15 sec
Other namescontact lens prescription pdf, contact lense prescription, blank contact lens prescription form, blank contact prescription form

How to Fill Out Form HFS 2803

Form HFS 2803 at a glance

What it is: HFS 2803 is the Illinois Department of Healthcare and Family Services OPTICAL PRESCRIPTION ORDER with a Document Control Number.

Who signs: Sign, then enter the Signature Date.

A filled-in Form HFS 2803 example: a provider fills out an optical prescription order
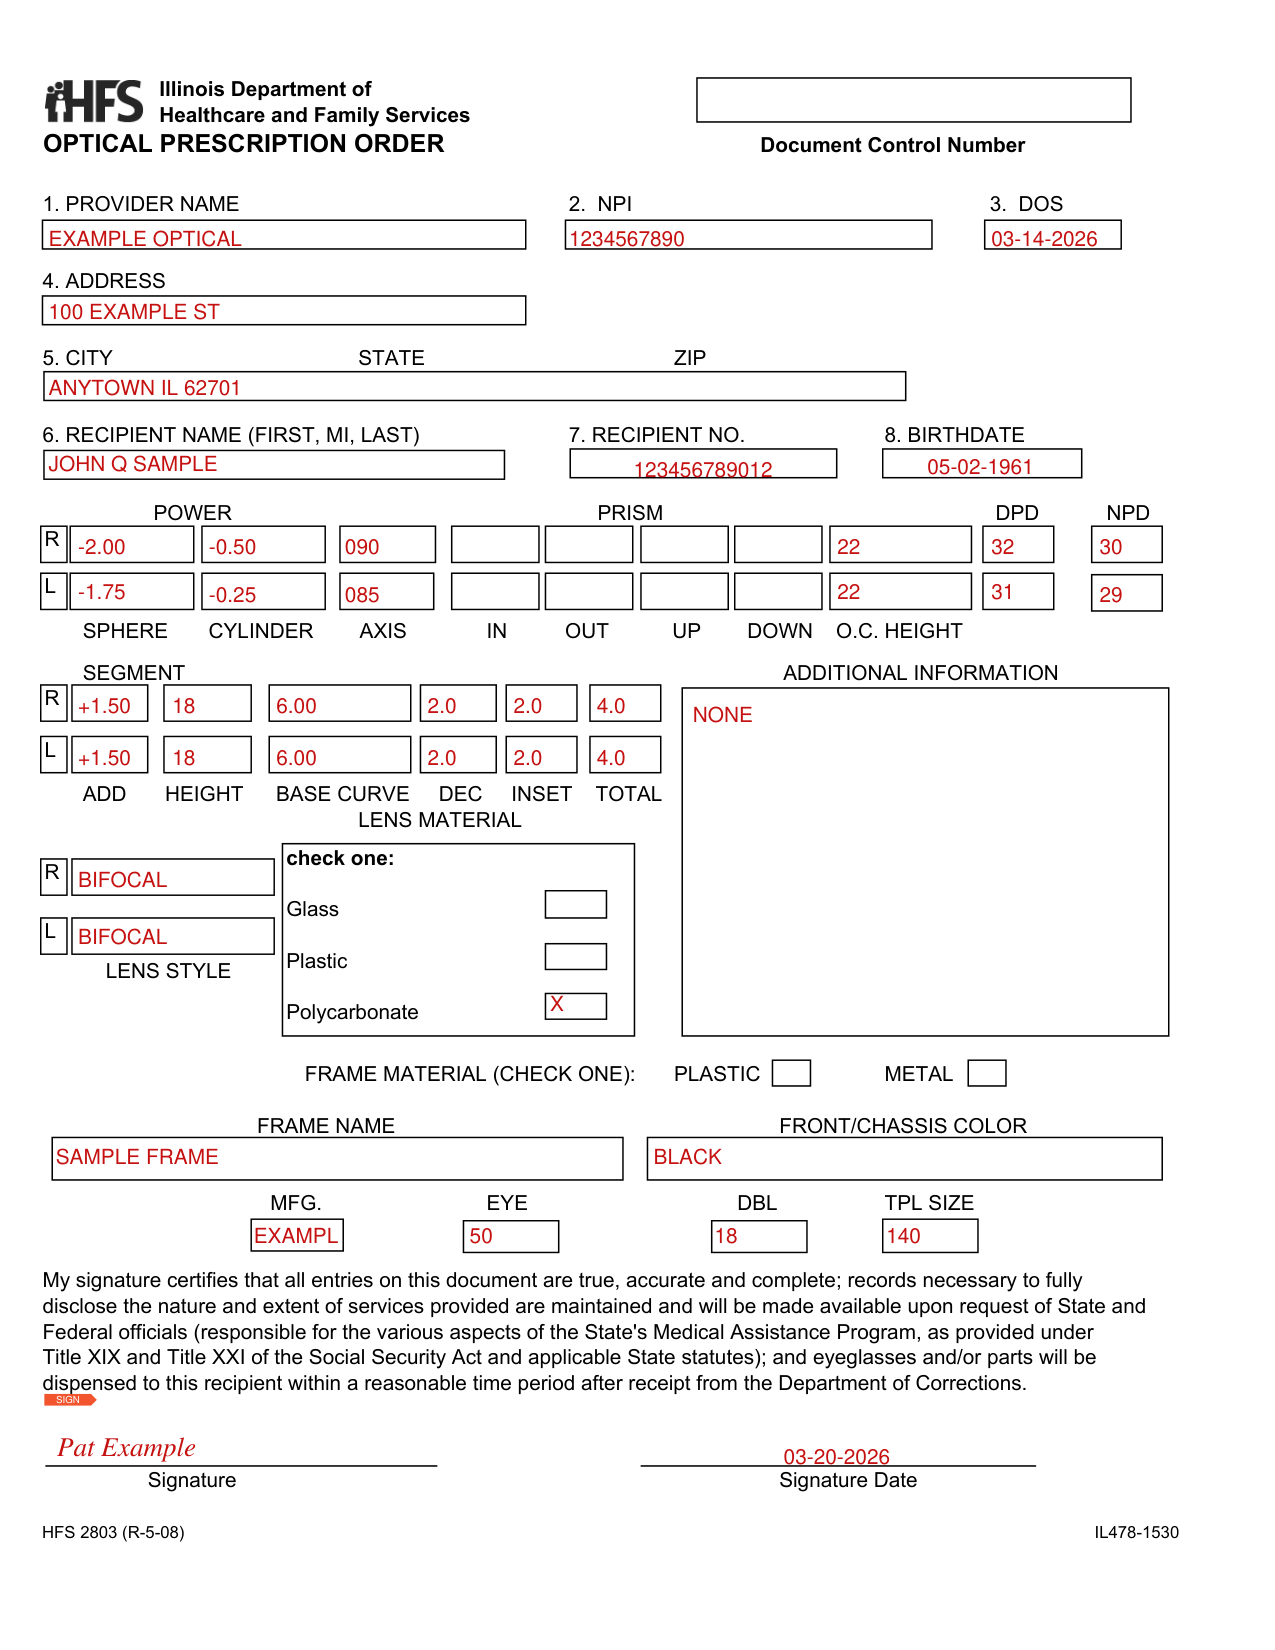
Form HFS 2803 example filled out, example: a provider fills out an optical prescription order
A provider fills out an optical prescription order for one recipient. The recipient needs polycarbonate bifocal lenses, so the LENS STYLE boxes say BIFOCAL and the SEGMENT boxes are filled for both eyes. The recipient needs no prism, so PRISM stays empty. The provider signs the order. The picture shows page 1, and none of its entries is real.

How to fill out Form HFS 2803, box by box

PROVIDER NAME, NPI and DOS

Form HFS 2803 example filled out, pROVIDER NAME, NPI and DOS

Enter the PROVIDER NAME in Box 1, the NPI in Box 2 and the DOS in Box 3.

ADDRESS and CITY STATE ZIP
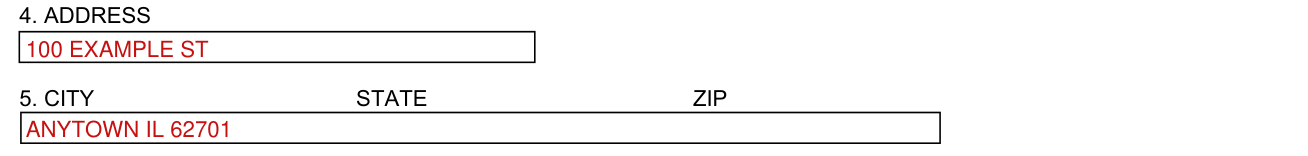
Form HFS 2803 example filled out, aDDRESS and CITY STATE ZIP

Enter the ADDRESS in Box 4 and the CITY STATE ZIP in Box 5.

RECIPIENT NAME, RECIPIENT NO. and BIRTHDATE

Form HFS 2803 example filled out, rECIPIENT NAME, RECIPIENT NO. and BIRTHDATE

Enter the RECIPIENT NAME (FIRST, MI, LAST) in Box 6, the RECIPIENT NO. in Box 7 and the BIRTHDATE in Box 8.

POWER
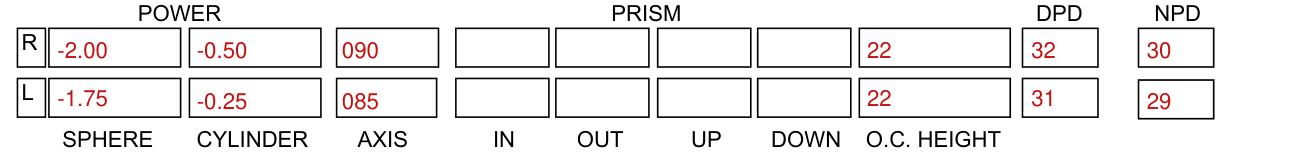
Form HFS 2803 example filled out, pOWER

For R and L, enter the POWER: SPHERE, CYLINDER and AXIS.

PRISM
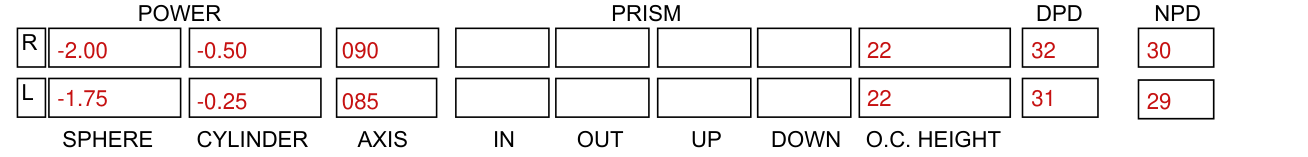
Form HFS 2803 example filled out, pRISM

For R and L, enter the PRISM: IN, OUT, UP and DOWN.

O.C. HEIGHT, DPD and NPD
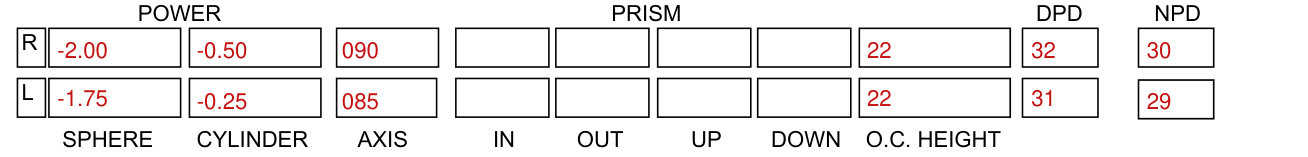
Form HFS 2803 example filled out, o.C. HEIGHT, DPD and NPD

For R and L, enter the O.C. HEIGHT, the DPD and the NPD.

SEGMENT, BASE CURVE, DEC, INSET and TOTAL
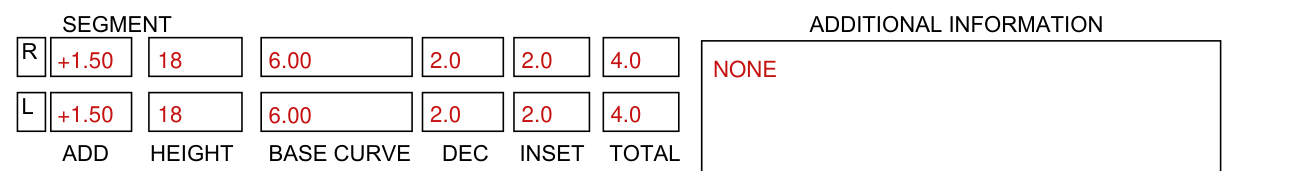
Form HFS 2803 example filled out, sEGMENT, BASE CURVE, DEC, INSET and TOTAL

For R and L, enter the SEGMENT ADD and HEIGHT, the BASE CURVE, the DEC, the INSET and the TOTAL.

ADDITIONAL INFORMATION
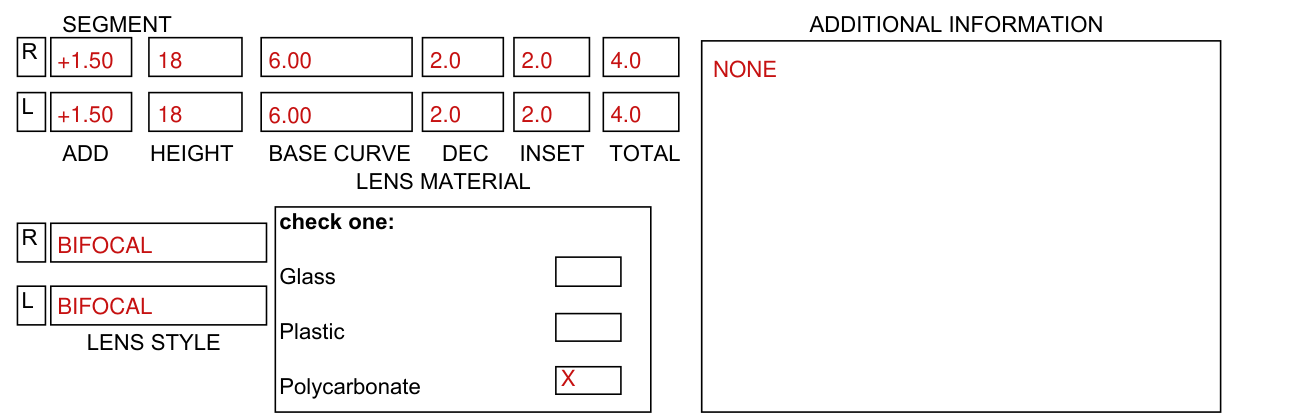
Form HFS 2803 example filled out, aDDITIONAL INFORMATION

Enter the ADDITIONAL INFORMATION.

LENS STYLE
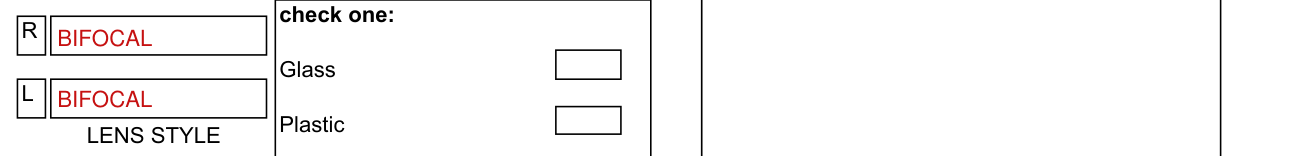
Form HFS 2803 example filled out, lENS STYLE

Enter the LENS STYLE for R and L.

LENS MATERIAL
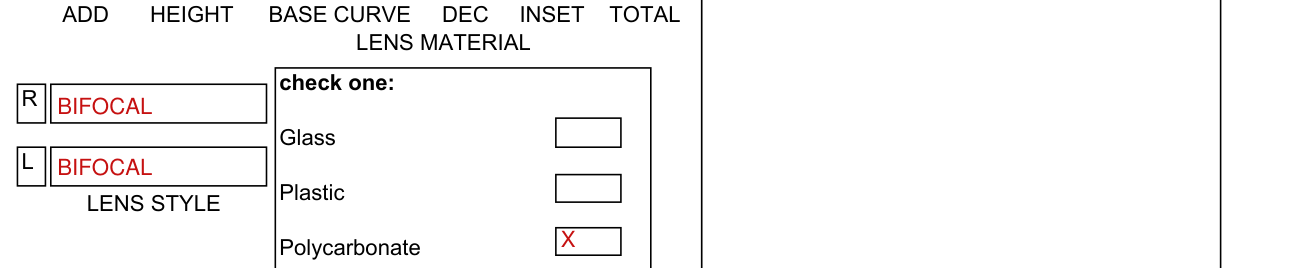
Form HFS 2803 example filled out, lENS MATERIAL

Check one: Glass, Plastic or Polycarbonate.

FRAME NAME, FRONT/CHASSIS COLOR, MFG., EYE, DBL and TPL SIZE
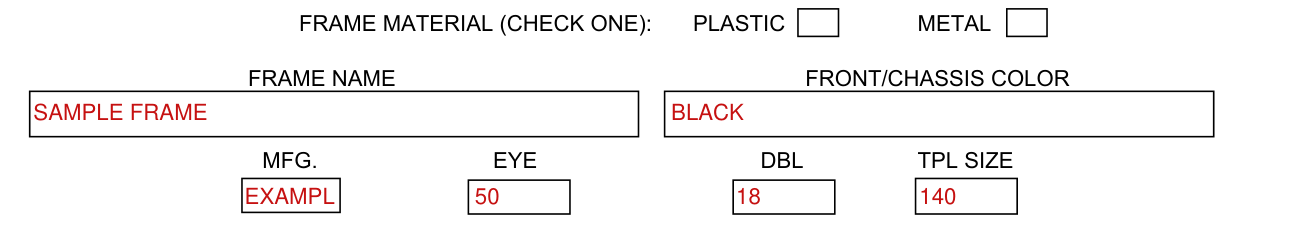
Form HFS 2803 example filled out, fRAME NAME, FRONT/CHASSIS COLOR, MFG., EYE, DBL and TPL SIZE

Enter the FRAME NAME, the FRONT/CHASSIS COLOR, the MFG., the EYE, the DBL and the TPL SIZE.

Signature

Form HFS 2803 example filled out, signature

The signature certifies that all entries on this document are true, accurate and complete; records necessary to fully disclose the nature and extent of services provided are maintained and will be made available upon request of State and Federal officials (responsible for the various aspects of the State's Medical Assistance Program, as provided under Title XIX and Title XXI of the Social Security Act and applicable State statutes); and eyeglasses and/or parts will be dispensed to this recipient within a reasonable time period after receipt from the Department of Corrections.

Sources

[1] Form HFS 2803 (R-5-08), Optical Prescription Order, Illinois Department of Healthcare and Family Services (the Official source link on this page).

Please rate Contact Lense Prescription Form

2 Votes
If you believe this page is infringing on your copyright, please familiarize yourself with and follow our DMCA notice and takedown process - click here to proceed .