
Form DC 37 Pre-Authorization or Claim for Completed Services at a glance
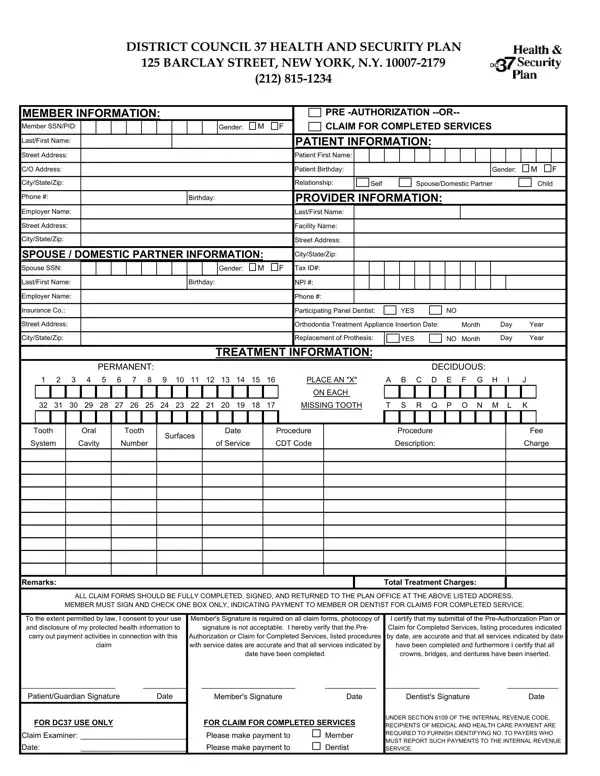
What it is: District Council 37 Health and Security Plan Pre-Authorization or Claim for Completed Services.
Who signs: The Member's Signature is required on all claim forms, and a photocopy of the signature is not acceptable.
The blank Form DC 37 Pre-Authorization or Claim for Completed Services: print it and complete it by hand
How to fill out Form DC 37 Pre-Authorization or Claim for Completed Services, box by box
Member information
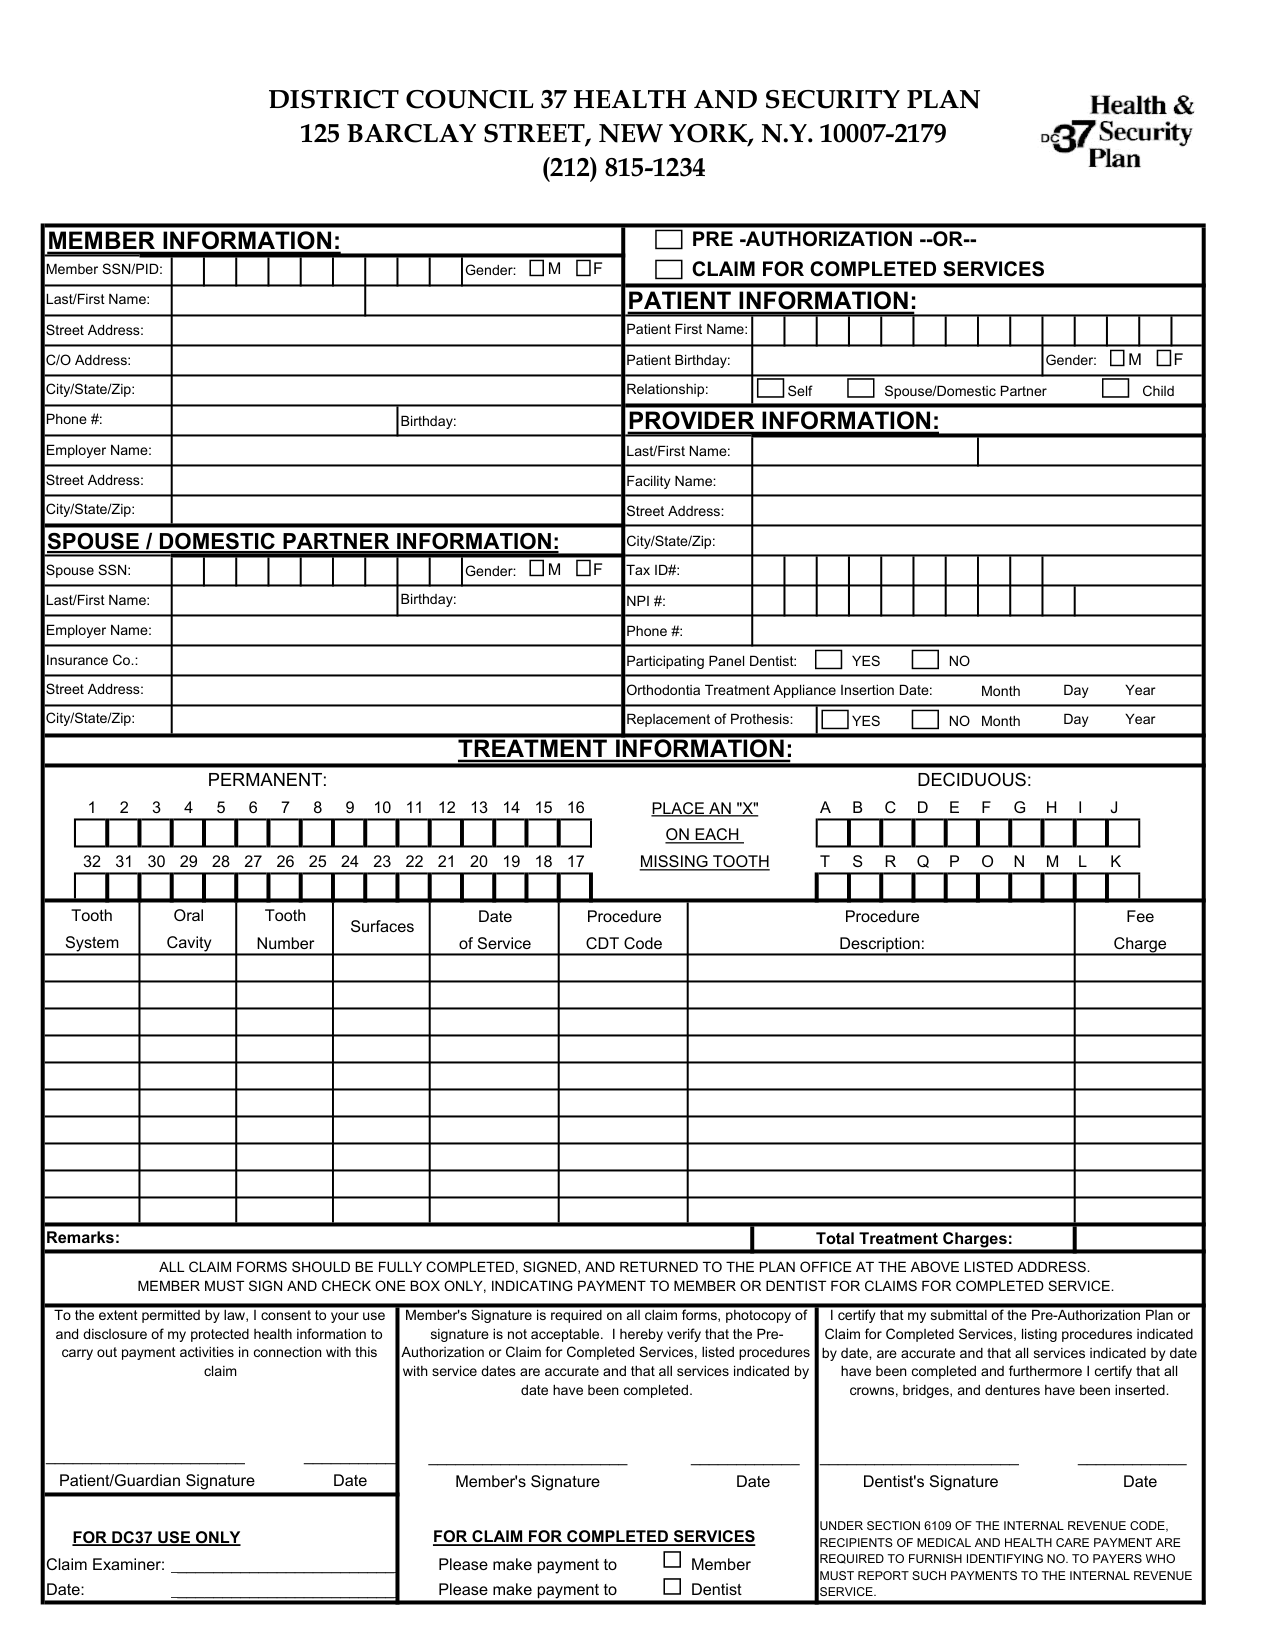
Under MEMBER INFORMATION, write the Member SSN/PID, the Last/First Name, the Street Address, the C/O Address, the City/State/Zip, the Phone # and the Employer Name.
Mark the Gender as M or F.
Patient
For the patient, write the Patient First Name and the Patient Birthday, mark the Gender, and mark the Relationship as Self, Spouse/Domestic Partner or Child.
Spouse / Domestic Partner information
Under SPOUSE / DOMESTIC PARTNER INFORMATION, write the Spouse SSN, the Last/First Name, the Birthday, the Employer Name, the Insurance Co. and the Street Address.
Provider information
Under PROVIDER INFORMATION, write the Last/First Name, the Facility Name, the Street Address, the Tax ID#, the NPI # and the Phone #.
Mark Participating Panel Dentist as YES or NO.
Treatment
For Orthodontia Treatment, write the Appliance Insertion Date as Month, Day and Year.
Mark Replacement of Prothesis as YES or NO.
Place an "X" on each MISSING TOOTH.
For each procedure, write the Tooth Number, the Oral Cavity, the Tooth Surfaces, the Date of Service, the CDT Code, the Procedure Description and the Fee.
Write the Total Treatment Charges.
Write any Remarks.
Signatures
The Member's Signature is required on all claim forms, and a photocopy of the signature is not acceptable.
All claim forms should be fully completed, signed, and returned to the Plan office at 125 Barclay Street, New York, N.Y. 10007-2179, and the member must sign and check one box only, indicating payment to the member or the dentist for claims for completed service.
The dentist, on the Dentist's Signature line, certifies that the submittal of the Pre-Authorization Plan or Claim for Completed Services, listing procedures indicated by date, are accurate and that all services indicated by date have been completed and furthermore that all crowns, bridges, and dentures have been inserted.
The patient or guardian, on the Patient/Guardian Signature line, consents, to the extent permitted by law, to the use and disclosure of protected health information to carry out payment activities in connection with this claim.
The patient or guardian signs on the Patient/Guardian Signature line, the member on the Member's Signature line and the dentist on the Dentist's Signature line, each with the Date.
More rules for Form DC 37 Pre-Authorization or Claim for Completed Services
Under Section 6109 of the Internal Revenue Code, recipients of medical and health care payment are required to furnish an identifying number to payers who must report such payments to the Internal Revenue Service.
Sources
[1] Pre-Authorization or Claim for Completed Services, District Council 37 Health and Security Plan, as served on the page (the Official source link on this page).