

Form 1010 at a glance
What it is: LW-WC-FORM 1010 is the Request of Authorization/Carrier or Self Insured Employer Response. Sections 1 and 2 are filled out by the Health Care Provider.
Who signs: The Health Care Provider signs on each Signature of Health Care Provider line, the Carrier/Self Insured Employer or Utilization Review Company signs on each Signature of Carrier/Self Insured Employer or Utilization Review Company line, and Section 6, Determination of Medical Services Section, has its own Signature and Printed Name.
A filled-in Form 1010 example: a doctor's office requests authorization
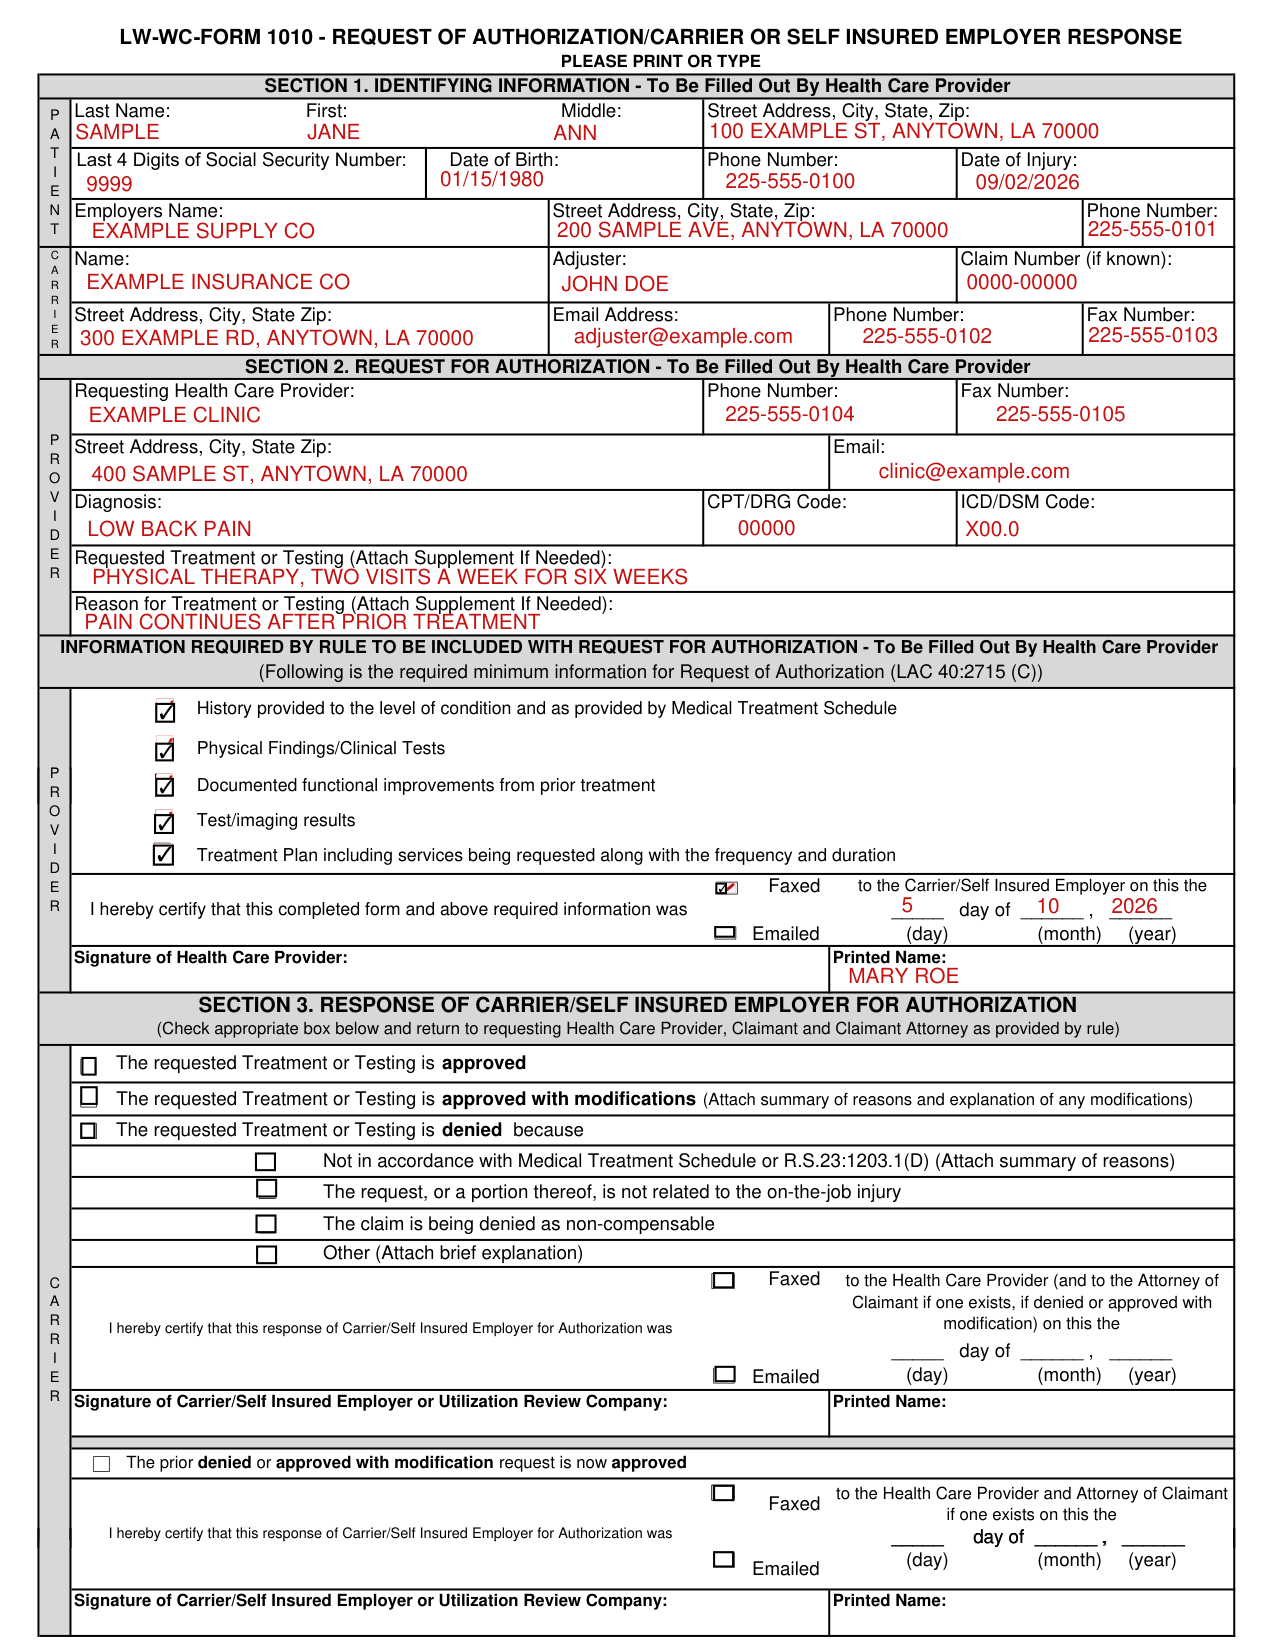
How to fill out Form 1010, box by box
Section 1. Identifying Information
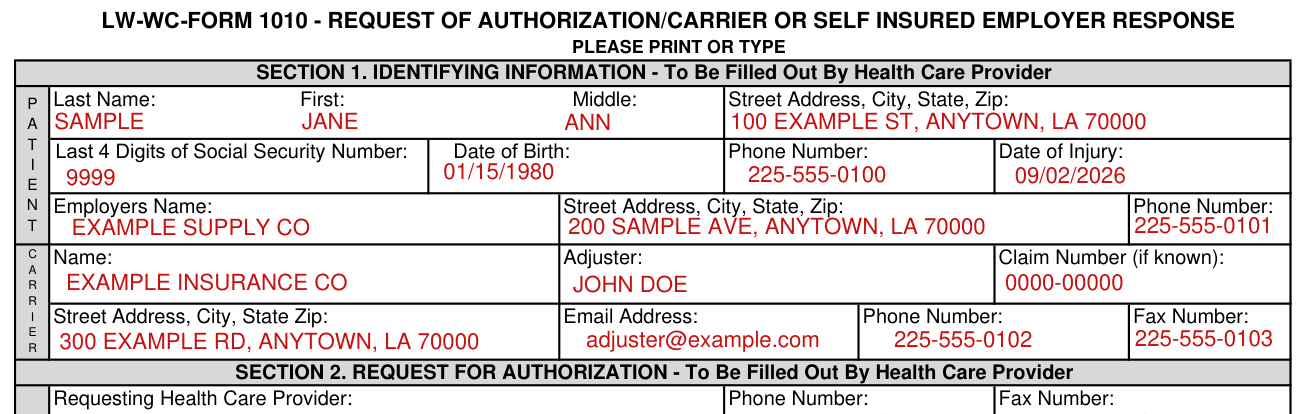
Section 1, Identifying Information, is filled out by the Health Care Provider.
Under PAT IE N T, enter the Last Name, First, Middle and Street Address, City, State, Zip.
Write the Last 4 Digits of Social Security Number, Date of Birth, Phone Number and Date of Injury.
Fill in the Employers Name, Street Address, City, State, Zip and Phone Number.
Under Carrier, enter the Name, Claim Number (if known), Adjuster, Street Address, City, State Zip, Email Address, Phone Number and Fax Number.
Section 2. Request for Authorization

Section 2, Request for Authorization, is filled out by the Health Care Provider.
Under Provider, enter the Requesting Health Care Provider, Phone Number, Fax Number, Street Address, City, State Zip and Email.
Write the Diagnosis, CPT/DRG Code and ICD/DSM Code.
Fill in the Requested Treatment or Testing (Attach Supplement If Needed).
Enter the Reason for Treatment or Testing (Attach Supplement If Needed).
Information required by rule to be included with Request for Authorization

The Health Care Provider fills out the Information Required by Rule to be Included with Request for Authorization, the required minimum information for Request of Authorization.
Check the box for each of these: History provided to the level of condition and as provided by Medical Treatment Schedule, Physical Findings/Clinical Tests, Documented functional improvements from prior treatment, Test/imaging results and Treatment Plan including services being requested along with the frequency and duration.
The Health Care Provider certifies that this completed form and the required information checked in the boxes before the Faxed and Emailed boxes was Faxed or Emailed to the Carrier/Self Insured Employer: check Faxed or Emailed and enter the day, month and year.
Sign on the Signature of Health Care Provider line, then enter the Printed Name.
Sections 3 to 7
Section 4. First Request
Form 1010A is required to be filled out by Carrier/Self Insured Employer and Health Care Provider.
Check The requested Treatment or Testing is delayed because minimum information required by rule was not provided.
The Carrier certifies that this First Request and accompanying Form 1010A was Faxed or Emailed to the Health Care Provider on this the day, month and year: check Faxed or Emailed, then sign on the Signature of Carrier/Self Insured Employer or Utilization Review Company line.
The Provider certifies that a response to the First Request and accompanying Form 1010A was Faxed or Emailed to the Carrier/Self Insured Employer on this the day, month and year: check Faxed or Emailed, sign on the Signature of Health Care Provider line and enter the Printed Name.
Section 6. Determination of Medical Services Section
Check one of these: The required information of LAC40:2715(C) was not provided; The required information of LAC40:2715(C) was provided.
OWCA certifies that a written determination was Faxed or Emailed to the Health Care Provider & Carrier/Self Insured Employer on this the day, month and year: check Faxed or Emailed, then sign on the Signature line and enter the Printed Name.
Section 7. Health Care Provider Response to Medical Services Determination
The Provider certifies that additional information, pursuant to the determination of Medical Services Section, was Faxed or Emailed to the Carrier/Self Insured Employer on this the day, month and year: check Faxed or Emailed, sign on the Signature of Health Care Provider line and enter the Printed Name.
Sources
[1] Form LW-WC-1010 (REV. 06/25) (the Official source link on this page).
