

Form NF-2 at a glance
What it is: This form is the application for motor vehicle no-fault benefits under the New York motor vehicle no-fault insurance law.
Who signs: To be eligible for benefits you must complete and sign this application, and you must sign any attached authorization(s). If the applicant is a minor, a parent or guardian signs and indicates capacity and relationship.
A filled-in Form NF-2 example: a passenger applies after a taxi crash

How to fill out Form NF-2, box by box
Your name, phone nos. and address
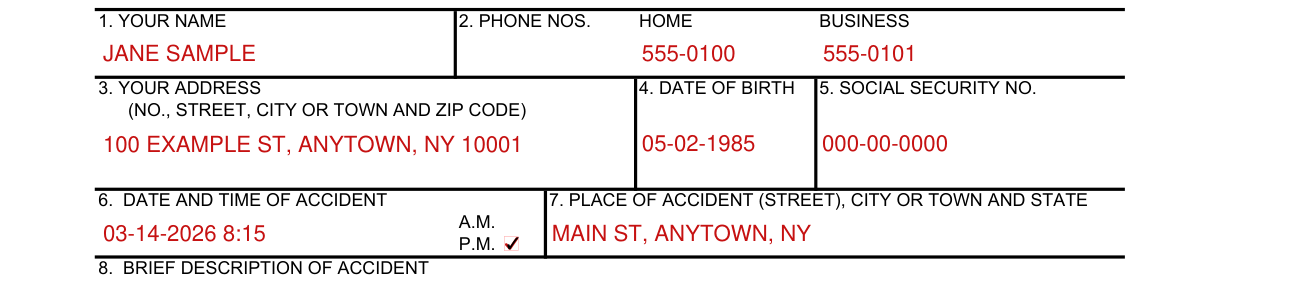
Enter your name, your phone nos., home and business, your address (no., street, city or town and zip code), your date of birth and your social security no.
Boxes 6 to 9, the accident and your injury

In box 6, enter the date and time of the accident and mark A.M. or P.M.
In box 7, enter the place of accident (street), city or town and state; in box 8, enter a brief description of the accident.
In box 9, describe your injury.
Box 10, the vehicle you occupied or operated
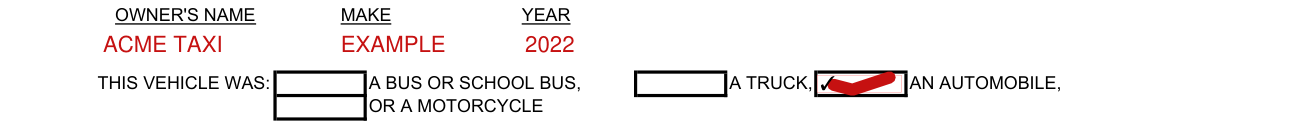
In box 10, enter the owner's name, make and year of the vehicle you occupied or operated at the time of the accident.
Mark what this vehicle was: a bus or school bus, a truck, an automobile, or a motorcycle.
Box 11, driver, passenger or pedestrian
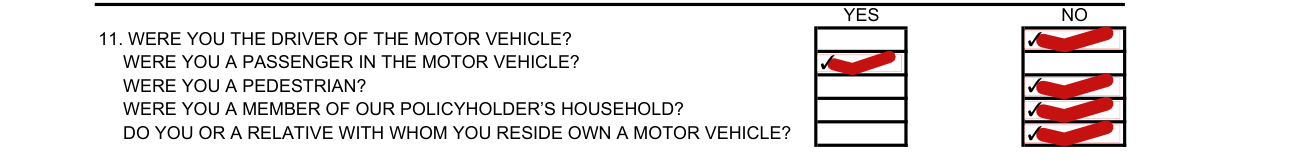
In box 11, mark yes or no for each of these: were you the driver of the motor vehicle, were you a passenger in the motor vehicle, were you a pedestrian, were you a member of the policyholder's household, and do you or a relative with whom you reside own a motor vehicle.
Boxes 12 and 13, doctors and hospital

In box 12, mark yes or no if you were treated by a doctor(s) or other person(s) furnishing health services; if yes, enter the name and address of such doctor(s) or person(s).
In box 13, if you were treated at a hospital(s), mark if you were an out-patient or an in-patient, and enter the date of admission and the hospital's name and address.
Boxes 14 to 16, health bills, more treatment and employment
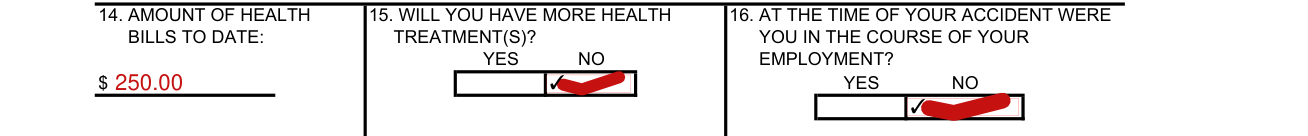
In box 14, enter the amount of health bills to date; in box 15, mark yes or no if you will have more health treatment(s); in box 16, mark yes or no if, at the time of your accident, you were in the course of your employment.
Boxes 17 to 20, time lost, earnings and employers
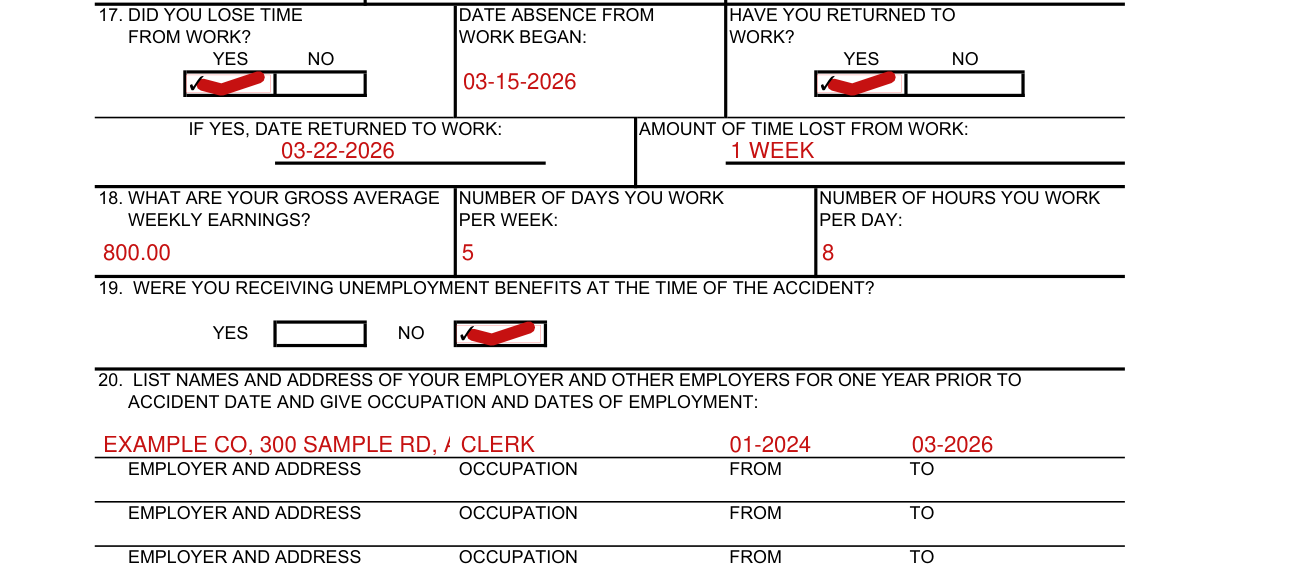
In box 17, mark yes or no if you lost time from work, and enter the date absence from work began; mark yes or no if you have returned to work, and if yes, enter the date returned to work and the amount of time lost from work.
In box 18, enter your gross average weekly earnings, the number of days you work per week and the number of hours you work per day.
In box 19, mark yes or no if you were receiving unemployment benefits at the time of the accident.
In box 20, list the names and address of your employer and other employers for one year prior to accident date, and enter the occupation and dates of employment, from and to, for each employer.
Boxes 21 and 22, other expenses and other payments

In box 21, mark yes or no if, as a result of your injury, you have had any other expenses; if yes, attach explanation and amounts of such expenses.
In box 22, mark yes or no if, due to this accident, you have received or are eligible for payments under New York State disability and under workers' compensation.
Signing the application
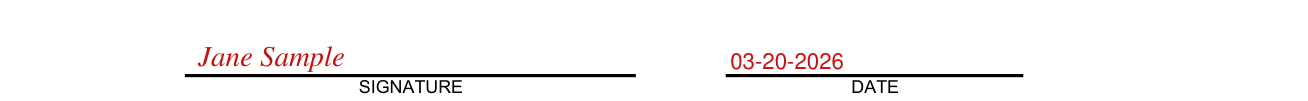
The applicant enters the signature and date; this form is subscribed and affirmed by the applicant as true under the penalties of perjury.
If the applicant is a minor, a parent or guardian signs and indicates capacity and relationship.
The applicant authorizes the insurer to submit any and all of these forms to another party or insurer if such is necessary to perfect its rights of recovery provided for under the no-fault law.
Any person who knowingly and with intent to defraud any insurance company or other person files a statement of claim for any commercial or personal insurance benefits containing any materially false information commits a fraudulent insurance act, which is a crime, and shall also be subject to a civil penalty not to exceed five thousand dollars and the value of the subject motor vehicle or stated claim for each violation.
The authorization for release of work and other loss information

For the authorization for release of work and other loss information, enter your name (print or type) and social security no., then enter the signature and date.
The authorization for release of health service or treatment information

For the authorization for release of health service or treatment information, enter your name (print or type), then enter the signature and date.
More rules for Form NF-2
Complete this form and return it promptly, to determine if you are entitled to benefits under the New York no-fault law.
Return the application promptly with copies of any bills you have received to date.
Sources
[1] Form NF-2 (Rev 1/2004), Application for Motor Vehicle No-Fault Benefits, New York State Department of Financial Services (the Official source link on this page).
