
Form Pd 16 at a glance
What it is: Universal Reporting Form: the NYC form for reporting diseases and conditions.
Where and when to file: Diseases and conditions in green and marked with an asterisk (*) are immediately notifiable. Report by calling the Provider Access Line at 866-692-3641. For all other diseases and conditions, report them by using the online Provider Reporting Interface and Secure Messenger (PRISM) via NYC.ID at a816-health.nyc.gov/prism; mailing this form to the NYC Department of Health and Mental Hygiene at 42-09 28th St., CN-22, Long Island City, NY 11101; or calling 866-692-3641 for the appropriate fax number.
A filled-in Form Pd 16 example: a clinic reports a patient from Brooklyn
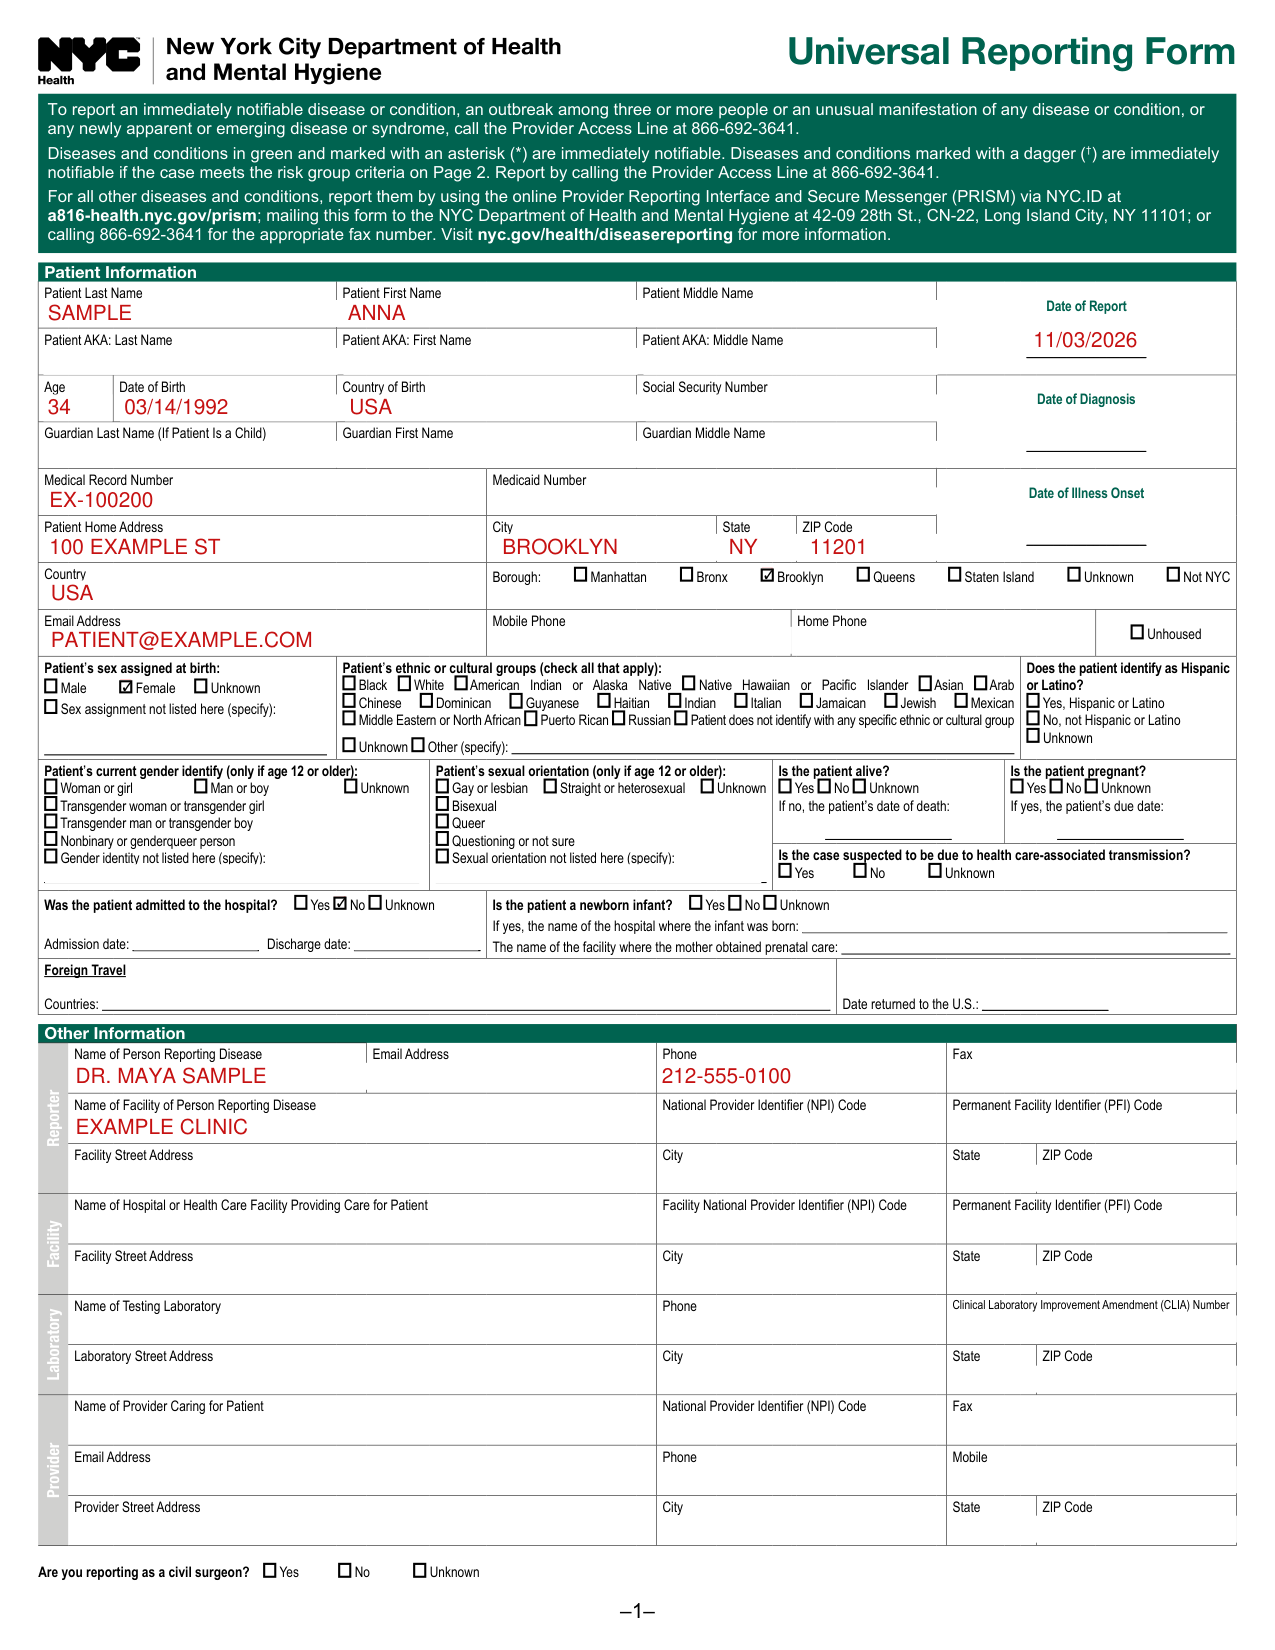
How to fill out Form Pd 16, box by box
Patient Information, Guardian and Medical Record Number
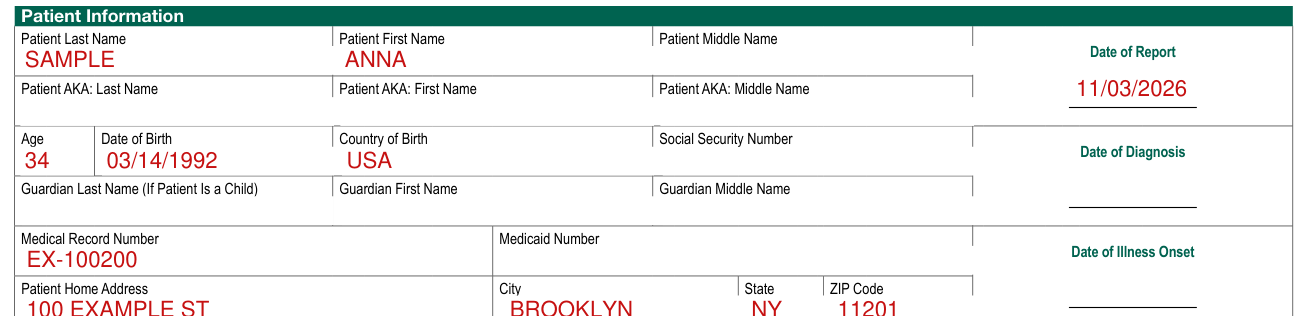
Enter the Patient Last Name, Patient First Name and Patient Middle Name, then the Patient AKA: Last Name, Patient AKA: First Name and Patient AKA: Middle Name. Enter the Age, Date of Birth, Country of Birth and Social Security Number.
Enter the Medical Record Number and Medicaid Number.
Enter the Guardian Last Name (If Patient Is a Child), Guardian First Name and Guardian Middle Name.
Date of Report, Date of Diagnosis and Date of Illness Onset
Enter the Date of Report, the Date of Diagnosis and the Date of Illness Onset.
Patient Home Address, Borough, Email Address and Unhoused

Enter the Patient Home Address, City, State, ZIP Code and Country. For Borough, check Manhattan, Bronx, Brooklyn, Queens, Staten Island, Unknown or Not NYC.
Enter the Email Address, Mobile Phone and Home Phone. Check Unhoused only if it applies.
Patientʼs sex assigned at birth, ethnic or cultural groups, gender and sexual orientation

For Patientʼs sex assigned at birth, check Male, Female, Unknown or Sex assignment not listed here (specify).
For Patientʼs ethnic or cultural groups (check all that apply), check Black, White, American Indian or Alaska Native, Native Hawaiian or Pacific Islander, Asian, Arab, Chinese, Dominican, Guyanese, Haitian, Indian, Italian, Jamaican, Jewish, Mexican, Middle Eastern or North African, Puerto Rican, Russian, Patient does not identify with any specific ethnic or cultural group, Unknown or Other (specify).
For Does the patient identify as Hispanic or Latino?, check Yes, Hispanic or Latino, No, not Hispanic or Latino or Unknown.
For Patientʼs current gender identify (only if age 12 or older), check Woman or girl, Man or boy, Unknown, Transgender woman or transgender girl, Transgender man or transgender boy, Nonbinary or genderqueer person or Gender identity not listed here (specify).
For Patientʼs sexual orientation (only if age 12 or older), check Gay or lesbian, Straight or heterosexual, Unknown, Bisexual, Queer, Questioning or not sure or Sexual orientation not listed here (specify).
For Is the patient alive?, check Yes, No or Unknown. If no, enter the patientʼs date of death.
For Is the patient pregnant?, check Yes, No or Unknown. If yes, enter the patientʼs due date.
Health care-associated transmission, hospital admission, newborn infant and Foreign Travel
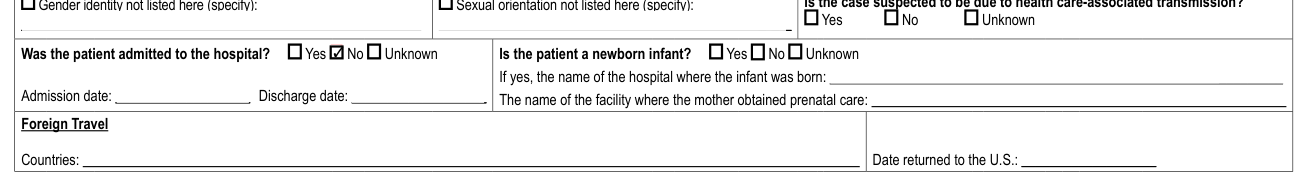
For Is the case suspected to be due to health care-associated transmission?, check Yes, No or Unknown.
For Was the patient admitted to the hospital?, check Yes, No or Unknown. Enter the Admission date and Discharge date.
For Is the patient a newborn infant?, check Yes, No or Unknown. If yes, enter the name of the hospital where the infant was born and the name of the facility where the mother obtained prenatal care.
Under Foreign Travel, enter the Countries and the Date returned to the U.S.
Reporter
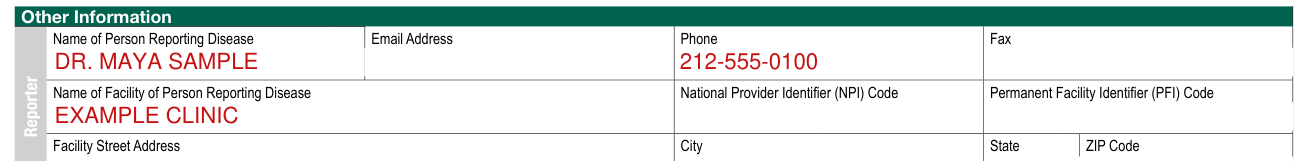
Under Reporter, enter the Name of Person Reporting Disease, Email Address, Phone and Fax.
Facility, Laboratory, Provider and civil surgeon
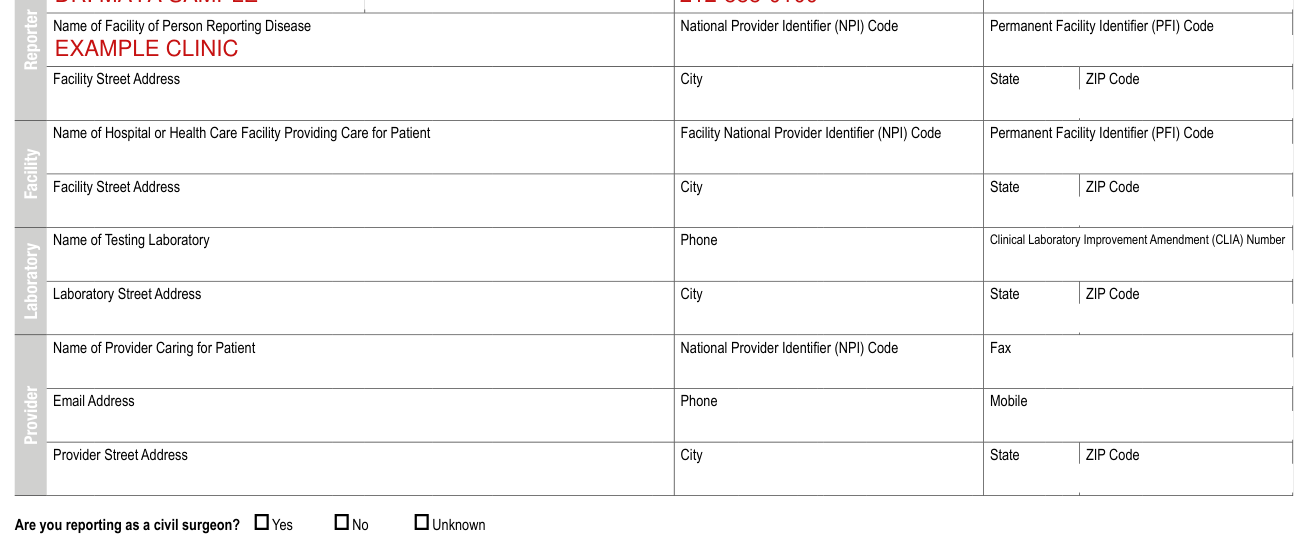
Enter the Name of Facility of Person Reporting Disease, its National Provider Identifier (NPI) Code, Permanent Facility Identifier (PFI) Code, Facility Street Address, City, State and ZIP Code. Under Facility, enter the Name of Hospital or Health Care Facility Providing Care for Patient, its Facility National Provider Identifier (NPI) Code, Permanent Facility Identifier (PFI) Code, Facility Street Address, City, State and ZIP Code.
Under Laboratory, enter the Name of Testing Laboratory, Phone, Clinical Laboratory Improvement Amendment (CLIA) Number, Laboratory Street Address, City, State and ZIP Code.
Under Provider, enter the Name of Provider Caring for Patient, National Provider Identifier (NPI) Code, Fax, Email Address, Phone, Mobile, Provider Street Address, City, State and ZIP Code.
For Are you reporting as a civil surgeon?, check Yes, No or Unknown.
More rules for Form Pd 16
Visit nyc.gov/health/diseasereporting for more information.
Immediately notifiable diseases and HIV
The disease or condition is immediately notifiable
Diseases and conditions marked with a dagger (†) are immediately notifiable if the case meets the risk group criteria on Page 2 (Risk Groups for Disease Exposure or Transmission). Complete Risk Groups for Disease Exposure or Transmission for diseases marked with a dagger (†). If the case meets any criteria, report it immediately to 866-692-3641.
The report is for HIV infection (not acute) or AIDS
HIV infection (not acute) and AIDS should be reported within seven days of diagnoses or receipt of laboratory results. Report using the New York State Provider Report Form (PRF). Call 518-474-4284 for forms or call 212-442-3388 for more information.
Sources
[1] Universal Reporting Form, NYC Department of Health and Mental Hygiene (the Official source link on this page).