


Gynecology Intake Form at a glance
What it is: Gynecology Intake Form: name, allergies and medications; mark No or Yes if you would like to fill out an advance directive, a document of your medical care wishes if you are unable to make decisions.
A filled-in Gynecology Intake Form example: a patient fills out page 1

How to fill out Gynecology Intake Form, box by box
Date, age, name, address, allergies, medications and Menstrual History

Enter Date, Age, Name, Birth Date, Address, Home #, Cell #, Work #, Primary Care MD and Height. Mark No or Yes to: Would you like to fill out an advanced directive, which indicates your medical care wishes if you are unable to make medical decisions? Write Anything you want to talk to your physician about. List ALLERGIES. Under MEDICATIONS, write the DRUG NAMES and the DOSAGE. Under Menstrual History, enter the first day of your last menstrual period, how long it lasts, how many days apart your menstrual cycles are, starting from the first day of one cycle to the first day of your next cycle, and what age you started having menses.
Pap smear and treated for

Enter when your last PAP smear was. Mark No or Yes to an abnormal Pap smear; if Yes, enter When and What abnormality. Mark each one you have been treated for: Chlamydia, Gonorrhea, Genital Warts, Herpes, Trichomonas, Syphilis.
Sexual activity and birth control
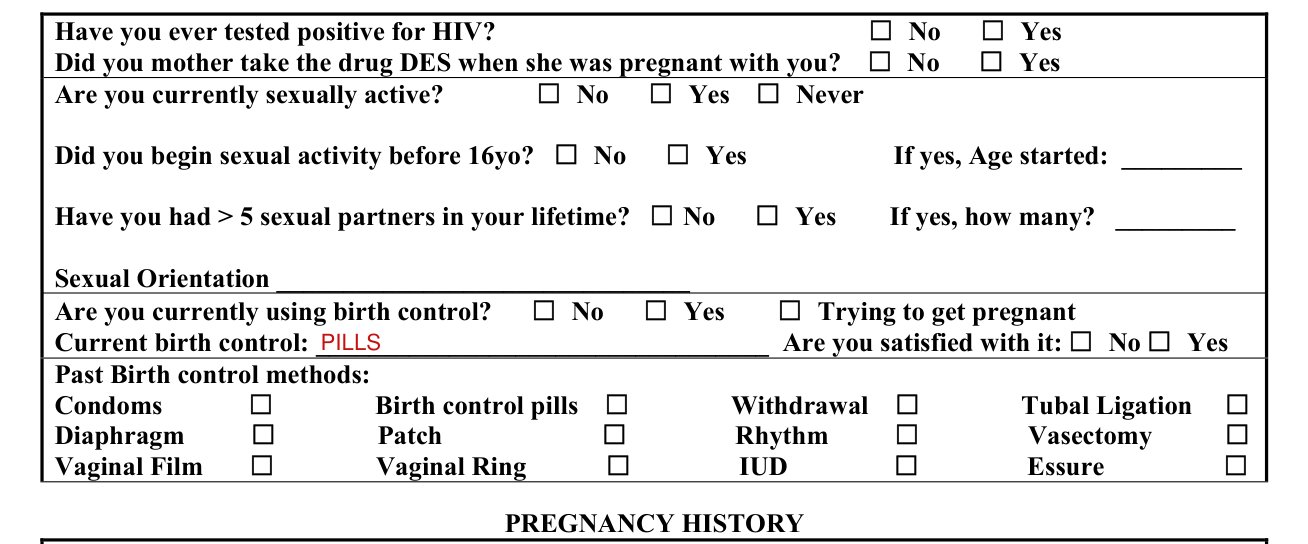
Mark No or Yes to: tested positive for HIV; Did your mother take the drug DES when she was pregnant with you; Are you currently sexually active (No, Yes or Never); Did you begin sexual activity before 16yo. If yes, enter Age started.
Mark No or Yes to: Have you had > 5 sexual partners in your lifetime? If yes, enter how many. Enter Sexual Orientation.
Mark No, Yes or Trying to get pregnant for using birth control. Enter Current birth control, and mark No or Yes to: Are you satisfied with it. Mark Past Birth control methods: Condoms, Birth control pills, Withdrawal, Tubal Ligation, Diaphragm, Patch, Rhythm, Vasectomy, Vaginal Film, Vaginal Ring, IUD, Essure.
Pregnancy history
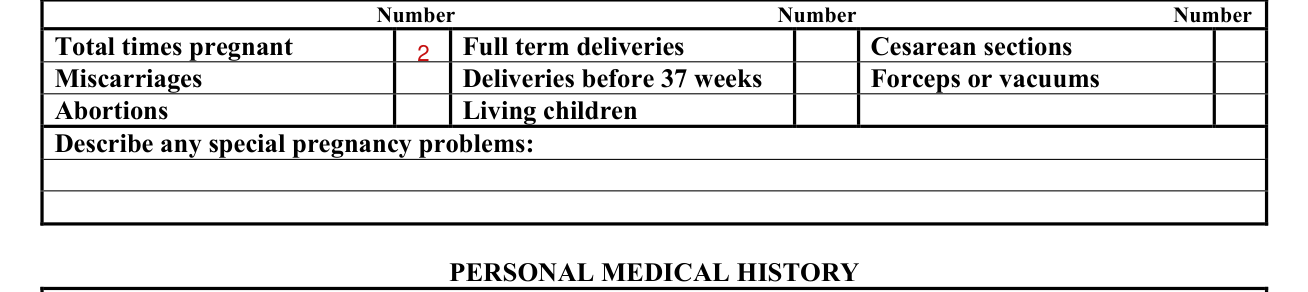
Under PREGNANCY HISTORY, enter the Number for Total times pregnant, Full term deliveries, Cesarean sections, Miscarriages, Deliveries before 37 weeks, Forceps or vacuums, Abortions and Living children. Describe any special pregnancy problems.
Personal medical and surgical history
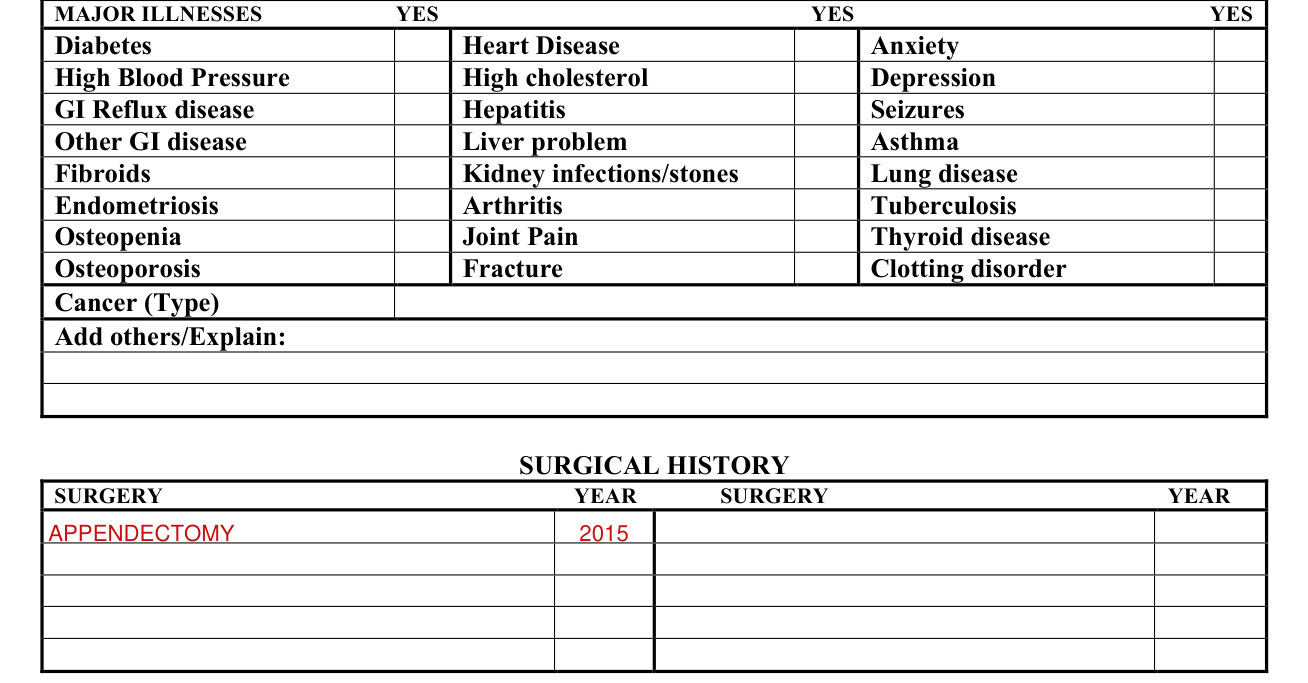
Under PERSONAL MEDICAL HISTORY, MAJOR ILLNESSES, mark YES for each one that applies: Diabetes, Heart Disease, Anxiety, High Blood Pressure, High cholesterol, Depression, GI Reflux disease, Hepatitis, Seizures, Other GI disease, Liver problem, Asthma, Fibroids, Kidney infections/stones, Lung disease, Endometriosis, Arthritis, Tuberculosis, Osteopenia, Joint Pain, Thyroid disease, Osteoporosis, Fracture, Clotting disorder. Enter Cancer (Type) and Add others/Explain.
Under SURGICAL HISTORY, enter the SURGERY and the YEAR.
Family history
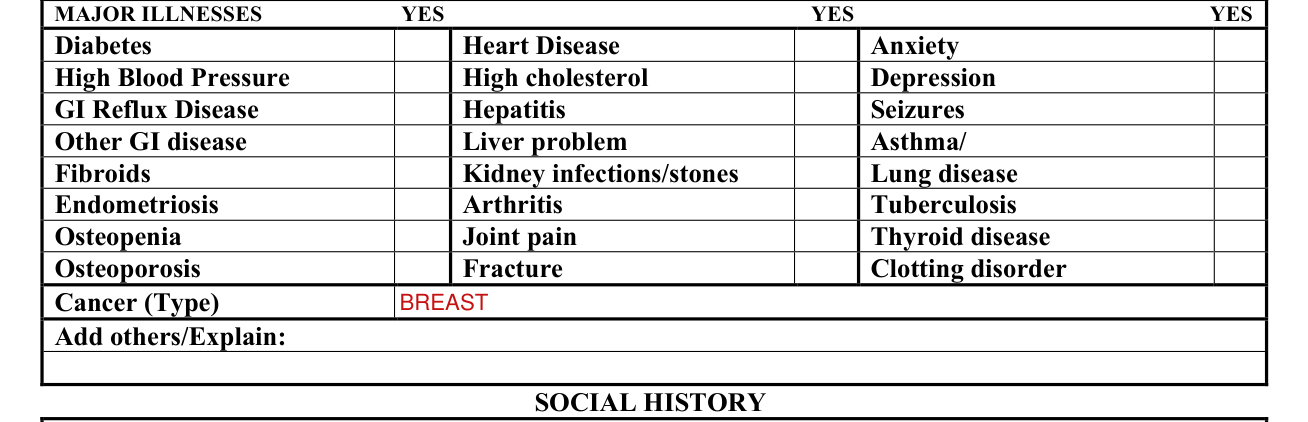
Under FAMILY HISTORY, MAJOR ILLNESSES, mark YES for each one that applies: Diabetes, Heart Disease, Anxiety, High Blood Pressure, High cholesterol, Depression, GI Reflux Disease, Hepatitis, Seizures, Other GI disease, Liver problem, Asthma, Fibroids, Kidney infections/stones, Lung disease, Endometriosis, Arthritis, Tuberculosis, Osteopenia, Joint pain, Thyroid disease, Osteoporosis, Fracture, Clotting disorder. Enter Cancer (Type) and Add others/Explain.
Social history
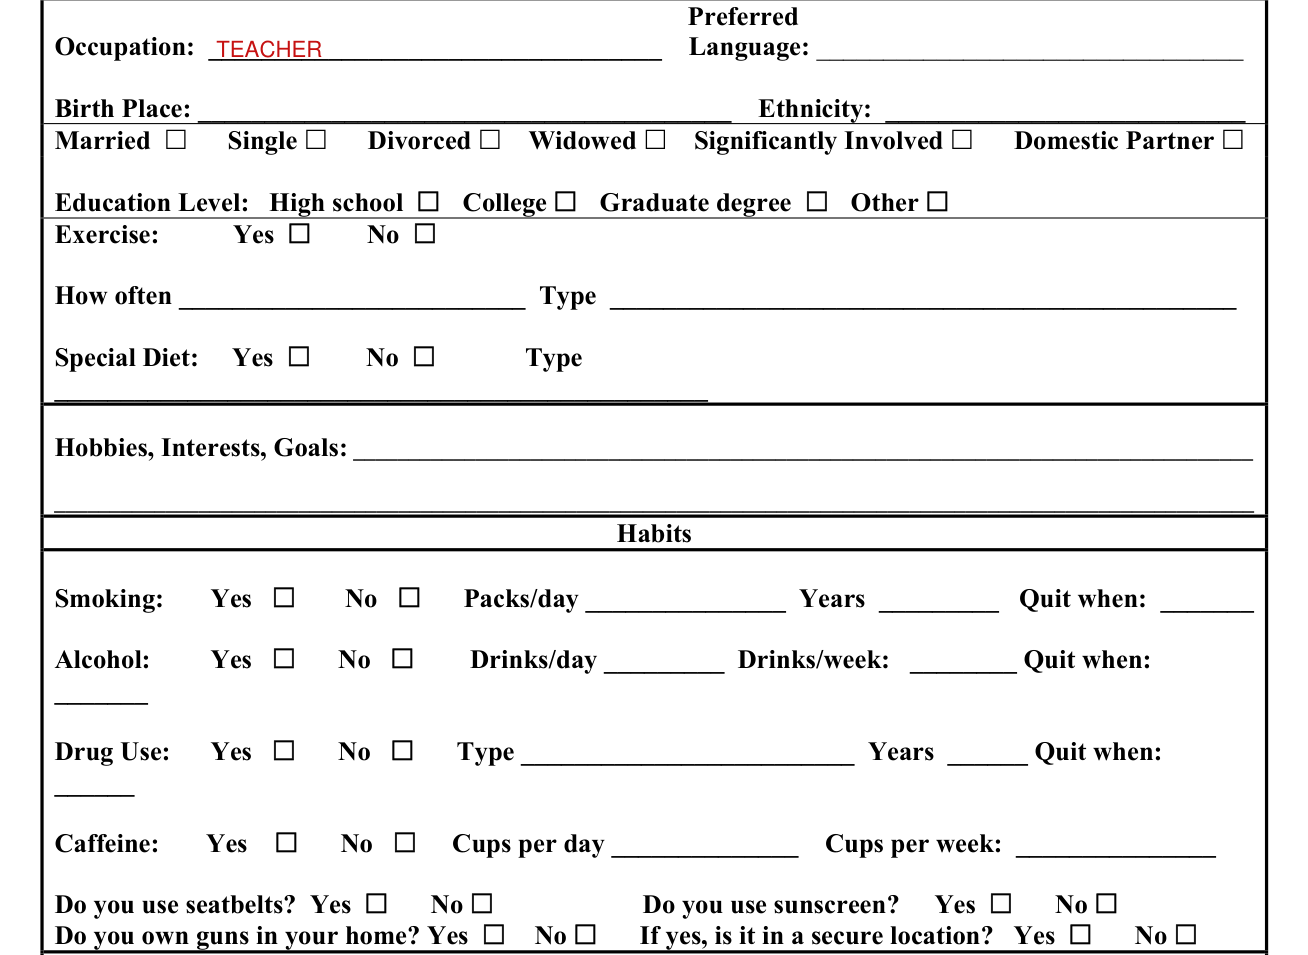
Under SOCIAL HISTORY, Personal Profile, enter Preferred Occupation, Language, Birth Place and Ethnicity. Mark one: Married, Single, Divorced, Widowed, Significantly Involved, Domestic Partner. Mark one Education Level: High school, College, Graduate degree, Other. Mark Yes or No for Exercise, and enter How often and Type. Mark Yes or No for Special Diet, and enter Type. Enter Hobbies, Interests, Goals.
Under Habits, mark Yes or No for Smoking, Alcohol, Drug Use and Caffeine. Enter Packs/day, Years and Quit when for Smoking; Drinks/day, Drinks/week and Quit when for Alcohol; Type, Years and Quit when for Drug Use; Cups per day and Cups per week for Caffeine. Mark Yes or No for: Do you use seatbelts? Do you use sunscreen? Do you own guns in your home? If yes, is it in a secure location?
Review of systems
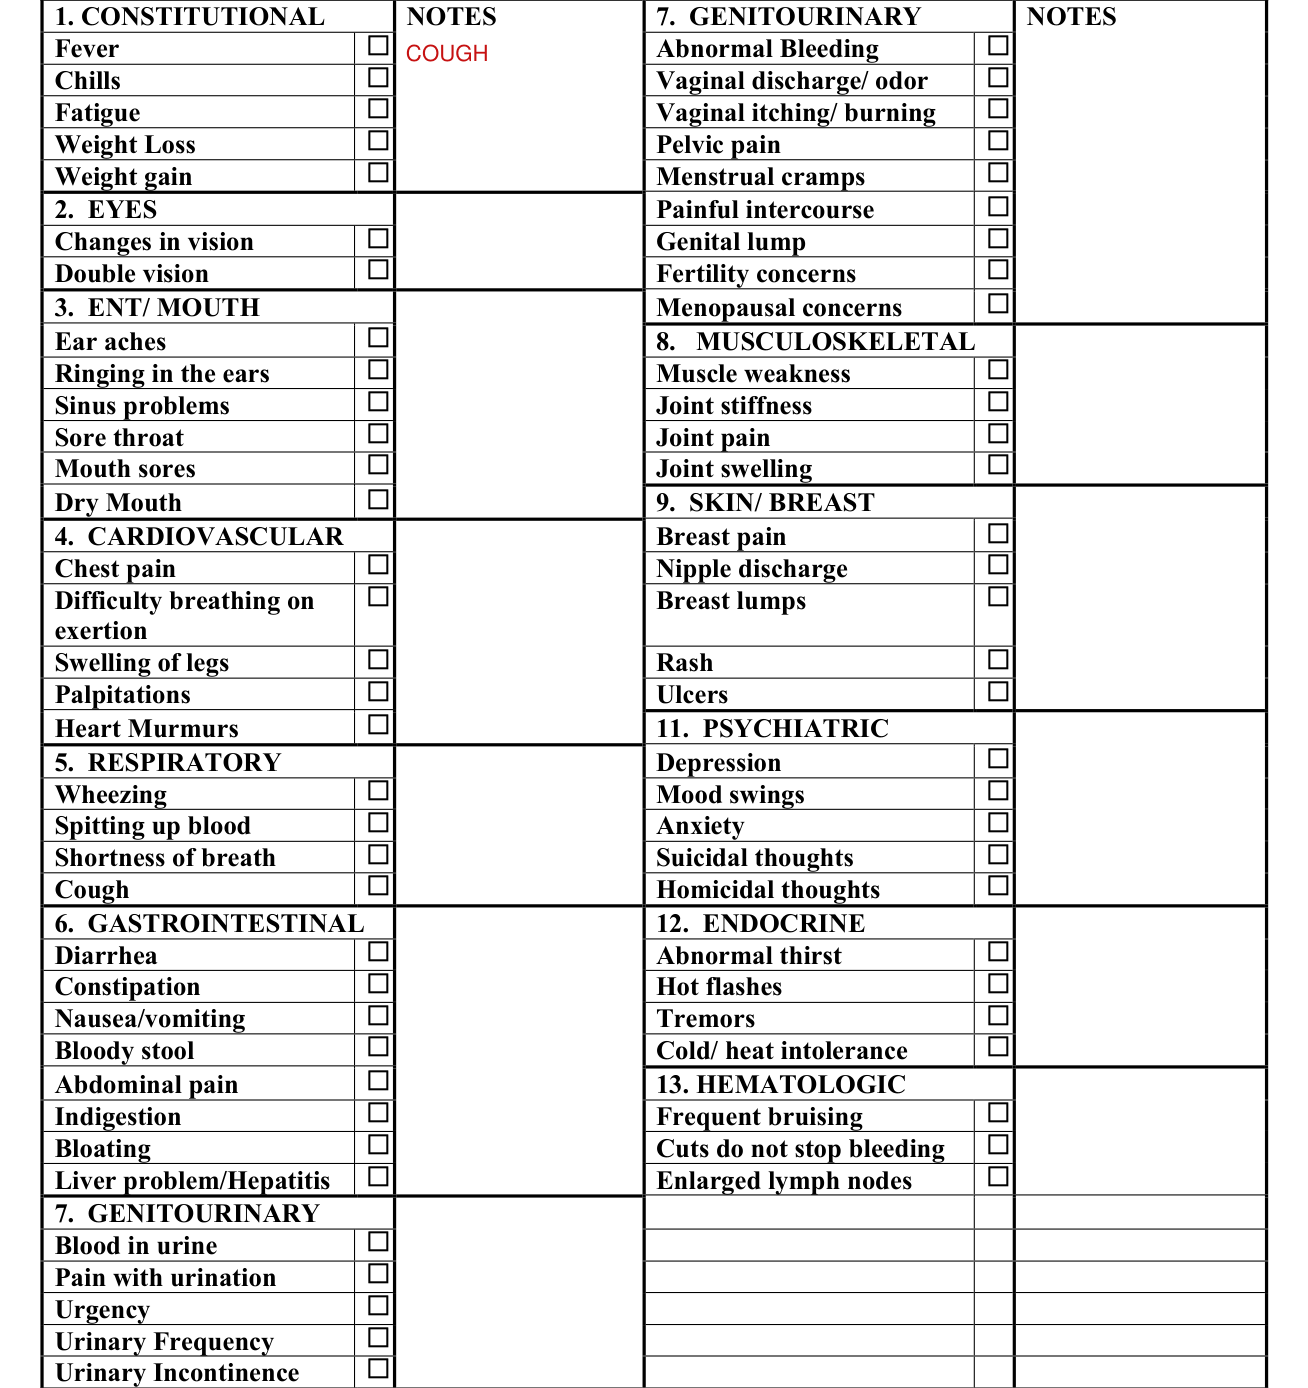
Under REVIEW OF SYSTEMS, 1. CONSTITUTIONAL, mark Fever, Chills, Fatigue, Weight Loss or Weight gain. Under 7. GENITOURINARY, mark Abnormal Bleeding, Vaginal discharge/ odor, Vaginal itching/ burning or Pelvic pain.
Also under GENITOURINARY, mark Menstrual cramps, Painful intercourse, Genital lump, Fertility concerns or Menopausal concerns. Mark 2. EYES: Changes in vision or Double vision.
Write NOTES.
Sources
[1] Gynecology Intake Form (11/07 KC) (the Official source link on this page).