


Emergency Room/Hospital Admittance Form at a glance
What it is: The Emergency Room/Hospital Admittance Form is to be completed by residential staff prior to bringing the individual with intellectual disability to the Emergency Room or admitting the individual to the hospital.
A filled-in Emergency Room/Hospital Admittance Form example: group home staff prepare a hospital visit

How to fill out Emergency Room/Hospital Admittance Form, box by box
Date, completed by and relationship

Enter the Date, Completed by and Relationship to Individual.
Name, Nickname/Likes to be called, DOB and Soc Sec #
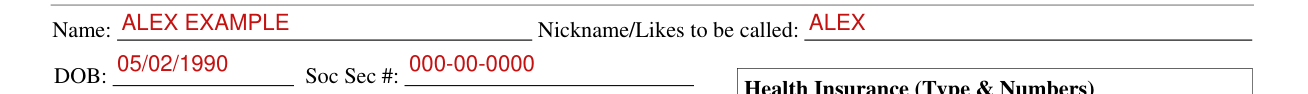
Write the Name, Nickname/Likes to be called, DOB and Soc Sec #.
Address and phone

Write the Address and the Phone #.
Health Insurance (Type & Numbers)

Under Health Insurance (Type & Numbers), write the Primary and the Secondary.
Allergies

Write the Allergies.
Living Status
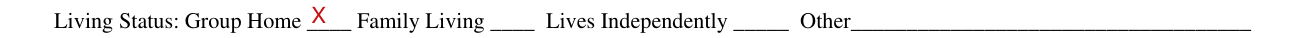
Under Living Status, mark Group Home, Family Living, Lives Independently or Other.
Nursing Supports
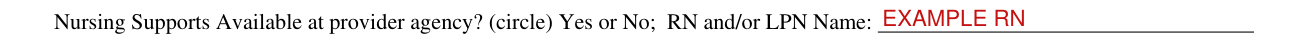
Under Nursing Supports Available at provider agency?, circle Yes or No and write the RN and/or LPN Name.
Emergency Contacts

Under Emergency Contacts, write the Name (Provider Agency) and the Name (Family), each with a Phone Number, the Relationship, and the Phone Number (After Hours).
Write the County Contact Person with the Phone Number and the Phone Number (After Hours).
Physicians and level of intellectual disability

Write the Primary Care Physician, Neurologist and Psychiatrist, each with a Phone Number. Write the Reason for ER visit today and the Current Medical Problems/Diagnoses. For Level of Intellectual disability (circle one), circle Mild, Moderate, Severe or Profound.
Consent Status

Under Consent Status, mark only one of the three boxes. Mark CAN give own consent.
Or mark CANNOT give own consent. Has a Legal Guardian. and write the Legal Guardian and the Phone Number.
Or mark CANNOT give own consent. Does not have a Legal Guardian. Has a Substitute Healthcare Decision Maker. and write the Name, the Phone Number, the Medical Durable POA and the Phone Number.
Resuscitation Status
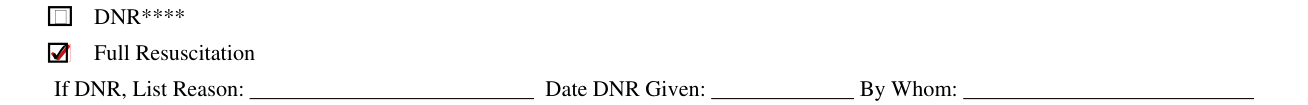
Under Resuscitation Status, mark DNR or Full Resuscitation.
If DNR, List Reason, Date DNR Given and By Whom.
Release of information and vaccines
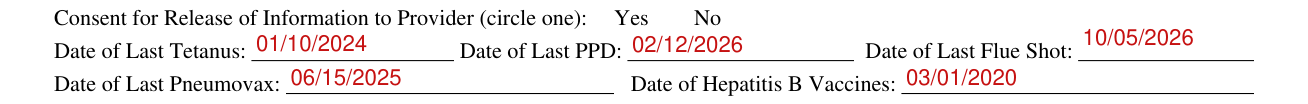
For Consent for Release of Information to Provider (circle one), circle Yes or No. Then write the Date of Last Tetanus, Date of Last PPD, Date of Last Flue Shot, Date of Last Pneumovax and Date of Hepatitis B Vaccines.
More rules for Emergency Room/Hospital Admittance Form
Under Communication, mark Able to Communicate, Communication Difficulties/Uses verbalizations, Communication Difficulties/Uses gestures, Not able to communicate needs or Unable to use call bell.
Under Medication Administration, mark Independent/Self Medicates or Medication Administered by Staff.
Under Ambulation, mark Independent, Needs Assistance, Walker or Wheelchair, and Steady, Unsteady, 1 Person, 2 Person, Cane, Crutches or Non-Ambulatory.
Under Dining/Eating, mark Independent, Needs Assistance, Totally Dependent, Fed Through a Tube or Other.
Under Vision, mark Normal, Low Vision, Blind, Wears glasses or Wears contact lenses. Under Hearing, mark Normal, Hard of hearing (Left/Right), Deaf (Left/Right) or Hearing Aid (Left/Right).
Under Personal Hygiene and Oral Hygiene, mark Independent or Special Needs. Under Oral Hygiene, also mark Dentures (Upper/Lower/Partial) and Head of Bed Elevated (Yes/No).
Under Diet Textures, mark Regular, Chopped, Ground, Puree or Thickened Liquid. Write the Diet type and the Last Meal Eaten.
Under Supportive Devices, mark Padded side rails, Splints, Braces, Helmet or Other. Under Toileting Ability, mark Continent, Needs Assistance, Incontinent, Catheterized or Other.
Under SPECIAL NEEDS Usual Response to Medical Exams, mark Cooperates, Partially Cooperates, Resistant/Becomes Agitated or Fearful/Anxious. Also mark Any sedation required for clinical visits, Special positioning required for examination, Staff required for assistance with exams, Requires limited waiting periods for exams, Prefers early day appointments, Prefers end of day appointments or Special communication device/method.
For Pain Response, mark Normal or Unique.
For Medical History, mark Known or Unknown. For information, contact: write the Relationship, the Phone and the Address.
Under SURGICAL, List all previous surgeries and dates (most recent first).
Under WOMEN'S HEALTH, mark Currently Pregnant Yes or No and Past History of Childbirth Yes or No. Write the Age menstruation started and the Age menstruation stopped, or mark Still menstruating. Write the Date of Last PAP, mark History of Abnormal PAP? Yes or No, and write the Date of Last Mammogram.
Mark Any previous problems with anesthesia: No or Yes. List any serious trauma or broken bones.
Under MEN'S HEALTH, write the Date of Last prostrate Exam and the Date of PSA, then mark Normal, Abnormal or N/A.
Under MEDICAL, List all serious medical illnesses (e.g., pneumonia, heart attack) and ongoing medical problems (e.g., diabetes, high blood pressure, epilepsy). Under PSYCHIATRIC, List all major behavioral and psychiatric diagnoses (e.g., depression, schizophrenia, self-injurious behavior).
Sources
[1] Emergency Room/Hospital Admittance Form, no issuer file: never published (the Official source link on this page).