

Non-Institutional Medicaid Provider Agreement at a glance
What it is: The Non-Institutional Medicaid Provider Agreement is where the Provider agrees to participate in the Florida Medicaid program under terms and conditions.
Who signs: The provider, or each principal of the provider if the provider is a corporation, partnership, association, or other entity, is required to sign this agreement.
A filled-in Non-Institutional Medicaid Provider Agreement example: the president signs the agreement

How to fill out Non-Institutional Medicaid Provider Agreement, box by box
Signatories

For this purpose, principals includes partners or shareholders of five (5) percent or more, officers, directors, managers, financial records custodian, medical records custodian, subcontractors, and individuals holding signing privileges on the depository account, and other affiliated person.
A chief executive officer (CEO) or president may sign this agreement in lieu of all principals.
For each signatory, legibly print name of signatory, Title, Signature and Date, and attach additional signature pages if necessary.
Failure to sign the agreement will make the agreement and provider number voidable by the agency.
The signatories represent and warrant that they have read the agreement, understand it, and are authorized to execute it on behalf of their respective principals or co-owners.
Provider information
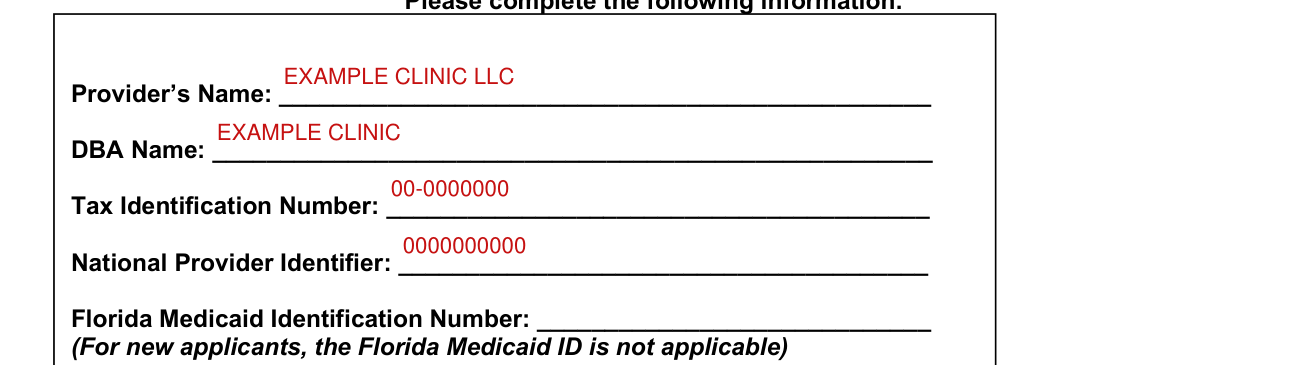
Complete the Provider's Name, DBA Name, Tax Identification Number, National Provider Identifier and Florida Medicaid Identification Number (For new applicants, the Florida Medicaid ID is not applicable).
More rules for Non-Institutional Medicaid Provider Agreement
Provided that all requirements for enrollment have been met, this agreement shall remain in effect for five (5) years from the effective date of the provider's eligibility for initial enrollment unless otherwise terminated.
With respect to reenrolling providers, the agreement shall remain in effect for five (5) years from either the date the most recent agreement expires or the date the provider signs the renewal agreement, which ever date is earlier, unless otherwise terminated.
The provider understands and agrees that no agency signature is required to make this agreement valid and enforceable.
Attest that all statements and information furnished by the prospective provider before signing the provider agreement shall be true and complete.
The filing of a materially incomplete, misleading or false application will make the application and agreement voidable at the option of the agency and is sufficient cause for immediate termination of the provider from the Medicaid program and/or revocation of the provider number.
This agreement becomes null and void upon transfer of assets; change of ownership; or upon discovery by the agency of the submission of a materially incomplete, misleading or false provider application unless subsequently ratified or approved by the agency.
This agreement may be terminated without cause upon thirty (30) days written notice by either party.
Accept Medicaid payment as payment in full, and not bill or collect from the recipient or the recipient's responsible party any additional amount except, and only to the extent the agency permits or requires, co-payments, coinsurance, or deductibles to be paid by the recipient for the services or goods provided.
Bill other insurers and third parties, including the Medicare program, before billing the Medicaid program, if the recipient is eligible for payment for health care or related services from another insurer or person and comply with all other state and federal requirements in this regard.
Agree to notify the agency of any changes to the information furnished on the Florida Medicaid Provider Enrollment Application, including but not limited to changes of address, tax identification number, group affiliation, or depository bank account. The provider shall report a change in any principal of the provider, including any officer, director, agent, managing employee, or affiliated person, or any partner or shareholder who has an ownership interest equal to five (5) percent or more in the provider to the agency in writing within thirty (30) days after the change occurs.
At least 60 days before the anticipated date of the change of ownership, the transferor shall notify the agency of the intended change of ownership and the transferee shall submit to the agency a Medicaid provider enrollment application.
Report and refund any moneys received in error or in excess of the amount to which the provider is entitled from the Medicaid program within 90 days of receipt.
Common questions about Non-Institutional Medicaid Provider Agreement
Is there a deadline?
Agree to notify the agency within 5 business days after suspension or disenrollment from Medicare.
Sources
[1] Non-Institutional Medicaid Provider Agreement (MPA Non-Institutional, December 2023), Florida Agency for Health Care Administration (the Official source link on this page).
