


IL 444-4765 at a glance
What it is: IL 444-4765 is the State of Illinois Department of Human Services REDETERMINATION APPLICATION, to keep getting benefits on your regular availability date.
Who signs: By signing, you swear or affirm, under penalty of perjury, that the answers on this application are true and correct to the best of your knowledge. To be considered a valid application, this form must be signed.
Your SNAP benefits will end; to keep getting benefits on your regular availability date, complete and sign this form.
If you receive TANF Cash, this form must be completed for your cash benefits to continue.
A filled-in IL 444-4765 example: a household list with one wage earner
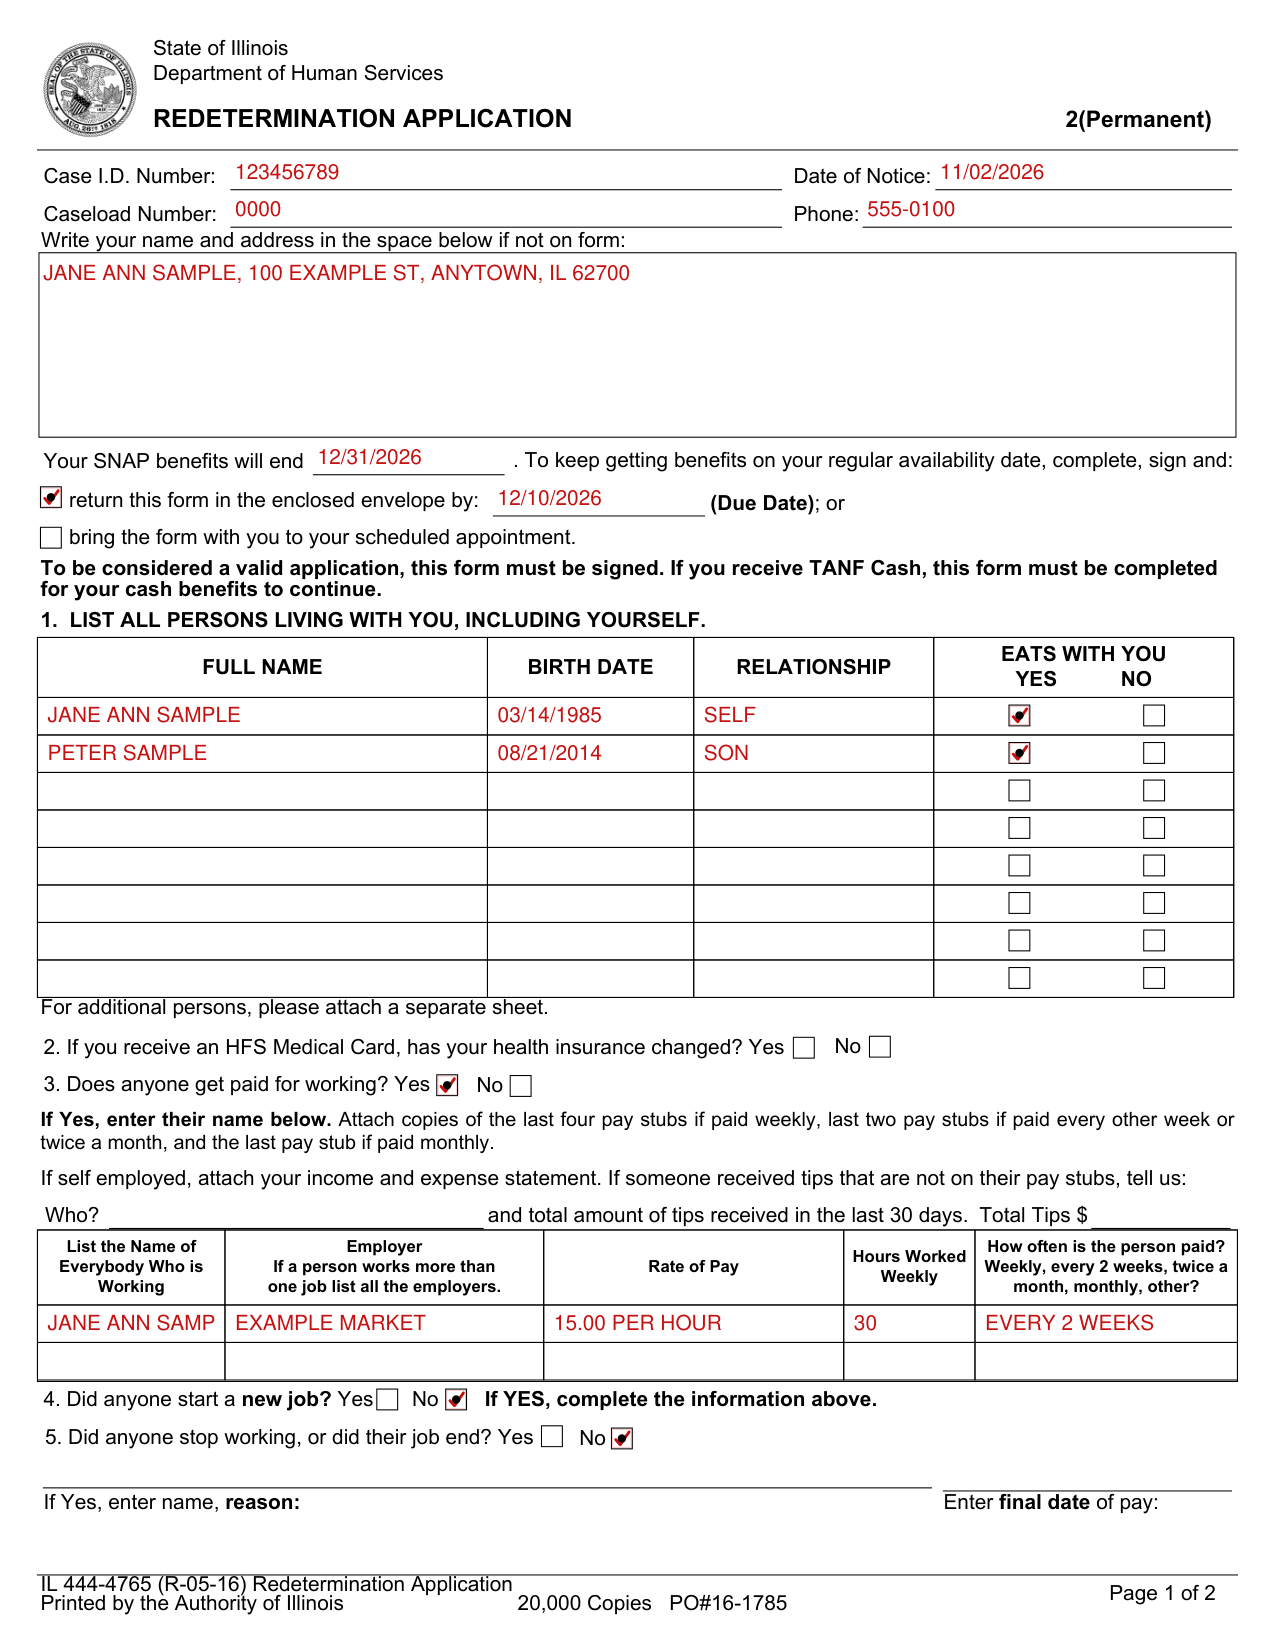
How to fill out IL 444-4765, box by box
Case I.D. Number, Date of Notice, Caseload Number and Phone
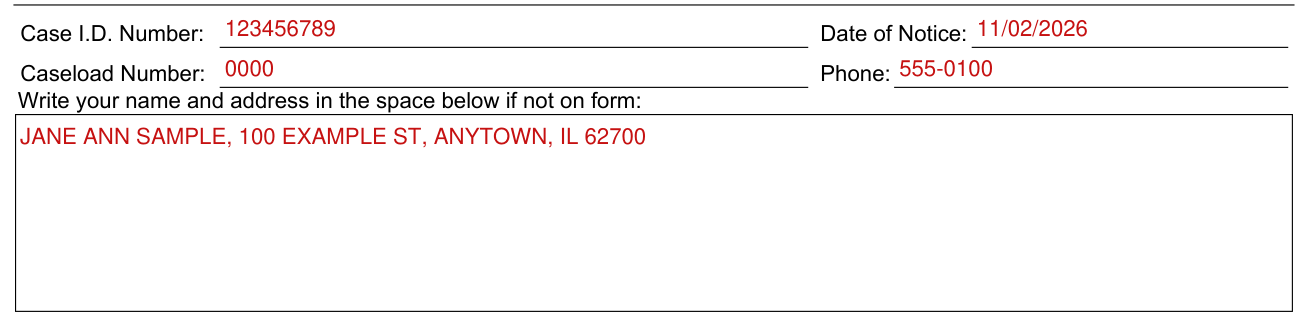
Enter the Case I.D. Number and the Date of Notice.
Enter the Caseload Number and the Phone, and write your name and address in the space if not on form.
Return this form in the enclosed envelope by the Due Date, or bring the form to your scheduled appointment

To keep getting benefits on your regular availability date, complete, sign and return this form in the enclosed envelope by the Due Date; or bring the form with you to your scheduled appointment.
Enter the date your SNAP benefits will end and the Due Date.
1. List All Persons Living With You, Including Yourself
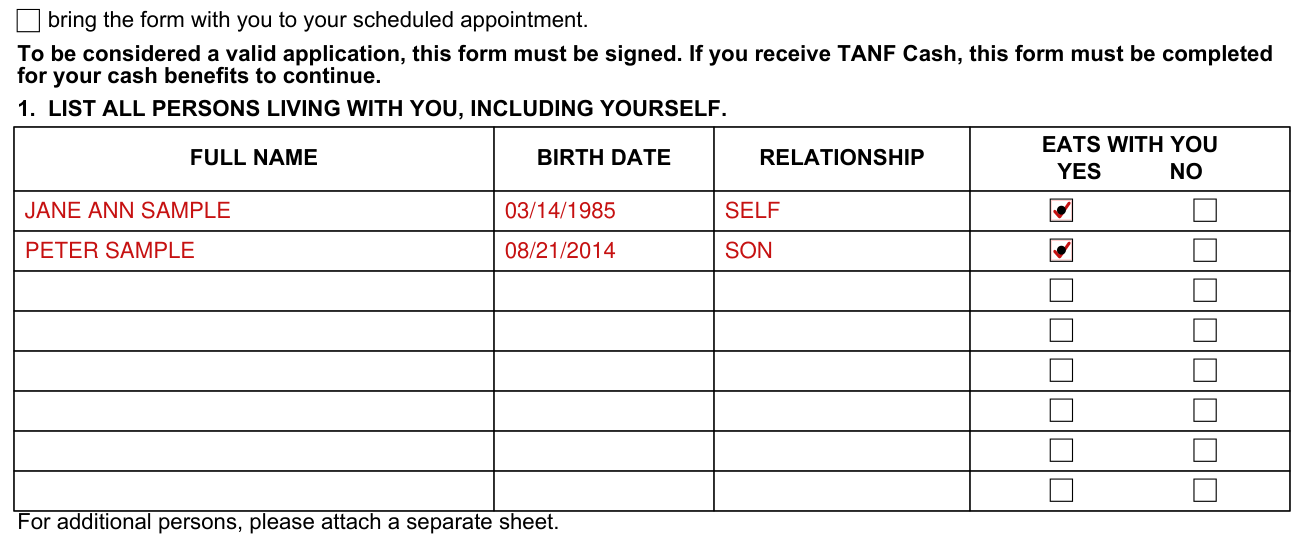
List all persons living with you, including yourself, with FULL NAME, BIRTH DATE and RELATIONSHIP, and mark YES or NO under EATS WITH YOU.
For additional persons, please attach a separate sheet.
2. HFS Medical Card and 3. Does anyone get paid for working?
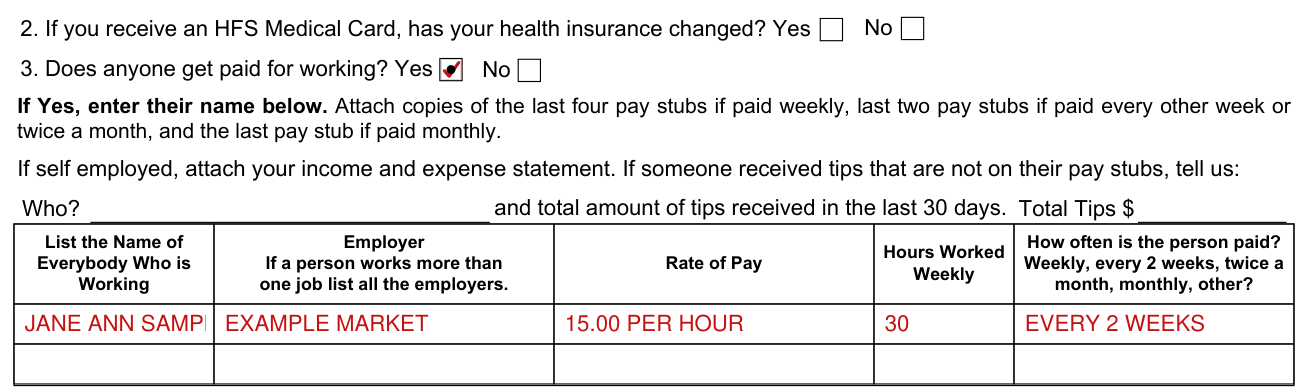
If you receive an HFS Medical Card, mark Yes or No: has your health insurance changed?
Mark Yes or No: does anyone get paid for working?
If Yes, enter their name. Attach copies of the last four pay stubs if paid weekly, last two pay stubs if paid every other week or twice a month, and the last pay stub if paid monthly.
If self employed, attach your income and expense statement. If someone received tips that are not on their pay stubs, enter Total Tips $ and total amount of tips received in the last 30 days.
List the Name of Everybody Who is Working, with Employer, Rate of Pay, Hours Worked Weekly, and how often the person is paid: Weekly, every 2 weeks, twice a month, monthly, other. If a person works more than one job list all the employers.
4. Did anyone start a new job?

Mark Yes or No: did anyone start a new job? If YES, complete the information.
5. Did anyone stop working, or did their job end?

Mark Yes or No: did anyone stop working, or did their job end? If Yes, enter name, reason, and enter final date of pay.
6. During the last 30 days did anyone receive any other income
Mark Yes or No: during the last 30 days did anyone receive any other income such as Child Support, Social Security, SSI, Unemployment, VA, Worker's Compensation, contributions, or any other money? If YES, complete the box with Name, Type of Income, Amount and How Often.
7. Do you expect any changes in anyone's income or employment?
Mark Yes or No: do you expect any changes in anyone's income or employment? If Yes, enter what the change is and when you expect this change to happen.
8. Have you moved or changed your address?
Mark Yes or No: have you moved or changed your address? If Yes, enter the new address.
9. How much is your Rent, Lot Rent or Mortgage?
Enter your Rent, Lot Rent and Mortgage, and any taxes and homeowner's insurance paid separately. Mark Yes or No: are any of the taxes or homeowner's insurance paid by someone else? If yes, enter who and how much.
10. Energy assistance payment, heat or air conditioning and other utilities
Mark Yes or No: did you receive an energy assistance payment of $21.00 or more this month or in any of the last twelve months from the Low Income Home Energy Assistance Program (LIHEAP) (in Chicago paid through CEDA)? (checked October 20, 2026) Answering yes will not reduce your benefits.
If no, mark Yes or No: are you billed separately from your rent or mortgage for heat or air conditioning, or excess cost for heat or air conditioning? Air conditioning is a window air or central air conditioning unit.
If NO, mark Yes or No: do you pay any other utilities? If YES, enter what utilities.
Mark Yes or No: does anyone help pay your utilities? If YES, enter who and what utilities.
11. Does anyone pay child support?
Mark Yes or No: does anyone pay child support? If Yes, enter who makes the payments, how much, and how often.
12. Do you pay for someone to care for a child or disabled adult?
Mark Yes or No: do you pay for someone to care for a child or disabled adult so you can work, look for a job, or receive training? If YES, enter who the care is for, who provides the care, how much you pay for the care, and how often.
13. Does anyone who is age 18 or over attend school?
Mark Yes or No: does anyone who is age 18 or over attend school, other than high school, half-time or more? If yes, enter who.
14. Monthly medical expenses and 15. A felony involving drugs
Mark Yes or No: does someone in your unit who is 60 or older or disabled have monthly medical expenses of $36 or more? (checked October 20, 2026)
Mark Yes or No: has any person who is receiving Cash assistance from DHS been convicted of a felony involving drugs?
SIGNATURE
Enter your Printed Name, sign on Signature and enter the Date and your Daytime or Cell Phone Number.
Sources
[1] IL 444-4765 (R-05-16) Redetermination Application, Illinois Department of Human Services (the Official source link on this page).