

Mirena Specialty Pharmacy Prescription Request Form at a glance
What it is: The Mirena Specialty Pharmacy Prescription Request Form is the request form for Rx Mirena (levonorgestrel-releasing intrauterine system).
Who signs: Sign the prescription: Product Substitution Permitted (Signature) Date or Dispense As Written (Signature) Date.
What to bring and attach to Mirena Specialty Pharmacy Prescription Request Form
Include copies of the patient's pharmacy benefit and medical insurance cards.
A filled-in Mirena Specialty Pharmacy Prescription Request Form example: a clinic orders Mirena for a patient
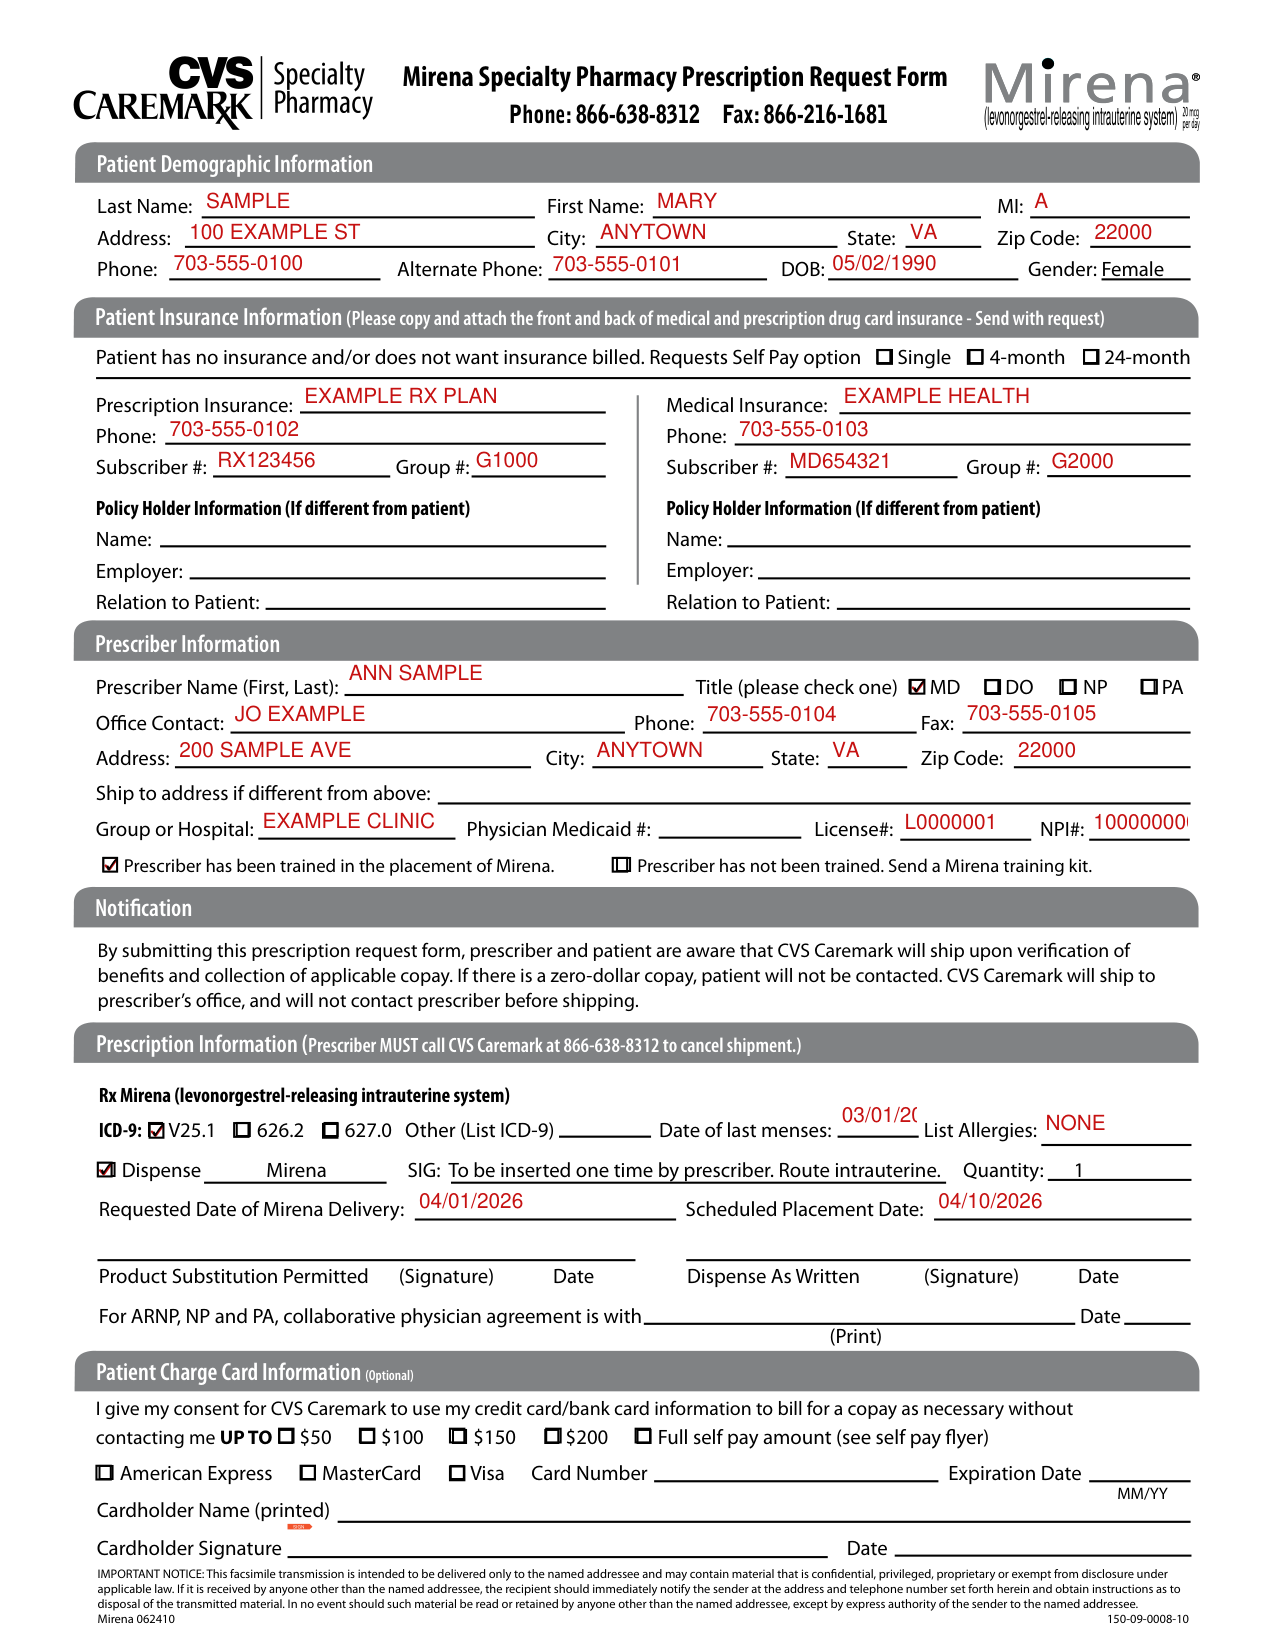
How to fill out Mirena Specialty Pharmacy Prescription Request Form, box by box
Patient demographic information

Under Patient Demographic Information, enter Last Name, First Name, MI, Address, City, State, Zip Code, Phone, Alternate Phone and DOB.
Patient insurance information and Self Pay

Copy and attach the front and back of medical and prescription drug card insurance. Send with request.
Enter Prescription Insurance and Medical Insurance, each with Phone, Subscriber # and Group #.
If the patient has no insurance and/or does not want insurance billed, the patient requests the Self Pay option: Single, 4-month or 24-month.
Policy holder information

Under Policy Holder Information (If different from patient), enter Name, Employer and Relation to Patient.
Prescriber information
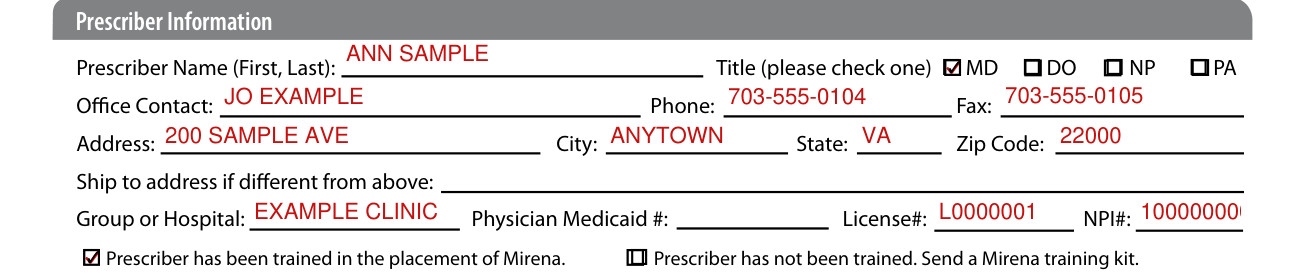
Under Prescriber Information, enter Prescriber Name (First, Last) and check one Title: MD, DO, NP or PA.
Enter Office Contact, Phone, Fax, Address, City, State and Zip Code.
Enter "Ship to address if different from above" if different from the Address in Prescriber Information.
Enter Group or Hospital, Physician Medicaid #, License# and NPI#.
Check Prescriber has not been trained (send a Mirena training kit) or Prescriber has been trained in the placement of Mirena.
Prescription information
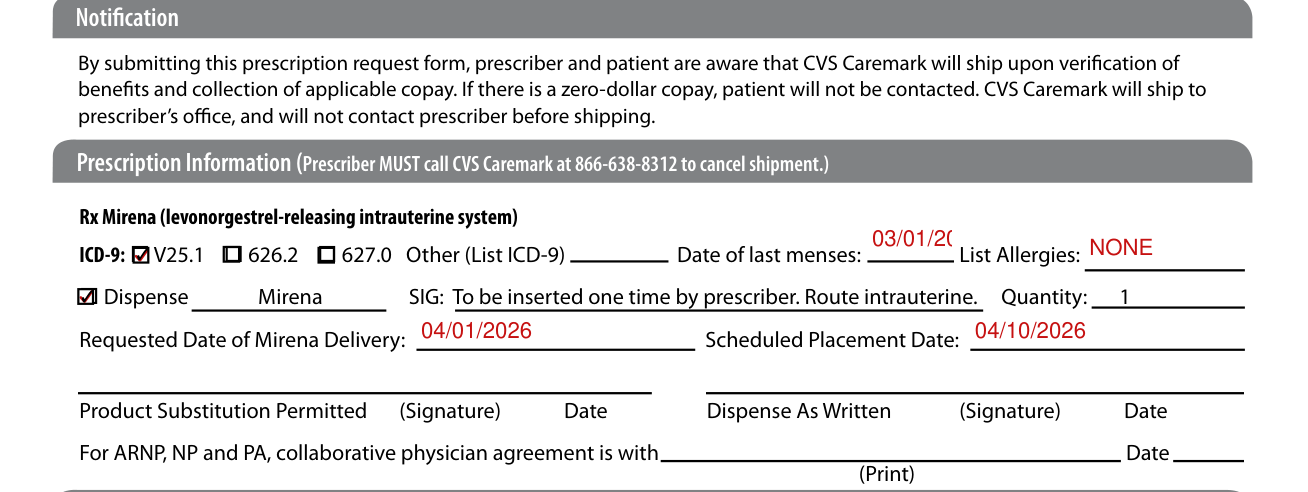
Indicate appropriate diagnosis code: ICD-9 V25.1, 626.2, 627.0 or Other (List ICD-9).
Enter Date of last menses and List Allergies.
Check Dispense Mirena. SIG: To be inserted one time by prescriber. Route intrauterine. Quantity: 1
Enter Requested Date of Mirena Delivery and Scheduled Placement Date.
For ARNP, NP and PA, identify who your collaborative agreement is with if requested to write prescriptions in your state.
Prescriber MUST call CVS Caremark at 866-638-8312 to cancel shipment.
Patient charge card information (optional)

3. Read the Notification section on the Prescription Request Form and request that your patient provide her charge card authorization.
Patient Charge Card Information is optional. Check the amount, or Full self pay amount (see self pay flyer), up to which the cardholder gives consent for CVS Caremark to use credit card/bank card information to bill for a copay as necessary without contacting the cardholder.
The applicable copay will be automatically billed to the patient's credit card.
Check American Express, MasterCard or Visa, then enter Card Number, Expiration Date and Cardholder Name (printed).
The cardholder signs Cardholder Signature and enters the Date.
More rules for Mirena Specialty Pharmacy Prescription Request Form
1. Enter the patient and health care provider information in the space provided on the Prescription Request Form including the patient's pharmacy drug benefit and medical insurance information.
By submitting this prescription request form, prescriber and patient are aware that CVS Caremark will ship upon verification of benefits and collection of applicable copay.
If there is a zero-dollar copay, patient will not be contacted. CVS Caremark will ship to prescriber's office, and will not contact prescriber before shipping.
Patients can contact CVS Caremark at 866-638-8312 after the prescription is faxed in to verify co-pays.
Provide your patient with the appointment reminder card.
6. Bill the patient's insurance for the procedure and your customary professional services charges only.
Common questions about Mirena Specialty Pharmacy Prescription Request Form
Where do I file it?
5. Fax the completed Prescription Form to CVS Caremark Specialty Pharmacy at 866-216-1681, or for questions call their Mirena team at 866-638-8312.
Sources
[1] Mirena Specialty Pharmacy Prescription Request Form, CVS Caremark and Bayer (no issuer file found) (the Official source link on this page).