

Disability Certificate (OCF-3) at a glance
What it is: The Disability Certificate (OCF-3) is for accidents that occur on or after November 1, 1996.
Who signs: Sign Signature of Applicant or Substitute Decision Maker, enter Name of Applicant or Substitute Decision Maker (please print) and Date (yyyy/mm/dd).
A filled-in Disability Certificate (OCF-3) example: an applicant completes Part 1

How to fill out Disability Certificate (OCF-3), box by box
Claim Number, Policy Number and Date of Accident

Enter the Claim Number, the Policy Number and the Date of Accident (yyyy/mm/dd).
Return this form to

Fill in Return this form to
Use this form for accidents that occur on or after November 1, 1996. If your insurance company asks you to complete this form, fill out Parts 1 to 3 and give the form to your health practitioner (chiropractor, dentist, nurse practitioner, occupational therapist, optometrist, physician, physiotherapist, psychologist, speech language pathologist). After your health practitioner has explained your accident-related injury to you, sign Part 4. Your health practitioner will complete the rest of the form, based on their most recent assessment, and return it to the insurance company.
Part 1 - Applicant Information: name, address, telephone and e-mail

Part 1 - Applicant Information is to be completed by the applicant: enter Last Name, First Name and Middle Name.
Enter Street Address, City/Town, Province and Postal Code.
Enter Date of Birth (yyyy/mm/dd), Gender, Telephone Number and E-mail (optional).
Working, Employment Insurance, primary caregiver and education
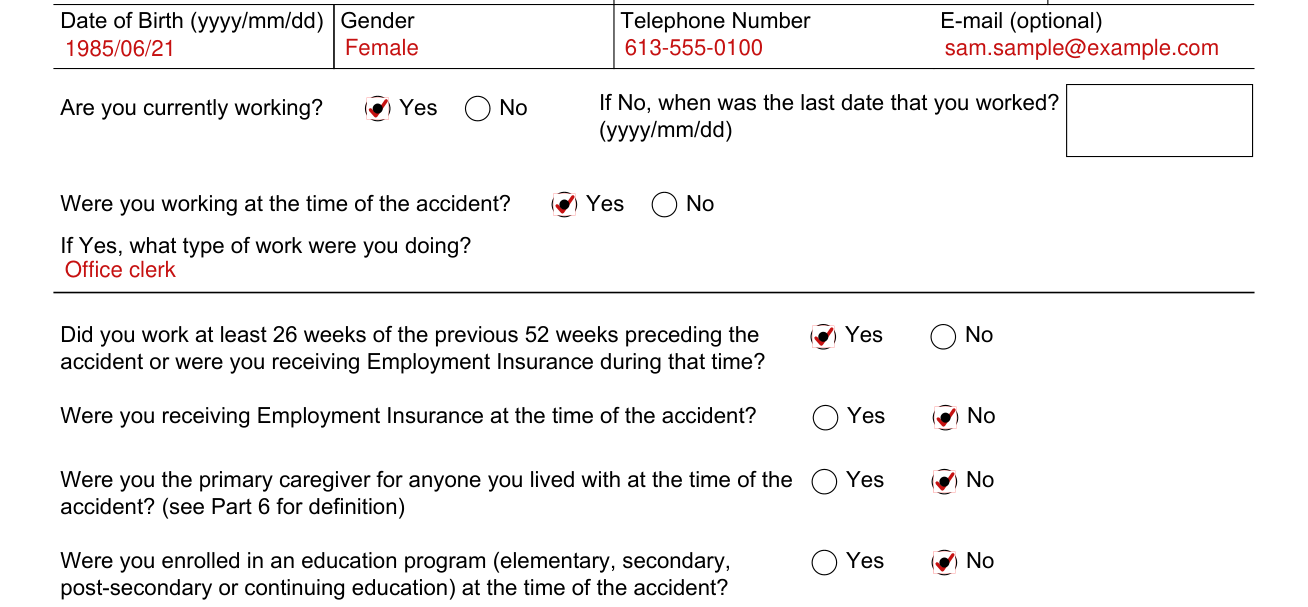
Mark Yes or No: Are you currently working? If No, enter when was the last date that you worked? (yyyy/mm/dd).
Mark Yes or No: Were you working at the time of the accident? If Yes, enter what type of work were you doing?
Mark Yes or No: Did you work at least 26 weeks of the previous 52 weeks preceding the accident or were you receiving Employment Insurance during that time?
Mark Yes or No: Were you receiving Employment Insurance at the time of the accident?
Mark Yes or No: Were you the primary caregiver for anyone you lived with at the time of the accident? (see Part 6 for definition)
Mark Yes or No: Were you enrolled in an education program (elementary, secondary, post-secondary or continuing education) at the time of the accident?
Part 2 - Insurance Company Information

Part 2 - Insurance Company Information is to be completed by the applicant: enter Insurance Company Name and City or Town of Branch Office (if applicable).
Enter Name of Insurance Company Representative, E-mail (optional), Telephone Number and Fax.
Name of Policy Holder same as Applicant, OR Policy Holder First Name and Last Name

Mark Name of Policy Holder same as Applicant, OR enter Policy Holder First Name and Policy Holder Last Name.
Part 3 - Accident Description

Part 3 - Accident Description is to be completed by the applicant: give a brief description of the accident and what happened to you, and describe any injuries you sustained as a direct result of the accident.
Mark Additional sheets attached.
Part 4 - Applicant Signature

Part 4 - Applicant Signature authorizes the treating health professional to collect, use and disclose to the insurer or to a health professional, social worker, or rehabilitation expert properly identified by the insurer to conduct an examination, only such information relating to the applicant's health condition and treatment received as a result of the automobile accident and any pre-existing or subsequently occurring health conditions that may be barriers to recovery as a result of the automobile accident, as is reasonably required for the purpose of providing treatment and determining eligibility for benefits.
The health practitioner who completes this form may contact the employer, if this is necessary, to confirm the essential tasks of the employment and the nature and extent of any available work with modified hours or duties.
This authorization does not apply to a consultation between the health care provider and the insurer's health professional conducting an examination. Separate express consent is required for this consultation. This consent should be in writing.
Certify that the information provided is true and correct.
It is an offence under the Insurance Act to knowingly make a false or misleading statement or representation to an insurer under a contract of insurance. It is an offence under the Criminal Code for anyone, by deceit, falsehood, or other dishonest act, to defraud or attempt to defraud an insurance company.
Part 5 - Injury and Sequelae Information
To the Health Practitioner: Please complete the following information based on your most recent examination of the applicant named in Part 1 and return the form to the insurance company listed in Part 2. Please print clearly.
Part 5 - Injury and Sequelae Information is to be completed by the health practitioner: provide a description (list most significant first) and associated ICD-10-CA code for any injuries and sequelae that are the direct result of the automobile accident. (Refer to the User manual at www.hcaiinfo.ca for ICD-10-CA coding information.)
Fill in Description and Code.
Part 10 - Health Practitioner Signature
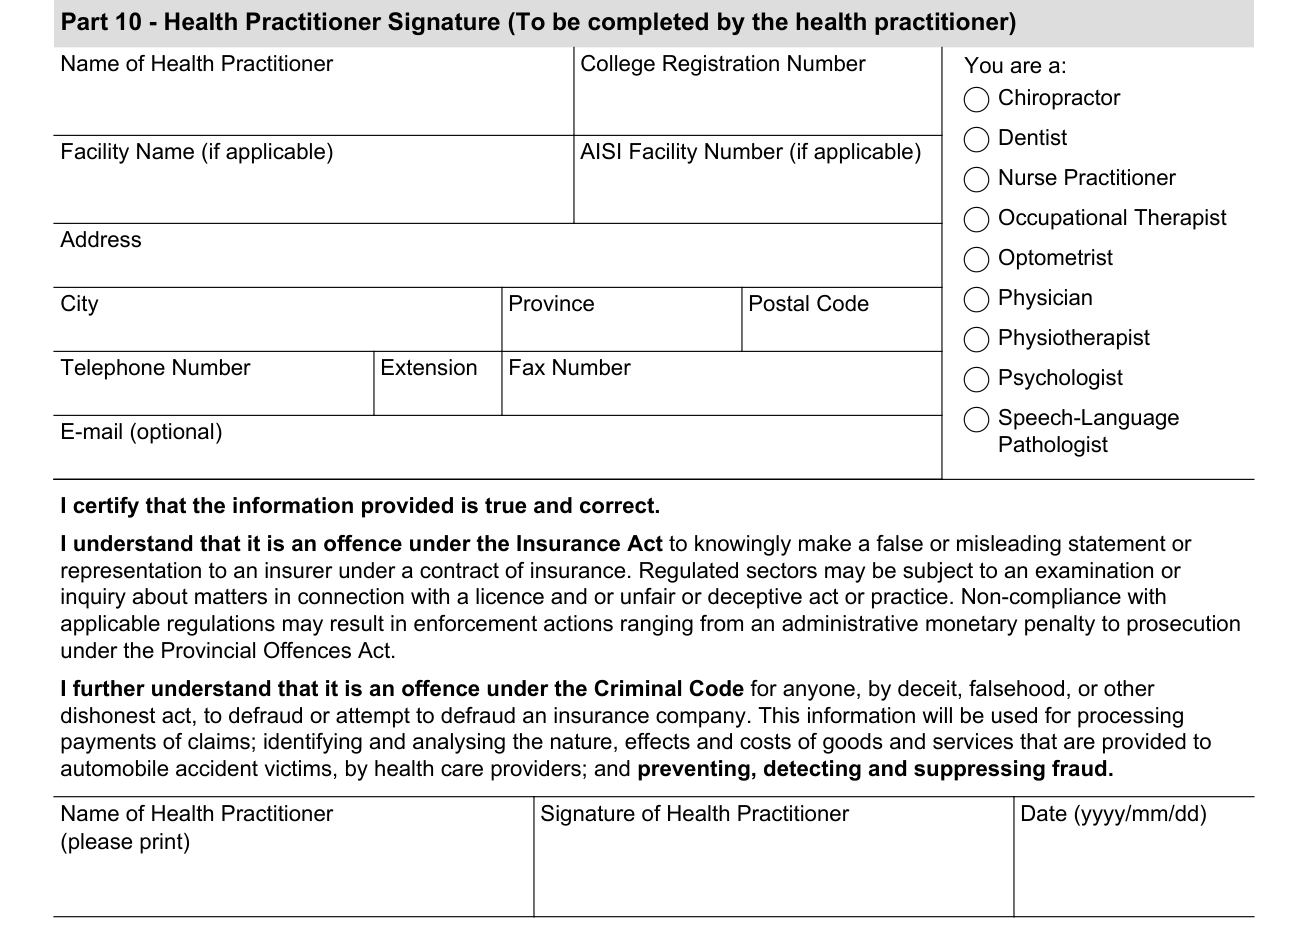
Part 10 - Health Practitioner Signature is to be completed by the health practitioner: enter Name of Health Practitioner and College Registration Number.
Mark one under You are a: Chiropractor, Dentist, Nurse Practitioner, Occupational Therapist, Optometrist, Physician, Physiotherapist, Psychologist or Speech-Language Pathologist.
Enter Facility Name (if applicable), AISI Facility Number (if applicable), Address, City, Province, Postal Code, Telephone Number, Extension, Fax Number and E-mail (optional).
Regulated sectors may be subject to an examination or inquiry about matters in connection with a licence and or unfair or deceptive act or practice. Non-compliance with applicable regulations may result in enforcement actions ranging from an administrative monetary penalty to prosecution under the Provincial Offences Act.
Sign Signature of Health Practitioner, enter Name of Health Practitioner (please print) and Date (yyyy/mm/dd).
Common questions about Disability Certificate (OCF-3)
What is the OCF 3?
The Disability Certificate (OCF-3) is for accidents that occur on or after November 1, 1996. Only an authorized health practitioner can complete this form. The health practitioner's opinion will be relied upon by people who review the certificate to make important decisions. Accordingly, it is necessary to be accurate and complete. Please print clearly and provide all information requested. This form may not be materially altered.
Are there fees?
The fee for completing this certificate must be billed to the insurer directly.
Sources
[1] Form AF-125E (2026), Disability Certificate (OCF-3), King's Printer for Ontario (the Official source link on this page).