
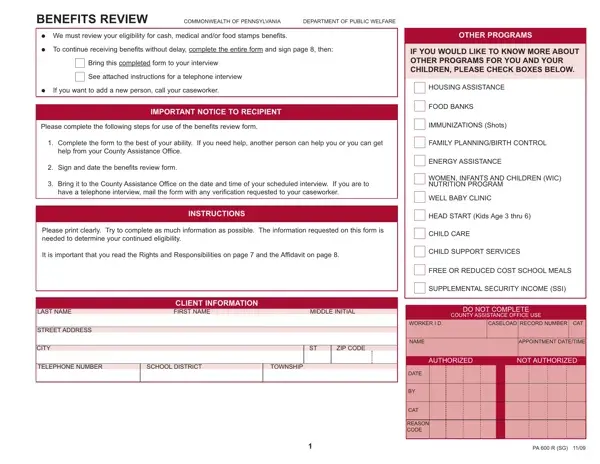
Form PA 600 R at a glance
What it is: Benefits Review is an application for cash, health care and SNAP benefits. If you need it in another language or someone to interpret, contact your local county assistance office.
Who signs: Sign and date the Benefits Review form on page 1 and on Understanding Your Rights and Responsibilities.
A filled-in Form PA 600 R example: a Pennsylvania resident fills out the first page
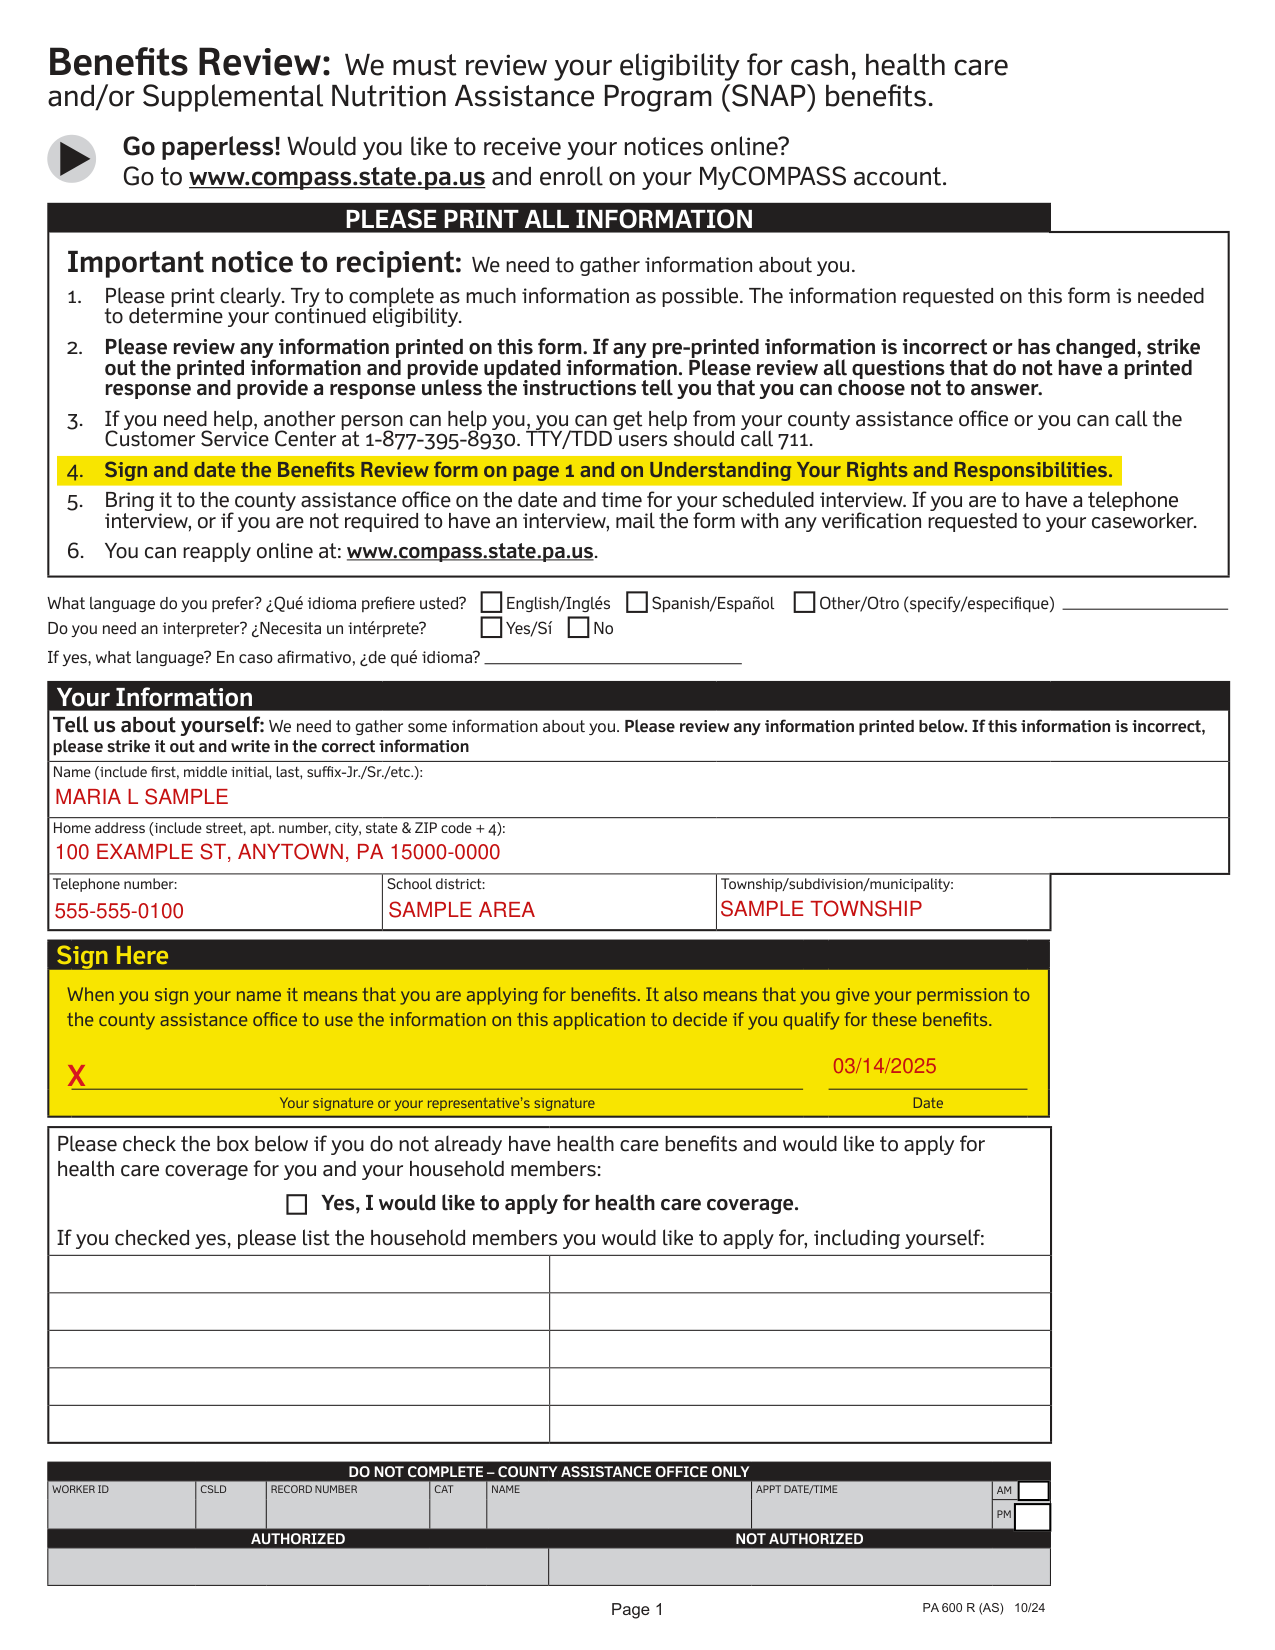
How to fill out Form PA 600 R, box by box
Your Information

Please review any information printed in Your Information. If this information is incorrect, please strike it out and write in the correct information.
Enter your Name (include first, middle initial, last, suffix-Jr./Sr./etc.).
Enter your Home address (include street, apt. number, city, state & ZIP code + 4).
Enter your Telephone number, School district and Township/subdivision/municipality.
Sign Here

When you sign your name it means that you are applying for benefits. It also means that you give your permission to the county assistance office to use the information on this application to decide if you qualify for these benefits.
Sign on the line for Your signature or your representative's signature and enter the Date.
Apply for health care coverage
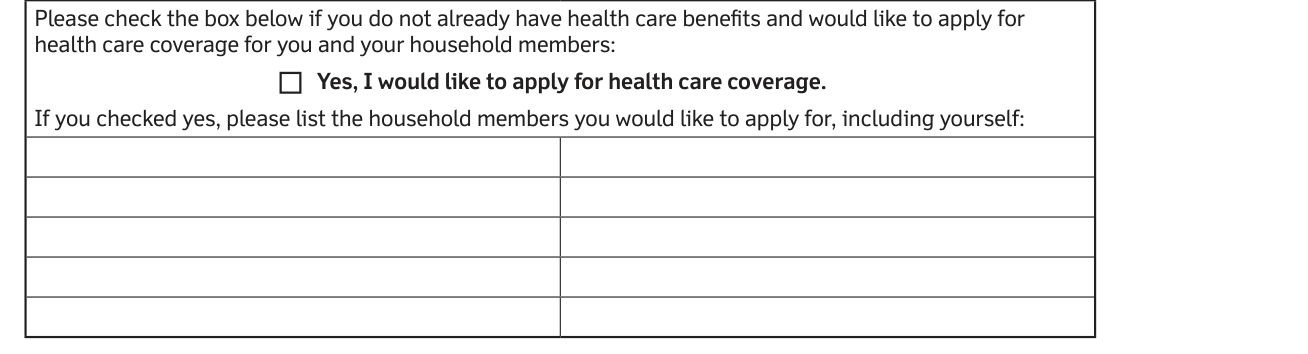
Please check the box if you do not already have health care benefits and would like to apply for health care coverage for you and your household members:
If you checked yes, please list the household members you would like to apply for, including yourself:
More rules for Form PA 600 R
Please print clearly. Try to complete as much information as possible. The information requested on this form is needed to determine your continued eligibility.
Please review any information printed on this form. If any pre-printed information is incorrect or has changed, strike out the printed information and provide updated information.
Please review all questions that do not have a printed response and provide a response unless the instructions tell you that you can choose not to answer.
If you need help, another person can help you, you can get help from your county assistance office or you can call the Customer Service Center at 1-877-395-8930.
If your situation is different
What language do you prefer?
What language do you prefer? English/Inglés, Spanish/Español or Other/Otro (specify/especifique).
Do you need an interpreter? Yes/Sí or No. If yes, what language? En caso afirmativo, ¿de qué idioma?
Tell Us About People In Your Home
Include information about everyone who lives at your address, even if they are not applying for benefits. For health care applicants, be sure to include anyone on your federal income tax return, even if they do not live with you. Note: You do not need to file a tax return to get benefits.
Enter Person 1 Name (include first, middle initial, last, suffix-Jr./Sr./etc.).
Enter your Social Security number.
Enter your Birthdate (MM/DD/YYYY).
Are you interested in any other services?
Are you interested in any other services? Put a check in the box if you are interested in any of these other services:
Resources
List all resources such as cash, vehicles, stocks, bonds, bank accounts, property, life insurance, etc.
Income
List all income such as wages, self-employment, pensions, Social Security benefits, Unemployment Compensation, Workers' Compensation, support, gambling/lottery, etc.
Health Insurance
Health Insurance: You do not need to answer these questions if you are applying only for SNAP.
If you have (or had in the last 90 days) more than one type of health care coverage, please fill in a box for each policy.
Note: If you have more than one policy, you will need to make a copy of the pages and attach them.
Expenses
This section is for SNAP applicants. Please tell about your expenses so that you can get the most benefits possible.
If requested, you must provide proof of your expenses.
Absent Relatives
Absent Relatives: This section is for cash applicants. If anyone is applying for a child who has parents not living in your home or if anyone applying has a spouse not living in your home, please answer these questions. You do not need to fill out this section if providing this information or seeking support would put you or family members at risk of domestic violence or make it more difficult to escape domestic violence, or if your child was born as a result of rape or incest, or if you are considering adoption.
Criminal History Inquiry
Criminal History Inquiry: You do not need to answer these questions if you are applying only for health care.
Voter Registration (Optional)
Voter Registration (Optional): This section is for U.S. Citizens only. Applying to register or declining to register to vote will not affect the amount of assistance you will be provided by this agency.
Reporting changes after you apply
Reporting changes: Changes you are required to report must be reported within the first 10 days of the month following the month of change or, for Long-Term Care and Home and Community-Based Services, within 10 days of the change.
Common questions about Form PA 600 R
Where do I file it?
Bring it to the county assistance office on the date and time for your scheduled interview. If you are to have a telephone interview, or if you are not required to have an interview, mail the form with any verification requested to your caseworker.
Is there a penalty?
Under 62 P.S. section 483, any person knowingly violating any of the rules and regulations of this department shall be guilty of a misdemeanor and, upon conviction shall be sentenced to pay a fine, not exceeding one hundred ($100) dollars, or to undergo imprisonment, not exceeding six months, or both (checked November 8, 2026).
Sources
[1] Form PA 600 R (AS) 10/24, Benefits Review, Pennsylvania Department of Human Services (the Official source link on this page).