
SAIF Form 801 at a glance
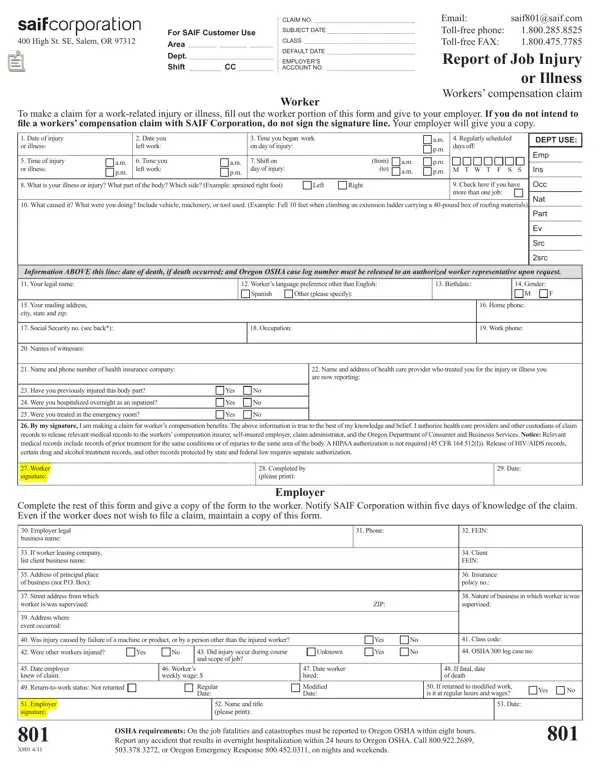
What it is: SAIF Form 801: Report of Job Injury or Illness, a workers' compensation claim.
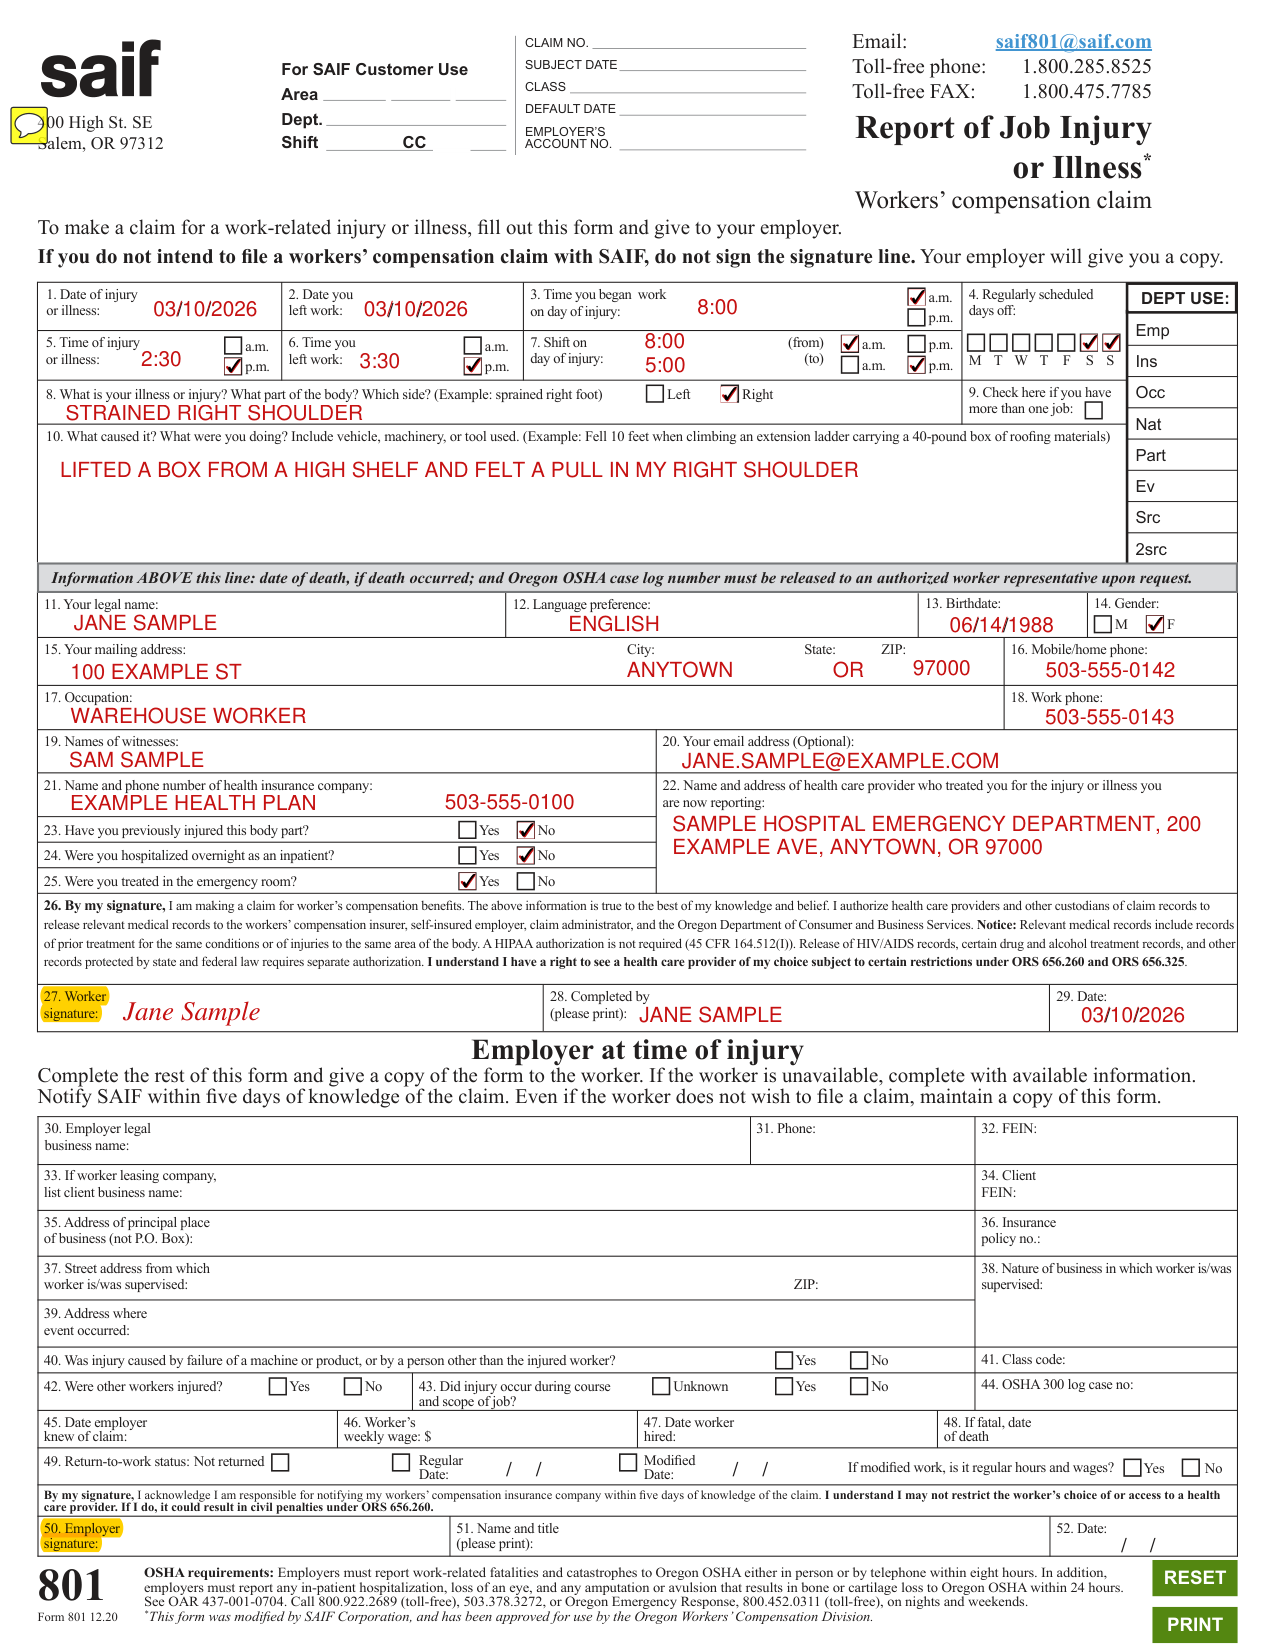
Who signs: Sign on the line in box 27, Worker signature. The employer signs in box 50, Employer signature.
A filled-in SAIF Form 801 example: a worker reports a shoulder injury
How to fill out SAIF Form 801, box by box
Dates, times and days off
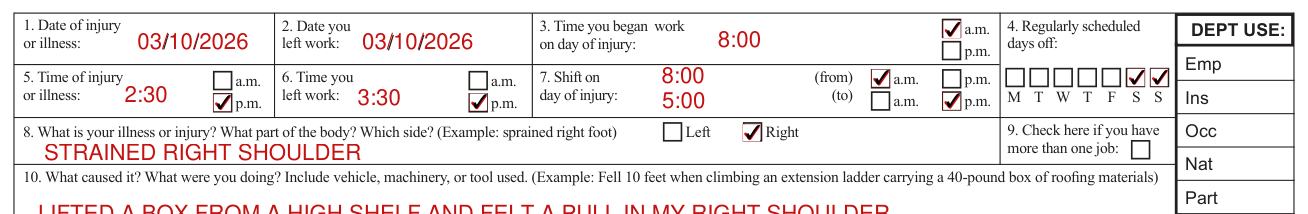
Enter the Date of injury or illness in box 1 and the Date you left work in box 2.
Enter the Time you began work on day of injury in box 3 and the Regularly scheduled days off in box 4. Enter the Time of injury or illness in box 5, the Time you left work in box 6 and the Shift on day of injury, from and to, in box 7.
Your illness or injury and what caused it

In box 8: What is your illness or injury? What part of the body? Which side? (Example: sprained right foot) Mark Left or Right.
In box 10: What caused it? What were you doing? Include vehicle, machinery, or tool used. (Example: Fell 10 feet when climbing an extension ladder carrying a 40-pound box of roofing materials)
Check here if you have more than one job

In box 9, check here if you have more than one job.
Your legal name, mailing address, phone and occupation
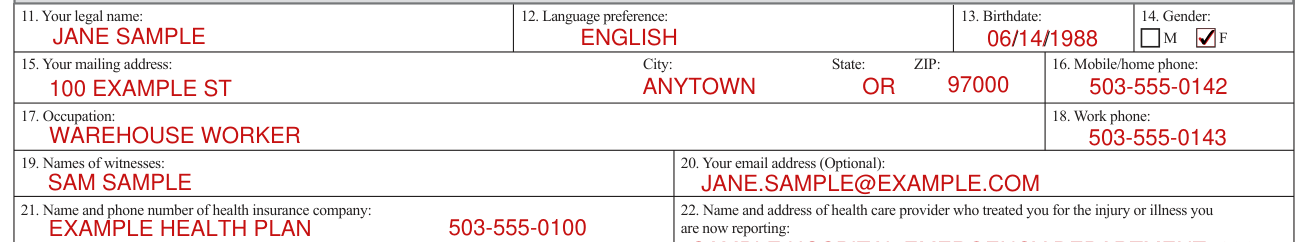
Enter your legal name in box 11, your Language preference in box 12, your Birthdate in box 13 and your Gender, M or F, in box 14.
Enter your mailing address in box 15 with City, State and ZIP, and your Mobile/home phone in box 16.
Enter your Occupation in box 17, your Work phone in box 18 and the Names of witnesses in box 19. Your email address in box 20 is Optional.
Health care, insurance and your signature

Enter the Name and phone number of health insurance company in box 21. Enter the Name and address of health care provider who treated you for the injury or illness you are now reporting in box 22.
In boxes 23, 24 and 25, mark Yes or No: Have you previously injured this body part? Were you hospitalized overnight as an inpatient? Were you treated in the emergency room?
By your signature, you are making a claim for worker's compensation benefits. The information is true to the best of your knowledge and belief. You authorize health care providers and other custodians of claim records to release relevant medical records to the workers' compensation insurer, self-insured employer, claim administrator, and the Oregon Department of Consumer and Business Services. Relevant medical records include records of prior treatment for the same conditions or of injuries to the same area of the body. A HIPAA authorization is not required (45 CFR 164.512(I)). Release of HIV/AIDS records, certain drug and alcohol treatment records, and other records protected by state and federal law requires separate authorization. You have a right to see a health care provider of your choice subject to certain restrictions under ORS 656.260 and ORS 656.325.
Sign on the line in box 27, Worker signature. The employer signs in box 50, Employer signature.
Enter Completed by (please print) in box 28 and the Date in box 29.
Employer at time of injury
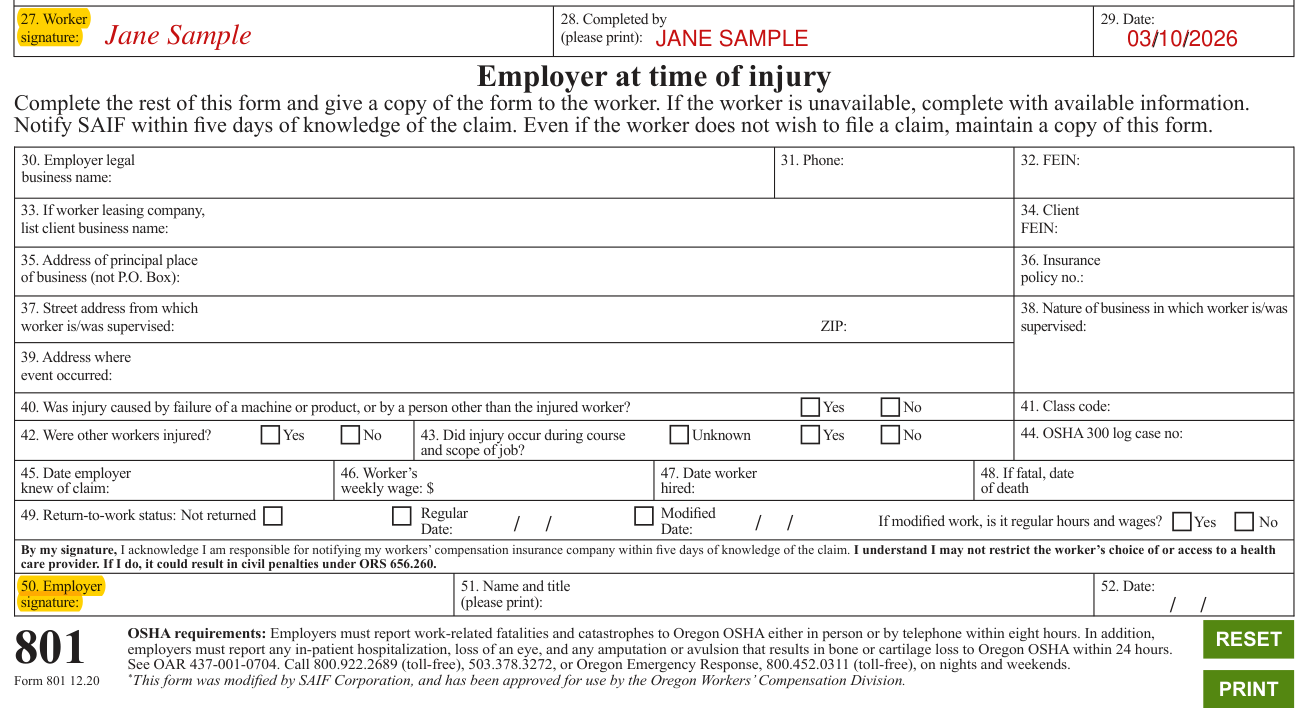
Employer at time of injury: Complete the rest of this form and give a copy of the form to the worker. If the worker is unavailable, complete with available information. Notify SAIF within five days of knowledge of the claim. Even if the worker does not wish to file a claim, maintain a copy of this form.
Enter the Employer legal business name in box 30, the Phone in box 31 and the FEIN in box 32. If worker leasing company, list client business name in box 33. Enter the Client FEIN in box 34.
Enter the Address of principal place of business (not P.O. Box) in box 35 and the Insurance policy no. in box 36. Enter the Street address from which worker is/was supervised, with its ZIP, in box 37. Enter the Nature of business in which worker is/was supervised in box 38 and the Address where event occurred in box 39.
In box 40, mark Yes or No: Was injury caused by failure of a machine or product, or by a person other than the injured worker? Enter the Class code in box 41. In box 42, mark Yes or No: Were other workers injured? In box 43, mark Yes, No or Unknown: Did injury occur during course and scope of job? Enter the OSHA 300 log case no in box 44, the Date employer knew of claim in box 45, the Worker's weekly wage in box 46, the Date worker hired in box 47 and, if fatal, the date of death in box 48.
In box 49, mark the Return-to-work status: Not returned, Regular or Modified, with a Date. If modified work, mark Yes or No: is it regular hours and wages?
Sign in box 50, Employer signature. By your signature, you acknowledge you are responsible for notifying your workers' compensation insurance company within five days of knowledge of the claim. You understand you may not restrict the worker's choice of or access to a health care provider. If you do, it could result in civil penalties under ORS 656.260. Enter the Name and title (please print) in box 51 and the Date in box 52.
More rules for SAIF Form 801
You do not need to have an SSN to get workers' compensation benefits. If you have an SSN, the Workers' Compensation Division (WCD) of the Department of Consumer and Business Services will get it from your employer, the workers' compensation insurer, or other sources.
Notify your employer and a health care provider of your choice about your job-related injury or illness as soon as possible. Your employer cannot choose your health care provider for you. Ask your employer the name of its workers' compensation insurer. Complete Form 801, “Report of Job Injury or Illness,” available from your employer and Form 827, “Workers' and Health Care Provider's Report for Workers' Compensation Claim,” available from your health care provider.
In order for you to receive payments for time off work, your health care provider must send written authorization to the insurer. Generally, you will not be paid for the first three calendar days for time off work. You may be paid for lost wages for the first three calendar days if you are off work for 14 consecutive days or hospitalized overnight. If your claim is denied within the first 14 days, you will not be paid for any lost wages. Keep your employer informed about what is going on and cooperate with efforts to return you to a modified- or light-duty job.
SAIF or your employer should be able to answer your questions. Call SAIF at 800.285.8525.
Common questions about SAIF Form 801
Where do I file it?
To make a claim for a work-related injury or illness, fill out this form and give it to your employer. If you do not intend to file a workers' compensation claim with SAIF, do not sign the signature line. Your employer will give you a copy.
Sources
[1] SAIF Form 801 (12.20), Report of Job Injury or Illness, SAIF Corporation (the Official source link on this page).