

Sanofi Patient Connection Patient Assistance Connection application at a glance
What it is: The Sanofi Patient Connection APPLICATION is for the Program that provides select Sanofi prescription medications and vaccines, at no cost, if you meet certain eligibility requirements.
Who signs: Please fill out and return this form (prescriber and patient signature required for all applications)
You must be a resident of the U.S. or the U.S. territories and be under the care of a licensed HCP authorized to prescribe, dispense, and administer medicine in the U.S.
You must have an annual household income of ≤400% of the current Federal Poverty Level. If you may be eligible for Medicaid, you will be required to provide documentation of Medicaid denial before being assessed for patient assistance eligibility. If you are enrolled in Medicare Part D, you may also be eligible based on the annual household income criteria.
You must have no insurance coverage or, for commercially insured patients, have no access to the prescribed product or treatment via your insurance.
For vaccines, you must be 19 years of age or older (except for Imovax® Rabies). For THYROGEN®, you must be 18 years of age or older.
What to bring and attach to Sanofi Patient Connection Patient Assistance Connection application
Please provide a copy of the patient's insurance card[s], both front and back, if available.
1If applying for Drug Replacement (ELITEK®, JEVTANA®, LOVENOX®, MOZOBIL®, and THYMOGLOBULIN®), a copy of the claim, denial, flow sheet(s), and drug dispensing log (with patient name, date of service, product NDC/Lot #, total dosage) must be submitted.
A filled-in Sanofi Patient Connection Patient Assistance Connection application example: a patient fills out page 2 for the Sharps program
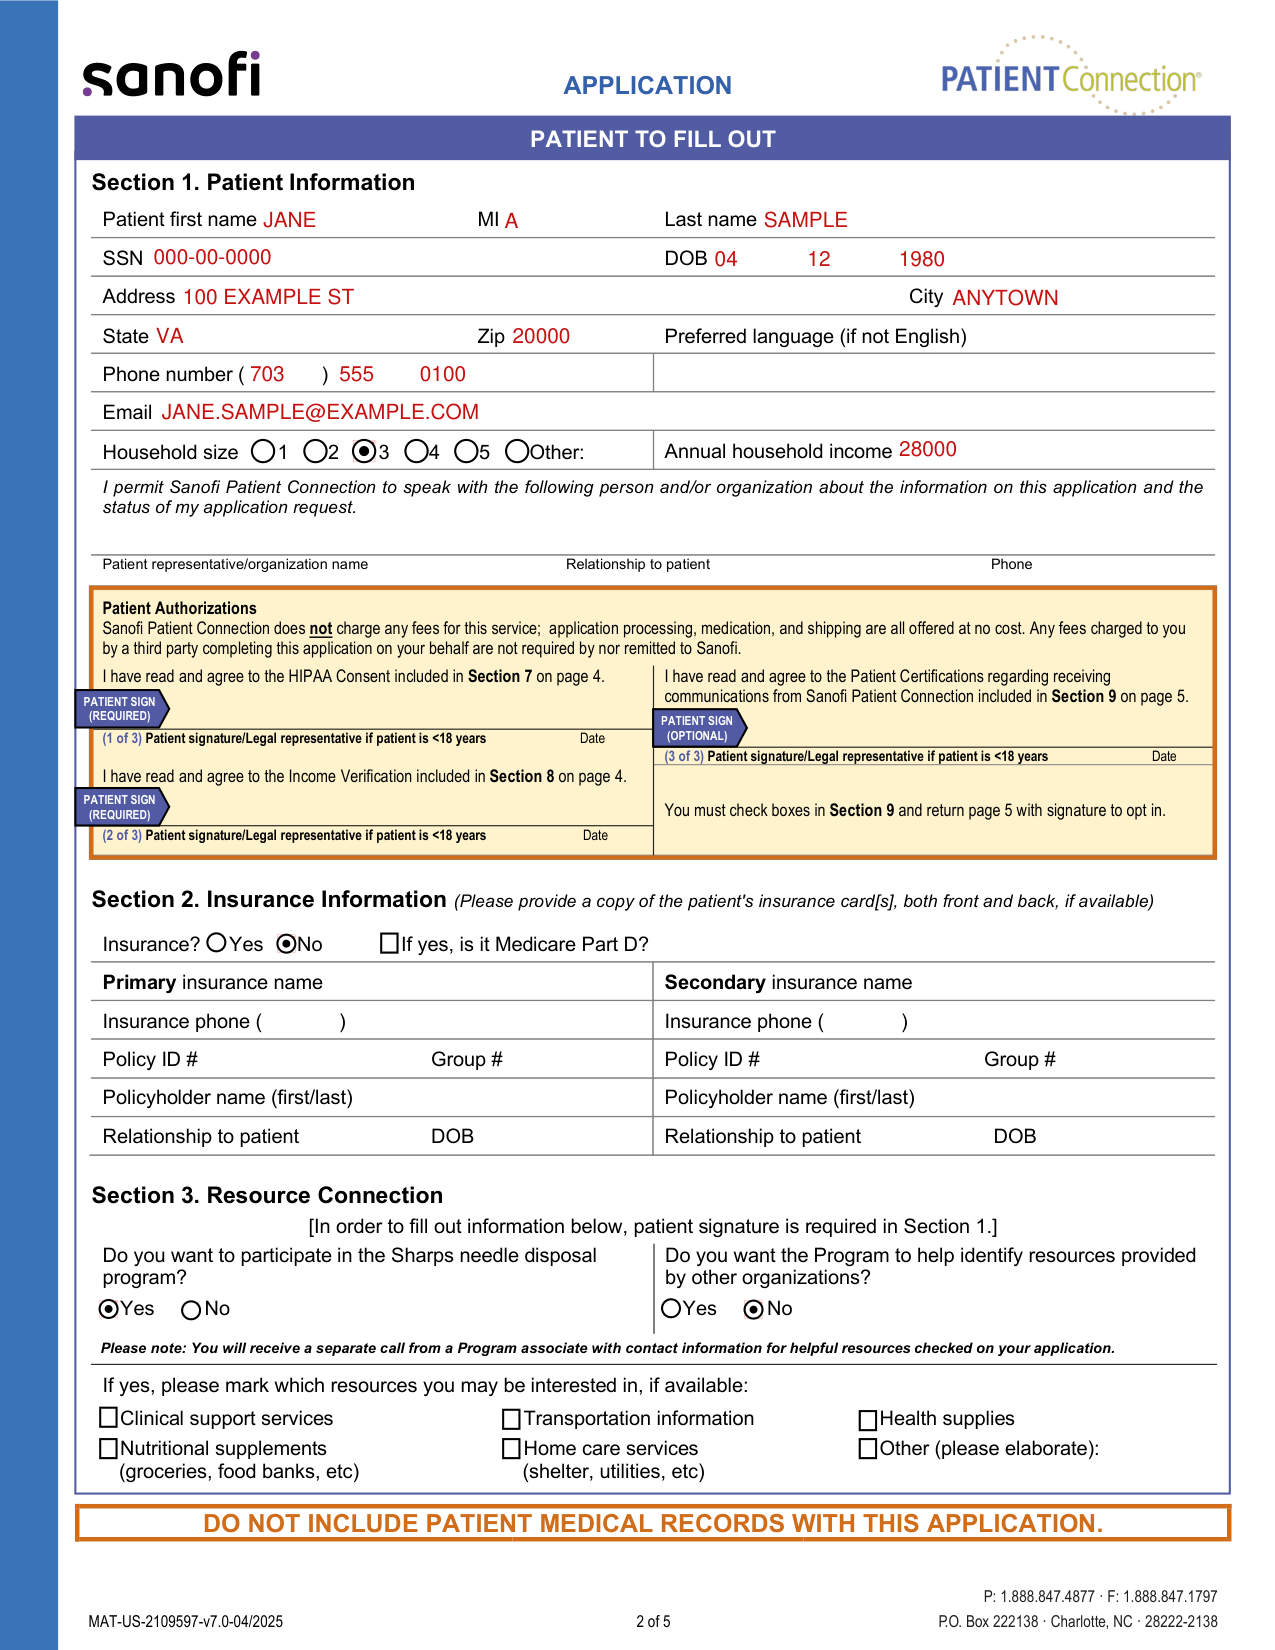
How to fill out Sanofi Patient Connection Patient Assistance Connection application, box by box
Household size
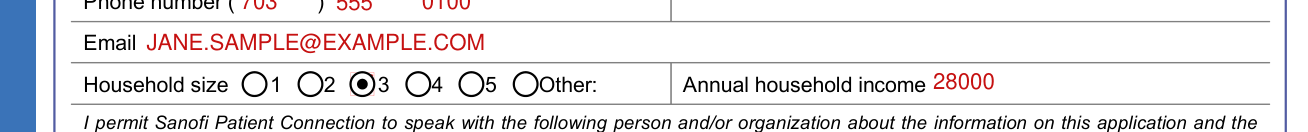
Under Household size, mark 1, 2, 3, 4, 5 or Other:, and enter your Annual household income.
Speak with the following person and/or organization

To permit Sanofi Patient Connection to speak with a person or organization about the information on this application and the status of your application request, enter the Patient representative/organization name, the Relationship to patient and the Phone.
Insurance Information
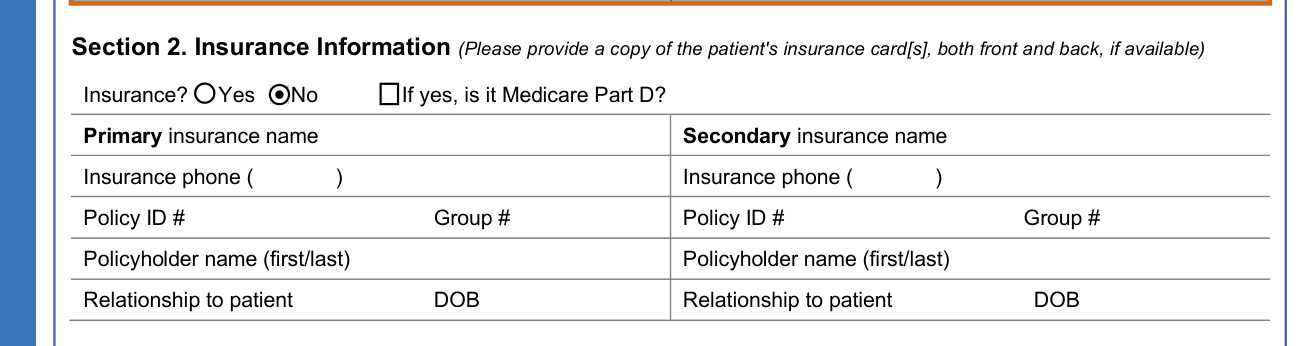
Mark Insurance? Yes or No. If yes, is it Medicare Part D?
For the Primary insurance and the Secondary insurance, enter the insurance name, Insurance phone, Policy ID #, Group #, Policyholder name (first/last), Relationship to patient and DOB.
Resource Connection
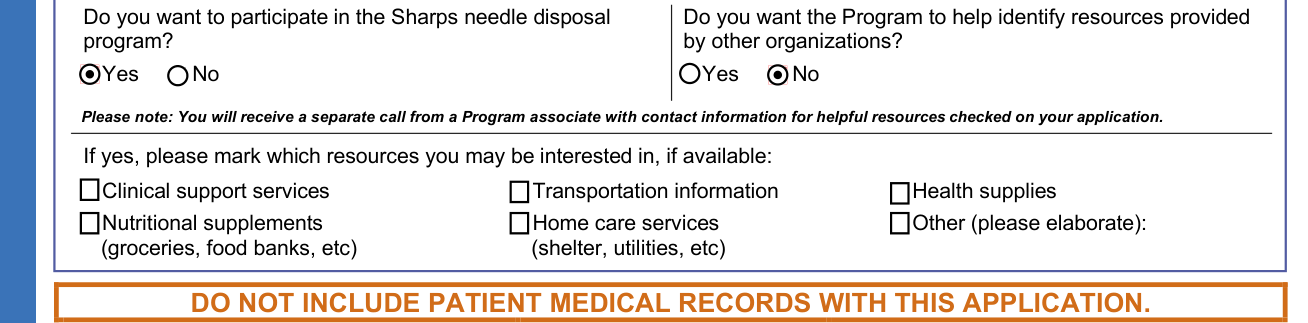
Section 3. Resource Connection: In order to fill out information below, patient signature is required in Section 1. Mark Yes or No to Do you want to participate in the Sharps needle disposal program?
Mark Yes or No to Do you want the Program to help identify resources provided by other organizations? If yes, please mark which resources you may be interested in, if available.
Clinical support services, Transportation information, Health supplies, Nutritional supplements, Home care services, and Other (please elaborate).
You will receive a separate call from a Program associate with contact information for helpful resources checked on your application.
Patient signature/Legal representative
Sign and date the REQUIRED patient authorizations for the HIPAA Consent and the Income Verification on each Patient signature/Legal representative if patient is <18 years line that is marked (REQUIRED), and enter the Date. The line marked (OPTIONAL) is not required.
The patient has read and agrees to the HIPAA Consent included in Section 7 on page 4. The patient has read and agrees to the Income Verification included in Section 8 on page 4.
Section 4. Treatment and Prescribing Information

Under Section 4. Treatment and Prescribing Information (See Section 6 for supported products), enter the Patient name and DOB. For Product #1 and Product #2, mark Vials, Pens or N/A, and enter the ICD-10 Code, Frequency, Maximum dose per day and Qty.
Section 5. Prescriber Information
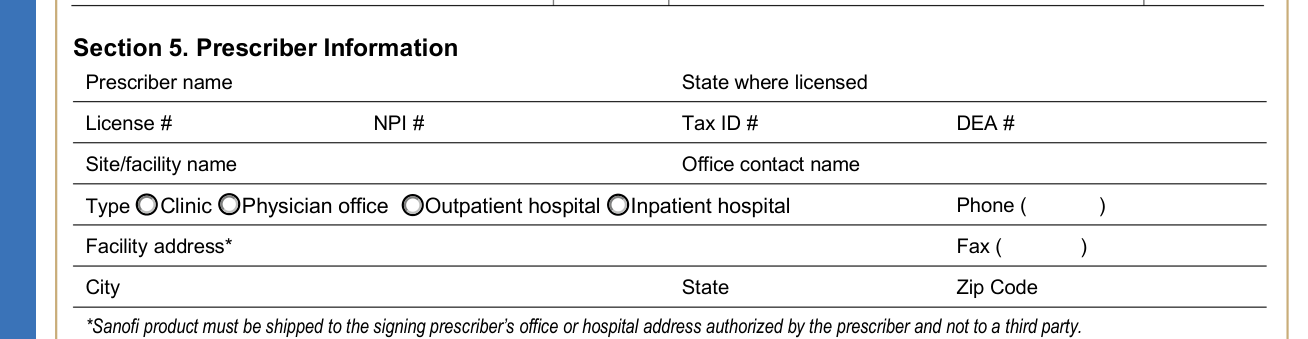
Under Section 5. Prescriber Information, enter the Prescriber name, State where licensed, License #, NPI #, Tax ID # and DEA #. Enter the Site/facility name, Office contact name, Facility address, City, State and Zip Code.
Mark the Type: Clinic, Physician office, Outpatient hospital or Inpatient hospital. Enter the Phone and the Fax.
For the Facility address*, Sanofi product must be shipped to the signing prescriber's office or hospital address authorized by the prescriber and not to a third party.
The prescriber certifies that the information provided is current, complete, and accurate to the best of the prescriber's knowledge. The prescriber certifies that the Sanofi product is medically necessary for this patient and that the prescriber is authorized under state law to prescribe and dispense the requested medication.
The prescriber signs the Prescriber signature (REQUIRED - no stamps) line, with the Printed name and Date.
Section 9. Patient Certification (OPTIONAL)

You must check boxes in Section 9 and return page 5 with signature to opt in.
Section 9. Patient Certification (OPTIONAL). The patient does not have to opt in to receive the Communications and can still receive patient assistance through the Program, as prescribed by the physician.
More rules for Sanofi Patient Connection Patient Assistance Connection application
Patients are free to authorize family, care team members, or third-party representatives to complete and manage their Sanofi Patient Connection application. The application can be fully completed by the patient and their licensed healthcare provider (HCP).
When your application is received, it will be reviewed to see if you qualify for Patient Assistance Connection. If you are eligible: 1. You and your HCP will receive a letter notifying you of enrollment. If you are a Medicare Part D patient, your plan sponsor will also receive a letter notifying it of your enrollment. 2. You will be enrolled for 12 months. If you are a Medicare Part D patient, you will be enrolled through the end of the calendar year. 3. Your medication will be sent directly to your HCP's office in approximately 5-7 business days from when you are approved. If you do not qualify for Patient Assistance Connection, you and your HCP will be sent a letter with the reason for denial.
Sanofi Patient Connection offers patients eligible for patient assistance programs a safe way to dispose of needles through the Sharps program. If you sign up for the Sharps program, you will receive a separate shipment for the Sharps container in order to dispose of your needles.
Sanofi Patient Connection ships most medications in a 90-day supply.
Authorization to Use and Disclose Health Information (REQUIRED) Patient: Please read the following carefully, then date and sign where indicated in Section 1 on page 2.
Section 8. Income Verification (REQUIRED) Patient: Please read the following carefully, then date and sign where indicated in Section 1 on page 2.
Continuation in the SPC Patient Assistance Program is conditioned upon timely verification of income.
Before you go
Complete all relevant information on page 2, and sign and date the REQUIRED patient authorizations for HIPAA consent and income verification on page 2.
Ask your HCP to complete page 3 and sign and date it.
Common questions about Sanofi Patient Connection Patient Assistance Connection application
Who signs it?
Please fill out and return this form (prescriber and patient signature required for all applications)
Where do I file it?
Ask your HCP to mail or fax your completed application (only pages 2 and 3 are needed). Missing information may delay processing of your application. Do not include patient medical records with this application. Your completed application may be submitted by your HCP by U.S. Mail to Sanofi Patient Connection PO Box 222138, Charlotte, NC 28222-2138, or by Fax 1.888.847.1797.
Are there fees?
Sanofi Patient Connection does not charge any fees for this service; application processing, medication, and shipping are all offered at no cost. Any fees charged to you by a third party completing this application on your behalf are not required by nor remitted to Sanofi.
Sources
[1] APPLICATION (MAT-US-2109597-v7.0-04/2025), Sanofi Patient Connection (the Official source link on this page).
