

Form 913 at a glance
What it is: DHHS Form 913 is the Application for South Carolina Medicaid, Breast and Cervical Cancer Program.
Where and when to file: The completed application is faxed to the Breast and Cervical Cancer Program at (803) 255-8223. A Pathology Report indicating the diagnosis and a copy of the applicant's insurance card must be faxed with the application. Note: A cytology report (Pap Smear) is not sufficient.
The Breast and Cervical Cancer Prevention and Treatment Act of 2000 allows states to provide full Medicaid benefits to uninsured women who are found to be in need of treatment for breast or cervical cancer or pre-cancerous lesions (CIN 2/3 or atypical breast hyperplasia).
"A woman diagnosed and found in need of treatment for either breast or cervical cancer or pre-cancerous lesions (CIN 2/3 or atypical breast hyperplasia) can qualify for Medicaid coverage if the following criteria are met: The applicant has been screened for breast or cervical cancer, diagnosed and found in need of treatment, is an adult under age 65, meets SC state residency, citizenship/alienage, and identity requirements, does not have other insurance coverage that would cover treatment, including Medicare Part A or B, has family income at or below 200% of the Federal Poverty Level, and is not eligible for another Medicaid eligibility group."
A filled-in Form 913 example: an applicant fills out Section II
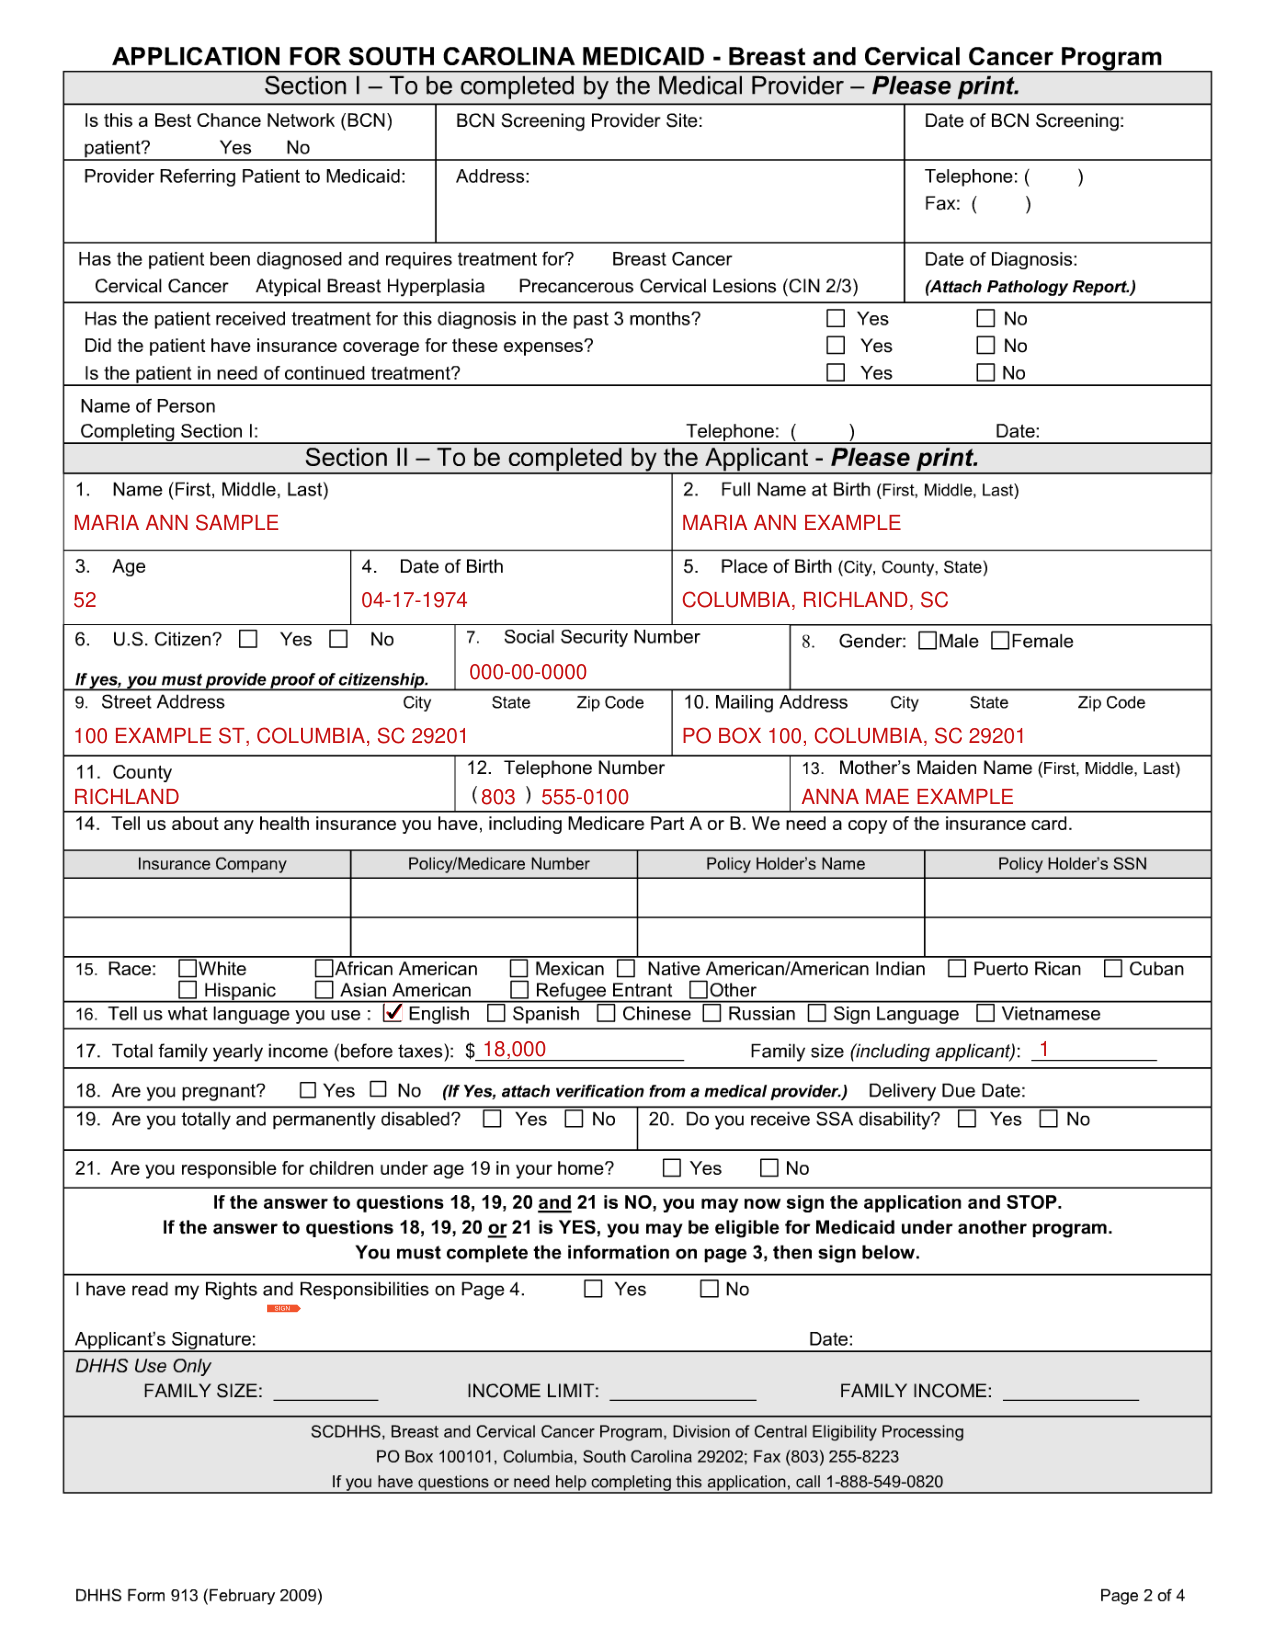
How to fill out Form 913, box by box
Section I: To be completed by the Medical Provider
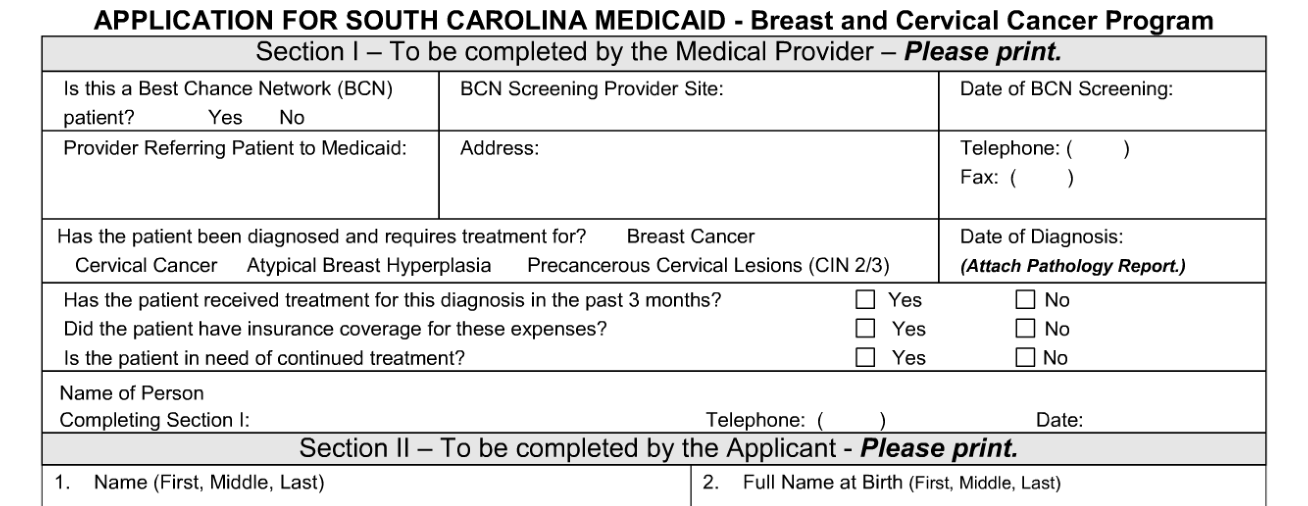
Section I is to be completed by the Medical Provider. Please print. Enter the Name of Person Completing Section I, the Telephone and the Date.
Mark Yes or No to Is this a Best Chance Network (BCN) patient? and enter the BCN Screening Provider Site, the Date of BCN Screening, the Provider Referring Patient to Medicaid, the Address, the Telephone and the Fax.
Mark what the patient has been diagnosed and requires treatment for: Breast Cancer, Cervical Cancer, Atypical Breast Hyperplasia or Precancerous Cervical Lesions (CIN 2/3), and enter the Date of Diagnosis. Attach Pathology Report. Mark Yes or No: Has the patient received treatment for this diagnosis in the past 3 months? Did the patient have insurance coverage for these expenses? Is the patient in need of continued treatment?
Section II: Name, birth and citizenship
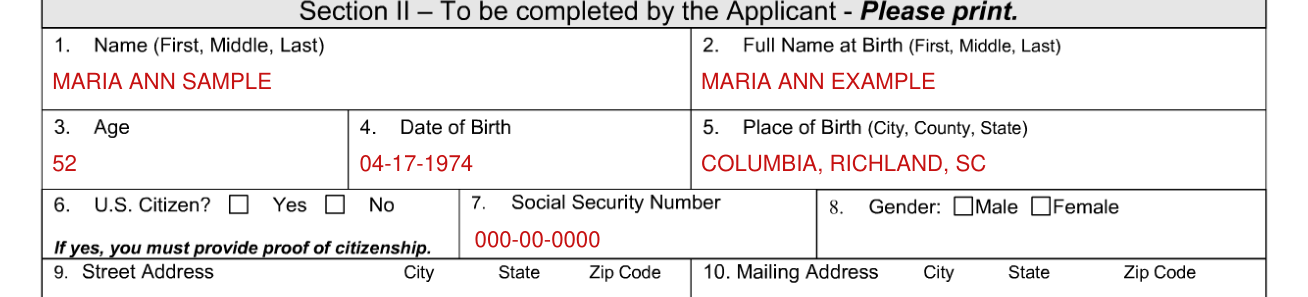
Section II is to be completed by the Applicant. Please print. Enter 1. Name (First, Middle, Last) and 2. Full Name at Birth (First, Middle, Last).
Enter 3. Age, 4. Date of Birth and 5. Place of Birth (City, County, State).
Mark 6. U.S. Citizen? Yes or No. If yes, you must provide proof of citizenship. Enter 7. Social Security Number and 8. Gender.
Addresses, county, telephone and mother's maiden name

Enter 9. Street Address, City, State and Zip Code and 10. Mailing Address, City, State and Zip Code.
Enter 11. County, 12. Telephone Number and 13. Mother's Maiden Name (First, Middle, Last).
Health insurance
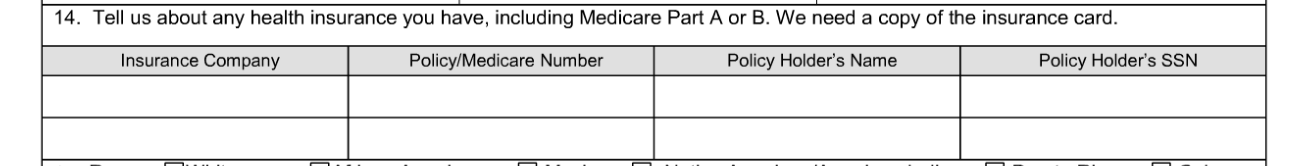
14. Enter any health insurance you have, including Medicare Part A or B. A copy of the insurance card is needed. Enter the Insurance Company, Policy/Medicare Number, Policy Holder's Name and Policy SSN.
Language, family yearly income and family size

15. Race: African, Mexican, Native American/American Indian, Puerto Rican, Cuban, Hispanic, Asian American, Refugee Entrant. 16. Language you use: English, Spanish, Chinese, Russian, Sign Language or Vietnamese. 17. Enter Total family yearly income (before taxes) and Family size (including applicant).
Delivery Due Date and questions 18 to 21

18. Are you pregnant? Mark Yes or No. If Yes, attach verification from a medical provider and enter the Delivery Due Date. 19. Are you totally and permanently disabled? Mark Yes or No. 20. Do you receive SSA disability? Mark Yes or No.
21. Are you responsible for children under age 19 in your home? Mark Yes or No.
If the answer to questions 18, 19, 20 and 21 is NO, you may now sign the application and STOP. If the answer to questions 18, 19, 20 or 21 is YES, you may be eligible for Medicaid under another program. You must complete the information on page 3, then sign below. I have read my Rights and Responsibilities on Page 4.
Signature and Date

Mark Yes or No, then sign at Signature and enter the Date. DHHS Use Only: FAMILY SIZE, INCOME LIMIT and FAMILY INCOME are not for you.
More rules for Form 913
Complete and sign the Breast and Cervical Cancer Program application.
The provider rendering the diagnosis must complete and sign Section I of the application.
Household, income and bank accounts, then review and treatment
Household, income, child support and bank accounts
22. List the adults and children who live with you. Social Security Numbers are not required for persons who are not applying for Medicaid. For each person enter the Name (First, Middle, Last), Relationship to You, Birthdate Mo/Day/Yr., Social Security Number, Race, Sex and Citizen? Yes or No.
23. Does anyone in your household work? Mark Yes or No. If Yes, enter the Name of Person Who Works, the Employer Name and Telephone Number and the Amount Earned Each Pay Period Before Taxes.
How much other income your family has: Child support, Alimony, Social Security payment, Unemployment benefits or Other (Please explain.), with the Amount, How Often Do You Get This Income? and Which Family Member Gets This Income? (Attach additional pages if necessary.)
Please send Proof of Income. Send copies of pay stubs for the last 4 weeks or a letter from your employer. If self-employed, please send a copy of your most recent Federal Income Tax form, including any appropriate Schedules. Please send copies of letters you have telling the amount of any benefits received or a copy of any checks received.
26. How much does the household have in cash, checking and savings accounts? Enter $ and the Name of Bank.
Please attach a copy of most recent bank statement(s). 27. Mark Yes or No for each of Home property, Land, other than your home, Vehicle(s) for transportation, Recreational vehicle(s), Stocks/Bonds, Burial plots/funds, Life insurance and Other (explain), and enter the Owner's Name and Total Value. Please attach proof of anything marked Yes.
Your application, review and treatment
The applicant will be notified in writing of approval or denial of the application. Women who qualify are eligible for the full range of Medicaid coverage. Coverage continues as long as eligibility criteria are met and the beneficiary continues treatment. The beneficiary must report to her Medicaid worker when treatment is completed.
Eligibility is reviewed annually for women with breast or cervical cancer and bi-annually (every six months) for women with pre-cancerous lesions. When it is time for the review, a review form is mailed to the beneficiary and must be returned or coverage will stop.
Once treatment is completed, the beneficiary must qualify under another Medicaid program for coverage to continue.
7. The beneficiary must report any and all changes in income, deductions, resources, living arrangements, members of the household, or other information that will affect medical help within ten (10) days of the date of the change(s). If the beneficiary fails to notify the department promptly, she may lose benefits and be subjected to penalties or prosecution.
Common questions about Form 913
Where do I file it?
SCDHHS, Breast and Cervical Cancer Program, Division of Central Eligibility Processing, PO Box 100101, Columbia, South Carolina 29202; Fax (803) 255-8223.
Where to get help with Form 913
If you have questions regarding the BCCP, or need help in completing the application, please call: 1-888-549-0820 (toll-free).
Sources
[1] DHHS Form 913 (February 2009), Application for South Carolina Medicaid, Breast and Cervical Cancer Program, South Carolina Department of Health and Human Services (the Official source link on this page).