
SFN 847 at a glance
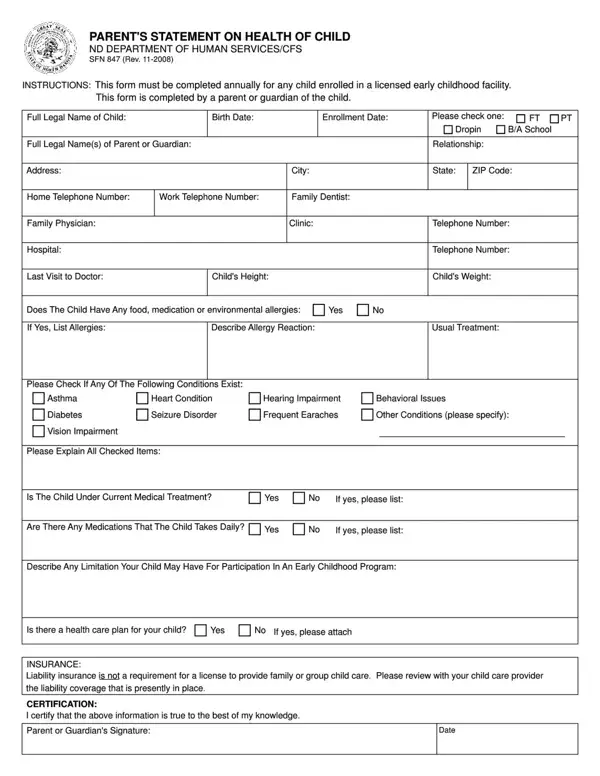
What it is: SFN 847 (5-2026) is the Parent's Statement on Health of Child of the Department of Health and Human Services, Early Childhood.
Who signs: Enter the Signature of Guardian and the Date Signed.
A parent or guardian of each child enrolled in child care must complete this form annually.
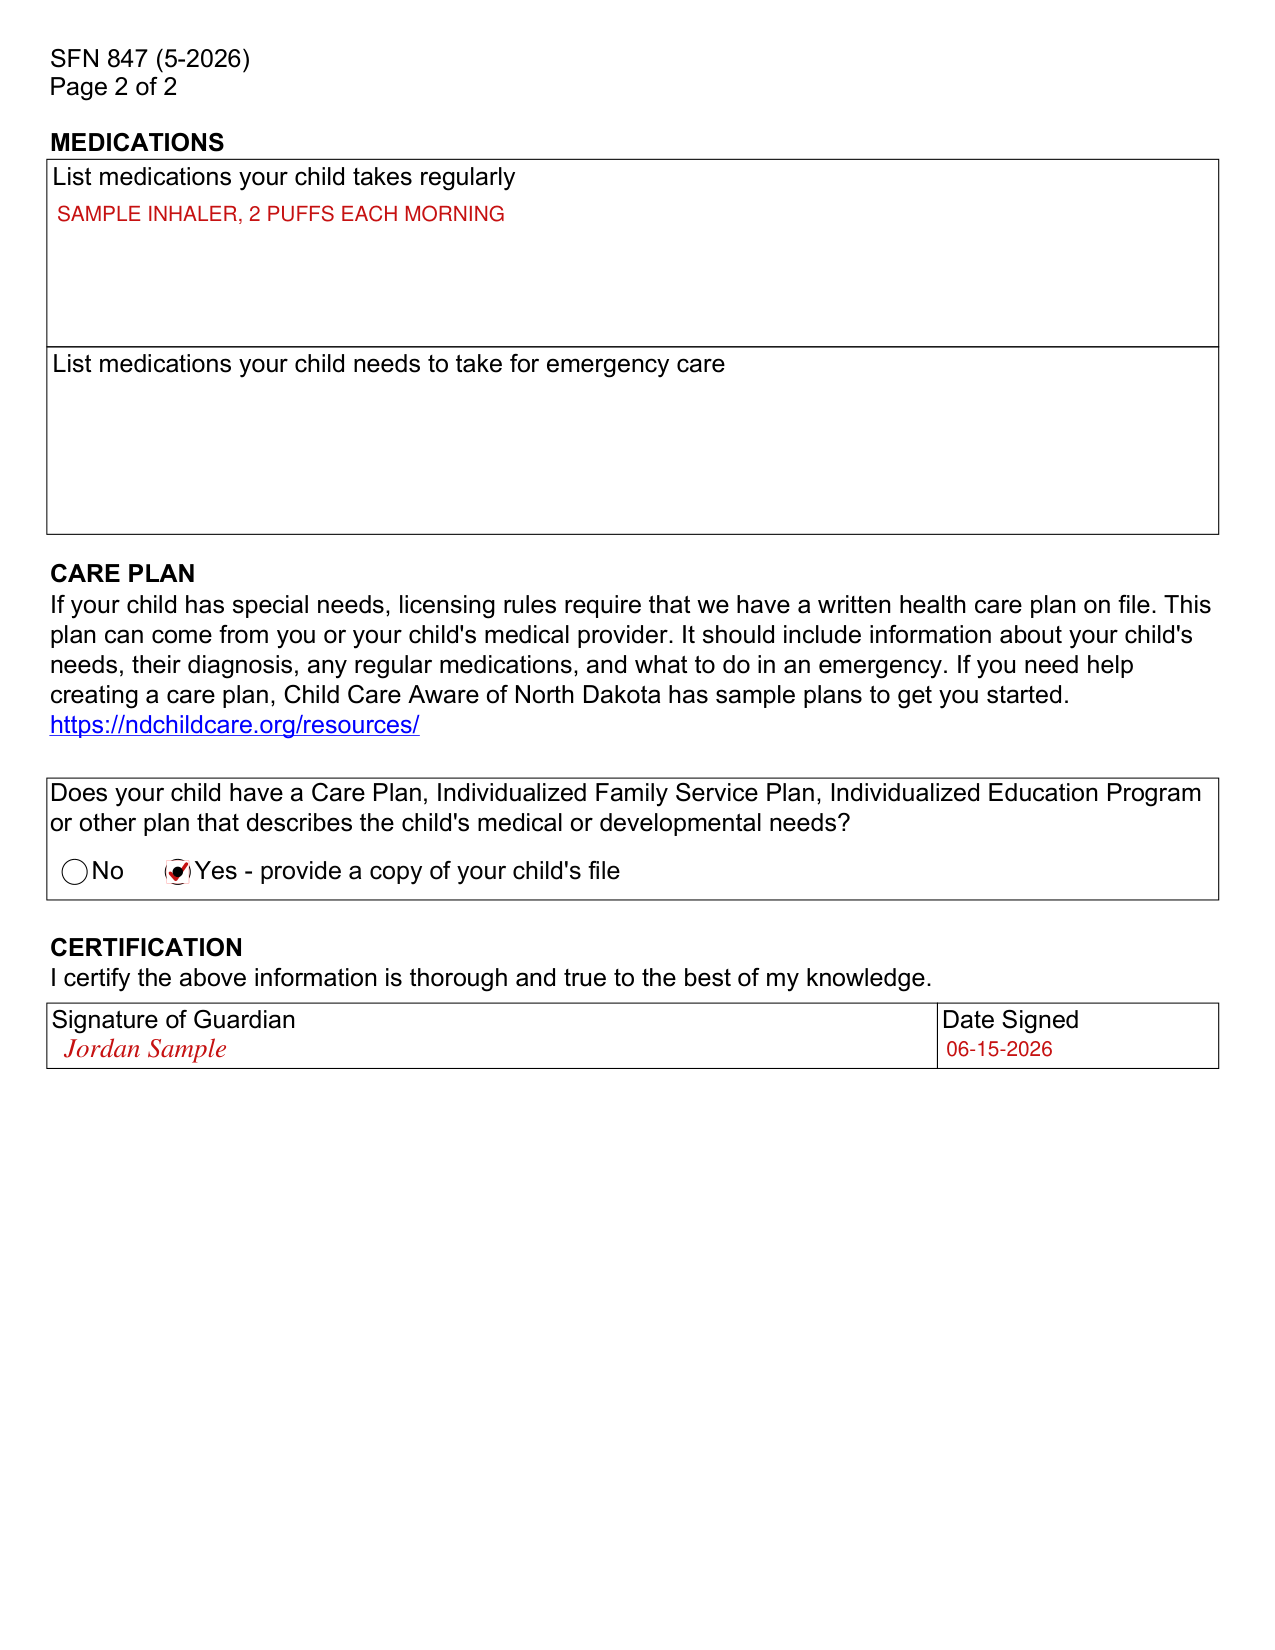
A filled-in SFN 847 example: a parent completes page 2
How to fill out SFN 847, box by box
Child's Name and Date of Birth

Enter the Child's Name and the Date of Birth.
Parent or Guardian Name and phone numbers
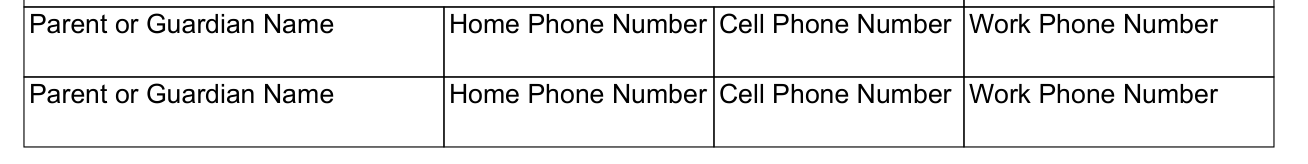
For each parent or guardian, enter the Parent or Guardian Name, Home Phone Number, Cell Phone Number and Work Phone Number.
Medical provider information

Under MEDICAL PROVIDER INFORMATION, enter the Preferred Hospital to Transport to in Case of Emergency.
Medical history
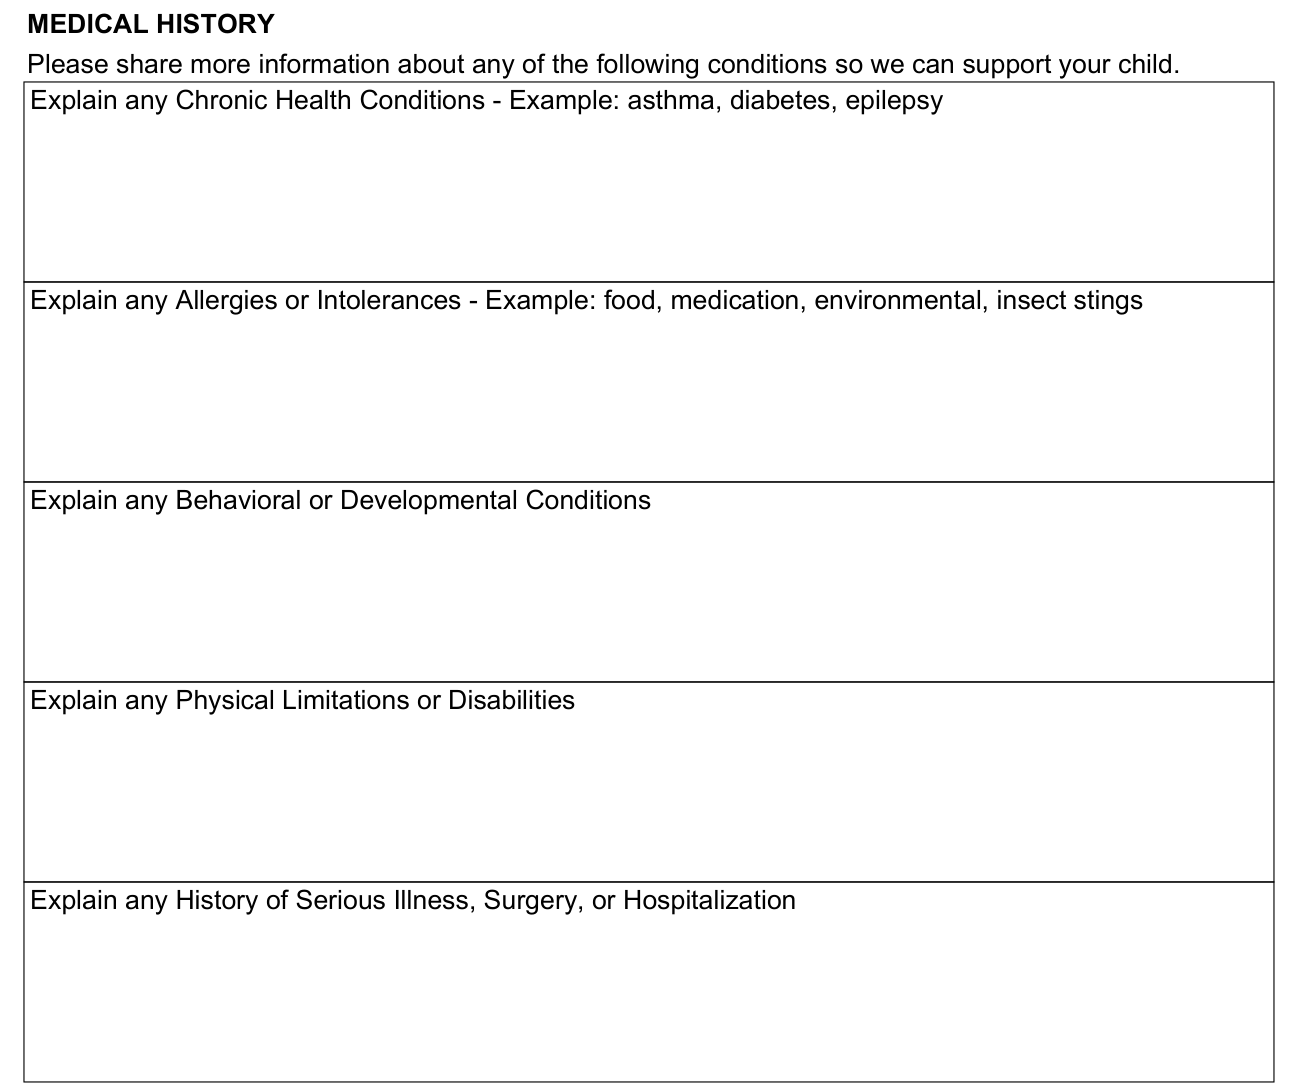
Under MEDICAL HISTORY, share more information about any of the following conditions.
Explain any Chronic Health Conditions - Example: asthma, diabetes, epilepsy.
Explain any Allergies or Intolerances - Example: food, medication, environmental, insect stings.
Explain any Behavioral or Developmental Conditions.
Explain any Physical Limitations or Disabilities.
Explain any History of Serious Illness, Surgery, or Hospitalization.
Medications

Under MEDICATIONS, list medications your child takes regularly.
List medications your child needs to take for emergency care.
Care plan

If your child has special needs, licensing rules require a written health care plan on file.
This plan can come from you or your child's medical provider.
It should include information about your child's needs, their diagnosis, any regular medications, and what to do in an emergency.
If you need help creating a care plan, Child Care Aware of North Dakota has sample plans to get you started.
Does your child have a Care Plan, Individualized Family Service Plan, Individualized Education Program or other plan that describes the child's medical or developmental needs? No. Yes - provide a copy of your child's file.
Certification

Certification: "I certify the information is thorough and true to the best of my knowledge."
Sources
[1] Form SFN 847 (5-2026), Parent's Statement on Health of Child, Department of Health and Human Services, Early Childhood (the Official source link on this page).