
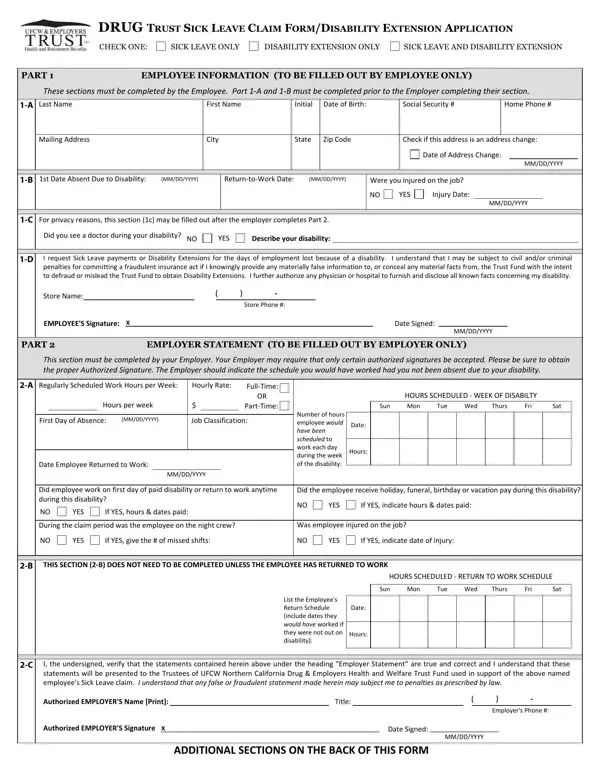

Drug Trust Sick Leave Claim Form/Disability Extension Application at a glance
What it is: Drug Trust Sick Leave Claim Form/Disability Extension Application.
Who signs: Employee's Signature and Date Signed. Authorized EMPLOYER'S Signature and Date Signed.
Where and when to file: Sick Leave: One year from the first day of your disability for Sick Leave Claims.
The blank Drug Trust Sick Leave Claim Form/Disability Extension Application: print it and complete it by hand
How to fill out Drug Trust Sick Leave Claim Form/Disability Extension Application, box by box
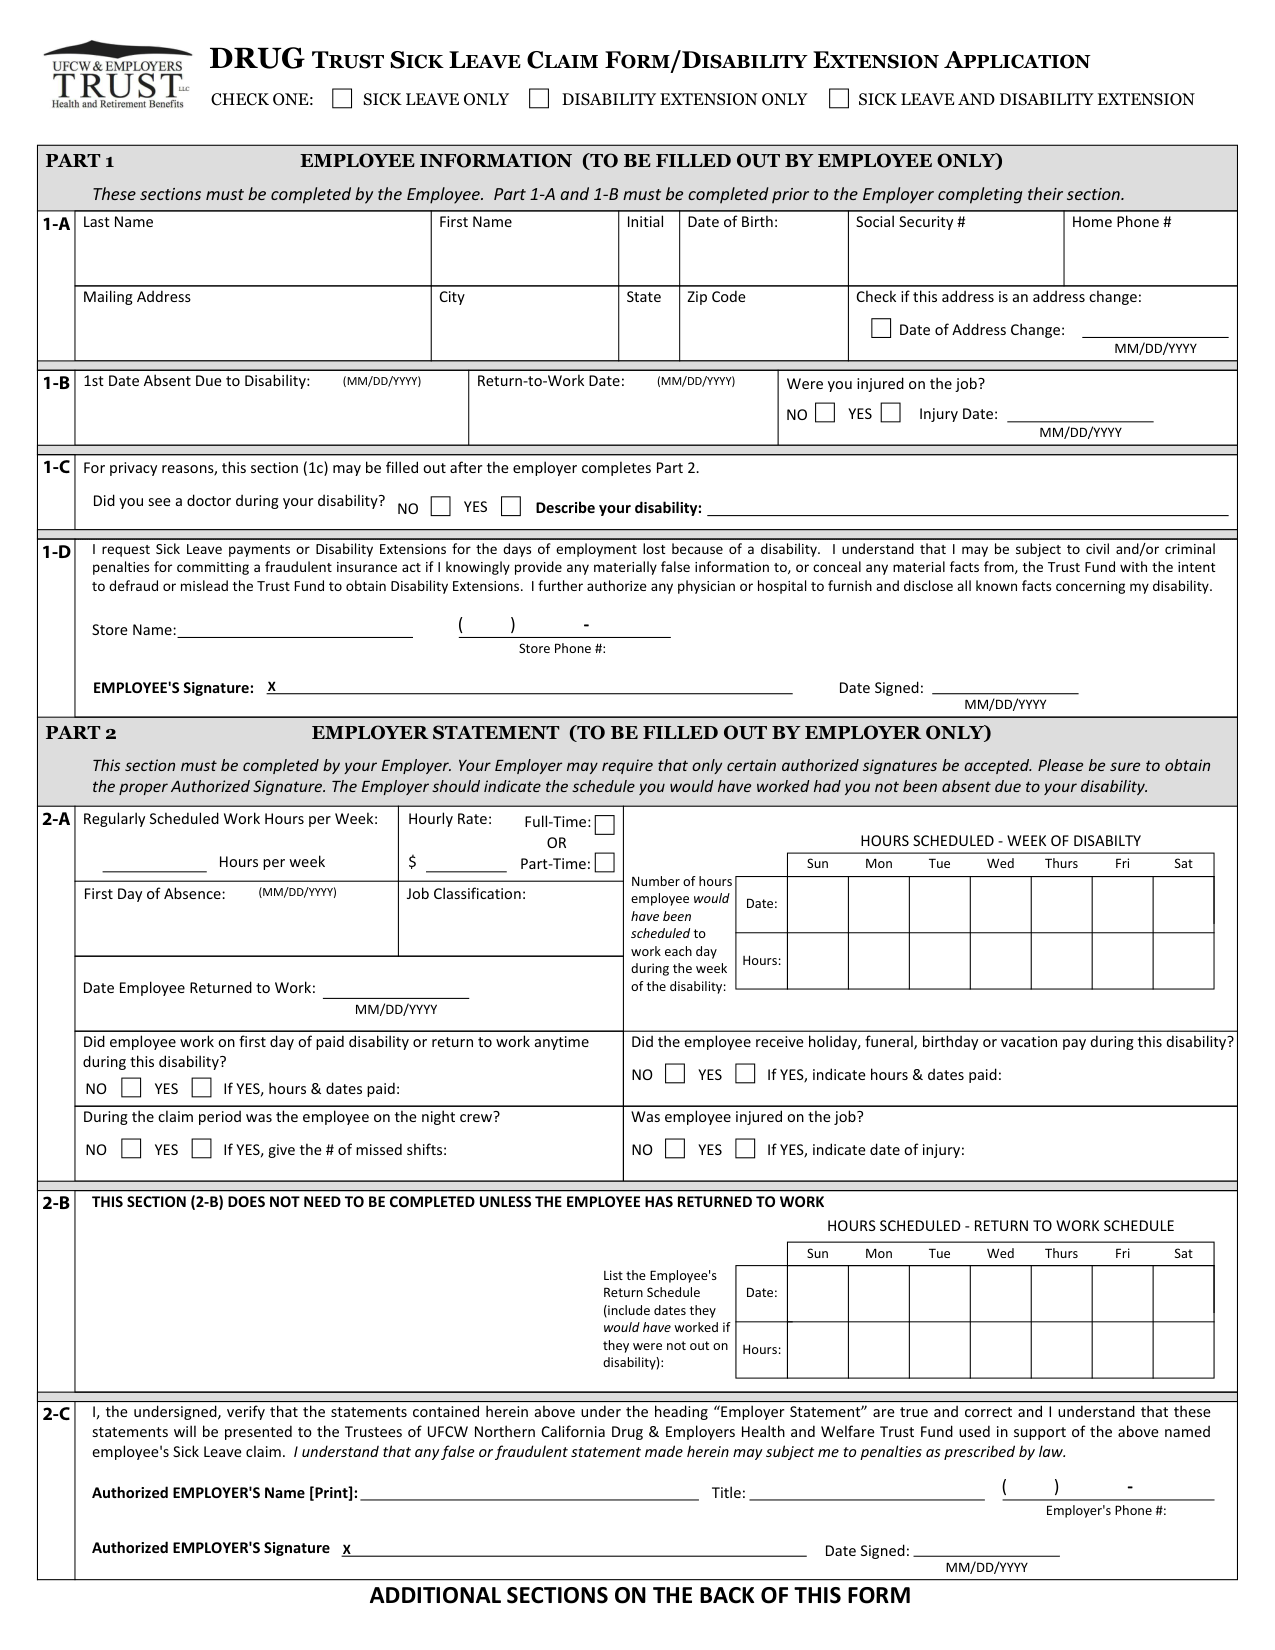
Check one
Check one: Sick Leave Only, Disability Extension Only, or Sick Leave and Disability Extension.
Part 1 Employee Information
Part 1, Employee Information, is to be filled out by employee only.
Part 1-A and 1-B must be completed prior to the Employer completing their section.
For privacy reasons, section 1c may be filled out after the employer completes Part 2.
In 1-D, you may be subject to civil and/or criminal penalties for committing a fraudulent insurance act if you knowingly provide any materially false information to, or conceal any material facts from, the Trust Fund with the intent to defraud or mislead the Trust Fund to obtain Disability Extensions.
Employee's Signature and Date Signed.
Employer Statement
The Employer Statement must be completed by your Employer. Your Employer may require that only certain authorized signatures be accepted. Please be sure to obtain the proper Authorized Signature. The Employer should indicate the schedule you would have worked had you not been absent due to your disability.
Section 2-B does not need to be completed unless the employee has returned to work.
2-C I, the undersigned, verify that the statements contained under the heading Employer Statement are true and correct. Any false or fraudulent statement made herein may subject me to penalties as prescribed by law.
Authorized EMPLOYER'S Signature and Date Signed.
Attending Physician
If your absence lasts longer than 7 calendar days, you must file for State Disability Insurance (SDI). The Attending Physician's Statement is to be filled out by physician only.
Hospital: Name, City, State, YES NO, Confined From and To. If patient is still disabled, give estimated date patient will be able to return to work. In order to be paid for the first day of disability or to be paid beyond the first week of disability, this section must be completed by your doctor.
You MUST be seen by your doctor within a seven-day period following commencement of the disability.
Please be sure your doctor provides the date you were treated.
Telephone advice does NOT satisfy this requirement.
A disability day is defined as any day in which you do not work more than 50% of your scheduled shift.
If you work more than 50% of your scheduled shift, this day will not be considered as a disability day and therefore will not be considered as your deductible day when not seen by a physician.
To be paid for the first day you must have 180 hours in your sick leave bank on the last day of the month preceding your disability and your doctor certifies that you were unable to work because of the disability on such day of absence.
Disabled more than Seven Calendar Days
Please call Member Services if you have any questions: (800) 552-2400. (1) Disabled more than Seven Calendar Days (Three Calendar Days If Disability Caused by Work) from first day of Absence: The Trust Fund pays in combination with State Disability Insurance (SDI) or Worker's Compensation (WC) benefits beginning your first week of disability.
You MUST file for SDI in order to receive your entire Sick Leave Benefit amount, because your disability lasted longer than 7 calendar days.
In order to receive your maximum benefits, you MUST file for SDI or WC and attach one of the following: A copy of your SDI Notice of Computation; or A Worker's Compensation Benefit Notice. If the Trust Fund receives this form without your SDI statement, the Trust Fund will reduce your Sick Leave benefits by the maximum State Disability benefit.
You MUST submit a copy of your first SDI or WC benefit notice to the Trust Fund in order to be paid for any additional benefits that are due.
If the amount of SDI or WC that you received was less than what the Trust Fund estimated, the Trust Fund will pay any additional benefits that are due. You will be requested to return any overpayments.
You cannot receive more than 100% of your regularly scheduled wages.
SDI and WC pay first toward your regularly scheduled wages. The Trust Fund will pay the difference between your regularly scheduled wages and what SDI or WC pays, as long as you have available Sick Leave hours. For example: If you are first absent on a Monday due to a disability and you are still absent the following Monday (more than 7 calendar days), then SDI becomes your primary payer of lost wages.
Call the SDI office at (800) 480-3287 for information on SDI filing deadlines.
Timely filing limit
(2) Timely Filing Limit: You will be disqualified for the Sick Leave Benefit and/or Disability Extension if you do not file your application by the following deadlines:
Sick Leave: One year from the first day of your disability for Sick Leave Claims.
Disability Extensions: 60 days from the date you receive your COBRA/ Loss of Eligibility notification for Disability Extension.
If you do not file your application within this 60-day period, you will be disqualified for a Disability Extension.
Eligibility For Disability Extensions
Return this completed form to the Trust Fund office within 60 days from the date your coverage ended or you received the COBRA continuation notice.
You must have been eligible for at least nine continuous months prior to the work month in which you became disabled.
The Plan also required you to have sufficient qualifying hours to be eligible for benefits. The total required hours can be a combination of hours worked and hours not worked due to disability. The combination of hours worked and scheduled hours not worked must equal or exceed the minimum qualifying hours.
If your disability lasts more than seven calendar days, you must submit proof of your disability.
You can request your doctor complete Part D or you may attach the notifications you received from State Disability or Workers' Compensation for benefits paid to you for the calendar month(s) for which this extension application is made.
If your Disability Extension Application is granted but you remain disabled when your extension expires, and you are eligible for additional extension (please confirm with Member Services if insure of your eligibility), you must file a new application within 60 days from the date the last Disability Extension expired.
Gold and Platinum Active participants who suffer a Total and Permanent Disability (as defined by Social Security Administration or other comparable standard) will be eligible for an additional 12-month extension - if they are eligible to receive 12 Disability Extensions.
To obtain this extension, you must notify the Trust Fund within 60 days of the date your total disability determination is issued.
You will receive notification from the Trust Fund Office when your application is processed.
For additional information about Disability Extensions and the maximum number allowed, please refer to your Summary Plan Description.
Common questions about Drug Trust Sick Leave Claim Form/Disability Extension Application
Where do I file it?
Mail completed forms to UFCW Northern California & Drug Employers Health and Welfare Trust Fund P.O. Box 8086 Walnut Creek, CA 94596-8086.
Sources
[1] Drug Trust Sick Leave Claim Form/Disability Extension Application, UFCW Northern California Drug & Employers Health and Welfare Trust Fund (the Official source link on this page).