


VA Form 10-0454 at a glance
What it is: This form is used to coordinate the transition into VA health care for transitioning Service members and new Veterans through a VA Liaison for Healthcare, which you can locate here: https://www.va.gov/POST911VETERANS/VA_Liaison_for_Healthcare_Locator.asp
A filled-in VA Form 10-0454 example: a soldier referred before leaving active duty
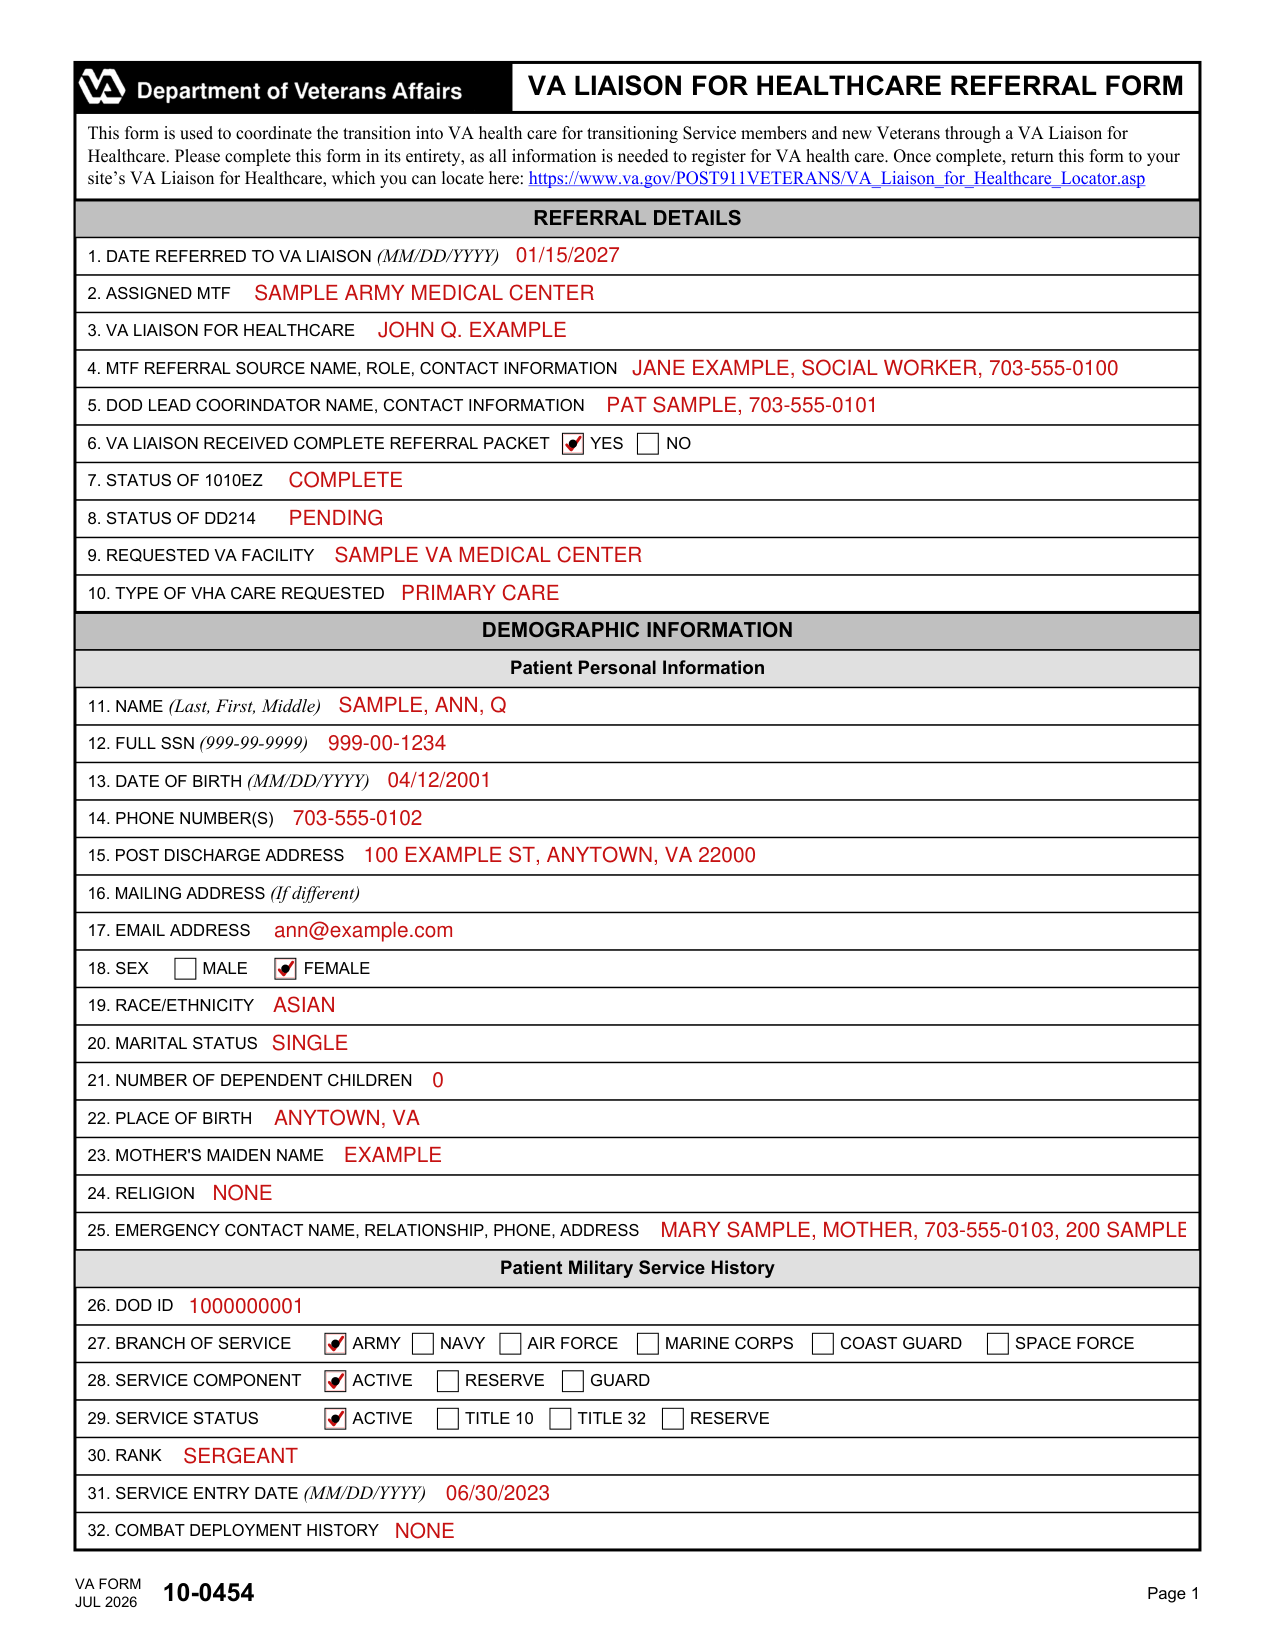
How to fill out VA Form 10-0454, box by box
Referral details
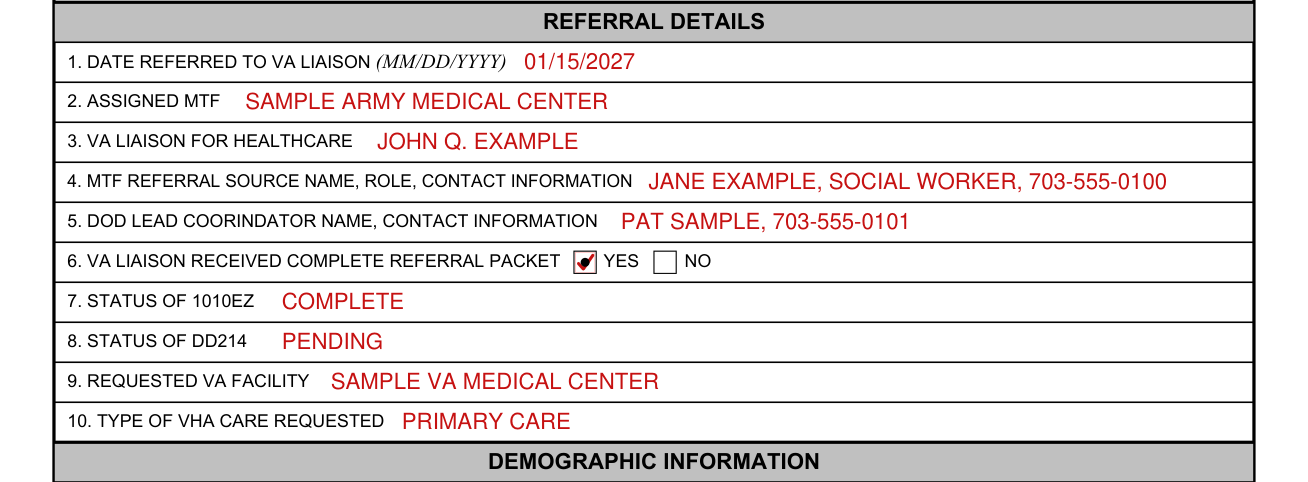
Enter the date referred to VA Liaison in Box 1 as MM/DD/YYYY.
Enter the assigned MTF in Box 2 and the VA Liaison for Healthcare in Box 3.
Enter the MTF referral source name, role and contact information in Box 4, and the DOD lead name and contact information in Box 5.
In Box 6, mark YES or NO: VA Liaison received complete referral packet.
Enter the status of 1010EZ in Box 7 and the status of DD214 in Box 8.
Enter the requested VA facility in Box 9 and the type of VHA care requested in Box 10.
Patient Personal Information
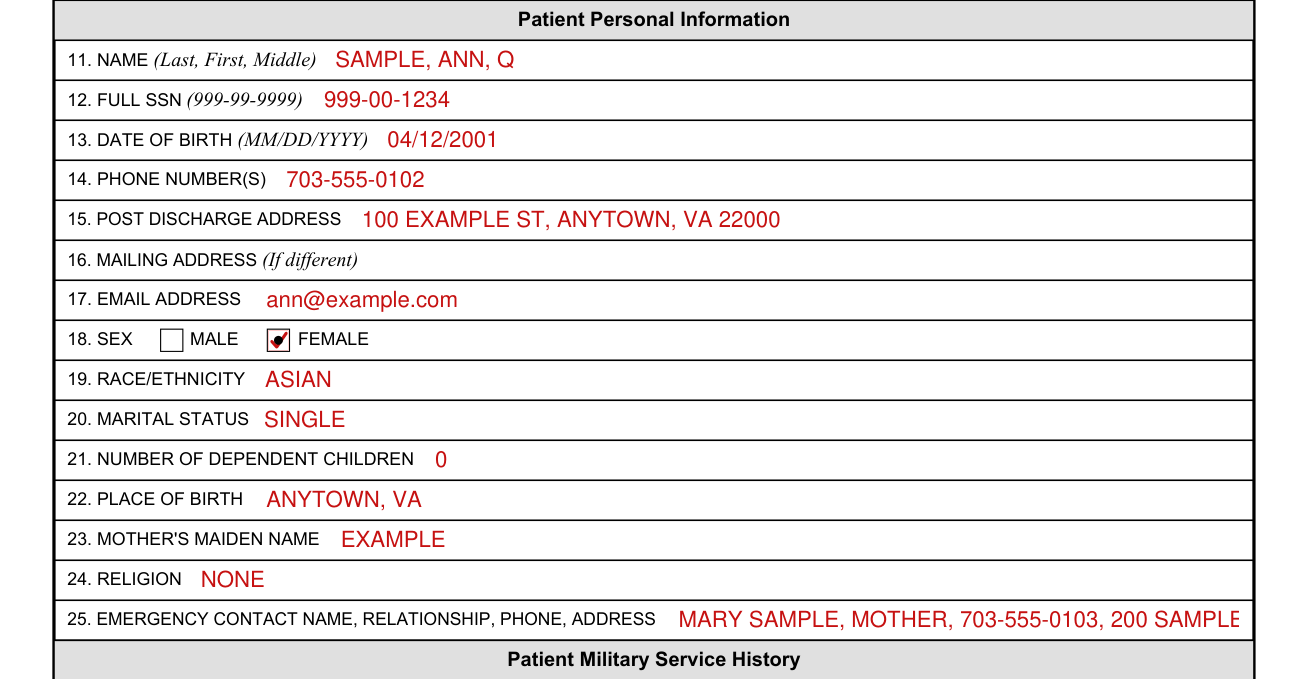
In Box 11, enter the name as Last, First, Middle.
In Box 12, enter the full SSN as 999-99-9999.
In Box 13, enter the date of birth as MM/DD/YYYY.
Enter the phone number(s) in Box 14 and the post discharge address in Box 15.
In Box 16, enter the mailing address (If different).
Enter the email address in Box 17 and mark MALE or FEMALE for sex in Box 18.
Enter the race/ethnicity in Box 19, the marital status in Box 20 and the number of dependent children in Box 21.
Enter the place of birth in Box 22, the mother's maiden name in Box 23 and the religion in Box 24.
In Box 25, enter the emergency contact name, relationship, phone, address.
Patient Military Service History

Enter the DOD ID in Box 26.
In Box 27, mark the branch of service: Army, Navy, Air Force, Marine Corps, Coast Guard or Space Force.
In Box 28, mark the service component: ACTIVE, RESERVE or GUARD.
In Box 29, mark the service status: ACTIVE, TITLE 10, TITLE 32 or RESERVE.
Enter the rank in Box 30, the service entry date in Box 31 as MM/DD/YYYY, and the combat deployment history in Box 32.
Patient Military Discharge Information
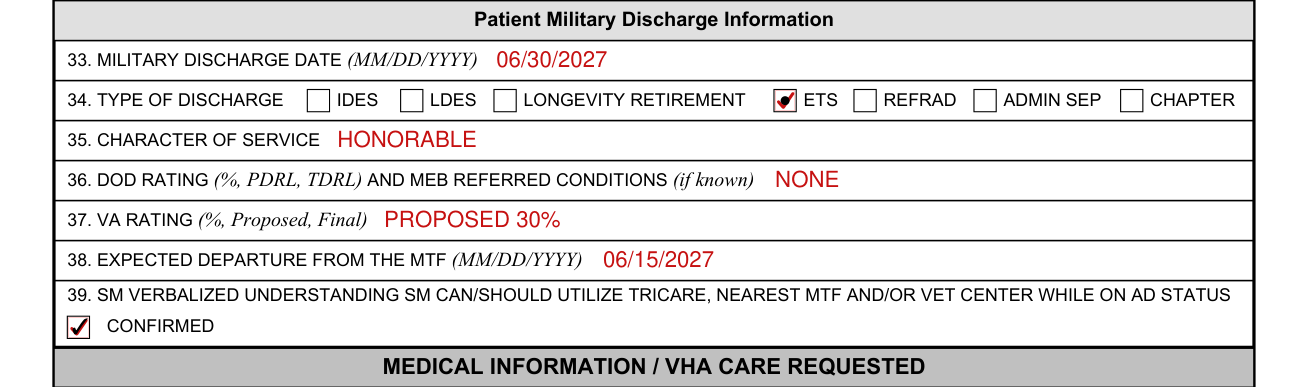
Enter the military discharge date in Box 33 as MM/DD/YYYY.
In Box 34, mark the type of discharge: IDES, LDES, Longevity Retirement, ETS, REFRAD, Admin Sep or Chapter.
Enter the character of service in Box 35.
In Box 36, enter the DOD rating (%, PDRL, TDRL) and MEB referred conditions (if known).
In Box 37, enter the VA rating (%, Proposed, Final). In Box 38, enter the expected departure from the MTF as MM/DD/YYYY.
Check CONFIRMED in Box 39 for SM verbalized understanding SM can/should utilize TRICARE, nearest MTF and/or Vet Center while on AD status.
Medical Information / VHA Care Requested
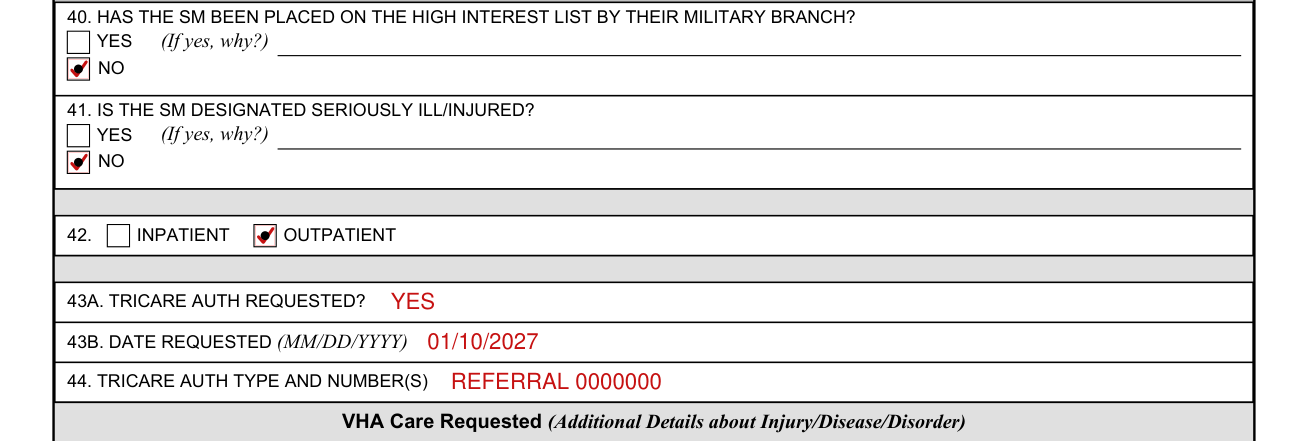
In Box 40, has the SM been placed on the high interest list by their military branch? Mark YES or NO. If yes, why?
In Box 41, is the SM designated seriously ill/injured? Mark YES or NO. If yes, why?
In Box 42, mark INPATIENT or OUTPATIENT.
In Box 43A, TRICARE auth requested? Enter YES or NO. Enter the date requested in Box 43B as MM/DD/YYYY, and the TRICARE auth type and number(s) in Box 44.
VHA Care Requested (Additional Details about Injury/Disease/Disorder)

Under VHA Care Requested (Additional Details about Injury/Disease/Disorder), enter primary care in Box 45, mental health (to include Suicide Prevention, Military Sexual Trauma) in Box 46 and specialty care in Box 47.
In Box 48, enter biopsychosocial needs; please include if at-risk for adverse outcomes during transition. If so, why?
Enter the medication in Box 49, the days of medication requested for transition period in Box 50 and the durable medical equipment/prosthetics in Box 51.
In Box 52, enter the discharge plan from the MTF/ military installation/ P3 site; include WHEN and WHERE the patient will be discharged, current discharge status, i.e. convalescent or transition/terminal leave, pending medical discharge, return to duty, return to MTF, separation, etc.
Sources
[1] VA Form 10-0454 (JUL 2026), VA Liaison for Healthcare Referral Form, U.S. Department of Veterans Affairs (the Official source link on this page).