

Chronic Fatigue Syndrome Disability Benefits Questionnaire at a glance
What it is: The Chronic Fatigue Syndrome (CFS) Disability Benefits Questionnaire is intended to be completed by the Veteran's healthcare provider, with VA obtaining additional medical information if necessary.
Who signs: The Examiner signs 8A, Examiner's signature.
A filled-in Chronic Fatigue Syndrome Disability Benefits Questionnaire example: a doctor completes page 3 for a Veteran

How to fill out Chronic Fatigue Syndrome Disability Benefits Questionnaire, box by box
2D. Acute onset and 2E. Daily activity level

2D. Did the Veteran have an acute onset of chronic fatigue syndrome? Yes or No.
2E. Has the debilitating fatigue reduced daily activity level to less than 50% of pre-illness level? Yes or No. If "Yes," specify length of time daily activity level has been reduced to less than 50% of pre-illness level: Less than 6 months or 6 months or longer.
3A. Findings, signs and symptoms

Under Section III, Findings, signs and symptoms, 3A: Does the Veteran now have or has the Veteran had any findings, signs and symptoms attributable to chronic fatigue syndrome? Yes or No. If "Yes," check all that apply: Debilitating fatigue, Headaches (of a type, severity or pattern that is different from headaches in the pre-morbid state), Low grade fever, Migratory joint pain, Nonexudative pharyngitis, Neuropsychologic symptoms, Palpable or tender cervical or axillary lymph nodes, Sleep disturbance, Generalized muscle aches or weakness, Other, Fatigue lasting 24 hours or longer after exercise. For all checked conditions, describe.
3B. Cognitive impairment

3B. Does the Veteran now have or has the Veteran had any cognitive impairment attributable to chronic fatigue syndrome? Yes or No. If "Yes," check all that apply: Inability to concentrate, Forgetfulness, Confusion, Other cognitive impairments. For all checked conditions, describe.
3C. Frequency of symptoms

3C. Specify frequency of symptoms: Symptoms are nearly constant (if checked complete question 3D), or Symptoms wax and wane (if checked skip to question 3E).
More rules for Chronic Fatigue Syndrome Disability Benefits Questionnaire
The Veteran is applying to the U.S. Department of Veterans Affairs (VA) for disability benefits, and VA will consider the information you provide on this questionnaire as part of their evaluation in processing the Veteran's claim. VA may obtain additional medical information, including an examination, if necessary, to complete VA's review of the Veteran's application. VA reserves the right to confirm the authenticity of ALL completed questionnaires.
VA will not pay or reimburse any expenses or cost incurred in the process of completing and/or submitting this form.
Under "Are you completing this Disability Benefits Questionnaire at the request of:", mark Veteran/Claimant, Third party (list the name(s) of organization(s) or individual(s)) or Other: describe.
Mark Yes or No for: Are you a VA Healthcare provider? Is the Veteran regularly seen as a patient in your clinic? Was the Veteran examined in person? If no, how was the examination conducted?
Under EVIDENCE REVIEW, mark Evidence reviewed: No records were reviewed or Records reviewed. For Records reviewed, identify the evidence reviewed (e.g. service treatment records, VA treatment records, private treatment records) and the date range.
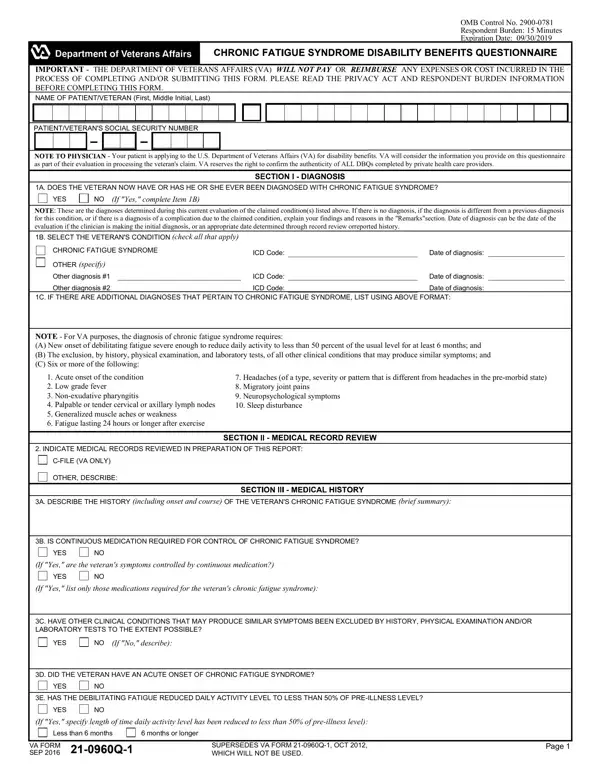
Under Section I, Diagnosis, for 1A, Does the Veteran currently have chronic fatigue syndrome (CFS)?, Yes or No, and enter the ICD code and the Date of diagnosis. Under OTHER (specify), enter Other diagnosis #1 and Other diagnosis #2, each with ICD code and Date of diagnosis.
1B. If there are additional diagnoses that pertain to chronic fatigue syndrome, list them in the format of Section I.
For VA purposes, the diagnosis of chronic fatigue syndrome requires: (A) New onset of debilitating fatigue severe enough to reduce daily activity to less than 50 percent of the usual level for at least 6 months; and (B) The exclusion, by history, physical examination, and laboratory tests, of all other clinical conditions that may produce similar symptoms; and (C) Six or more of the following: 1. Acute onset of the condition 2. Low grade fever 3. Non-exudative pharyngitis 4. Palpable or tender cervical or axillary lymph nodes 5. Generalized muscle aches or weakness 6. Fatigue lasting 24 hours or longer after exercise 7. Headaches (of a type, severity or pattern that is different from headaches in the pre-morbid state) 8. Migratory joint pains 9. Neuropsychologic symptoms 10. Sleep disturbance.
Under Section II, Medical history, 2A: Describe the history (including onset and course or whether the condition is now completely resolved and no longer requires treatment of any type) of the Veteran's chronic fatigue syndrome (brief summary).
2B. Is continuous medication required for control of chronic fatigue syndrome? Yes or No. If "Yes," are the Veteran's symptoms controlled by continuous medication? Yes or No. If "Yes," list only those medications required for the Veteran's chronic fatigue syndrome.
2C. Have other clinical conditions that may produce similar symptoms been excluded by history, physical examination and/or laboratory tests to the extent possible? Yes or No. If "No," describe.
3D. If the symptoms due to chronic fatigue syndrome are nearly constant, do they restrict routine daily activities as compared to the pre-illness level? Yes or No. If "Yes," specify % of restriction (check all that apply): Symptoms restrict routine daily activities almost completely and may occasionally preclude self-care; Symptoms restrict routine daily activities to less than 50 percent of the pre-illness level; Symptoms restrict daily activities from 50 to 75 percent of the pre-illness level; Symptoms restrict routine daily activities by less than 25 percent of the pre-illness level; Other (describe).
For VA purposes, chronic fatigue syndrome is considered incapacitating only while it requires bed rest and treatment by a physician.
3E. Do the Veteran's symptoms due to chronic fatigue syndrome result in periods of incapacitation? Yes or No. If "Yes," indicate total duration of periods of incapacitation: At least 6 weeks per year; At least 4 but less than 6 weeks per year; At least 2 but less than 4 weeks per year; At least 1 but less than 2 weeks per year; Less than 1 week per year.
Under Section IV, Other pertinent physical findings, scars, complications, conditions, signs and/or symptoms, 4A: Does the Veteran have any other pertinent physical findings, complications, conditions, signs and/or symptoms related to any of the conditions listed in the diagnosis section? Yes or No. If yes, describe (brief summary).
4B. Does the Veteran have any scars or other disfigurement (of the skin) related to any conditions or to the treatment of any conditions listed in the diagnosis section? Yes or No. If "Yes," also complete appropriate dermatological DBQ.
Under Section V, Diagnostic testing, 5A: Are there any significant diagnostic test findings and/or results? Yes or No. If "Yes," provide type of test or procedure, date and results - brief summary.
If testing has been performed and reflects the Veteran's current condition, repeat testing is not required.
Under Section VI, Functional impact, 6A: Does the Veteran's chronic fatigue syndrome impact his or her ability to work? Yes or No. If "Yes," describe the impact of the Veteran's chronic fatigue syndrome, providing one or more examples.
Under Section VII, Remarks, 7A: Remarks (if any).
Common questions about Chronic Fatigue Syndrome Disability Benefits Questionnaire
Who signs it?
Enter 8A. Examiner's signature, 8B. Examiner's printed name and title (e.g. MD, DO, DDS, DMD, Ph.D, Psy.D, NP, PA-C), 8C. Examiner's Area of Practice/Specialty (e.g. Cardiology, Orthopedics, Psychology/Psychiatry, General Practice), 8D. Date Signed, 8E. Examiner's phone/fax numbers, 8F. National Provider Identifier (NPI) number, 8G. Medical license number and state, and 8H. Examiner's address.
Is there a penalty?
PENALTY: The law provides severe penalties which include fine or imprisonment, or both, for the willful submission of any statement or evidence of a material fact, knowing it to be false, or for the fraudulent acceptance of any payment to which you are not entitled.
What am I certifying when I sign?
The CERTIFICATION: "To the best of my knowledge, the information contained herein is accurate, complete and current."
Sources
[1] Chronic Fatigue Syndrome (CFS) Disability Benefits Questionnaire (Updated on: 2024-08-02), U.S. Department of Veterans Affairs (the Official source link on this page).