
Updated:
Get Form Now
ICE Form I-983 is a document required by U.S. Immigration and Customs Enforcement (ICE) for students on F-1 visas who are applying for or are currently engaged in STEM (Science, Technology, Engineering, and Mathematics) Optional Practical Training (OPT) extensions. This form is filled out collaboratively by the student on an F-1 visa and their employer to outline a detailed training plan that reflects the educational objectives for the student’s development in their field of study.
The purpose of the ICE Form I-983 is to ensure that the STEM OPT extension is educational and directly related to the student’s field of study. It requires detailed information about how the employment will contribute to the student’s professional growth and learning. The U.S. government uses the form to verify that the training provided is legitimate and that it adheres to all the requirements of the STEM OPT program.
Other PDF Forms
Looking for other PDF forms? Check out the selection just below to see what you’ll be able to fill in and edit with our tool. Also, remember that it is easy to upload, fill out, and edit any PDF at FormsPal.
What it is: ICE Form I-983 is the Training Plan for STEM OPT Students, Science, Technology, Engineering & Mathematics (STEM) Optional Practical Training (OPT).
Who signs: Signature of Student and Signature of Employer Official with Signatory Authority.
Section 1 is completed by the student, Section 3 is completed by the employer, and Section 5 is completed by the student and employer.
The information collection on this form is used to assist in the administration of the STEM Optional Practical Training (OPT) extension so that Designated School Officials (DSO) can properly recommend the Student for and review and help coordinate his or her STEM optional practical training opportunity.

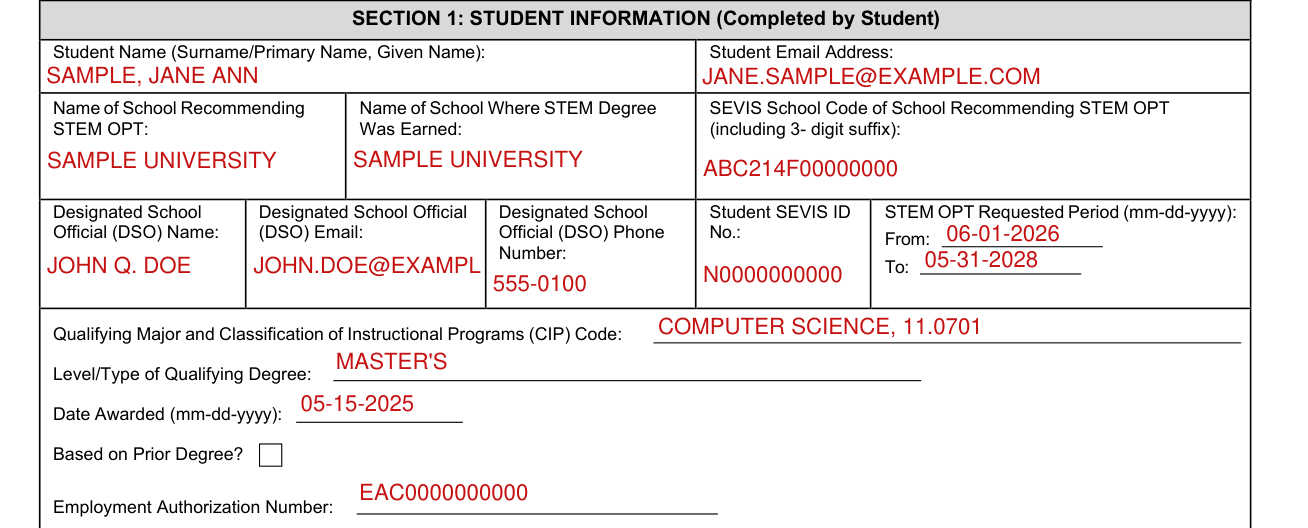
In SECTION 1: STUDENT INFORMATION, enter the Student Name (Surname/Primary Name, Given Name), the Student Email Address, the Name of School Recommending STEM OPT and the Name of School Where STEM Degree Was Earned.
Enter the SEVIS School Code of School Recommending STEM OPT (including 3-digit suffix), and the Designated School Official (DSO) Name, Email and Phone Number.
Enter the Student SEVIS ID No. and the STEM OPT Requested Period (mm-dd-yyyy), From and To.
Enter the Qualifying Major and Classification of Instructional Programs (CIP) Code, the Level/Type of Qualifying Degree, the Date Awarded (mm-dd-yyyy), Based on Prior Degree? and the Employment Authorization Number.

Under SECTION 2: STUDENT CERTIFICATION, the student declares and affirms under penalty of perjury that the statements and information made herein are true and correct to the best of the student's knowledge, information and belief. The law provides severe penalties for knowingly and willfully falsifying or concealing a material fact, or using any false document in the submission of this form.
Under Section 2, you certify: I will notify the DSO at the earliest available opportunity regarding any material changes to or deviations from this Plan, including any nontrivial reduction in compensation from the amount previously submitted on the Plan that is not tied to a reduction in hours worked, and any decrease in hours below the 20-hours-per-week minimum required under this rule.
Sign Signature of Student, then enter the Printed Name of Student and the Date (mm-dd-yyyy).
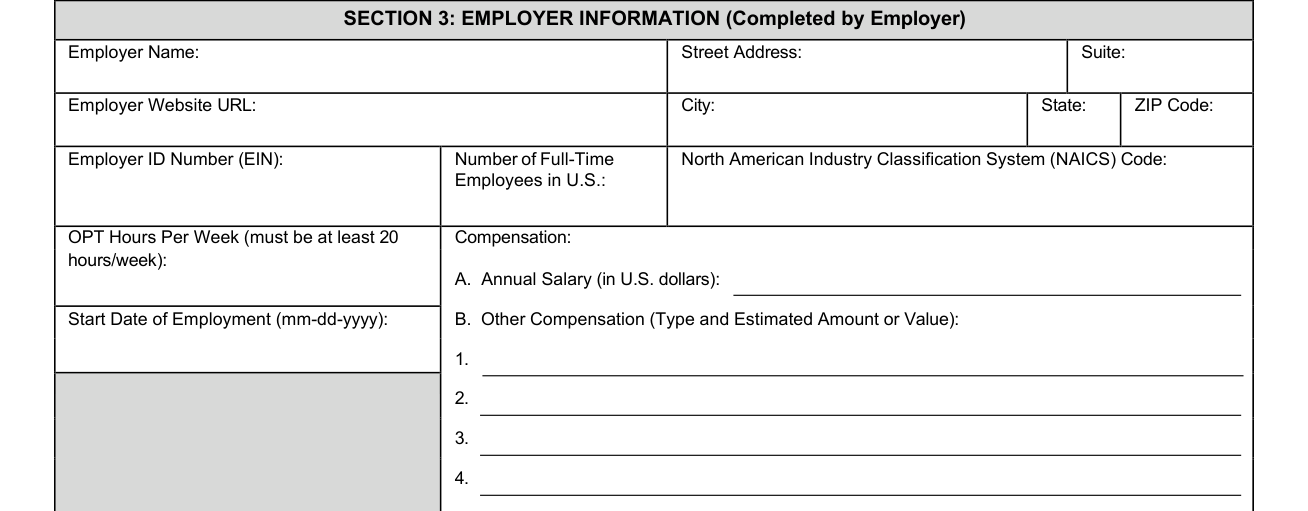
In SECTION 3: EMPLOYER INFORMATION (Completed by Employer), enter the Employer Name, Street Address, Suite, Employer Website URL, City, State and ZIP Code.
Enter the Employer ID Number (EIN), the Number of Full-Time Employees in U.S. and the North American Industry Classification System (NAICS) Code.
Enter the OPT Hours Per Week (must be at least 20 hours/week).
Enter the A. Annual Salary (in U.S. dollars), the Start Date of Employment (mm-dd-yyyy) and the B. Other Compensation (Type and Estimated Amount or Value).

On behalf of the employer, I certify that: I will notify the DSO at the earliest available opportunity regarding any material changes to this Plan, including any reduction in compensation from the amount previously submitted on the Plan that is not tied to a reduction in hours worked.
Within five business days of the termination or departure of the student during the authorized period of OPT, the employer will report such termination or departure to the DSO.
In SECTION 4: EMPLOYER CERTIFICATION, sign Signature of Employer Official with Signatory Authority, then enter the Printed Name and Title of Employer Official with Signatory Authority, the Date (mm-dd-yyyy) and the Printed Name of Employing Organization.
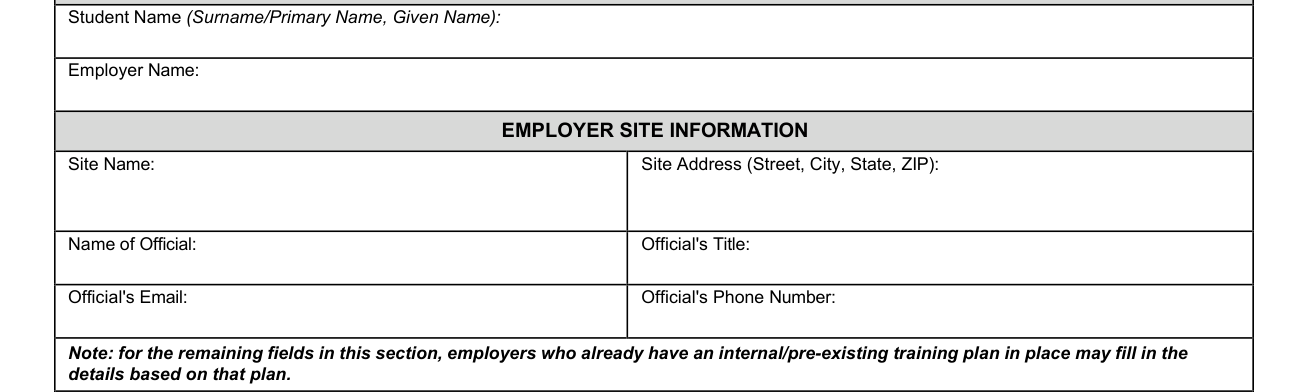
Enter the Student Name (Surname/Primary Name, Given Name) and the Employer Name.
Under EMPLOYER SITE INFORMATION, enter the Site Name, Site Address (Street, City, State, ZIP), Name of Official, Official's Title, Official's Email and Official's Phone Number.
For the remaining fields in this section, employers who already have an internal/pre-existing training plan in place may fill in the details based on that plan.

In Section 5, Training Plan for STEM OPT Students, Student Role: Describe the student's role with the employer and how that role is directly related to enhancing the student's knowledge obtained through his or her qualifying STEM degree.
Goals and Objectives: Describe how the assignment(s) with the employer will help the student achieve his or her specific objectives for work-based learning related to his or her STEM degree. The description must both specify the student's goals regarding specific knowledge, skills, or techniques as well as the means by which they will be achieved.
Employer Oversight: Explain how the employer provides oversight and supervision of individuals filling positions such as that being filled by the named F-1 student. If the employer has a training program or related policy in place that controls such oversight and supervision, please describe.
Measures and Assessments: Explain how the employer measures and confirms whether individuals filling positions such as that being filled by the named F-1 student are acquiring new knowledge and skills. If the employer has a training program or related policy in place that controls such measures and assessments, please describe.
Additional Remarks (optional): Provide additional information pertinent to the Plan.

Under Employer Official with Signatory Authority - I certify that: 2. I will conduct the required periodic evaluations of the student;* *See evaluation forms that follow for student's first evaluation, to occur before the one year anniversary of the start date of the student's STEM OPT employment authorization, and final program evaluation.
In SECTION 6: EMPLOYER OFFICIAL CERTIFICATION, add the Printed Name and Title and the Date (mm-dd-yyyy), and sign Signature of Employer Official with Signatory Authority.

In EVALUATION ON STUDENT PROGRESS and FINAL EVALUATION ON STUDENT PROGRESS, provide a self-evaluation of your performance, using the measures previously identified, in applying and acquiring new knowledge, skills, and competencies identified in the Training Plan for STEM OPT Students. Discuss accomplishments, successful projects, overall contributions, etc., during this review period. Address whether there are any modifications to the objectives and goals for projects, or new areas for skill and competency development.
Enter the Range of Evaluation Dates: From (mm-dd-yyyy) and To (mm-dd-yyyy); the student signs Signature of Student and enters the Printed Name of Student and the Date (mm-dd-yyyy); the employer official signs Signature of Employer Official with Signatory Authority and enters the Printed Name of Employer Official with Signatory Authority and the Date (mm-dd-yyyy).
Signature of Student and Signature of Employer Official with Signatory Authority.
[1] ICE Form I-983 (7/16), U.S. Immigration and Customs Enforcement (the Official source link on this page).