


California Advance Health Care Directive at a glance
What it is: ADVANCE HEALTH CARE DIRECTIVE (California Probate Section 4701): you have the right to give instructions about your own health care and to name someone else to make health care decisions for you.
Who signs: After completing this form, sign and date the form at the end.
Notary: The form must be signed by two qualified witnesses or acknowledged before a notary public.
A filled-in California Advance Health Care Directive example: a signer names a physician
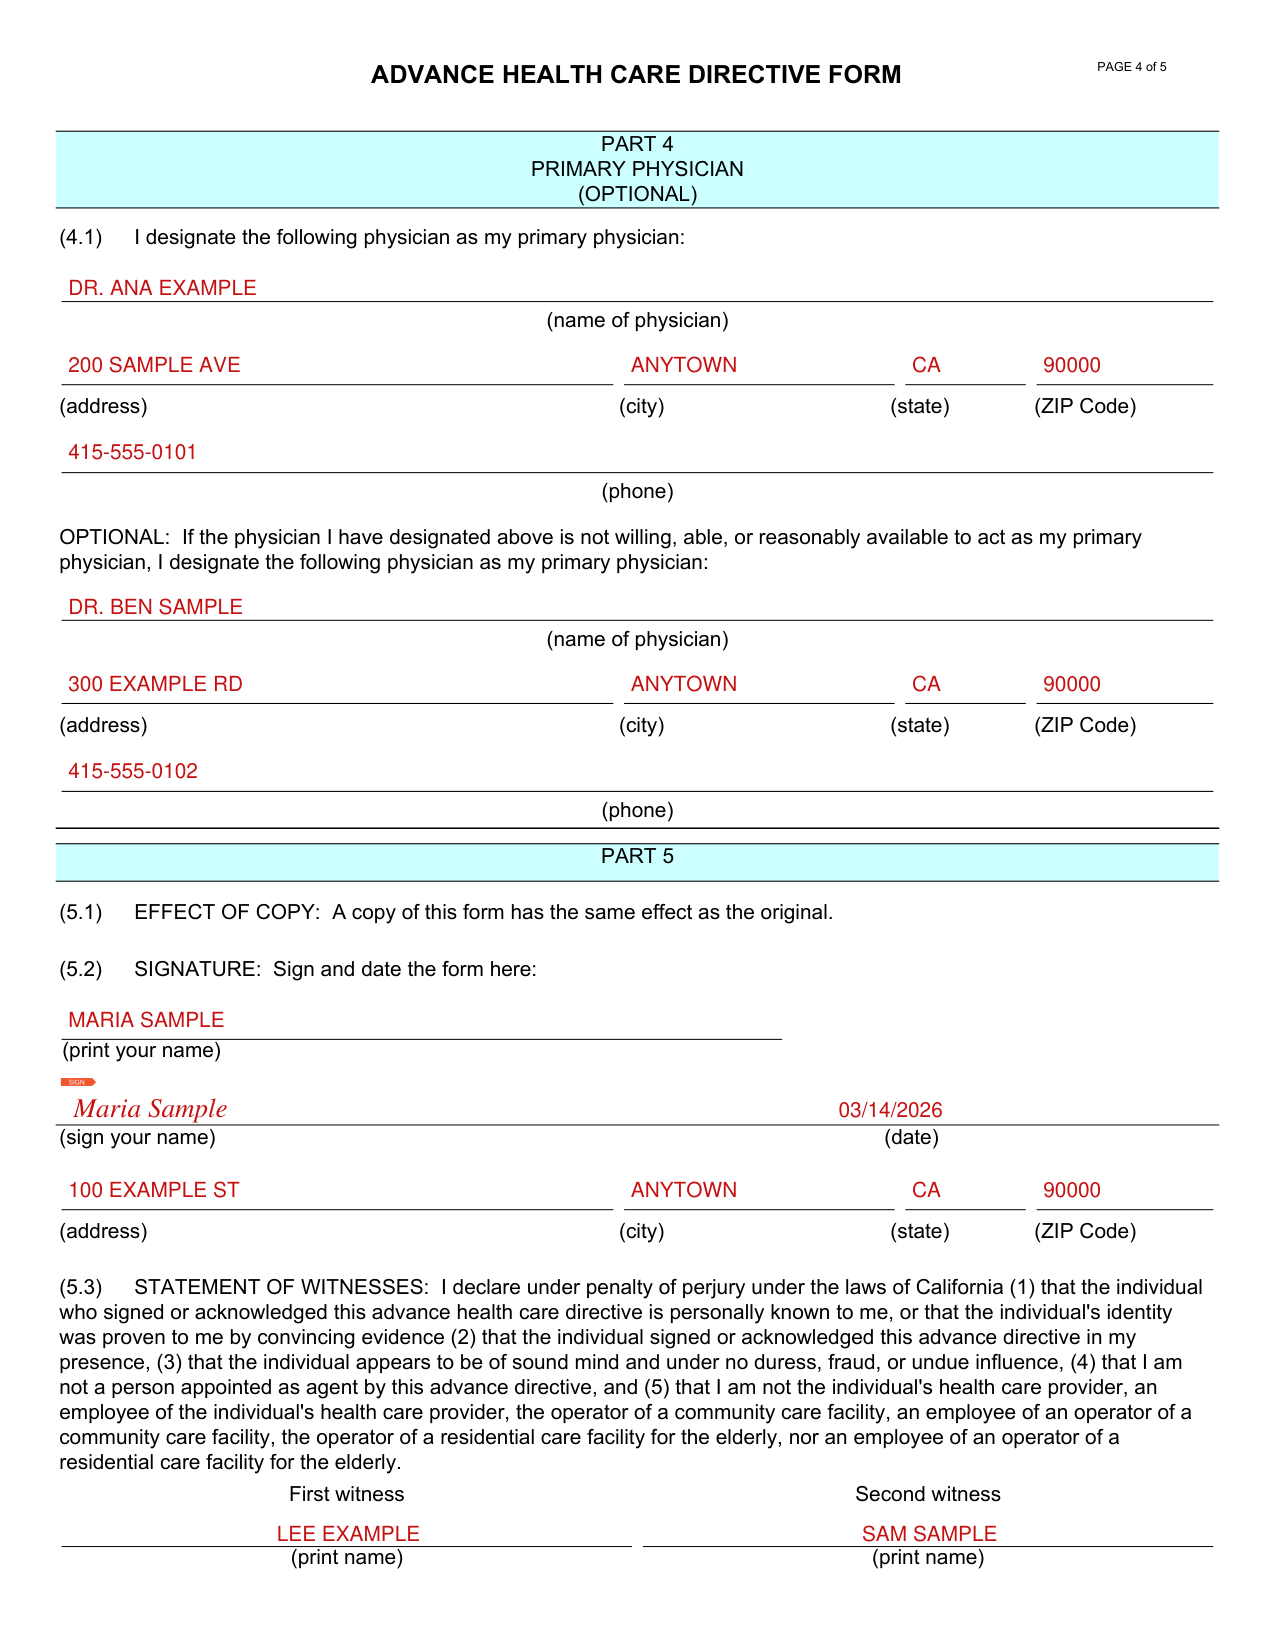
How to fill out California Advance Health Care Directive, box by box
Primary physician
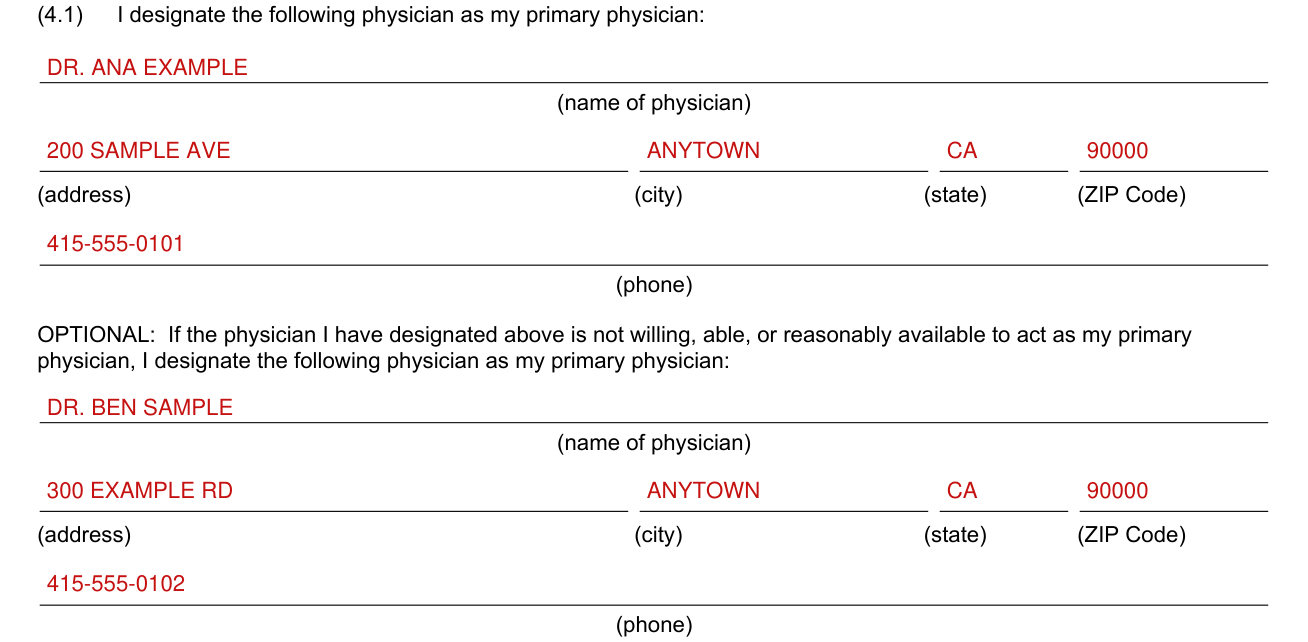
PART 4 PRIMARY PHYSICIAN (OPTIONAL): (4.1) enter the name, address, city, state, ZIP Code and phone of the physician you designate as your primary physician.
OPTIONAL: if the physician you have designated is not willing, able, or reasonably available to act as your primary physician, enter the name, address, city, state, ZIP Code and phone of the physician you designate.
Signature

In (5.2) SIGNATURE, sign and date the form: print your name, sign your name, enter the date, and enter your address, city, state and ZIP Code.
Statement of witnesses

In (5.3) STATEMENT OF WITNESSES, each witness declares under penalty of perjury under the laws of California (1) that the individual who signed or acknowledged this advance health care directive is personally known to the witness, or that the individual's identity was proven to the witness by convincing evidence (2) that the individual signed or acknowledged this advance directive in the witness's presence, (3) that the individual appears to be of sound mind and under no duress, fraud, or undue influence.
Each witness also declares (4) that the witness is not a person appointed as agent by this advance directive, and (5) that the witness is not the individual's health care provider, an employee of the individual's health care provider, the operator of a community care facility, an employee of an operator of a community care facility, the operator of a residential care facility for the elderly, nor an employee of an operator of a residential care facility for the elderly.
Under First witness and Second witness, each witness prints a name.
Witness address, signature and date
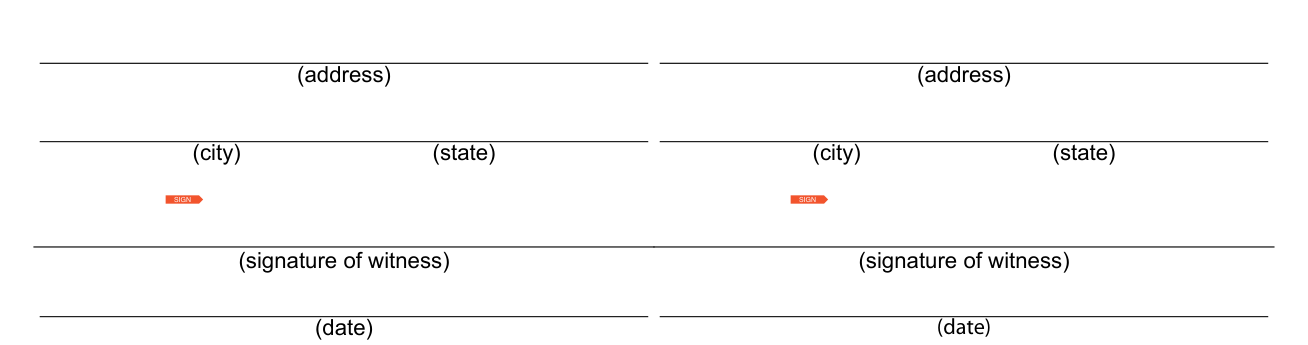
Each witness enters an address, city and state, the signature of witness, and the date.
Additional statement of witnesses

(5.4) ADDITIONAL STATEMENT OF WITNESSES: at least one of the witnesses must also sign the following declaration: I further declare under penalty of perjury under the laws of California that I am not related to the individual executing this advance health care directive by blood, marriage, or adoption, and to the best of my knowledge, I am not entitled to any part of the individual's estate upon his or her death under a will now existing or by operation of law.
The witness signs on the signature of witness line.
Special witness requirement

PART 6 SPECIAL WITNESS REQUIREMENT: (6.1) The following statement is required only if you are a patient in a skilled nursing facility, a health care facility that provides the following basic services: skilled nursing care and supportive care to patients whose primary need is for availability of skilled nursing care on an extended basis.
The patient advocate or ombudsman must sign the statement that declares under penalty of perjury under the laws of California that the signer is a patient advocate or ombudsman as designated by the State Department of Aging and is serving as a witness as required by Section 4675 of the Probate Code.
More rules for California Advance Health Care Directive
Give a copy of the signed and completed form to your physician, to any other health care providers you may have, to any health care institution at which you are receiving care, and to any health care agents you have named.
You have the right to revoke this advance health care directive or replace this form at any time.
(5.1) EFFECT OF COPY: A copy of this form has the same effect as the original.
Agent, instructions and donation
Designation of agent
Part 1 of this form is a power of attorney for health care. Part 1 lets you name another individual as agent to make health care decisions for you if you become incapable of making your own decisions or if you want someone else to make those decisions for you now even though you are still capable.
In (1.1) DESIGNATION OF AGENT, enter the name of the individual you choose as agent, then the address, city, state, ZIP Code, home phone and work phone.
Your agent may not be an operator or employee of a community care facility or a residential care facility where you are receiving care, or your supervising health care provider or employee of the health care institution where you are receiving care, unless your agent is related to your or is a coworker.
Alternate agents
You may also name an alternate agent to act for you if your first choice is not willing, able, or reasonably available to make decisions for you.
OPTIONAL: if you revoke your agent's authority or if your agent is not willing, able, or reasonably available to make a health care decision for you, enter the name, address, city, state, ZIP Code, home phone and work phone of your first alternate agent.
OPTIONAL: if you revoke the authority of your agent and first alternate agent or if neither is willing, able, or reasonably available to make a health care decision for you, enter the name, address, city, state, ZIP Code, home phone and work phone of your second alternate agent.
Part 2 instructions for health care
Part 2 of this form lets you give specific instructions about any aspect of your health care, whether or not you appoint an agent. If you are satisfied to allow your agent to determine what is best for you in making end-of-life decisions, you need not fill out Part 2 of this form.
If you fill out this part of the form, you may strike any wording you do not want.
(2.1) END-OF-LIFE DECISIONS: you direct that your health care providers and others involved in your care provide, withhold, or withdraw treatment in accordance with the choice you have marked.
(a) Choice Not to Prolong Life: you do not want your life to be prolonged if (1) you have an incurable and irreversible condition that will result in your death within a relatively short time, (2) you become unconscious and, to a reasonable degree of medical certainty, you will not regain consciousness, or (3) the likely risks and burdens of treatment would outweigh the expected benefits, OR
(b) Choice to Prolong Life: you want your life to be prolonged as long as possible within the limits of generally accepted health care standards.
In (2.2) RELIEF FROM PAIN, except as you state in the space, you direct that treatment for alleviation of pain or discomfort be provided at all times, even if it hastens your death. (Add additional sheets if needed.)
In (2.3) OTHER WISHES, if you do not agree with any of the optional choices and wish to write your own, or if you wish to add to the instructions you have given, you may do so here, after "I direct that:".
Donation of organs at death
Part 3 is OPTIONAL. (3.1) Upon your death, mark the applicable box: (a) you give any needed organs, tissues, or parts, OR (b) you give the following organs, tissues, or parts only.
(c) Your gift is for these purposes (strike any you do not want): (1) Transplant (2) Therapy (3) Research (4) Education.
Sources
[1] Advance Health Care Directive (California Probate Code Section 4701), generic template (the Official source link on this page).