

CalPERS Long-Term Care Claim Form at a glance
What it is: CalPERS Long-Term Care Claim Form. Filing a claim can be done in 4 steps.
Who signs: Signature of Participant (or Participant's Representative).
A filled-in CalPERS Long-Term Care Claim Form example: a participant names a contact person

How to fill out CalPERS Long-Term Care Claim Form, box by box
1. Participant and 2. Contact Person
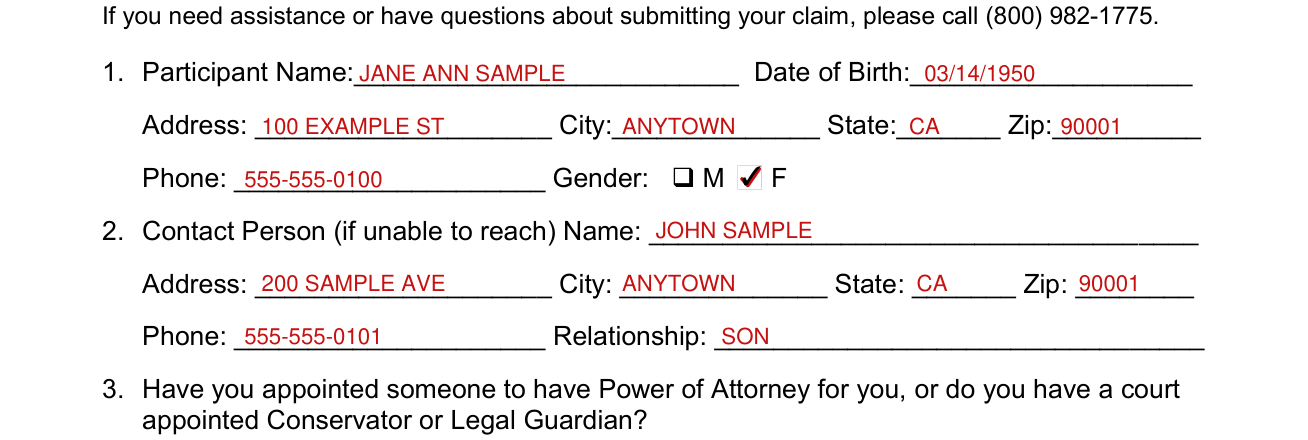
Under 1. Participant, enter the Name, Date of Birth, Address, City, State, Zip and Phone, and mark Gender M or F.
Under 2. Contact Person (if unable to reach), enter the Name, Address, City, State, Zip, Phone and Relationship.
3. Power of Attorney, Conservator or Legal Guardian

Have you appointed someone to have Power of Attorney for you, or do you have a court appointed Conservator or Legal Guardian?
If Yes (you have appointed someone to have Power of Attorney for you, or you have a court appointed Conservator or Legal Guardian), enter the Name, Address, City, State, Zip and Phone.
If you have appointed more than one person to represent you, provide information on the other person(s) on a separate sheet.
Please attach a copy of the legal documents executing the Power of Attorney, Conservatorship, or Legal Guardianship to this claim form before returning.
In accordance with The Health Insurance Portability and Accountability Act (HIPAA), information will not be disclosed to individuals who do not hold Power of Attorney, or who are not listed in your claim as an Authorized Individual. In order to authorize an individual please complete an Authorization for use and Disclosure of Protected Health Information form, which requires the participant's signature or the signature of a legal representative.
Cause or condition, injury or accident, attorney and hospitalized
What cause(s) or condition(s) result in your need for long-term care? (i.e., illness, injury or accident)
If your care needs were caused by an injury/accident, when, where and how did the injury/accident occur?
If your care needs were caused by an injury/accident, are you represented by an attorney in this matter? Please provide the following information about your attorney: Name, Phone, Address, City, State, Zip.
Please describe what long-term care assistance you think you need and when the need for such assistance began.
Are you currently hospitalized, or have you been hospitalized within the last year? Enter the Hospital Name/Address, From and To.
Current Physician and facility, Home Health Care or Adult Day Care
Please provide the following information: Name of Current Physician, Specialty, Address, City, State, Zip, Phone, Condition(s) being treated and From and To. Please attach additional pages if necessary.
Complete the information if applicable. Under Nursing Home, Assisted Living, Residential Care Facility, enter the Name of Facility, Address, City, State, Zip, Phone, Fax #, Date Admitted, Date Discharged and Payer Source.
Under Home Health Care or Adult Day Care Services, enter the Name of Provider, Address, City, State, Zip, Phone, Fax #, Date Admitted, Date Discharged and Payer Source.
Medicare and other insurance
Do you currently have coverage for medical care under Medicare? Mark No Medicare coverage, Part A only, Part B only or Part A and B.
Has a claim been submitted? Mark Yes or No.
Do you have any other insurance that may provide coverage? (Check all that apply) Worker's Compensation, Supplement to Medicare, Coverage under a Medical Plan, Other Long-Term Care, Other Third Party Coverage (Auto Insurance, Injury/Accident, Property Insurance, etc.), No Insurance or Unknown. For each insurance, enter the Company, Policy # and Phone. Has a claim been submitted? Yes or No. For your protection some states require that you be informed that any person who knowingly files a statement of claim containing false or misleading information is subject to criminal and civil penalties, depending upon the state.
Such actions may be deemed a felony and substantial fines may be imposed.
If benefits have been determined to be paid under this coverage as a result of your fraudulent action(s), those benefit amounts may be recovered directly from you or by reducing any subsequent benefit payments under this coverage.
SIGN: Signature of Participant
"I declare that all of the answers given are complete and true to the best of my knowledge and belief. I understand that the company reserves the right to require further proof."
Sign on the Signature of Participant (or Participant's Representative) line and enter the Date signed (Month, Day, Year), the Participant (or Participant's Representative) Name, Signed at (City, State) and, if Representative, the relationship to Participant.
More rules for CalPERS Long-Term Care Claim Form
The CalPERS Long-Term Care team is available to assist you throughout the process at (800) 982-1775.
Once your care begins, you will need to complete a claim form.
Call the Intake Team, Provide authorized representatives, Complete the claim form, Submit documentation.
Before you file a claim, please contact one of the Intake Specialists. You can reach an Intake Specialist at (800) 982-1775, Monday through Friday between 8:00 a.m. and 5:00 p.m. Pacific Time.
Provide as much detail as possible to each of the questions, including your and your providers' current addresses and telephone numbers.
Providing incomplete information may lengthen the claim processing time.
Feel free to attach additional pages if you need more room to respond to any question.
Sign the enclosed Authorization for Use and Disclosure of Protected Health Information form included with the claim packet.
If available, please submit a copy of your Government Issued Photo Identification (ID) such as your driver's license, state issued ID card or passport.
If your situation is different
You will not be handling your claim personally
If you will not be handling your claim personally, CalPERS will need one of the following so an authorized representative can manage the claim on behalf of the participant: A signed Third Party Authorization Form, or A copy of the Healthcare or Durable Power of Attorney document.
This form is written assuming you are the participant.
"This form is for use and disclosures only; it does not authorize anyone other than me or my legal representative to make any changes to my coverage, billing or demographic information."
You wish to use direct deposit
If you wish to use direct deposit for your benefit payments please complete and return the included Direct Deposit Form for Long-Term Care Claim Reimbursements.
On the Direct Deposit Form, check off one: Initial setup or Account Change. A copy of a voided check or savings account withdrawal slip must be attached to ensure the correct numbers are obtained. Please allow six weeks for setup of direct deposit.
You may elect to have benefits assigned to a service provider
You may elect to have benefits assigned directly to a service provider. To establish an assignment of benefits you must first establish if the provider is willing to consider assignment.
If the direct deposit is for a service provider, an Assignment of Benefits Form and a current W9 is required for the direct deposit request to be completed.
The assignment of benefits will not be in effect until the CalPERS Long-Term Care Program has received the completed form.
Note the assignment of benefits may be terminated in the future upon receipt of a written request stating you wish to revoke the assignment.
Completed Assignment of Benefits, W9, and Direct Deposit forms can be returned by mail to CalPERS Long-Term Care Program, P.O. Box 64902, St. Paul, MN 55164-0902, or faxed to 1-866-294-6967.
Common questions about CalPERS Long-Term Care Claim Form
Where do I file it?
Mail the completed claim form, a copy of your Government Issued Photo Identification (ID) such as your driver's license, state issued ID card or passport and all available claim documentation to: CalPERS Long-Term Care Program P.O. Box 64902 St. Paul, MN 55164-0902 FAX: (866) 294-6967.
Sources
[1] CalPERS Long-Term Care Claim Form (CLM - 001 Online Claim Form LTCG), CalPERS Long-Term Care Program (the Official source link on this page).