
Form CFS 431-A at a glance
What it is: CFS 431-A is the PSYCHOTROPIC MEDICATION REQUEST FORM of the Illinois Department of Children & Family Services.
Where and when to file: Fax completed form to 312-814-7015. Requests for consent can now be submitted online. Visit guardianconsent.dcfs.illinois.gov to learn more and submit your consent request today!
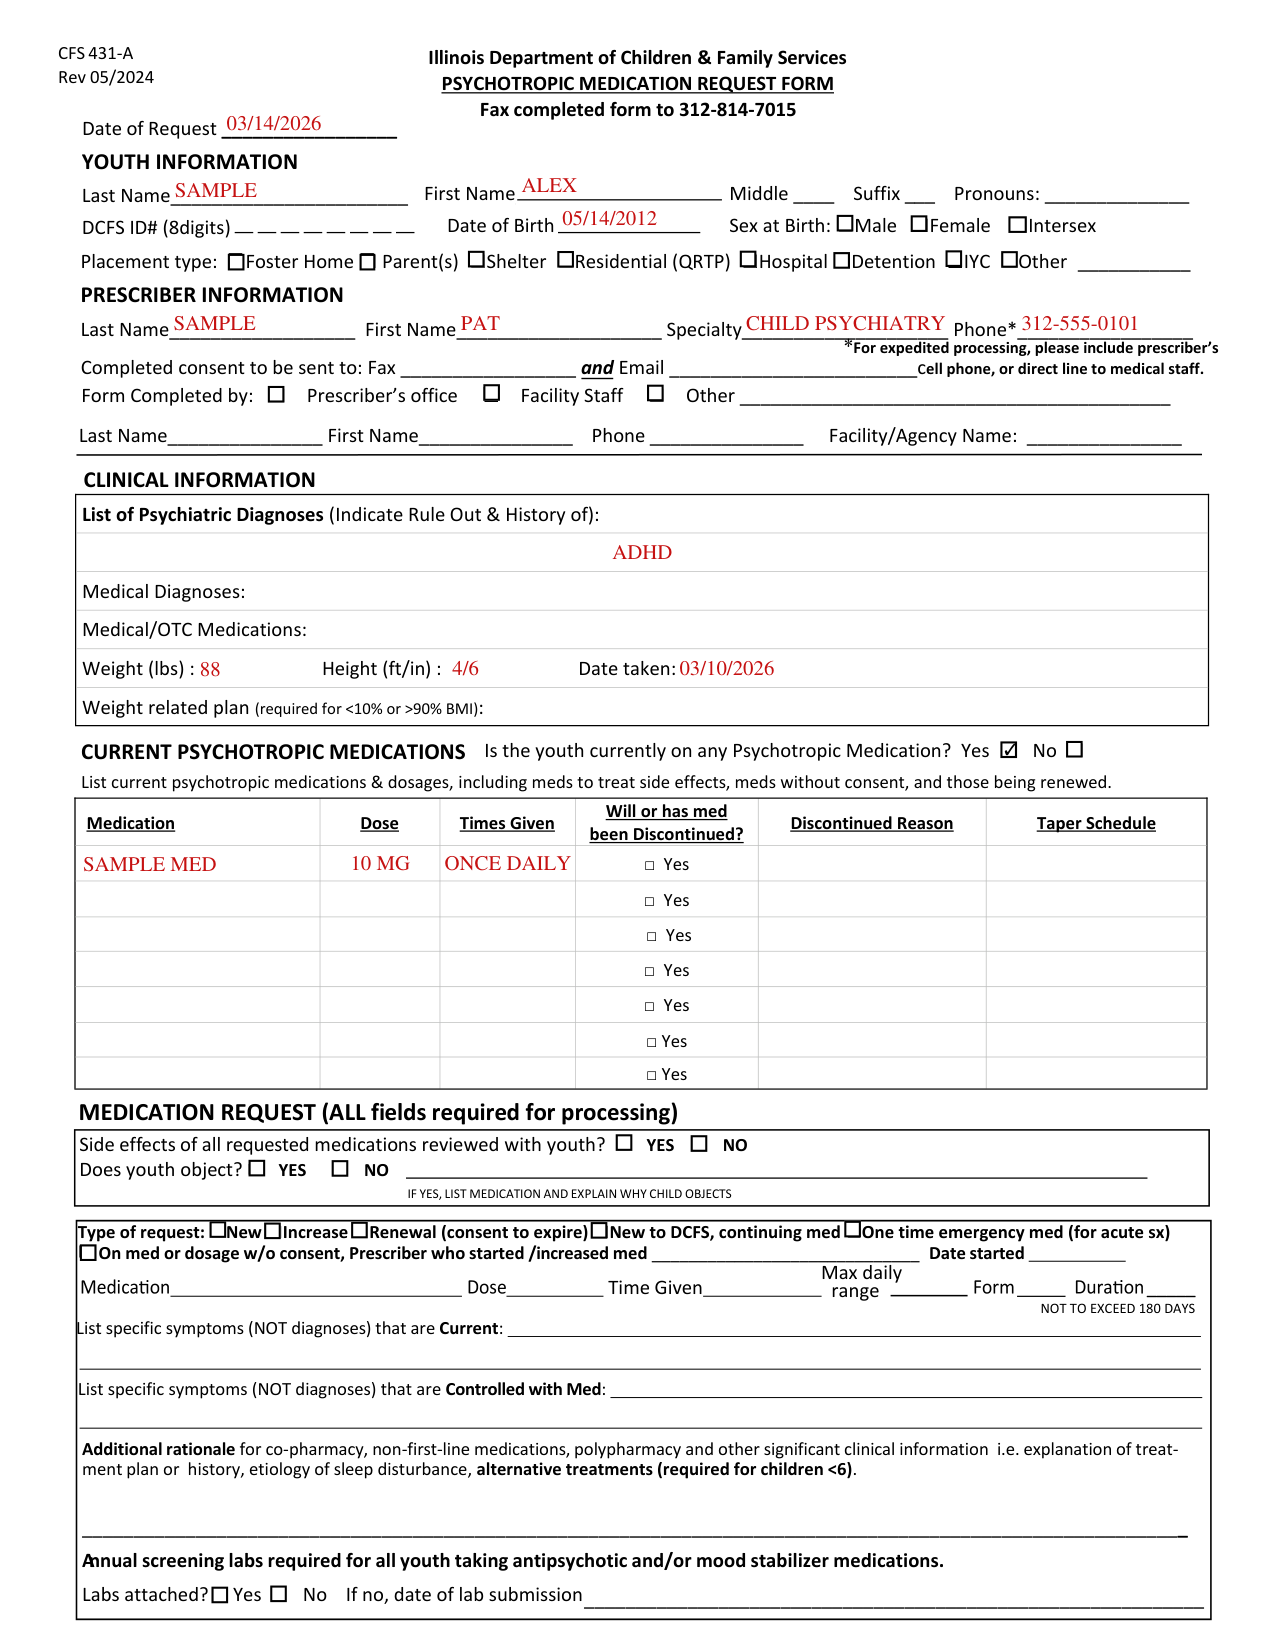
A filled-in Form CFS 431-A example: a medication request for one youth
How to fill out Form CFS 431-A, box by box
Date of Request and youth information

Enter the Date of Request.
Under YOUTH INFORMATION, enter the Last Name, First Name, Middle, Suffix and Pronouns.
Enter the DCFS ID# (8digits) and the Date of Birth.
Mark Sex at Birth: Male, Female or Intersex.
Mark the Placement type: Foster Home, Parent(s), Shelter, Residential (QRTP), Hospital, Detention, IYC or Other.
Prescriber information
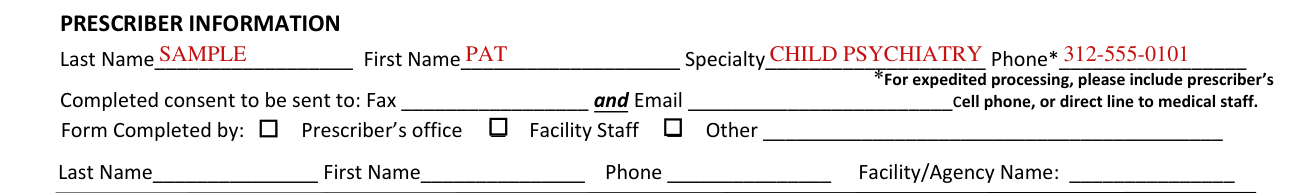
Under PRESCRIBER INFORMATION, enter the Last Name, First Name, Specialty and Phone*. For expedited processing, please include prescriber's cell phone, or direct line to medical staff. Enter the Fax and Email where the Completed consent is to be sent.
Mark Form Completed by: Prescriber's office, Facility Staff or Other. Enter the Last Name, First Name, Phone and Facility/Agency Name.
Clinical information
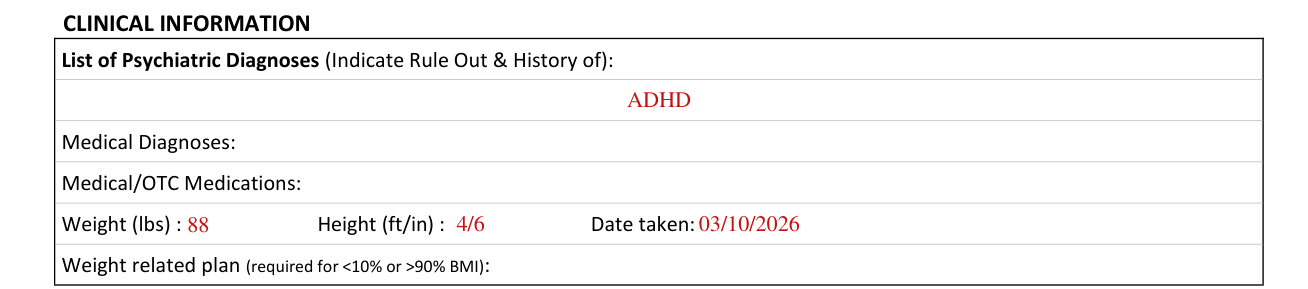
Under CLINICAL INFORMATION, list the Psychiatric Diagnoses and indicate Rule Out & History of.
List the Medical Diagnoses and the Medical/OTC Medications.
Enter the Weight (lbs), Height (ft/in) and Date taken.
Enter the Weight related plan (required for <10% or >90% BMI).
Current psychotropic medications
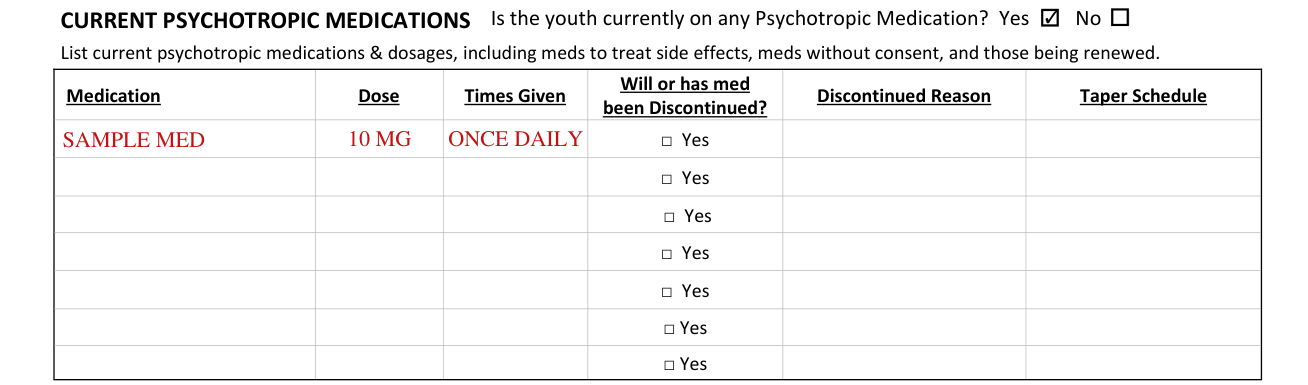
Under CURRENT PSYCHOTROPIC MEDICATIONS, mark Yes or No: is the youth currently on any Psychotropic Medication?
List current psychotropic medications & dosages, including meds to treat side effects, meds without consent, and those being renewed.
For each, enter the Medication, Dose and Times Given, mark Yes if the medication will or has been Discontinued, and enter the Discontinued Reason and Taper Schedule.
Medication request
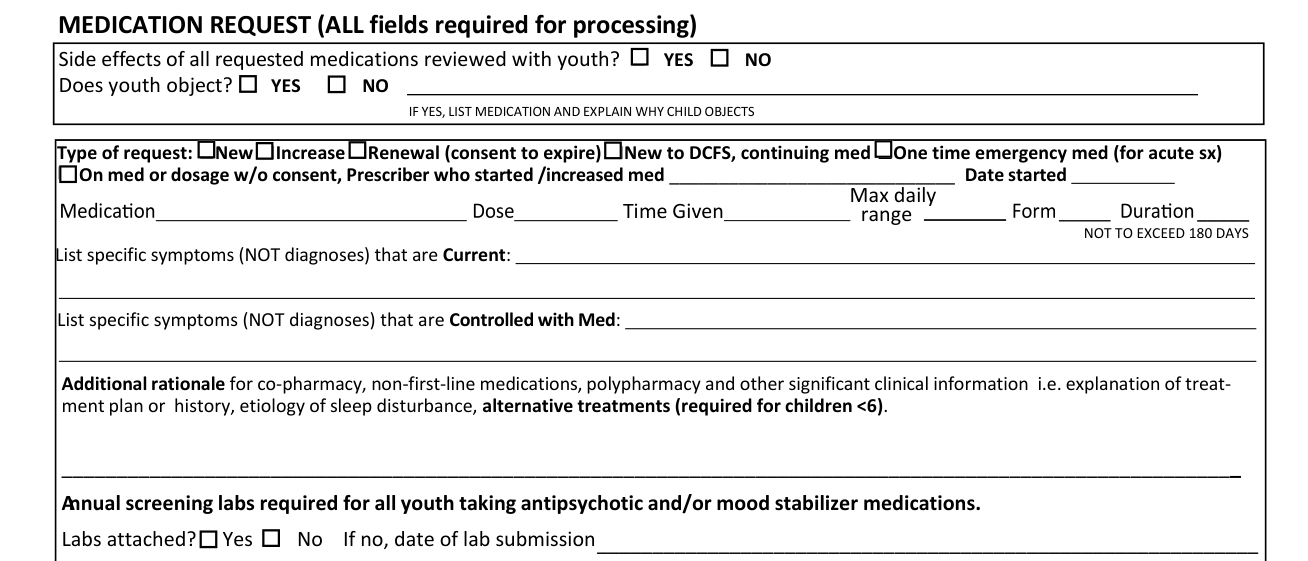
Under MEDICATION REQUEST (ALL fields required for processing), mark YES or NO for Side effects of all requested medications reviewed with youth, and YES or NO for Does youth object.
If yes, list medication and explain why child objects.
Mark the Type of request: New, Increase, Renewal (consent to expire), New to DCFS, continuing med, One time emergency med (for acute sx) or On med or dosage w/o consent. Enter the Prescriber who started /increased med and the Date started.
Enter the Max daily range and the Time Given.
NOT TO EXCEED 180 DAYS.
List specific symptoms (NOT diagnoses) that are Current, and list specific symptoms (NOT diagnoses) that are Controlled with Med.
Enter the Additional rationale for co-pharmacy, non-first-line medications, polypharmacy and other significant clinical information i.e. explanation of treatment plan or history, etiology of sleep disturbance, alternative treatments (required for children <6).
Annual screening labs are required for all youth taking antipsychotic and/or mood stabilizer medications. Mark Labs attached? Yes or No, and if no, enter the date of lab submission.
More rules for Form CFS 431-A
Page 2 is not to be sent without page 1. Enter the Youth's name and DCFS ID#.
Common questions about Form CFS 431-A
Where do I file it?
Fax completed form to 312-814-7015.
Sources
[1] Form CFS 431-A (Rev 05/2024), Psychotropic Medication Request Form, Illinois Department of Children & Family Services (the Official source link on this page).