


Form DHS 1266 at a glance
What it is: Form DHS 1266 is the Employment Record and Payroll Certification Form of the State of Hawaii Department of Human Services, Benefit, Employment and Support Services Division.
Who signs: The Applicant/Recipient signs and dates to give permission for the release of information to the Department of Human Services regarding their employment and earnings. The Employer's Representative signs to certify that the information provided is a true and correct extract from the employment and payroll record(s), of which the undersigned has legal custody.
A filled-in Form DHS 1266 example: a payroll clerk answers for a former employee

How to fill out Form DHS 1266, box by box
TO, DATE, SSN and BD

Employment and payroll record information on the individual is being requested; fill in TO, DATE, RE, SSN and BD, and the date after Please respond by.
1. to 3. Starting and ending dates of employment, Nature of employment, Reason for termination

Enter the starting and ending dates of employment From and To, the Nature of employment, and the Reason for and type of termination from employment (i.e., quit, fired, laid-off) and Last day worked.
4. to 9. Pension, sick pay and other payments

4. Is there any possibility of your re-employing this individual now or anytime in the future? If YES, approximate date:
5. Is this individual entitled to a pension? If YES, furnish date and amount of each payment.
6. Did this individual receive any sick pay, vacation pay, or severance pay upon termination? If YES, furnish date and amount of each payment (attach separate sheet).
7. Did this individual receive any cash payments or commissions other than those recorded in wage or salary pay records? If yes, date and amount of each payment (attach separate sheet).
8. Did this individual receive compensation, gifts, rewards, or premiums in place of financial payments? If YES, please describe type of compensation and date given (attach separate sheet).
9. Did this individual apply for and receive any Workmen's Compensation or Temporary Disability Insurance claim payments while employed by you? If YES, furnish dates and amount of each payment or give the name of the insurance carrier or other agency providing benefits: If NO, state reasons for ineligibility.
10. and 11. Is health insurance available

10. Is health insurance available? YES NO Was this individual covered by any health plan(s)? If YES, Plan and No.: Type of coverage (i.e., basic, drug, vision, dental): Effective date: Names of persons covered by plans: Termination date of health insurance plan:
11. If health insurance is not available, please state reason(s) why the employee is not eligible for service.
12. Please attach copies of payroll records
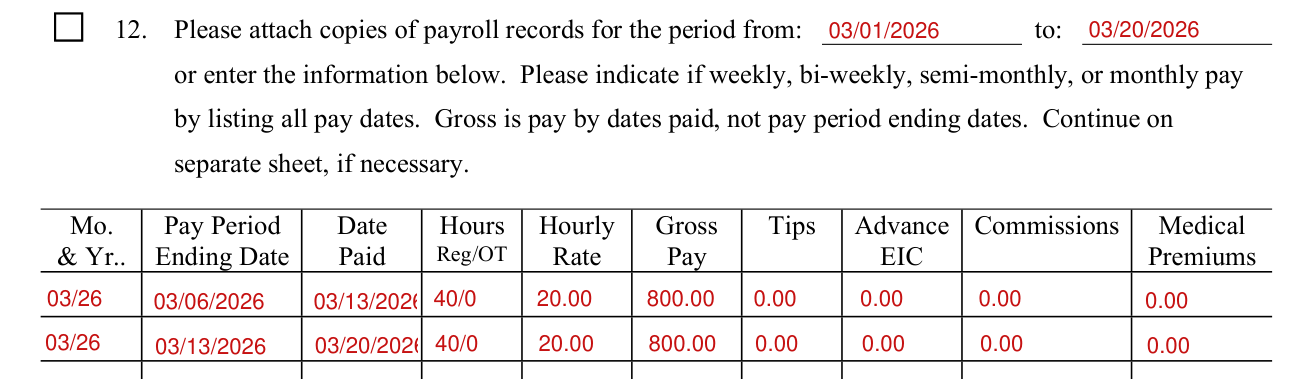
12. Please attach copies of payroll records for the period from: to: or enter the information, and indicate if weekly, bi-weekly, semi-monthly, or monthly pay by listing all pay dates.
Gross is pay by dates paid, not pay period ending dates.
For each line enter the Pay Period Ending Date, Date Paid, Hours Reg/OT, Hourly Rate, Gross Pay, Tips, Advance EIC, Commissions and Medical Premiums.
Continue on separate sheet, if necessary.
Additional Comments and the Signature

Write Additional Comments, then the Employer's Representative and Job Title, the Signature, Phone and Date Prepared.
More rules for Form DHS 1266
Distribution: Original to Employer; Copy to Case File.
Sources
[1] Form DHS 1266 (2/03), Employment Record and Payroll Certification Form, State of Hawaii Department of Human Services (the Official source link on this page).