

Form DSHS 14-078 at a glance
What it is: This is the Eligibility Review form, DSHS 14-078 (REV. 09/2026). For healthcare, this form can only be used to renew coverage for the Washington Apple Health programs listed on this form.
Where and when to file: You can take your review to a local office or fax to 1-888-338-7410.
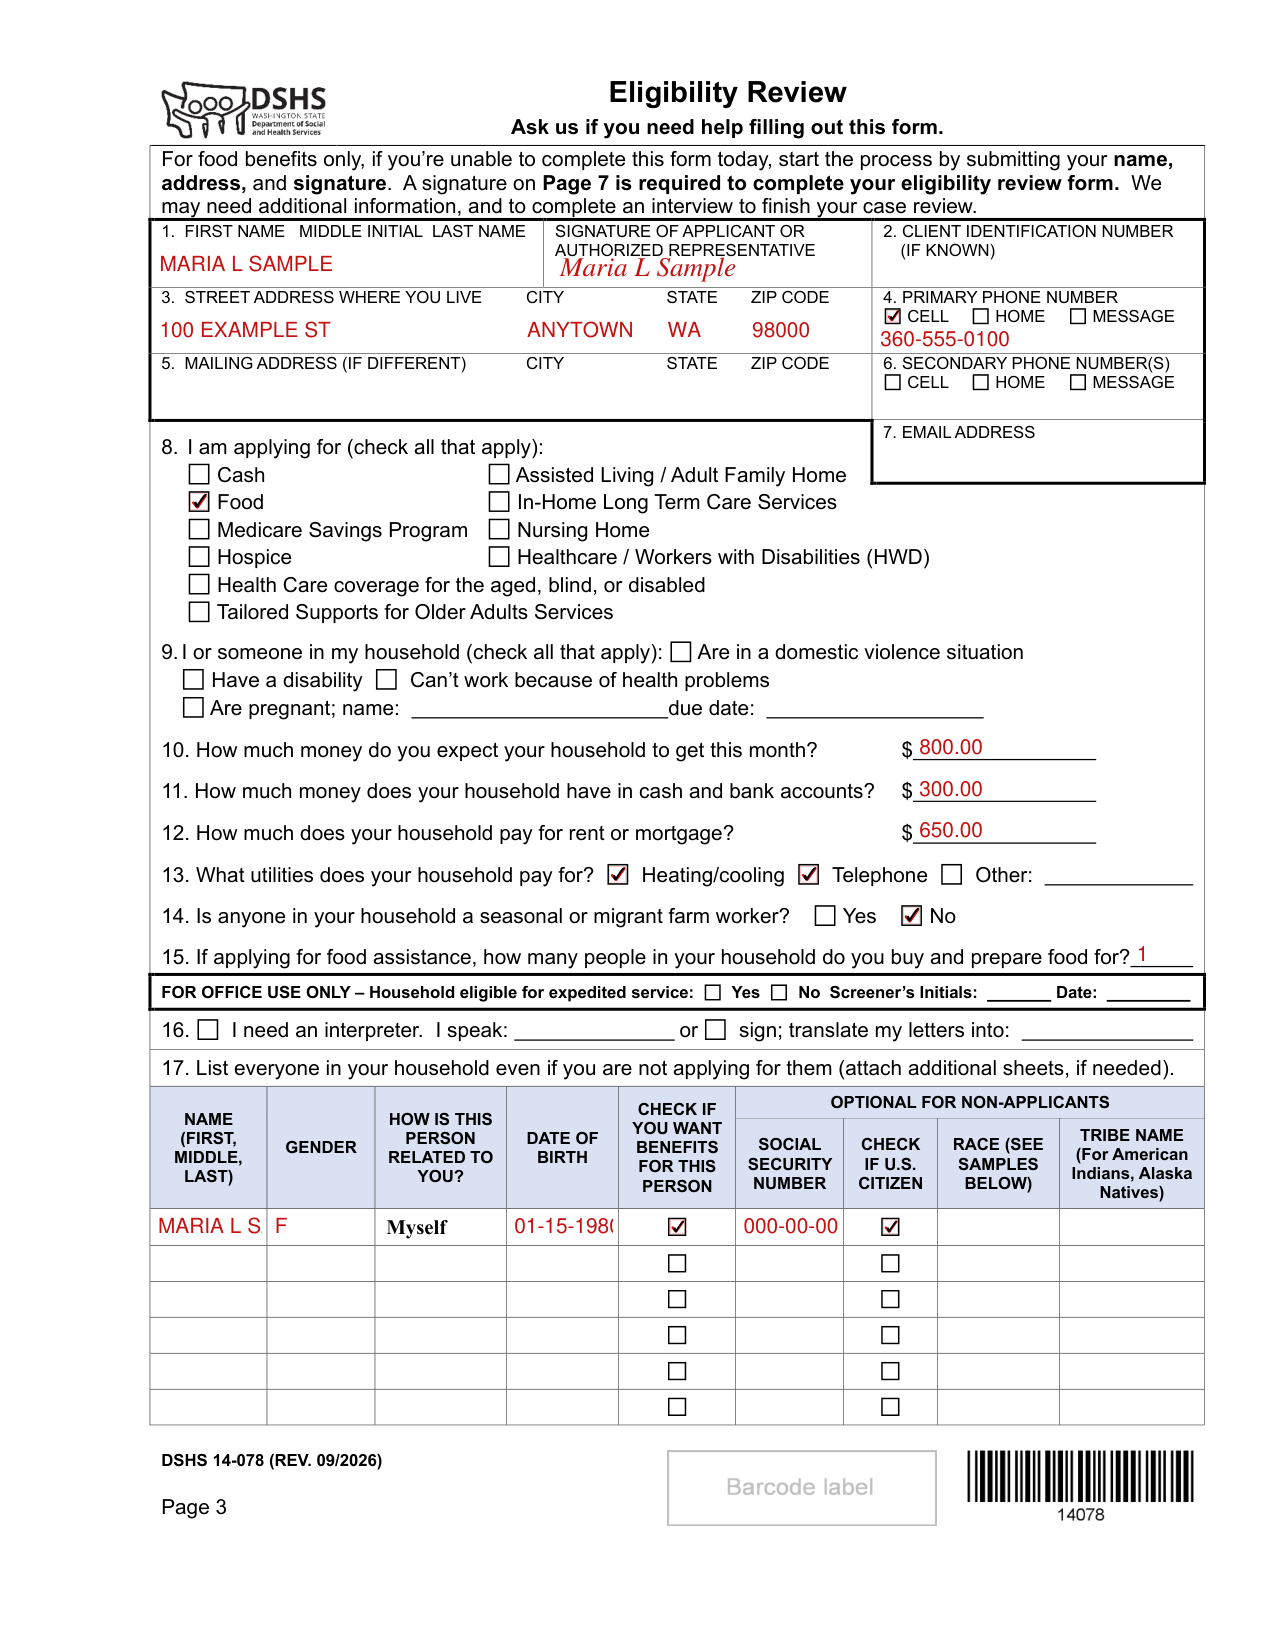
A filled-in Form DSHS 14-078 example: a single adult asks for food assistance
How to fill out Form DSHS 14-078, box by box
Your name, address and phone numbers
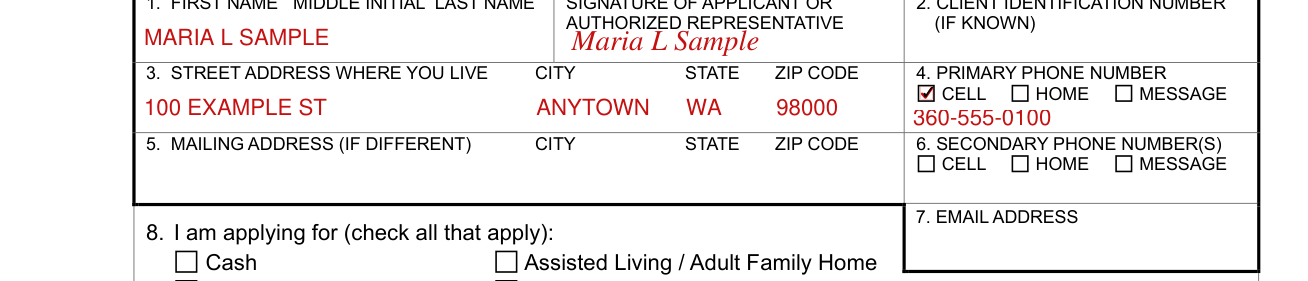
You can start the process now by submitting this review at a community services office. It must have your name, address, and signature or the signature of your authorized representative. You can file your review now even if it only contains these three items. For food benefits only, if you're unable to complete this form today, start the process by submitting your name, address, and signature.
A signature on Page 7 is required to complete your eligibility review form.
Write your first name, middle initial and last name, your client identification number if known, the street address where you live, city, state and zip code, your primary phone number, your mailing address if different, your secondary phone numbers and your email address. Check cell, home or message for a phone number.
Sign on the line for the signature of the applicant or authorized representative.
I am applying for

Under 8. I am applying for, check all that apply: Cash, Assisted Living / Adult Family Home, Food, In-Home Long Term Care Services, Medicare Savings Program, Nursing Home, Hospice, Healthcare / Workers with Disabilities (HWD), Health Care coverage for the aged, blind, or disabled, Tailored Supports for Older Adults Services.
I or someone in my household

Under 9. I or someone in my household, check all that apply: Are in a domestic violence situation, Have a disability, Can't work because of health problems, Are pregnant (write the name and the due date).
Money, rent and utilities

Write how much money you expect your household to get this month, how much money your household has in cash and bank accounts, and how much your household does pay for rent or mortgage.
Under 13. What utilities does your household pay for, check Heating/cooling, Telephone or Other.
Farm worker, food household and interpreter

Check Yes or No: is anyone in your household a seasonal or migrant farm worker (14)?
If applying for food assistance, write how many people in your household you buy and prepare food for (15).
Under 16, check I need an interpreter, then fill in I speak or sign and translate my letters into.
List everyone in your household
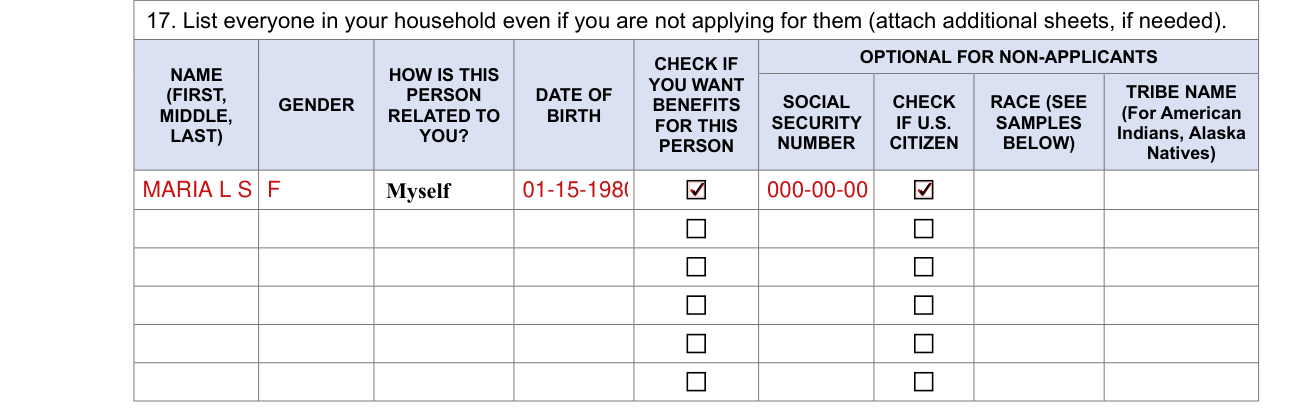
List everyone in your household even if you are not applying for them (attach additional sheets, if needed).
Under Federal Law (42 CFR § 435.910, 45 CFR §205.52, 7 CFR §273.6), you must give the Social Security Number (SSN) for anyone you live with who applies for Washington Apple Health, TANF, or food assistance. SSNs of parents and spouses who live with you but don't apply may also be needed.
For each person fill in the name (first, middle, last), gender, how this person is related to you, date of birth, Social Security number (optional for non-applicants), race and tribe name (for American Indians, Alaska Natives), and check if you want benefits for this person and check if U.S. citizen.
Race examples: White, Black or African American, Asian, Native Hawaiian, Pacific Islander, American Indian, Alaska Native, or any combination of races.
More rules for Form DSHS 14-078
You may get more benefits or get them sooner if you complete the form by answering the questions, signing page seven and giving your review and any other information as soon as you can.
If you need help reading or completing this form, please ask for help. Keep Page 1 for your records.
Other situations
You need food assistance right away
If you need food assistance right away, fill in Questions 1 through 14 and take this form to your local office.
You are applying from an institution
If you are submitting your application from an institution, the start date is the date of your release or discharge.
You are applying for Food Assistance and other programs
If you're applying for Food Assistance and other programs: the SNAP rules for processing your application must be followed. This includes processing the application within time limits, issuing proper notices, and advising you of your administrative rights. Your Food Assistance cannot be denied just because your application for other assistance programs was denied.
File a program discrimination complaint
The USDA, its agencies, offices, employees, and institutions participating in or administering USDA programs are prohibited from discriminating based on race, color, national origin, religion, sex, disability, age, marital status, family/parental status, income derived from a public assistance program, political beliefs, or reprisal or retaliation for prior civil rights activity, in any program or activity conducted or funded by USDA (not all bases apply to all programs). Remedies and complaint filing deadlines vary by program or incident.
Persons with disabilities who require alternative means of communication for program information (e.g., Braille, large print, audiotape, American Sign Language, etc.) should contact the state or local agency that administers the program or contact USDA through the Telecommunications Relay Service at 711 (voice and TTY). Additionally, program information may be made available in languages other than English.
To file a program discrimination complaint, complete the USDA Program Discrimination Complaint Form, AD- 3027, found online at How to File a Program Discrimination Complaint and at any USDA office or write a letter addressed to USDA and provide in the letter all of the information requested in the form. To request a copy of the complaint form, call (866) 632-9992. Submit your completed form or letter to USDA by: 1. Mail: USDA Food and Nutrition Service, 1320 Braddock Place, Room 334 Alexandria, VA 22314; or 2. Email: FNSCIVILRIGHTSCOMPLAINTS@usda.gov.
Common questions about Form DSHS 14-078
Who signs it?
For cash, all adults (or authorized representatives) in the household must sign. For health care coverage, the applicant (or authorized representative) must sign. For food assistance, both the applicant and authorized representative must sign unless there is a current authorized representative document on file.
Is there a deadline?
If you need food assistance right away, fill in Questions 1 through 14 and take this form to your local office: eligibility for food assistance is decided within 7 days if you show proof of your identity and meet eligibility rules. Benefits are issued by the day after you are decided eligible. Food assistance usually starts the day your application is received. Cash assistance usually starts the day there is all the information to decide you are eligible. Eligibility for Food Assistance must be decided within 30 days of the date you submit your application.
Where do I file it?
Mail your review to one of the following: DSHS CSD-Customer Service Center, PO Box 11699, Tacoma, WA 98411-6699; or Home and Community Services - Long Term Care Services, PO Box 45826, Olympia, WA 98504-5826. You can fill out this review online at www.washingtonconnection.org
Is there a penalty?
Any member who breaks any of the rules on purpose can be subject to prosecution under other applicable Federal and State laws, barred from the SNAP for one year to permanently, fined, imprisoned up to 20 years, or barred from SNAP for an additional 18 months if court ordered.
What am I certifying when I sign?
By signing, you certify or declare under penalty of perjury under the laws of the State of Washington that the information you gave in this application, including the information concerning citizenship and alien status of the members applying for benefits, is true and correct.
When is this form not the right one?
This form can only be used to renew coverage for the Washington Apple Health programs listed on this form. For other healthcare coverage you must apply either online at www.wahealthplanfinder.org, by calling 1-855-923-4633, or by using the HCA Application for Health Care Coverage (HCA 18-001).
Sources
[1] DSHS 14-078 Eligibility Review (REV. 09/2026), Washington State Department of Social and Health Services (the Official source link on this page).
