


Form DE 2523F at a glance
What it is: Form DE 2523F is the Report of Voluntary Plan Family Leave (VPFL) Claim.
Where and when to file: Submit the completed form to EDD-Paid Family Leave (PFL), PO Box 997017, Sacramento, CA 95899-7017.
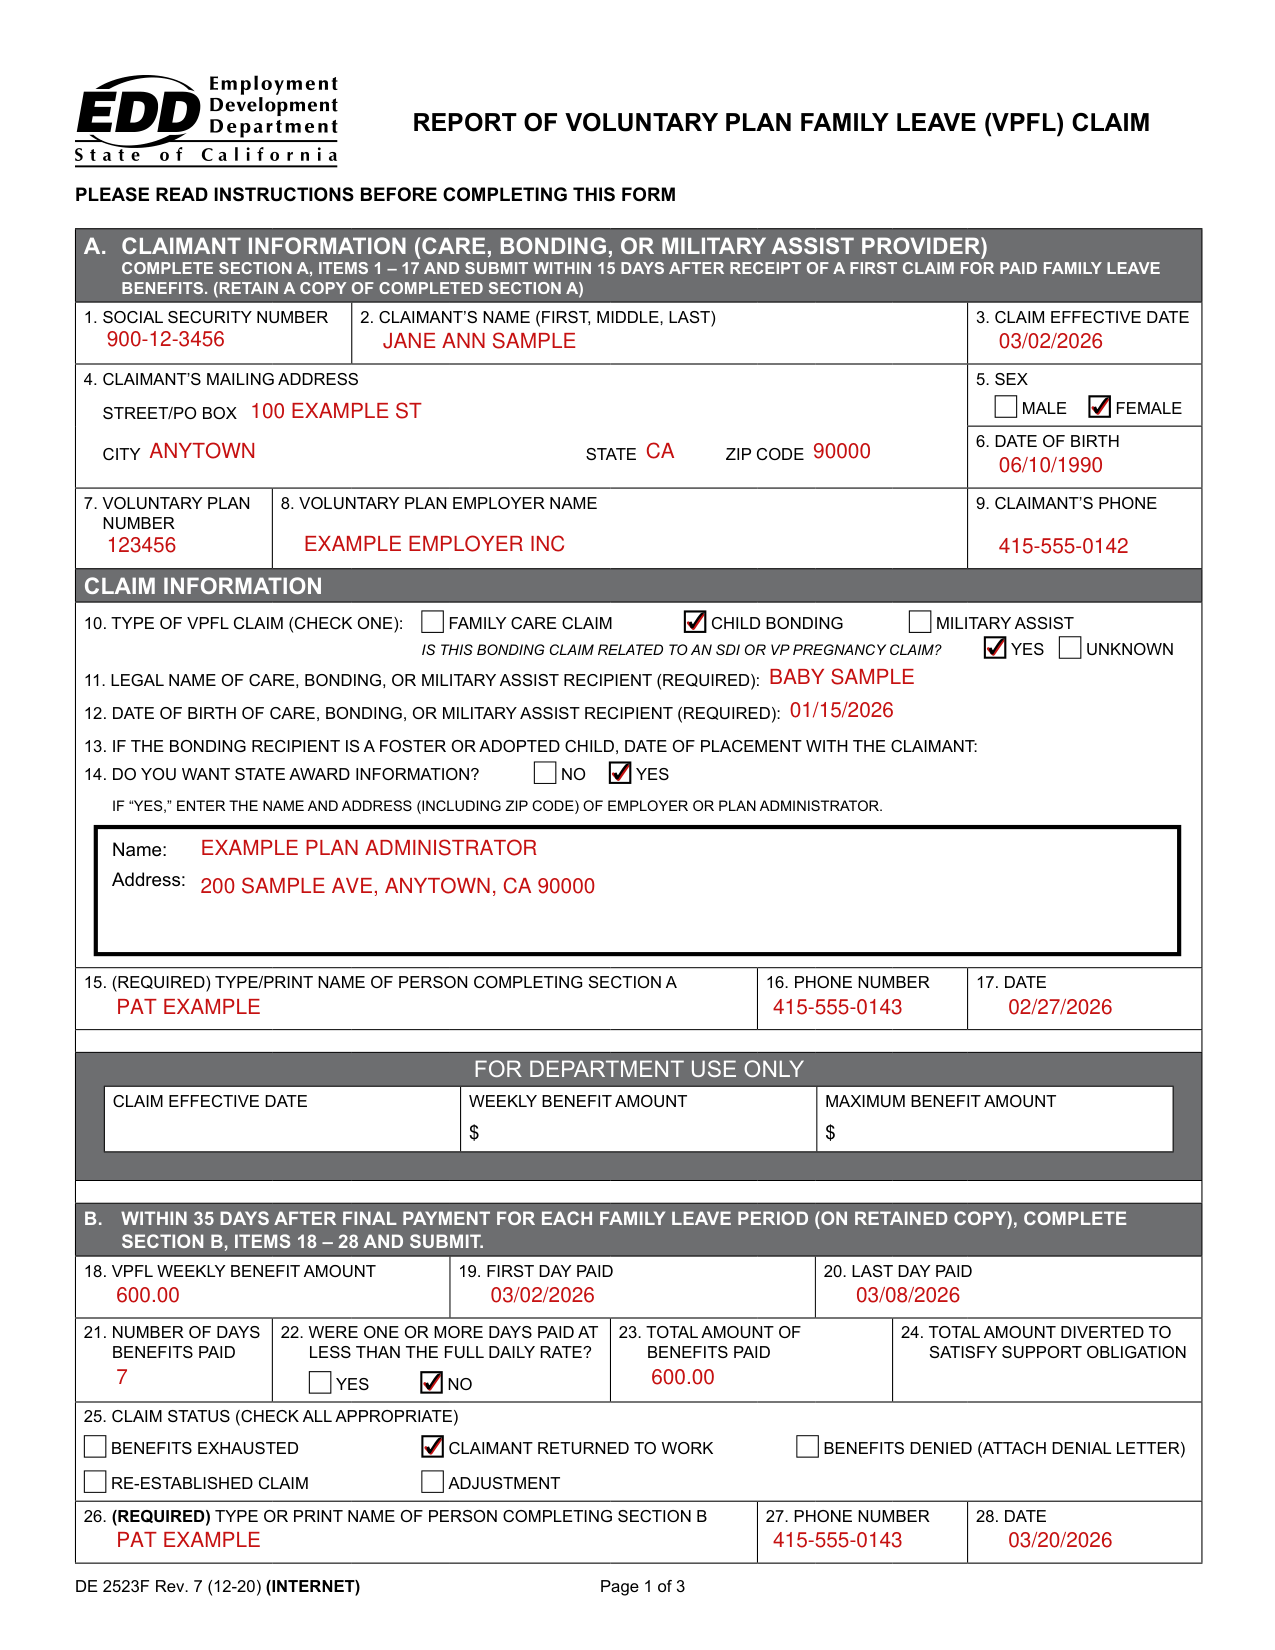
A filled-in Form DE 2523F example: a bonding claim reported in both sections
How to fill out Form DE 2523F, box by box
Section A: Social Security number, name and claim effective date

Common mistake: Enter all digits of VPFL claimant's Social Security number (SSN). (A claim cannot be processed without an accurate SSN. The use of an incorrect SSN can result in erroneous notices to the claimant and employer.)
Enter the VPFL claimant's full name.
Enter the claim effective date the VPFL claim began. This is the date the claimant has given as the first date he/she wants benefits to begin.
Claimant's mailing address, sex and date of birth

Enter the VPFL claimant's current mailing address.
Sex: enter a check mark in the appropriate box.
Enter the month, day, and year of the VPFL claimant's date of birth.
Voluntary plan number, employer name and phone

Enter the six digit voluntary plan number.
Enter the voluntary plan employer's name.
Enter the claimant's phone number.
Type of VPFL claim

Check the appropriate box for care for family member, bond with child, or military assist.
If the VP previously paid benefits on a disability pregnancy claim, and the claimant is now requesting child-bonding benefits for the same child, check the "Yes" box. If unsure of the type of claim previously paid, check the "Unknown" box.
Care, bonding or military assist recipient

Enter the legal name of the care, bonding, or military assist recipient who will receive family care.
Enter the date of birth of care, bonding, or military assist recipient (required).
If the bonding recipient is a foster or adopted child, enter the date that the foster or adopted child was placed in the claimant's home.
State award information

Do you want State award information? Check the appropriate box, No or Yes.
If "Yes" is checked, enter the name and address (including ZIP code) of the employer or plan administrator.
The Department will mail the award information to the address provided.
Person completing Section A

Enter the printed name of the person completing Section A (required).
Enter the phone number of the person completing Section A.
For Section A, enter the current date.
Section B: weekly benefit amount, first and last day paid and number of days
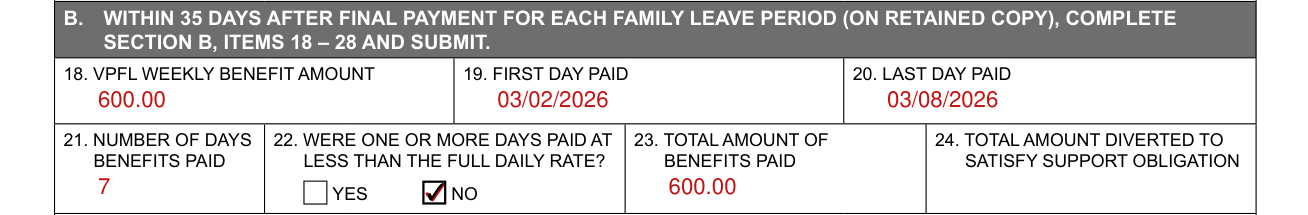
Enter the Voluntary Plan weekly benefit amount.
Enter the first date for which benefits were paid.
Enter the last date for which benefits were paid.
Enter the number of days for which benefits were paid.
Paid at less than the full daily rate

Check the appropriate box. If the claimant was paid less than his/her full daily benefit rate for one or more days, check the "Yes" box.
If the claimant did not receive less than his/her full daily benefit rate for any days which benefits were paid, check the "No" box.
Total benefits paid and amount diverted to satisfy a support obligation

Enter the total dollar amount of benefits paid.
Common mistake: Enter the amount of PFL benefits that were diverted to satisfy a support obligation. (Enter the amount of benefits withheld under the Support Intercept Program.) This amount must be included in the total of item 23.
Claim status

Check the boxes that apply to the current claim status.
Benefits Exhausted: The total maximum benefit amount was paid on the claim.
PFL claimant has returned to work: Self-explanatory. Benefits Denied: No benefits have been paid.
Common mistake: If benefits are denied, include with this form a copy of the claimant's denial letter. You are required to notify the claimant in writing if you deny benefits in whole or in part. A copy of that letter must be sent to the Department with the DE 2523F.
Re-established claim: This applies if there has been a break in benefit payment periods for the same or different care, bonding, or military assist claim within the past 12 months.
Adjustment: Use if a previous report was submitted, and this is a correction or change to that report.
Person completing Section B

Enter the printed name of the person completing Section B.
Enter the phone number of the person completing Section B.
For Section B, enter the current date.
Before you go
Items 1-14: Information regarding the care/bonding/military assist provider and his/her family member.
Retain a copy of completed Section A.
Common questions about Form DE 2523F
Is there a deadline?
Complete items 1-17 in Section A and return within 15 days after receipt of a first claim for VPFL benefits (California Code of Regulations, title 22, section 3267-1). On retained copy of completed Section A, complete Items 18-28 and return within 35 days after final payment for each period of Voluntary Plan Family Leave (California Code of Regulations, title 22, section 3267-1).
Where do I file it?
Submit the completed form to EDD-Paid Family Leave (PFL), PO Box 997017, Sacramento, CA 95899-7017.
Sources
[1] Form DE 2523F (12-20), Report of Voluntary Plan Family Leave (VPFL) Claim, California Employment Development Department (EDD) (the Official source link on this page).