


Form SSA-1021 at a glance
What it is: SSA-1021 is the Appeal of Determination for Extra Help with Medicare Prescription Drug Plan Costs.
Who signs: If you cannot sign, a representative may sign for you.
A filled-in Form SSA-1021 example: an applicant asks for a telephone hearing

How to fill out Form SSA-1021, box by box
Applicant and spouse
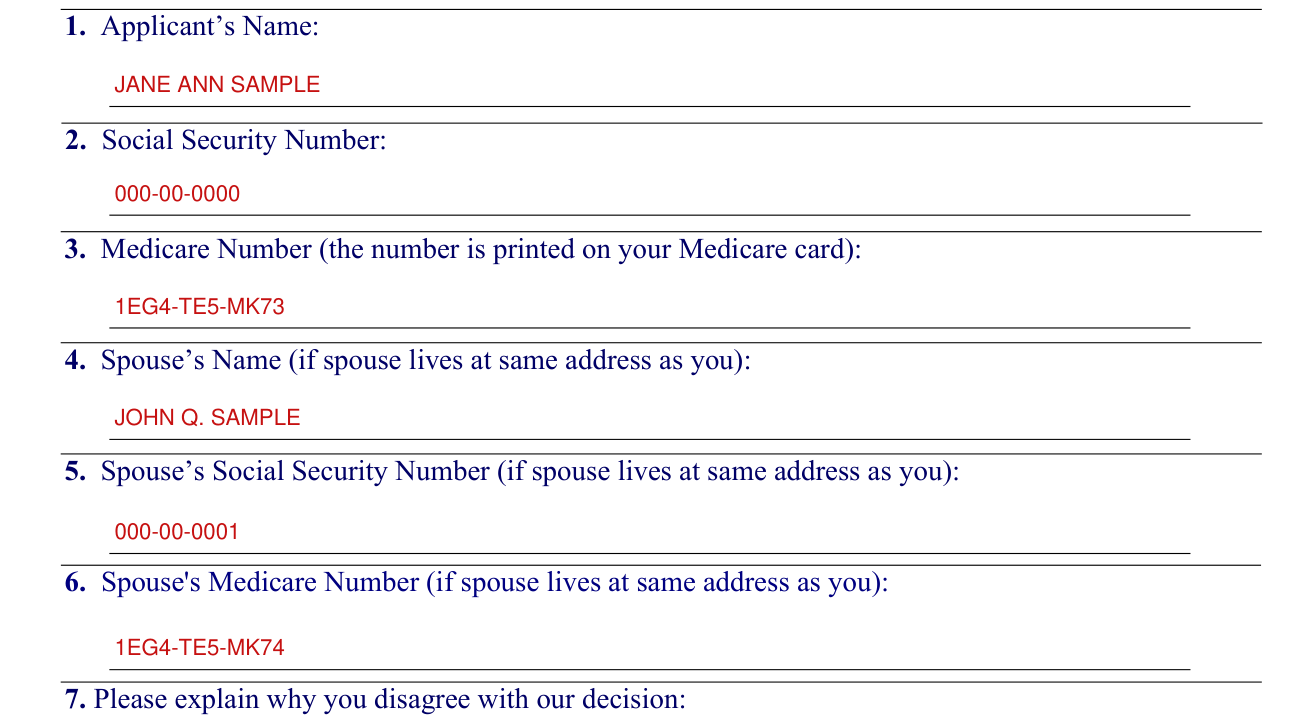
In boxes 1, 2 and 3, enter the Applicant's Name, Social Security Number and Medicare Number (the number is printed on your Medicare card).
In boxes 4, 5 and 6, enter the Spouse's Name, Spouse's Social Security Number and Spouse's Medicare Number (if spouse lives at same address as you).
Why you disagree and additional information
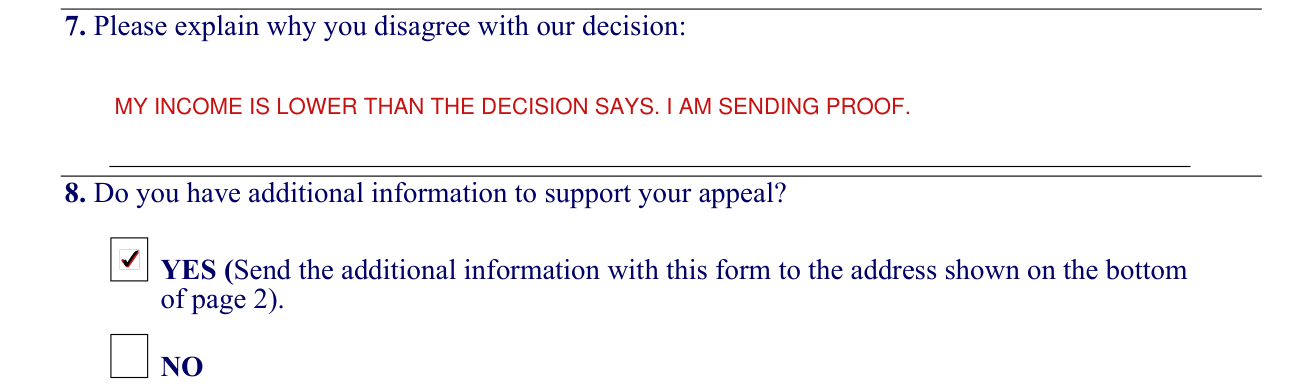
In box 7, explain why you disagree with the decision.
Box 8: Do you have additional information to support your appeal? If YES, send the additional information with this form to the address shown on the bottom of page 2.
Do you want a hearing

Box 9: Do you want a hearing? If you have a hearing, it will be by telephone. YES (You will receive a notice with the date and time of the hearing. Please complete questions 10 through 13). NO (You will receive a decision based on the information available and any additional information you provide).
Hearing sooner, interpreter and other people

To give you time to prepare for the hearing, the Social Security Administration allows at least 20 days between the date of your request and the date it schedules the hearing.
Box 10: Do you want a hearing sooner if scheduling permits?
Box 11: Do you need an interpreter? If YES, specify language.
Box 12: Are you hearing impaired?
Box 13: Will you have other people at the hearing? If YES, will you and the other people need to talk to the Social Security Administration from more than one telephone number? If YES, the Social Security Administration calls this a conference call. When it sends you the notice with your hearing date and time, it will also give you a telephone number and additional instructions for this conference call.
Section A: your signature and address

Please complete Section A. If someone assisted you, complete Section B as well.
In Section A, sign on Your Signature and enter your Phone Number.
In Section A, enter Your Home Street Address, Apt. #, City, State and ZIP Code.
Enter Your Mailing Street Address (if different from home address), Apt. #, City, State and ZIP Code. If you recently changed your address, put an X here.
If you would prefer that the Social Security Administration contact someone else if it has additional questions, please provide the person's name and a daytime phone number: Print First Name, Print Last Name and Phone Number.
Section B: someone who assisted you
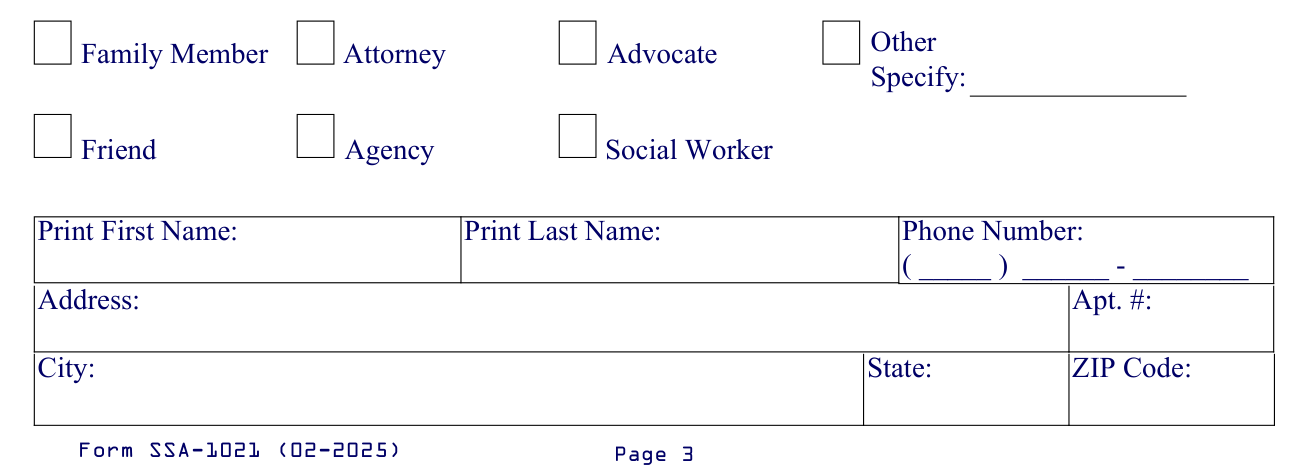
In Section B, if someone assisted you, place an X in the box that describes that person: Family Member, Attorney, Advocate, Friend, Agency, Social Worker or Other (Specify).
In Section B, enter Print First Name, Print Last Name, Phone Number, Address, Apt. #, City, State and ZIP Code.
More rules for Form SSA-1021
Section 1860 D-14 of the Social Security Act, as amended, allows the Social Security Administration to collect this information, which it will use to review and re-determine if you are eligible for a Medicare Part D subsidy.
Common questions about Form SSA-1021
Where do I file it?
Please return your completed appeal form, including the signature page, and any additional information to: Social Security Administration Wilkes-Barre Direct Operations Center P.O. Box 1030 Wilkes-Barre, PA 18767-1030
Is there a penalty?
Making a false statement is a crime punishable under Federal law.
What am I certifying when I sign?
You declare under penalty of perjury that you have examined all the information on this form, and on any accompanying statements or forms, and it is true to the best of your knowledge.
Sources
[1] Form SSA-1021 (02-2025), Appeal of Determination for Extra Help with Medicare Prescription Drug Plan Costs, Social Security Administration (the Official source link on this page).