


Form SSA-831 C3/U3 at a glance
What it is: Form SSA-831 C3/U3, Disability Determination and Transmittal, is used to determine eligibility for benefits and for program evaluation and management.
A filled-in Form SSA-831 C3/U3 example: a claimant found disabled
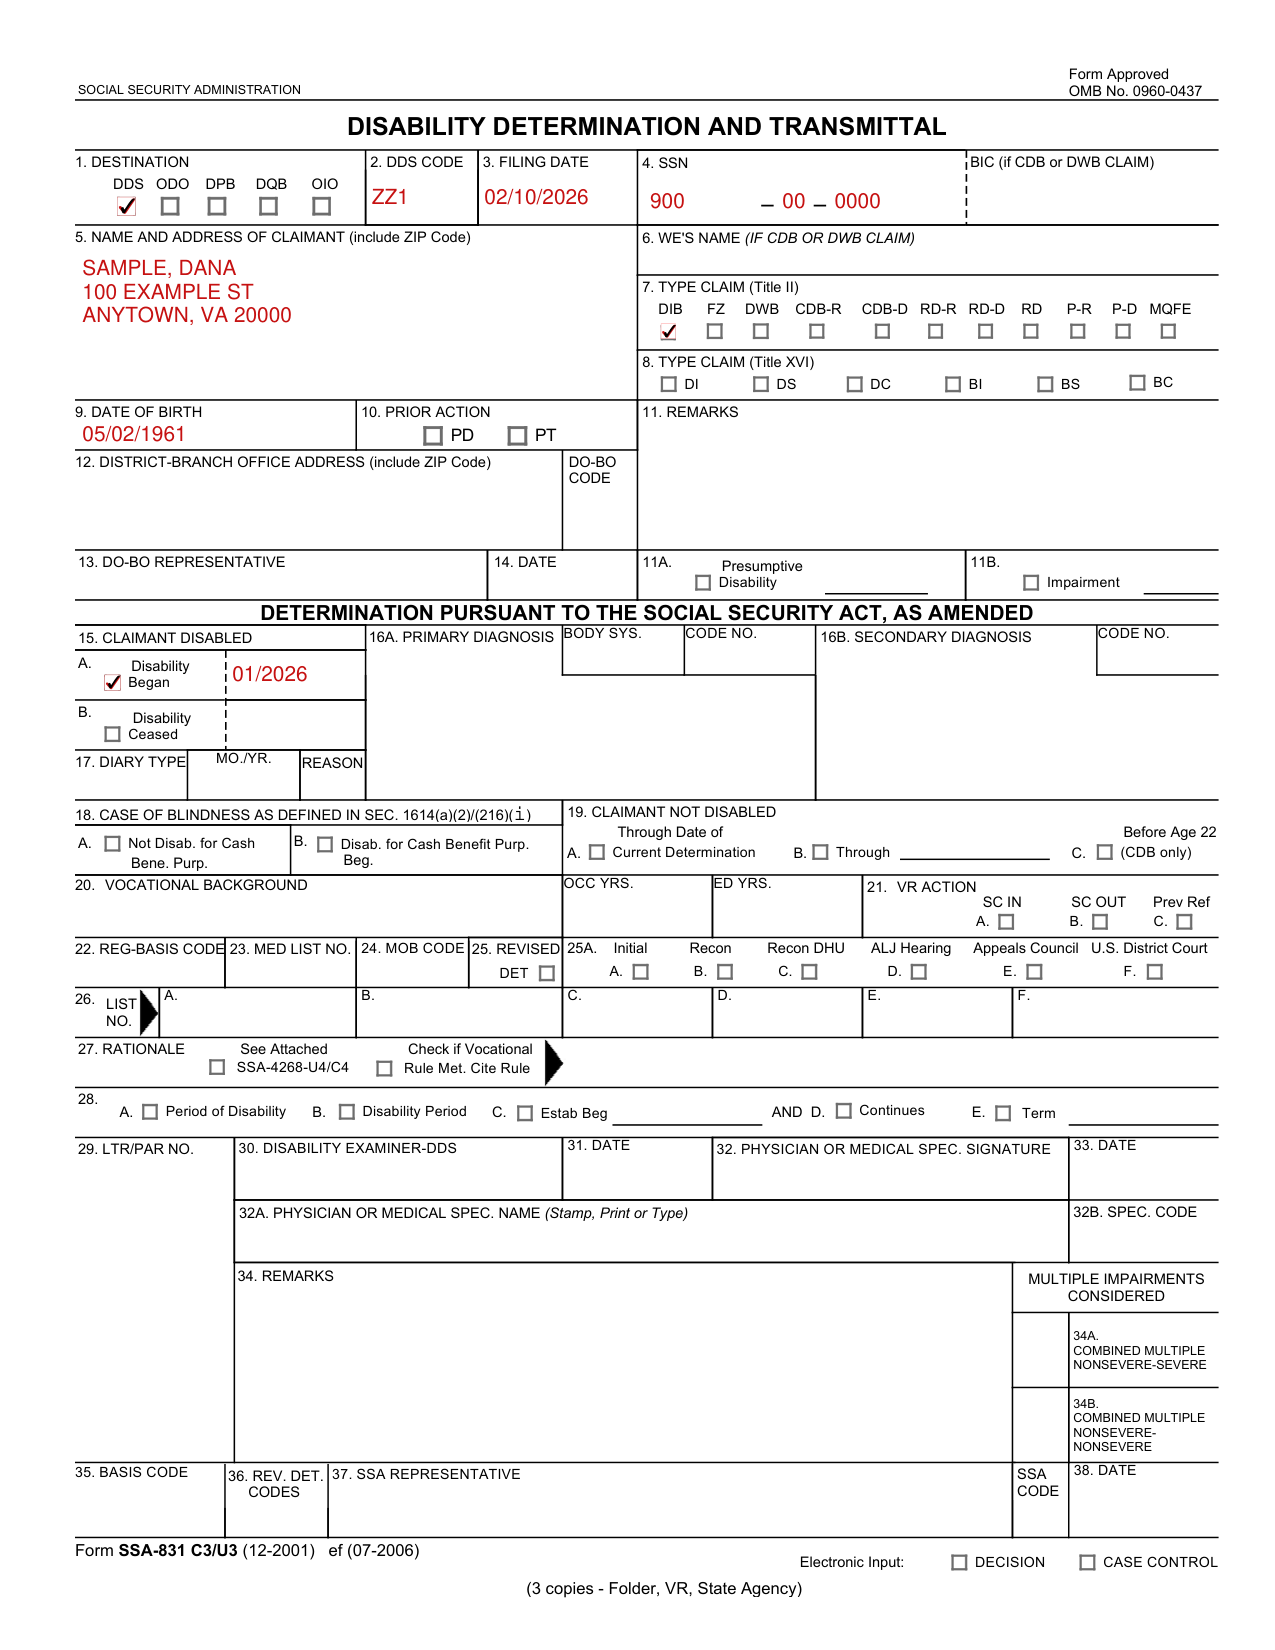
How to fill out Form SSA-831 C3/U3, box by box
1. DESTINATION, codes, date and SSN

Under 1. DESTINATION, mark DDS, ODO, DPB, DQB or OIO.
Enter the DDS CODE in Box 2 and the FILING DATE in Box 3.
Enter the SSN in Box 4, and the BIC if it is a CDB or DWB claim.
5. NAME AND ADDRESS OF CLAIMANT and TYPE CLAIM

Enter the NAME AND ADDRESS OF CLAIMANT in Box 5, including the ZIP Code.
Under 7. TYPE CLAIM (Title II), mark DIB, FZ, DWB, CDB-R, CDB-D, RD-R, RD-D, RD, P-R, P-D or MQFE.
Box 8 is the TYPE CLAIM (Title XVI): mark DI, DS, DC, BI, BS or BC.
9. DATE OF BIRTH to 14. DATE
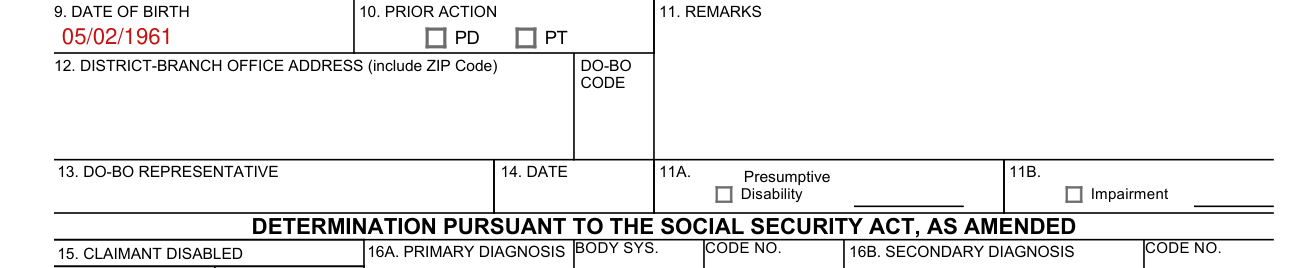
Enter the DATE OF BIRTH in Box 9.
Under 10. PRIOR ACTION, mark PD or PT.
Enter the REMARKS in Box 11.
Enter the DISTRICT-BRANCH OFFICE ADDRESS, including the ZIP Code, in Box 12, and the DO-BO CODE.
Enter the DO-BO REPRESENTATIVE in Box 13 and the DATE in Box 14.
15. CLAIMANT DISABLED to 17. DIARY TYPE
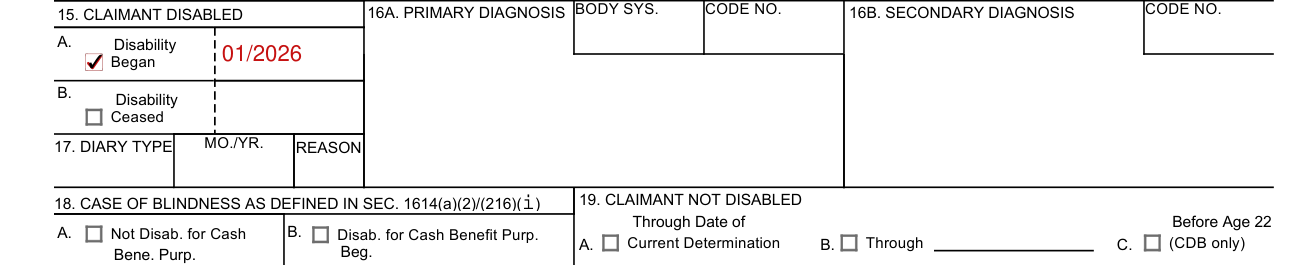
Under 15. CLAIMANT DISABLED, mark Disability Began or Disability Ceased.
Enter the PRIMARY DIAGNOSIS in Box 16A and the SECONDARY DIAGNOSIS in Box 16B.
Enter the DIARY TYPE, MO./YR. and REASON in Box 17.
18. CASE OF BLINDNESS to 24. MOB CODE
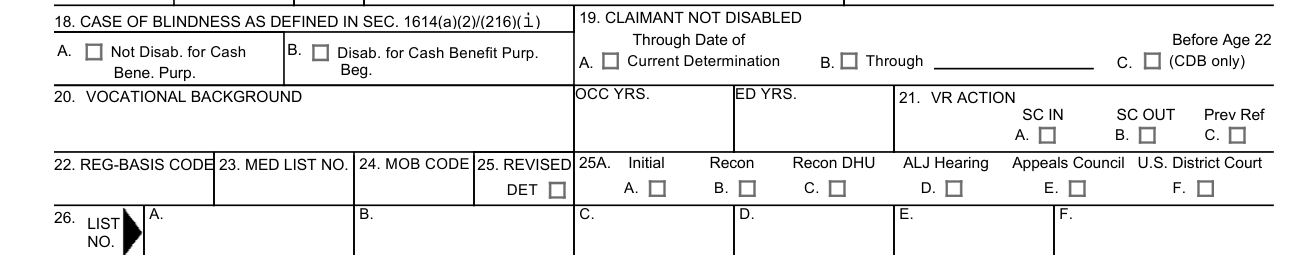
Box 18 is the CASE OF BLINDNESS AS DEFINED IN SEC. 1614(a)(2)/(216)(i).
Box 19 is CLAIMANT NOT DISABLED: A. Through Date of Current Determination, B. Through, or C. Before Age 22 (CDB only).
Enter the VOCATIONAL BACKGROUND in Box 20, with the OCC YRS. and ED YRS.
Box 21 is the VR ACTION: SC IN, SC OUT or Prev Ref.
Enter the REG-BASIS CODE in Box 22, the MED LIST NO. in Box 23 and the MOB CODE in Box 24.
26. LIST NO. and 27. RATIONALE

Enter the LIST NO. in Box 26.
Box 27 is the RATIONALE: See Attached, or check if Vocational Rule Met and cite the rule.
30. DISABILITY EXAMINER-DDS to 38. DATE
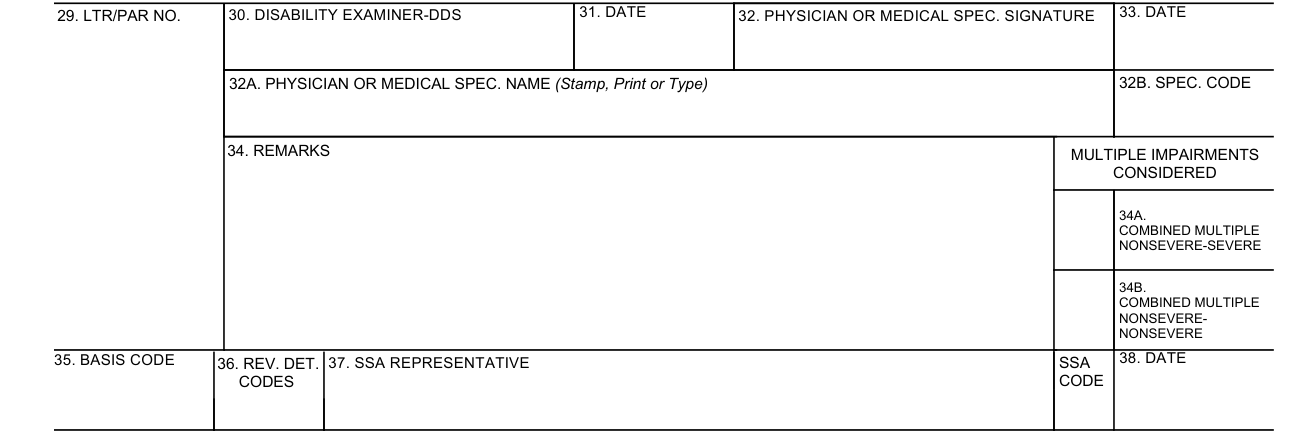
Box 30 is the DISABILITY EXAMINER-DDS, with the DATE in Box 31.
Box 32 is the PHYSICIAN OR MEDICAL SPEC. SIGNATURE, with the DATE in Box 33.
Enter the PHYSICIAN OR MEDICAL SPEC. NAME (Stamp, Print or Type) in Box 32A and the SPEC. CODE in Box 32B.
Enter the REMARKS in Box 34 and the MULTIPLE IMPAIRMENTS CONSIDERED.
Box 35 is the BASIS CODE, Box 36 the REV. DET. CODES, Box 37 the SSA REPRESENTATIVE and Box 38 the DATE.
More rules for Form SSA-831 C3/U3
The form has 3 copies: Folder, VR, State Agency.
It will take about 15 minutes to read the instructions, gather the facts, and answer the questions.
Sources
[1] Form SSA-831 C3/U3 (12-2001), Disability Determination and Transmittal, Social Security Administration (the Official source link on this page).