

Estimated Functional Capacity Evaluation at a glance
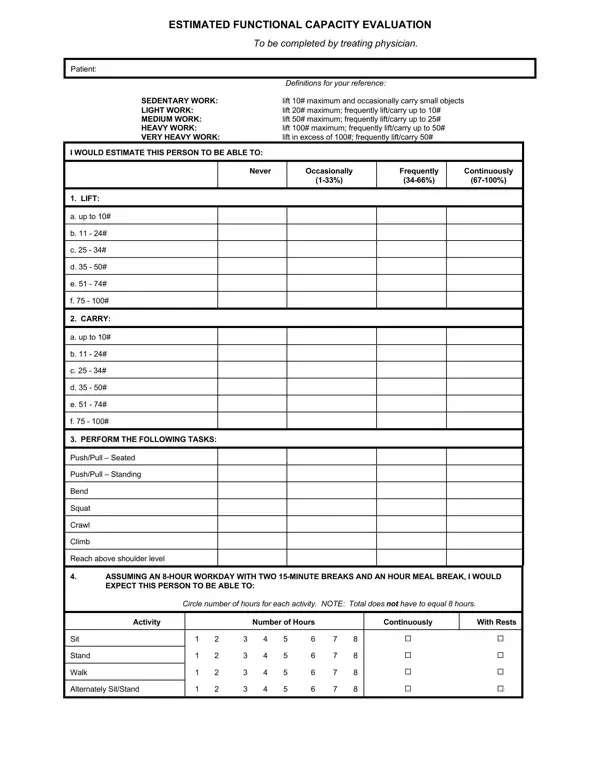
What it is: This is the estimated functional capacity evaluation.
Who signs: It is to be completed by the treating physician.
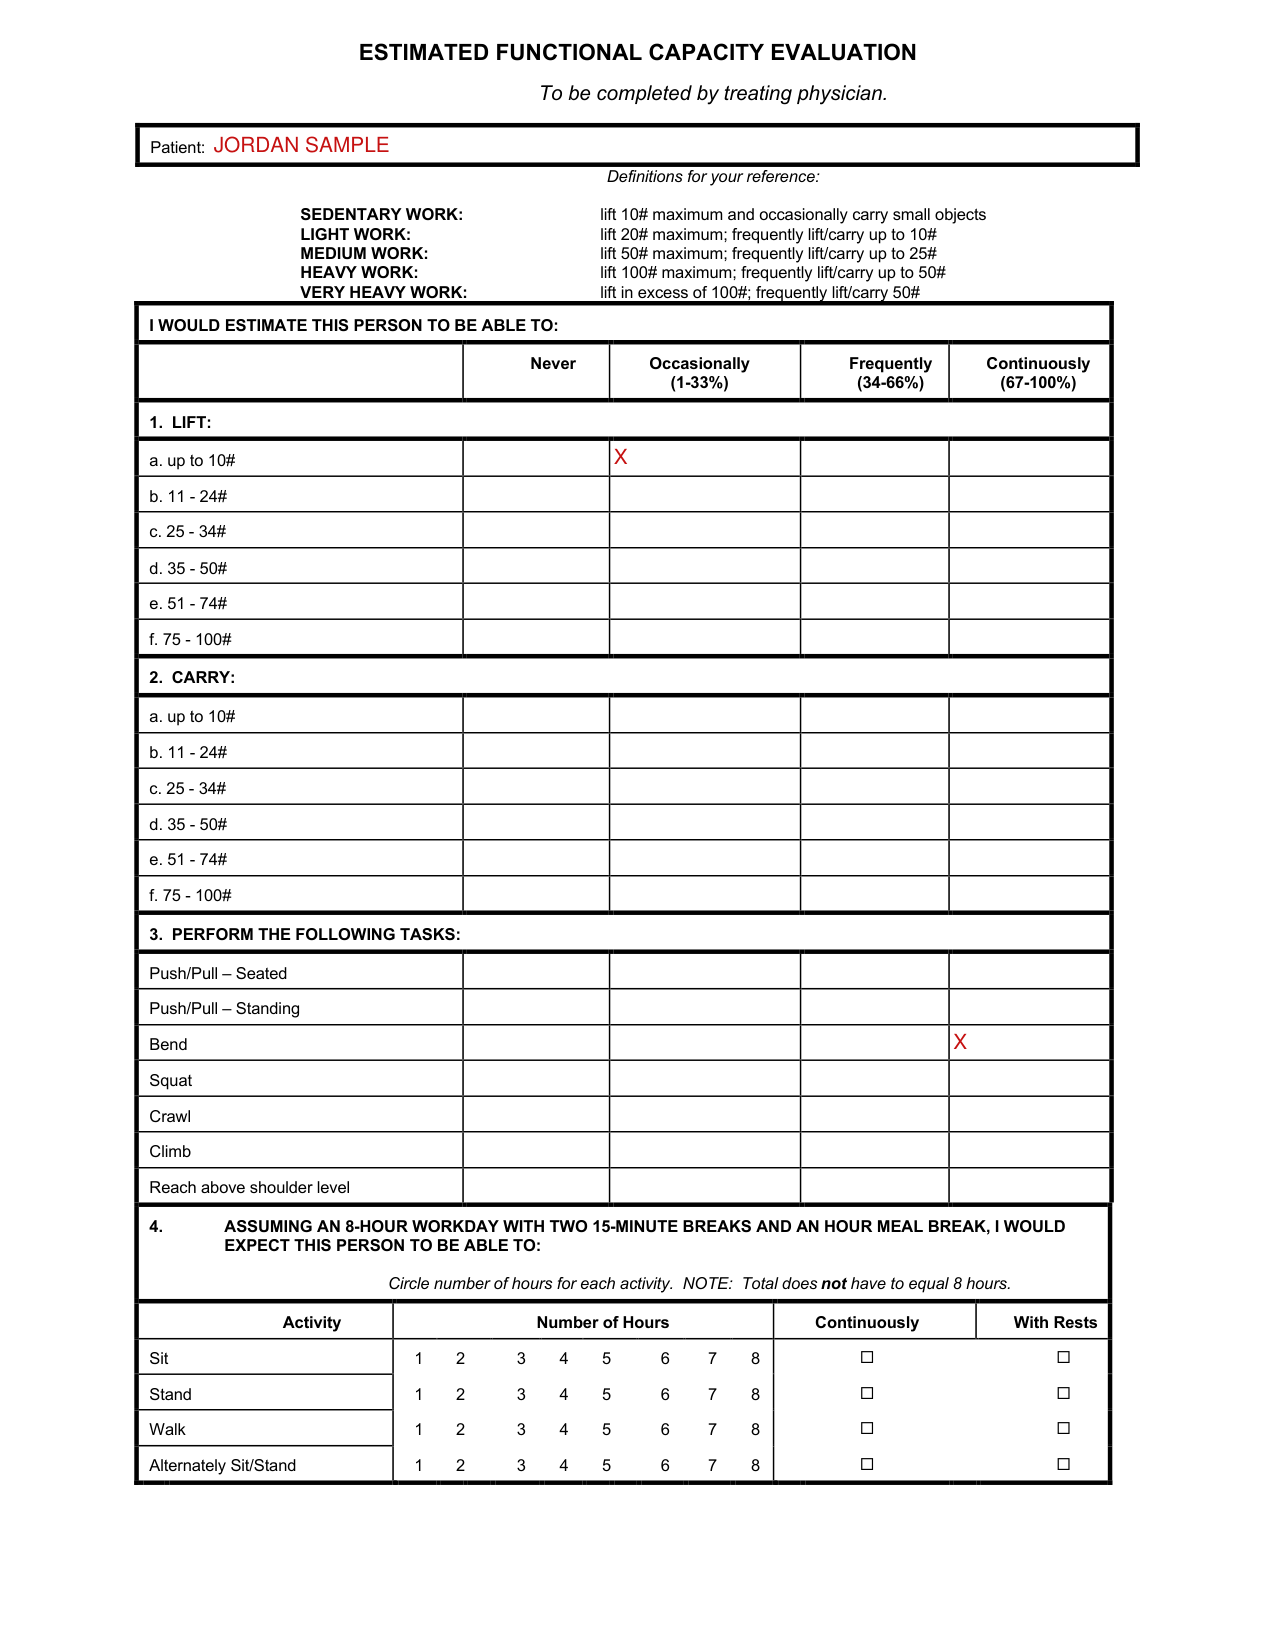
A filled-in Estimated Functional Capacity Evaluation example: a physician estimates one patient
How to fill out Estimated Functional Capacity Evaluation, box by box
Patient, lift, carry, tasks and workday hours
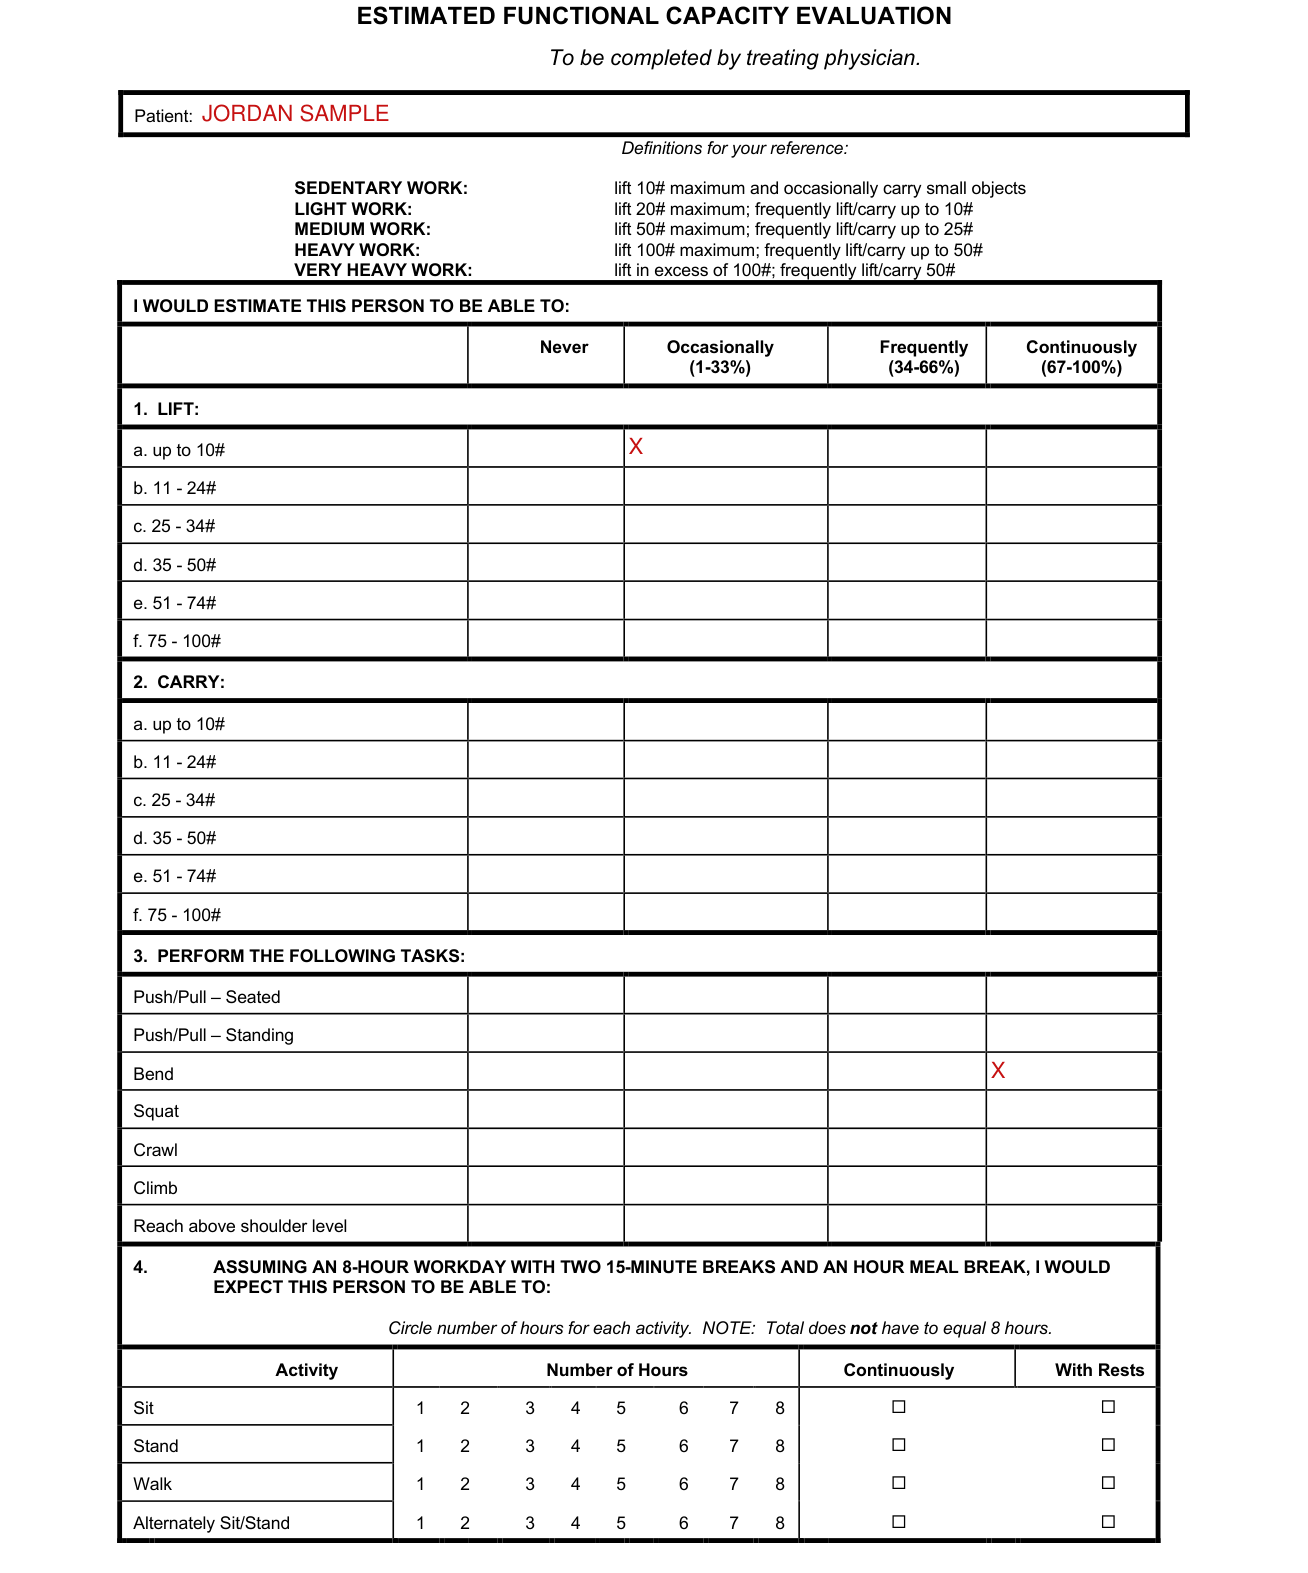
Fill in Patient.
For 1. LIFT, estimate this person to be able to lift up to 10#, 11 - 24#, 25 - 34#, 35 - 50#, 51 - 74# and 75 - 100#, as Never, Occasionally (1-33%), Frequently (34-66%) or Continuously (67-100%).
For 2. CARRY, estimate this person to be able to carry up to 10#, 11 - 24#, 25 - 34#, 35 - 50#, 51 - 74# and 75 - 100#, as Never, Occasionally (1-33%), Frequently (34-66%) or Continuously (67-100%).
For 3., mark Never, Occasionally (1-33%), Frequently (34-66%) or Continuously (67-100%) for each of Push/Pull - Seated, Push/Pull - Standing, Bend, Squat, Crawl, Climb and "Reach above shoulder level".
For 4., assuming an 8-hour workday with two 15-minute breaks and an hour meal break, circle the number of hours, 1 to 8, for each activity (Sit, Stand, Walk and Alternately Sit/Stand), Continuously or With Rests. Total does not have to equal 8 hours.
Hands, feet, restrictions, job, comments, physician and signature
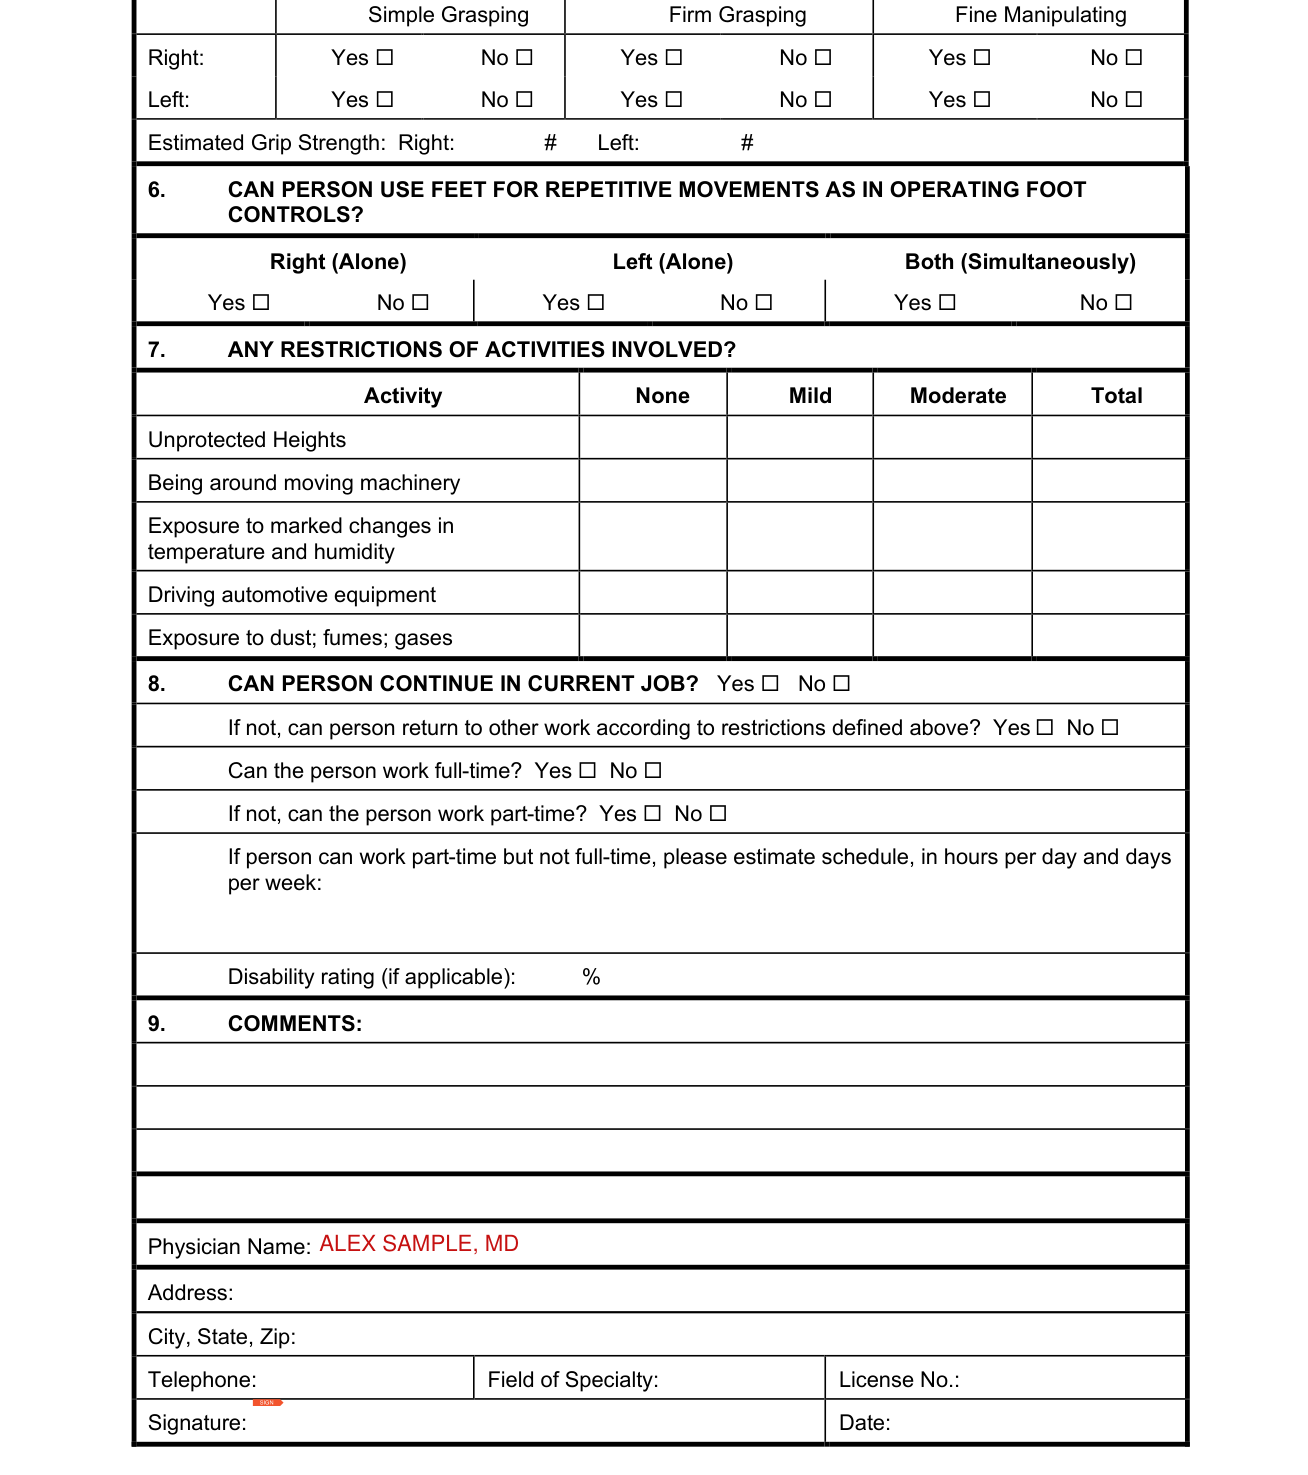
For 5. Can person use hands for repetitive actions such as: Simple Grasping, Firm Grasping and Fine Manipulating, mark Yes or No for Right and for Left, and enter the Estimated Grip Strength for Right and Left.
For 6. Can person use feet for repetitive movements as in operating foot controls?, mark Yes or No for Right (Alone), Left (Alone) and Both (Simultaneously).
For 7. Any restrictions of activities involved?, mark None, Mild, Moderate or Total for Unprotected Heights, Being around moving machinery, Exposure to marked changes in temperature and humidity, Driving automotive equipment and Exposure to dust; fumes; gases.
For 8. Can person continue in current job?, mark Yes or No. If not, mark Yes or No for can person return to other work according to restrictions defined in 7. Any restrictions of activities involved?
Mark Yes or No for Can the person work full-time. If not, mark Yes or No for can the person work part-time. If the person can work part-time but not full-time, estimate the schedule, in hours per day and days per week. Enter the Disability rating (if applicable) in %.
Write the 9. COMMENTS.
Fill in Physician Name, Address, City, State, Zip, Telephone, Field of Specialty and License No.
SIGN: enter the Signature and the Date.
More rules for Estimated Functional Capacity Evaluation
SEDENTARY WORK is lift 10# maximum and occasionally carry small objects; LIGHT WORK is lift 20# maximum; frequently lift/carry up to 10#; MEDIUM WORK is lift 50# maximum; frequently lift/carry up to 25#; HEAVY WORK is lift 100# maximum; frequently lift/carry up to 50#; VERY HEAVY WORK is lift in excess of 100#; frequently lift/carry 50#.
Sources
[1] Estimated Functional Capacity Evaluation (the served file; no issuer file found) (the Official source link on this page).