Generic Request Form PDF Details

In the realm of healthcare and prescription management, a critical tool that facilitates the intersection of patient care and regulatory compliance is the Generic Request Form. It's explicitly designed for use within the Department of Defense (DoD) TRICARE pharmacy program, with Express Scripts serving as the contractor. This form is a cornerstone in prescribing practices, requiring completion and signature by the prescriber when opting for a brand name drug over its generic counterpart. It navigates through a process that starts with basic patient and physician information, emphasizing the importance of A-rated generic drugs by the FDA for bioequivalence and therapeutic equivalence, underscoring the policy of mandatory substitution except under clinically justified circumstances. The form intricately lays out a step-by-step approach, addressing whether a patient has previously tried a generic product, their reaction to it, and detailed patient-specific clinical justifications for requiring a brand name drug. This mechanism not only upholds the standards set by the 32 CFR 199.21 (j)(2) regarding generic drug use but also prioritizes patient safety and efficacy. It ensures that the prescribed medication, brand name or generic, aligns with the patient’s health needs while adhering to regulatory mandates. The method of submission is made accessible via fax, mail, or email, illustrating the program's flexibility and adaptability to modern communication methodologies. In essence, the Generic Request Form bridges the gap between healthcare regulations, patient care, and the prescriber’s clinical judgment, marking a pivotal step in the prescription process for those under the DoD TRICARE pharmacy program.

QuestionAnswer
Form NameGeneric Request Form
Form Length1 pages
Fillable?No
Fillable fields0
Avg. time to fill out15 sec
Other namesgeneric request print, generic request template, generic request printable, generic request form template

How to Fill Out Brand over Generic Prior Authorization Request Form

Brand over Generic Prior Authorization Request Form at a glance

What it is: The Brand over Generic Prior Authorization Request Form is to be used only for prescriptions which are to be filled through the Department of Defense (DoD) TRICARE pharmacy program (TPHARM).

Who signs: The Brand over Generic Prior Authorization Request Form is to be completed and signed by the prescriber.

Where and when to file: The completed form may be faxed to: 1-866-684-4477.

A filled-in Brand over Generic Prior Authorization Request Form example: a prescriber asks for a brand name drug
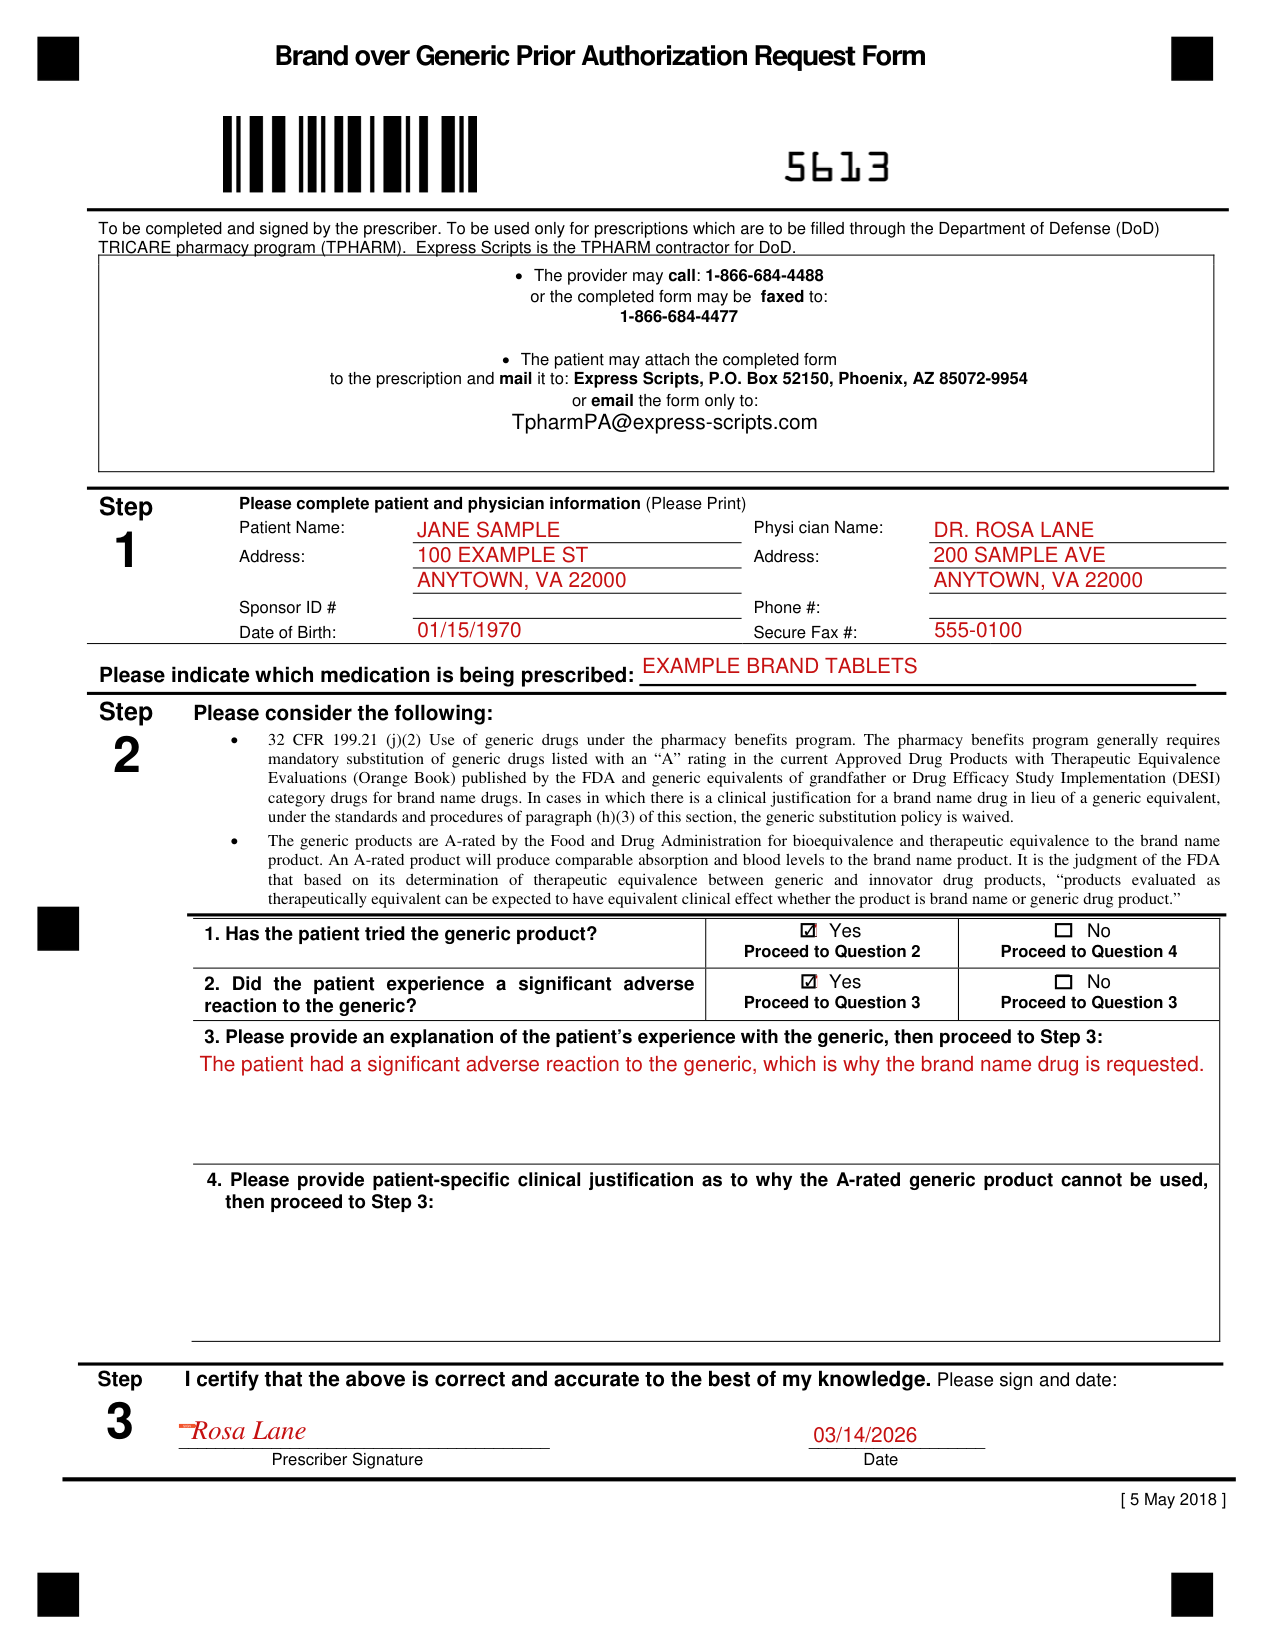
Brand over Generic Prior Authorization Request Form example filled out, example: a prescriber asks for a brand name drug
Dr. Rosa Lane fills out this request form for a patient. The patient tried the generic and had a significant adverse reaction, so patient-specific clinical justification stays empty. The picture shows page 1 only, and every value in it is made up.

How to fill out Brand over Generic Prior Authorization Request Form, box by box

Patient and physician information

Brand over Generic Prior Authorization Request Form example filled out, patient and physician information

In Step 1, complete the patient and physician information (Please Print): Patient Name, Physician Name, Address, Sponsor ID #, Phone #, Date of Birth and Secure Fax #.

Indicate which medication is being prescribed.

Has the patient tried the generic product and the adverse reaction to the generic

Brand over Generic Prior Authorization Request Form example filled out, has the patient tried the generic product and the adverse reaction to the generic

1. Has the patient tried the generic product? Yes: Proceed to Question 2. No: Proceed to Question 4.

2. Did the patient experience a significant adverse reaction to the generic? Yes: Proceed to Question 3. No: Proceed to Question 3.

An explanation of the patient's experience with the generic

Brand over Generic Prior Authorization Request Form example filled out, an explanation of the patient's experience with the generic

3. Please provide an explanation of the patient's experience with the generic, then proceed to Step 3.

Patient-specific clinical justification why the A-rated generic product cannot be used

Brand over Generic Prior Authorization Request Form example filled out, patient-specific clinical justification why the A-rated generic product cannot be used

4. Please provide patient-specific clinical justification as to why the A-rated generic product cannot be used, then proceed to Step 3.

Certify, sign and date

Brand over Generic Prior Authorization Request Form example filled out, certify, sign and date

"I certify that the above is correct and accurate to the best of my knowledge." Please sign and date: Prescriber Signature, Date.

More rules for Brand over Generic Prior Authorization Request Form

Express Scripts is the TPHARM contractor for DoD.

In cases in which there is a clinical justification for a brand name drug in lieu of a generic equivalent, under the standards and procedures of paragraph (h)(3) of this section, the generic substitution policy is waived.

The generic products are A-rated by the Food and Drug Administration for bioequivalence and therapeutic equivalence to the brand name product.

Common questions about Brand over Generic Prior Authorization Request Form

Where do I file it?

The patient may attach the completed form to the prescription and mail it to: Express Scripts, P.O. Box 52150, Phoenix, AZ 85072-9954 or email the form only to: TpharmPA@express-scripts.com. The provider may call: 1-866-684-4488.

Sources

[1] Brand over Generic Prior Authorization Request Form, TRICARE pharmacy program (TPHARM) (the Official source link on this page).

Please rate Generic Request Form

1 Votes
If you believe this page is infringing on your copyright, please familiarize yourself with and follow our DMCA notice and takedown process - click here to proceed .