

Form PA 564 at a glance
What it is: The PA 564 is the Semiannual Reporting Form of the Commonwealth of Pennsylvania Department of Human Services, needed to determine continued eligibility for cash, the Supplemental Nutrition Assistance Program (SNAP), Extended Medical Coverage and/or Medicaid.
Who signs: Sign the certification section. An unsigned form is considered incomplete.
Your household circumstances require you to report semiannually (every 6 months).
When answering the questions, you must give information for all persons included in your cash, SNAP and/or Medicaid benefits. This includes stepparents and information for sponsors of aliens, even if the sponsor does not live in your home.
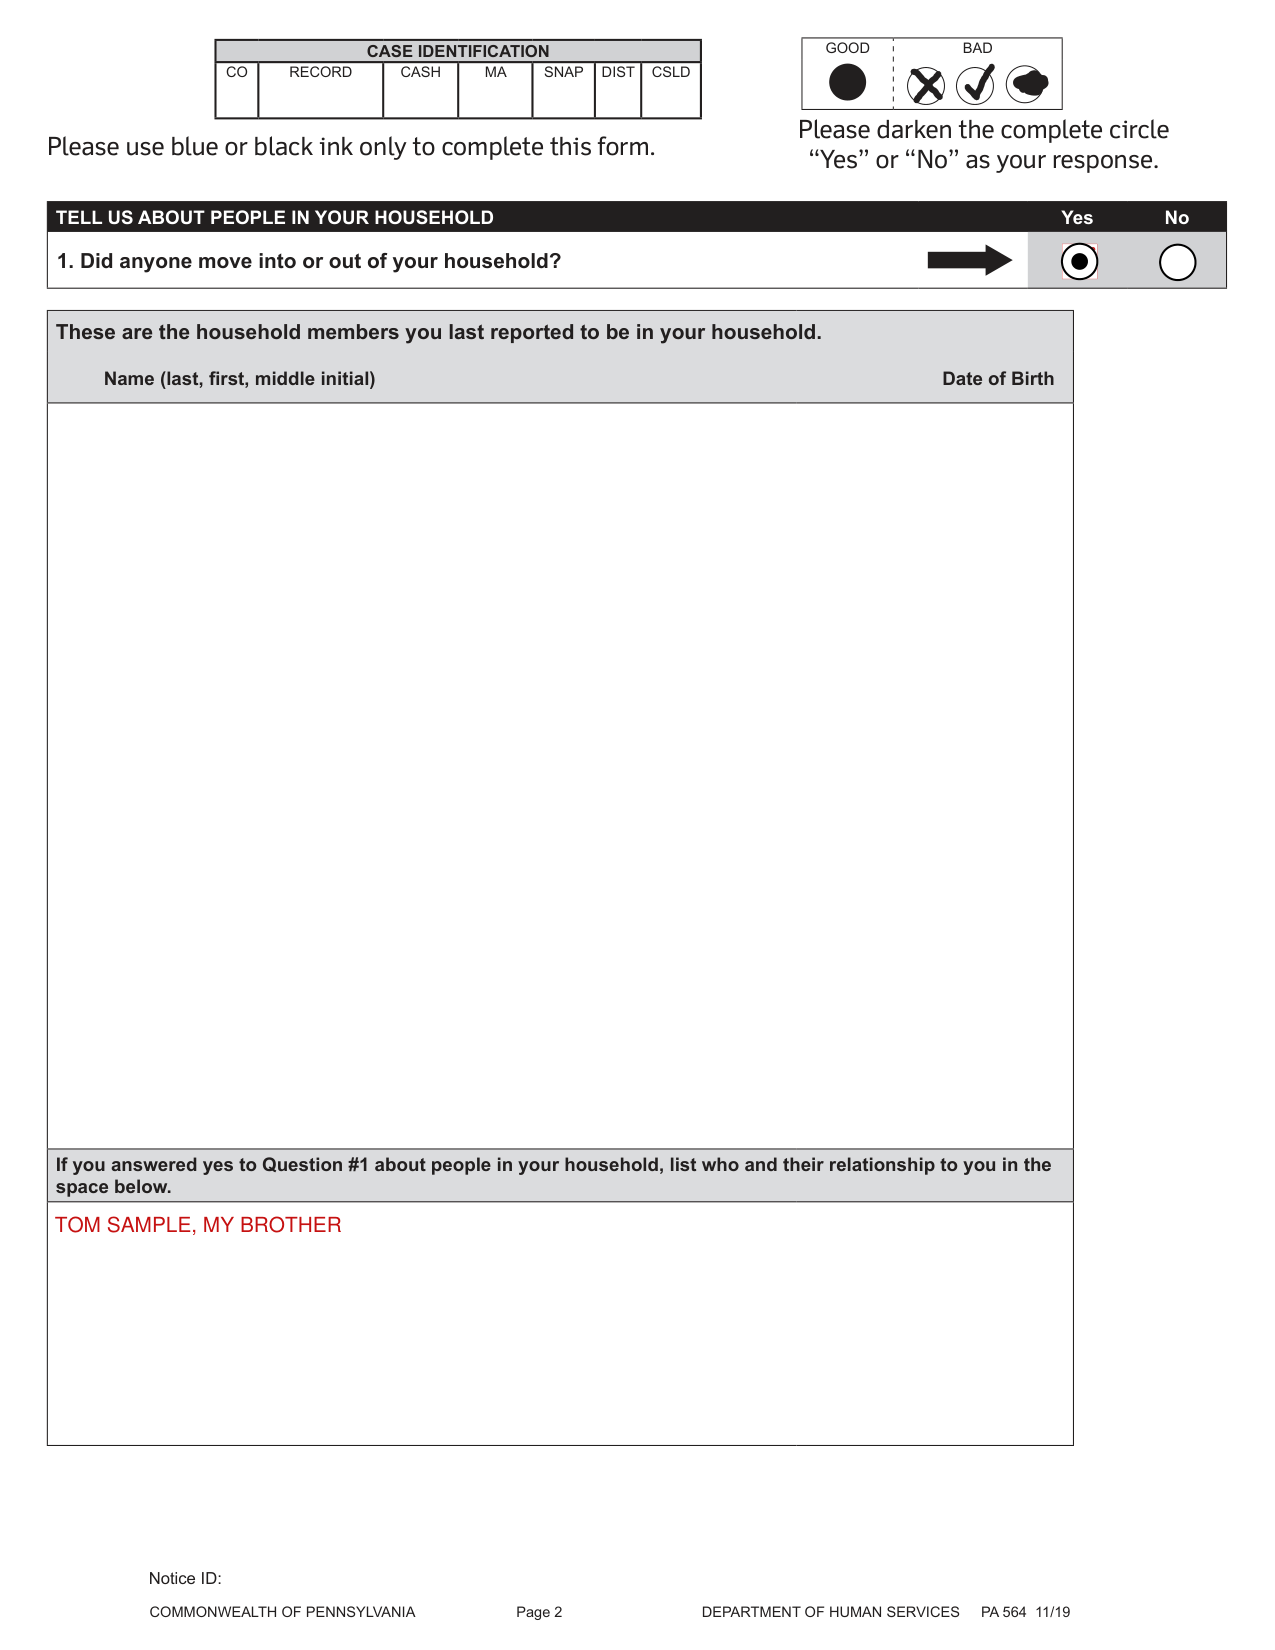
A filled-in Form PA 564 example: a household member moves in
How to fill out Form PA 564, box by box
Question 1: people in your household
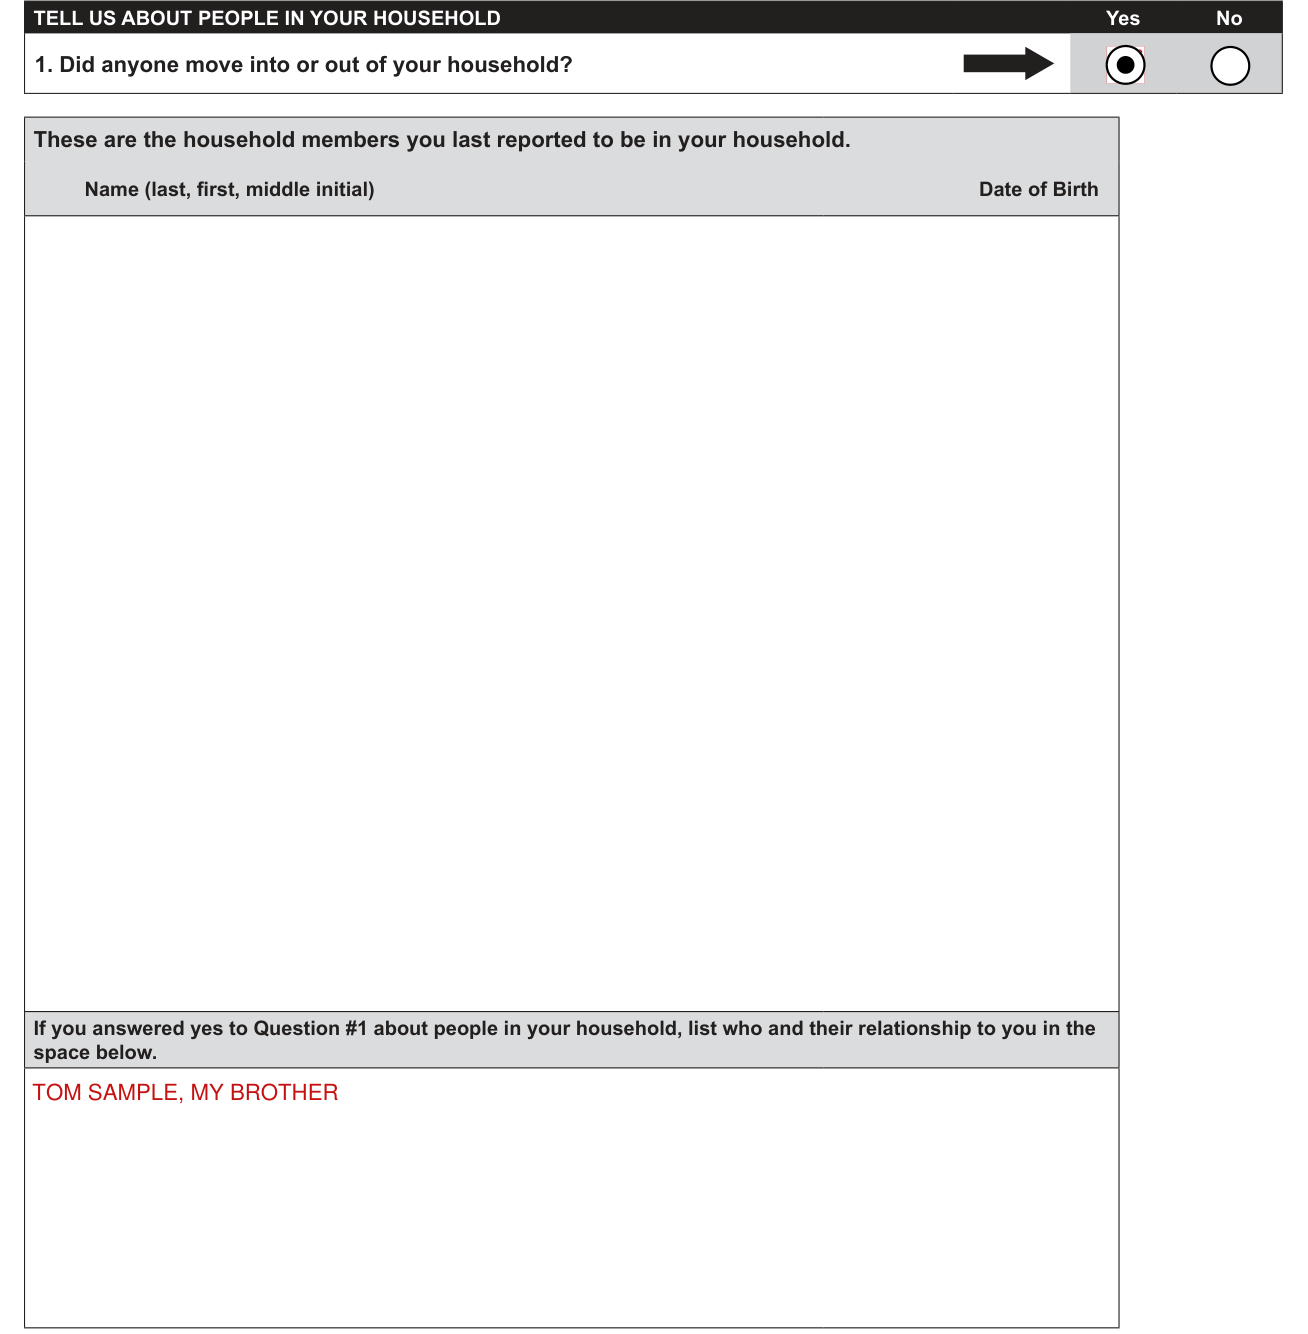
1. Did anyone move into or out of your household? "If you answered yes to Question #1 about people in your household, list who and their relationship to you in the space below."
More rules for Form PA 564
You must give information for the reporting month shown on page 1 of the form.
Please return all pages of this form in the enclosed envelope.
Use blue or black ink only to complete this form, and completely fill in the correct circle with your response as demonstrated on each page of this form.
Please darken the complete circle "Yes" or "No" as your response.
If you need additional space for any of the questions, use a separate piece of paper and attach it to this form. A separate sheet of paper must be sent in with the form.
If you need help or if you have questions about the proof needed to verify changes, call your caseworker or the Customer Service Center.
2. Did any household member start a new job, change a job, or stop working? If you answered yes to Question #2 about work income, list any changes, such as job start date, end date, date of first pay, how often paid. 3. Provide proof (pay stubs, employer statements, etc.) of all work income any household member received in the month of:
4. Did any household member lose or start receiving income or have a change in amount? These are the household members you last reported as having income from a source other than work or public assistance. (Examples: child support, Social Security, pension income, etc.) If you answered yes to Question #4 about income from other sources, list any changes. Provide proof (award letter, support court orders, etc.).
5. Is the address on this form your current address? If you answered no to Question #5 about your current address, what is your new address? Provide proof (Examples: lease, landlord statement, deed, etc.).
Answer only if you receive SNAP benefits and have moved. Answering these questions may help you receive more SNAP benefits. Do you pay for your own heating and/or air conditioning? What are your shelter (rent/mortgage) and utility costs?
6. Did any household member have a change in the amount he/she is requested to pay? This is the last reported amount of child support paid for children outside the household. If you answered yes to Question #6 about child support payments, list any changes. Provide copy of support order or letter and proof of payment.
7. Are there any changes to the information you last reported about child care or for care of a sick or disabled person? You do not have to answer this question or provide proof. Answering this question and providing proof may help you to remain eligible or receive more benefits. If you answered yes to Question #7 about child and dependent care, list any changes. Provide copy of bill or statement from caregiver.
8. Have there been any changes to the resource information? Does any household member have resources not listed? These are the household members you last reported as having resources including vehicles (Examples: bank account, property, etc.). If you answered yes to either question about resource, list any changes. Provide proof (copy of bank statement, vehicle registration, etc.). If this form is to determine eligibility for medical benefits only and you are pregnant OR under 21 years OR living with your dependent child who is under the age of 21, you do not have to answer this question.
YOU MAY CLAIM "GOOD CAUSE" if you have a good reason for not completing the form or for returning it late. To claim "good cause", you must state your reason(s) in the space under I AM CLAIMING "GOOD CAUSE" BECAUSE, sign your statement and return this form to the county assistance office as soon as possible, within 30 days from the due date. If you wish to claim good cause, sign and include page A.
You may also claim "good cause" orally by contacting your caseworker, but you must also return this form to the county assistance office as soon as possible, within 30 days from the due date.
If the form is late or incomplete, you may not receive your cash and/or SNAP benefits on time. If you DO NOT return the form, action may be taken to close your case.
If you disagree with the decision to reduce or stop your benefit(s), you have the right to appeal. You will be sent a notice to tell you about any proposed reduction or stoppage of your benefits.
Note: You may report changes at any time if the change would increase your benefits (such as if you lose your job or your hours of work decrease).
Please return page C if you wish to register to vote. If you are not registered to vote where you live now, would you like to apply to register to vote here today? If you do not check either box, you will be considered to have decided not to register to vote at this time.
Common questions about Form PA 564
Who signs it?
In the certification, give the Signature of Payment Name or Authorized Representative for SNAP, the Date and the Daytime Telephone Number.
Is there a deadline?
You must complete, sign and return the form to the county assistance office by the date shown on page 1 of the form.
Where do I file it?
Mail the completed form in the return envelope provided or fax the form to the county assistance office with proof of all household members' income from work and proof of any changes reported on this form.
Is there a penalty?
I understand that willful failure to give accurate information or to report changes may result in a fine or imprisonment or both.
What am I certifying when I sign?
CERTIFICATION I swear that the information given on this form is complete and correct to the best of my knowledge. I agree to report any changes in circumstances that may affect my eligibility or the amount of cash, Medicaid, and/or SNAP benefits.
Sources
[1] Form PA 564 (11/19), Semiannual Reporting Form, Pennsylvania Department of Human Services (the Official source link on this page).
