
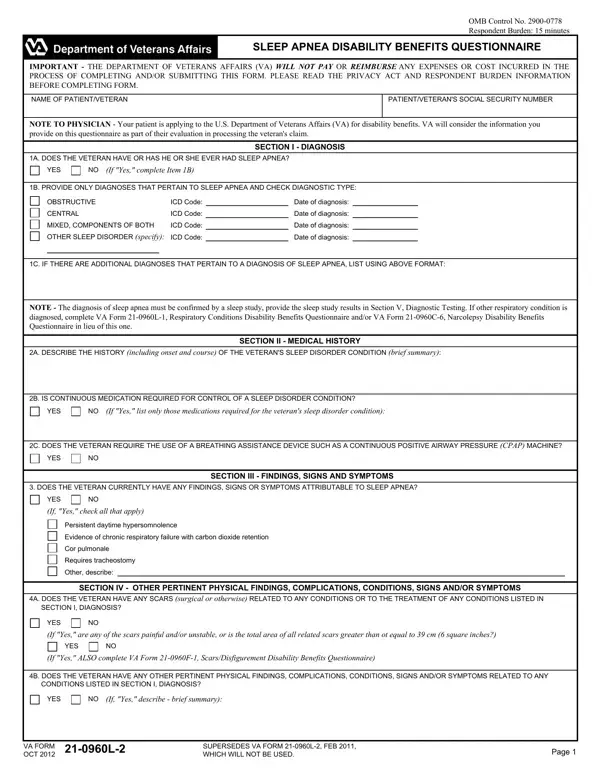
Sleep Apnea Disability Benefits Questionnaire at a glance
What it is: The Sleep Apnea Disability Benefits Questionnaire is intended to be completed by the Veteran's healthcare provider, and VA may obtain additional medical information, including an examination, if necessary.
Who signs: The Examiner signs 8A, Examiner's signature.
It is intended that this questionnaire will be completed by the Veteran's healthcare provider. The Veteran is applying to the U.S. Department of Veterans Affairs (VA) for disability benefits, and VA will consider the information you provide on this questionnaire as part of their evaluation in processing the Veteran's claim. VA may obtain additional medical information, including an examination, if necessary, to complete VA's review of the Veteran's application. VA reserves the right to confirm the authenticity of ALL completed questionnaires.
A filled-in Sleep Apnea Disability Benefits Questionnaire example: a sleep specialist completes page 2 for a Veteran

How to fill out Sleep Apnea Disability Benefits Questionnaire, box by box
Patient, Veteran and date of examination

Enter the Name of Patient/Veteran, the Patient/Veteran's Social Security Number and the Date of examination.
Request, examiner and evidence, 1A Diagnosis, 1B Diagnostic type and 1C Additional diagnoses
Under "Are you completing this Disability Benefits Questionnaire at the request of:", mark Veteran/Claimant, Third party (list the name(s) of organization(s) or individual(s)) or Other: describe.
Mark Yes or No for: Are you a VA Healthcare provider? Is the Veteran regularly seen as a patient in your clinic? Was the Veteran examined in person? If no, how was the examination conducted?
Under EVIDENCE REVIEW, mark Evidence reviewed: No records were reviewed or Records reviewed. For Records reviewed, identify the evidence reviewed (e.g. service treatment records, VA treatment records, private treatment records) and the date range.
Under Section I, Diagnosis, for 1A, Does the Veteran have or has he or she ever had sleep apnea?, mark Yes or No.
If other respiratory condition is diagnosed, complete the Respiratory and / or Narcolepsy Questionnaire(s), in lieu of this one. The diagnosis of sleep apnea must be confirmed by a sleep study; provide sleep study results in Diagnostic testing section.
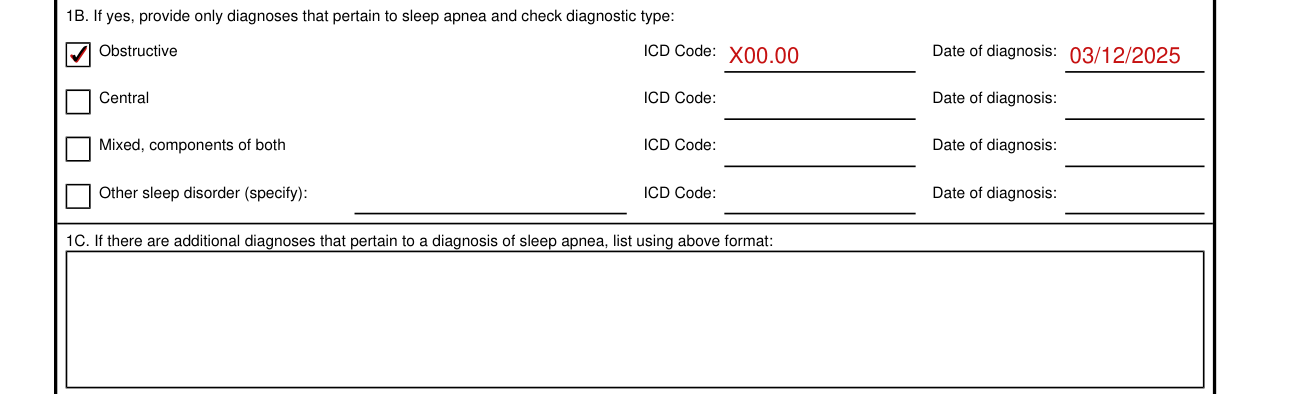
1B. If yes, provide only diagnoses that pertain to sleep apnea and check diagnostic type: Obstructive, Central, Mixed, components of both, or Other sleep disorder (specify). For each, enter the ICD Code and the Date of diagnosis.
1C. If there are additional diagnoses that pertain to a diagnosis of sleep apnea, list them in the format of 1B.
2A. History, 2B. Continuous medication and 2C. Breathing assistance device
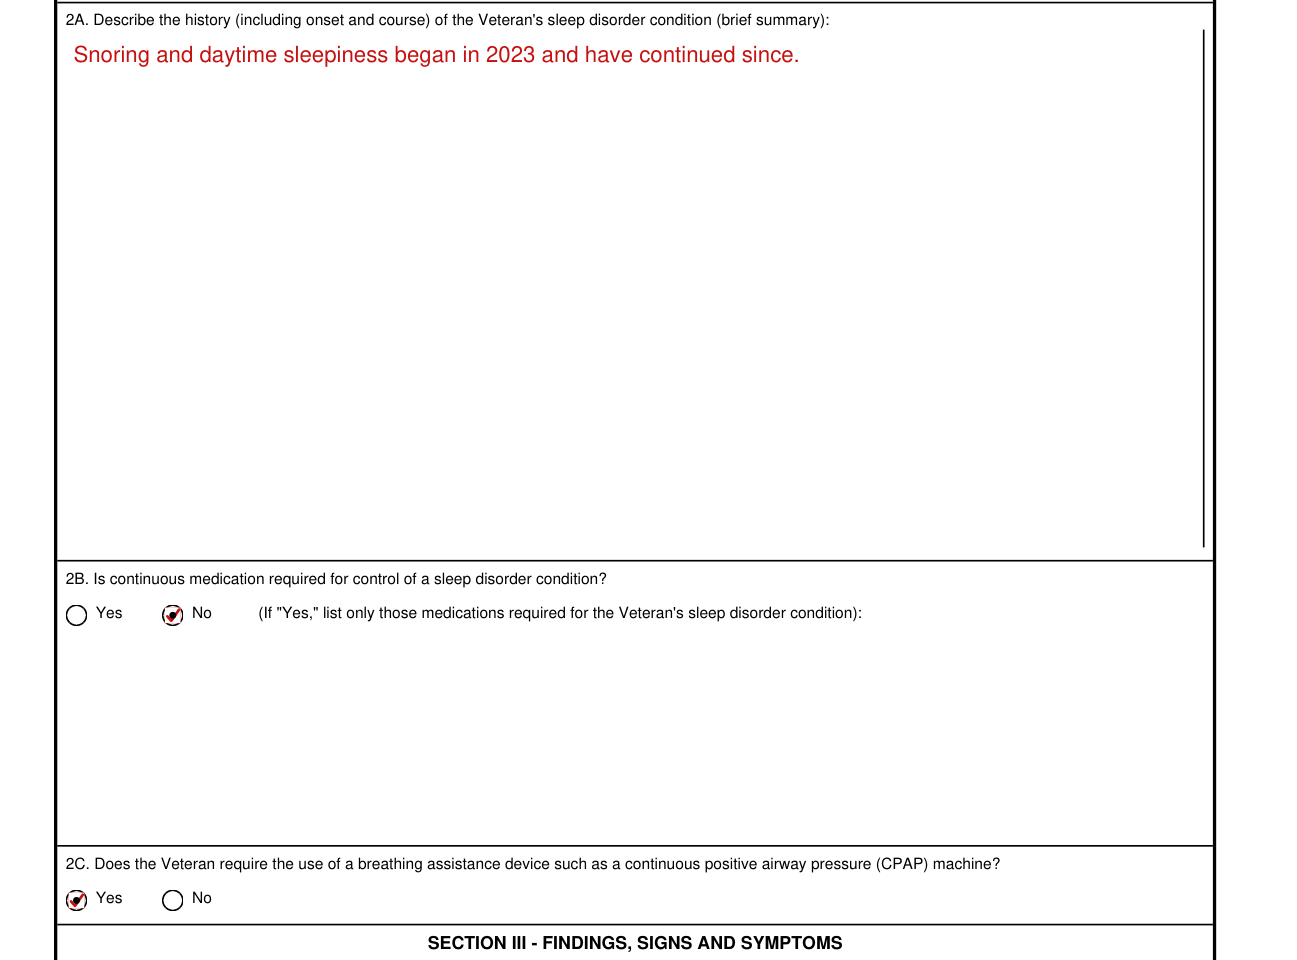
Under Section II, Medical history, 2A: Describe the history (including onset and course) of the Veteran's sleep disorder condition (brief summary).
2B. Is continuous medication required for control of a sleep disorder condition? Yes or No. If "Yes," list only those medications required for the Veteran's sleep disorder condition.
2C. Does the Veteran require the use of a breathing assistance device such as a continuous positive airway pressure (CPAP) machine? Yes or No.
3A. Findings, signs and symptoms

Under Section III, Findings, signs and symptoms, 3A: Does the Veteran currently have any findings, signs or symptoms attributable to sleep apnea? Yes or No. If "Yes," check all that apply: Persistent daytime hypersomnolence, Cor pulmonale, Carbon dioxide retention, Requires tracheostomy, Chronic respiratory failure, or Other, describe.
More rules for Sleep Apnea Disability Benefits Questionnaire
VA will not pay or reimburse any expenses or cost incurred in the process of completing and/or submitting this form.
Under Section IV, Other pertinent physical findings, complications, conditions, signs and/or symptoms, 4A: Does the Veteran have any other pertinent physical findings, complications, conditions, signs or symptoms related to any conditions listed in the diagnosis section? Yes or No. If yes, describe (brief summary).
4B. Does the Veteran have any scars (surgical or otherwise) related to any conditions or to the treatment of any conditions listed in the diagnosis section? Yes or No. If yes, are any of these scars painful or unstable; have a total area equal to or greater than 39 square cm (6 square inches); or are located on the head, face or neck? Yes or No. If yes, also complete VA Form 21-0960f-1, scars/disfigurement.
If no, provide location and measurements of scar in centimeters: Location, and Measurements: length cm X width cm. If there are multiple scars, enter additional locations and measurements in Comment section. It is not necessary to also complete a Scars DBQ.
NOTE: An "unstable scar" is one where, for any reason, there is frequent loss of covering of the skin over the scar.
4C. Comments, if any.
If diagnostic test results are in the medical record and reflect the Veteran's current sleep apnea condition, repeat testing is not required.
Under Section V, Diagnostic testing, 5A: Has a sleep study been performed? Yes or No. If "Yes," does the Veteran have documented sleep disorder breathing? Yes or No. Enter the Date of sleep study, the Name of facility where sleep study performed, if known, and the Results.
5B. Are there any other significant diagnostic test findings and/or results? Yes or No. If "Yes," provide type of test or procedure, date and results (brief summary).
Under Section VI, Functional impact, 6A: Does the Veteran's sleep apnea impact his or her ability to work? Yes or No. If "Yes," describe impact of the Veteran's sleep apnea, providing one or more examples.
Under Section VII, Remarks, 7A: Remarks (If any).
Common questions about Sleep Apnea Disability Benefits Questionnaire
Who signs it?
Enter 8A. Examiner's signature, 8B. Examiner's printed name and title (e.g. MD, DO, DDS, DMD, Ph.D, Psy.D, NP, PA-C), 8C. Examiner's Area of Practice/Specialty (e.g. Cardiology, Orthopedics, Psychology/Psychiatry, General Practice), 8D. Date Signed, 8E. Examiner's phone/fax numbers, 8F. National Provider Identifier (NPI) number, 8G. Medical license number and state, and 8H. Examiner's address.
Is there a penalty?
PENALTY: The law provides severe penalties which include fine or imprisonment, or both, for the willful submission of any statement or evidence of a material fact, knowing it to be false, or for the fraudulent acceptance of any payment to which you are not entitled.
What am I certifying when I sign?
The CERTIFICATION: "To the best of my knowledge, the information contained herein is accurate, complete and current."
Sources
[1] Sleep Apnea Disability Benefits Questionnaire (Updated on: 2024-07-19), U.S. Department of Veterans Affairs (the Official source link on this page).