


Attending Physician Statement (MetLife, APSLTD 5320) at a glance
What it is: The ATTENDING PHYSICIAN STATEMENT is a Metropolitan Life Insurance Company form whose purpose is to assist in making a disability determination; a MetLife claim representative may telephone your office if additional information is needed.
Who signs: A section of this form must be completed and signed by the employee/patient. Under Physician, enter the Contact person if additional information is necessary, then sign the Signature line and enter the Date.
A filled-in Attending Physician Statement (MetLife, APSLTD 5320) example: a patient fills in the employee section
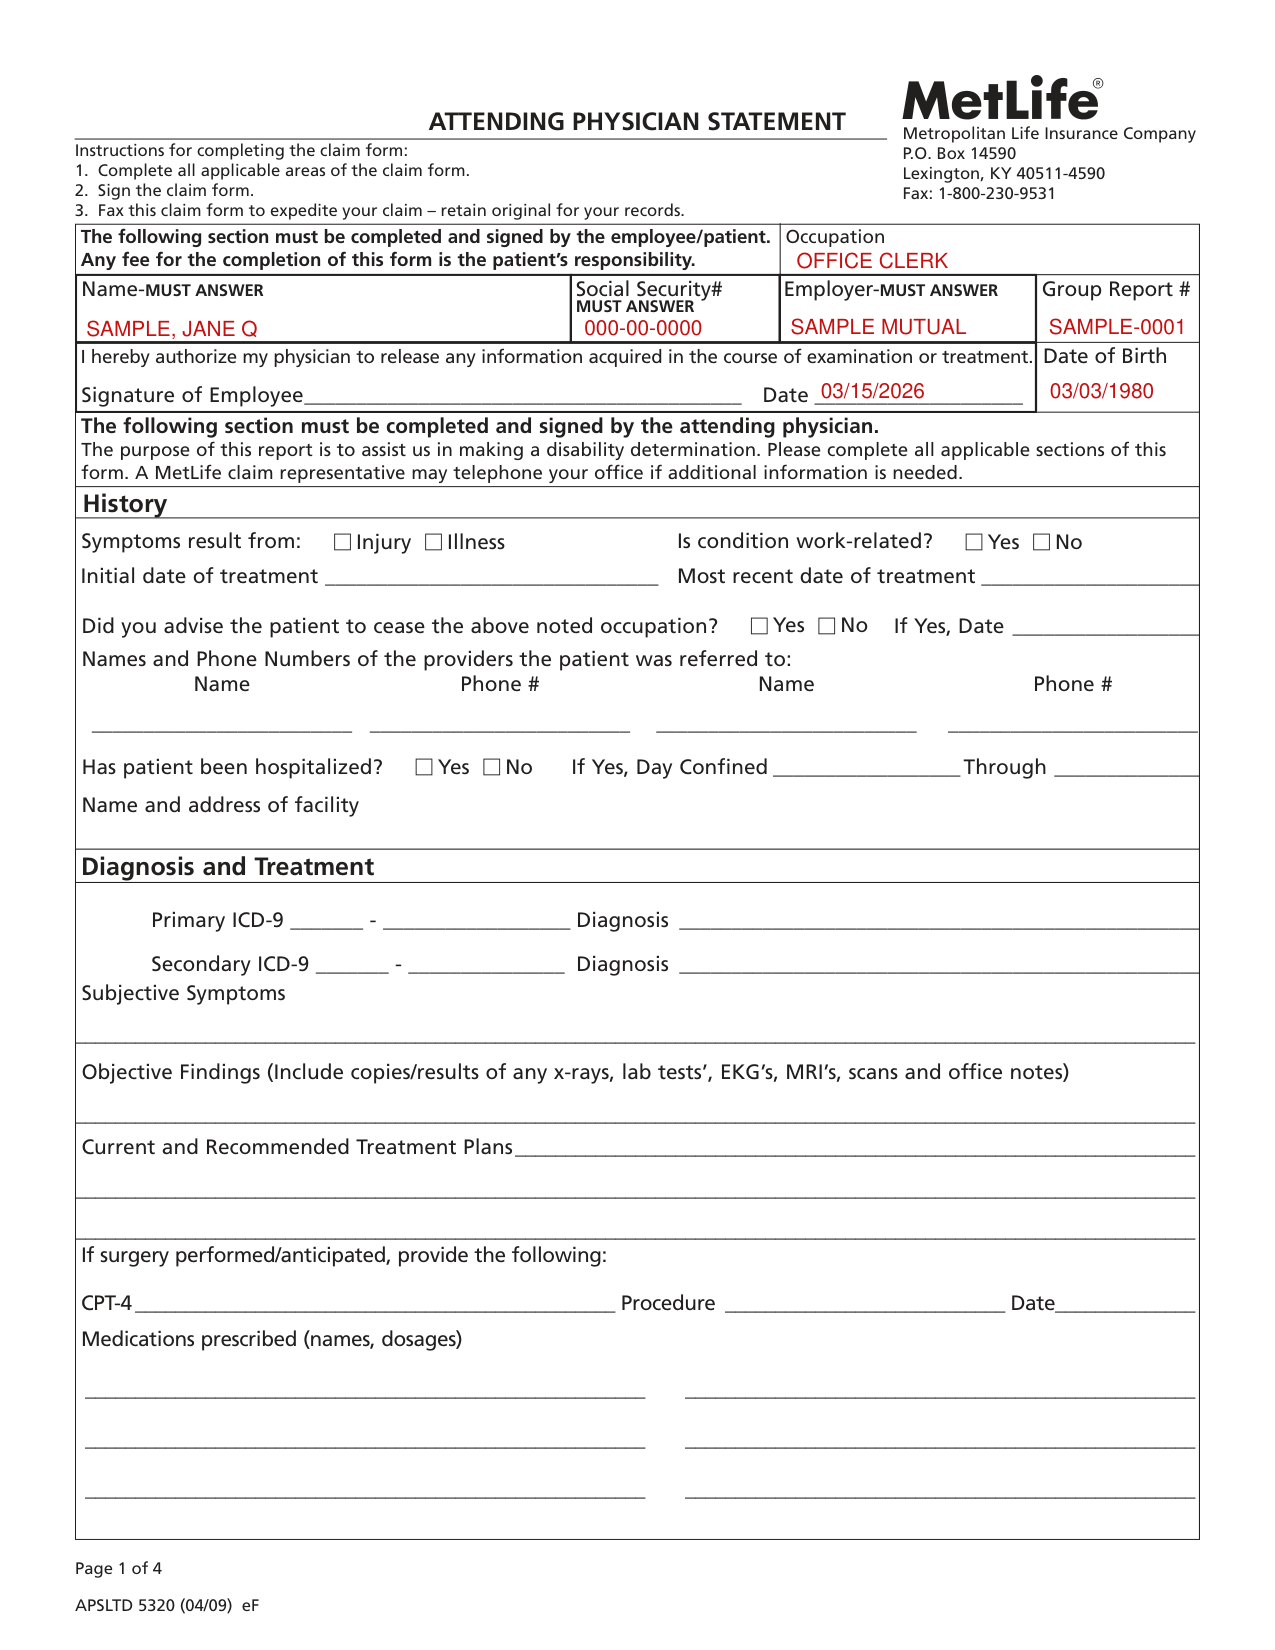
How to fill out Attending Physician Statement (MetLife, APSLTD 5320), box by box
Name, Social Security#, Occupation, Employer and Group Report #
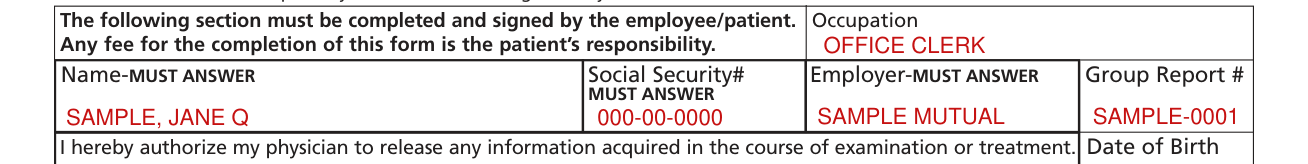
Enter Name-MUST ANSWER, Social Security#, Occupation, Employer-MUST ANSWER and Group Report #.
Signature of Employee and Date of Birth

Sign Signature of Employee under "I hereby authorize my physician to release any information acquired in the course of examination or treatment", and enter the Date and the Date of Birth.
Symptoms result from, Initial date of treatment and providers the patient was referred to

Mark Injury or Illness for Symptoms result from, mark Yes or No for Is condition work-related?, and enter the Initial date of treatment and the Most recent date of treatment.
Mark Yes or No for "Did you advise the patient to cease the above noted occupation?"; If Yes, enter the Date.
Under Names and Phone Numbers of the providers the patient was referred to, enter the Name and Phone # of each provider.
Has patient been hospitalized?

Mark Yes or No for Has patient been hospitalized?; If Yes, enter the Day Confined, Through and the Name and address of facility.
Diagnosis and Treatment
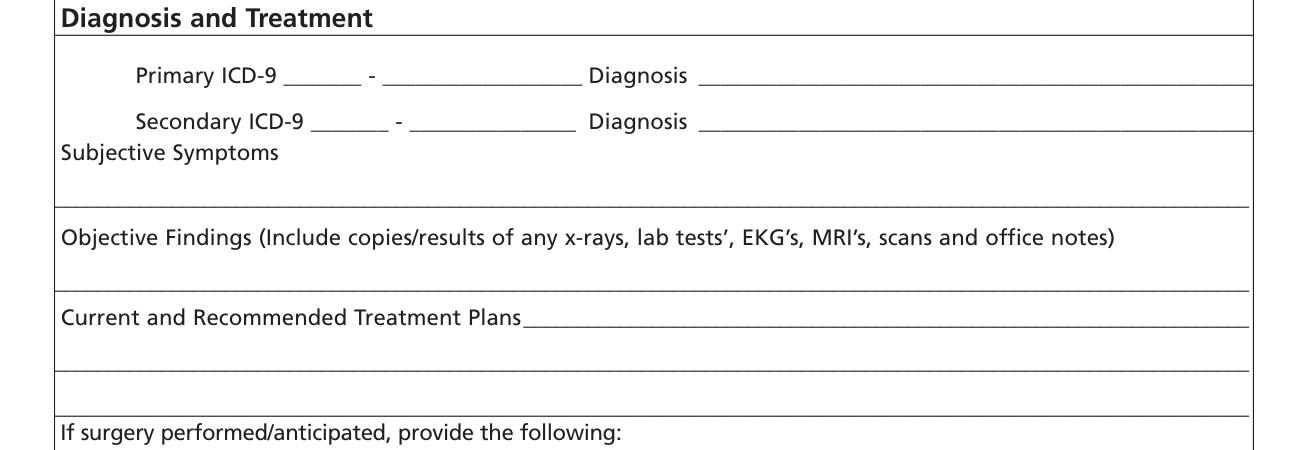
Enter the Primary ICD-9 and its Diagnosis, the Secondary ICD-9 and its Diagnosis, and the Subjective Symptoms.
For Objective Findings, include copies/results of any x-rays, lab tests', EKG's, MRI's, scans and office notes.
Enter the Current and Recommended Treatment Plans.
If surgery performed/anticipated

If surgery performed/anticipated, provide the following: CPT-4, Procedure and Date.
Enter the Medications prescribed (names, dosages).
Psychological Functions
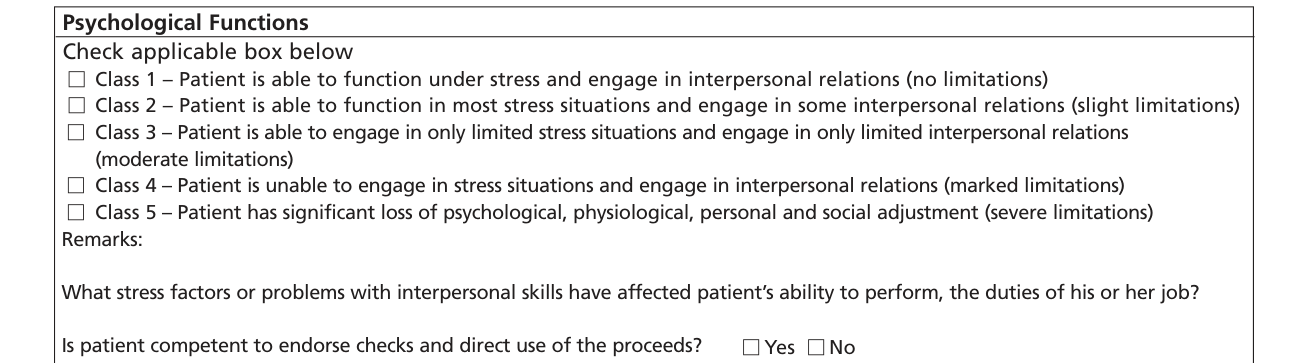
Under Psychological Functions, check the applicable box: Class 1 (no limitations), Class 2 (slight limitations), Class 3 (moderate limitations), Class 4 (marked limitations) or Class 5 (severe limitations), and write any Remarks.
Write: What stress factors or problems with interpersonal skills have affected patient's ability to perform, the duties of his or her job?
Mark Yes or No for Is patient competent to endorse checks and direct use of the proceeds?
Physical Capabilities
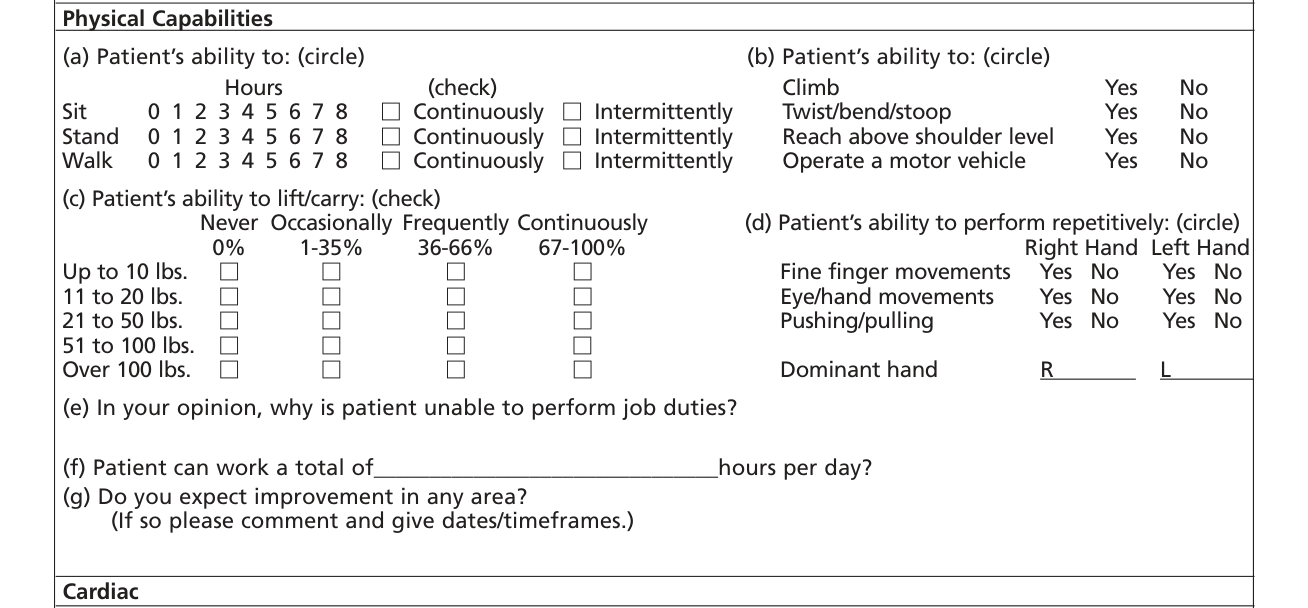
Under Physical Capabilities, circle Yes or No for Climb, Twist/bend/stoop, "Reach above shoulder level" and Operate a motor vehicle, circle the Hours for Sit, Stand and Walk, and check Continuously or Intermittently.
Check Never, Occasionally, Frequently or Continuously for Patient's ability to lift/carry Up to 10 lbs., 11 to 20 lbs., 21 to 50 lbs., 51 to 100 lbs. and Over 100 lbs., and mark Dominant hand R or L.
For Patient's ability to perform repetitively, circle Yes or No for the Right Hand and the Left Hand for Fine finger movements, Eye/hand movements and Pushing/pulling.
Write: In your opinion, why is patient unable to perform job duties?
Enter the hours per day Patient can work a total of, and for Do you expect improvement in any area?, comment and give dates/timeframes.
Cardiac Functional Capacity
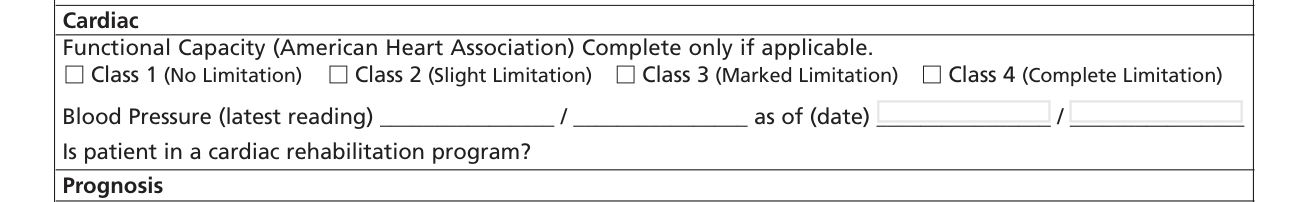
Complete the Cardiac Functional Capacity (American Heart Association) section only if applicable, and check Class 1 (No Limitation), Class 2 (Slight Limitation), Class 3 (Marked Limitation) or Class 4 (Complete Limitation).
Enter the Blood Pressure (latest reading) and the as of (date), and enter Yes or No for Is patient in a cardiac rehabilitation program?
Prognosis

For Prognosis, enter Yes or No for Have you advised patient to return to work?: If Yes, enter the date of return and check To regular occupation or To any other occupation, each Full Time or Part Time; If Not, please explain.
Enter any work/activity restrictions applicable (please be specific).
Rehab

Under Rehab, for Do you suggest that the patient become involved in any of the following?, please check as many as apply.
Check Physical Therapy, Pain Management Program, Vocational Rehabilitation, Occupational Therapy, Work Hardening Program, Psychological Counseling, Cardiac Rehabilitation, Job Modification or Other, and mark Yes or No for If so, was this discussed with the patient?
Physician
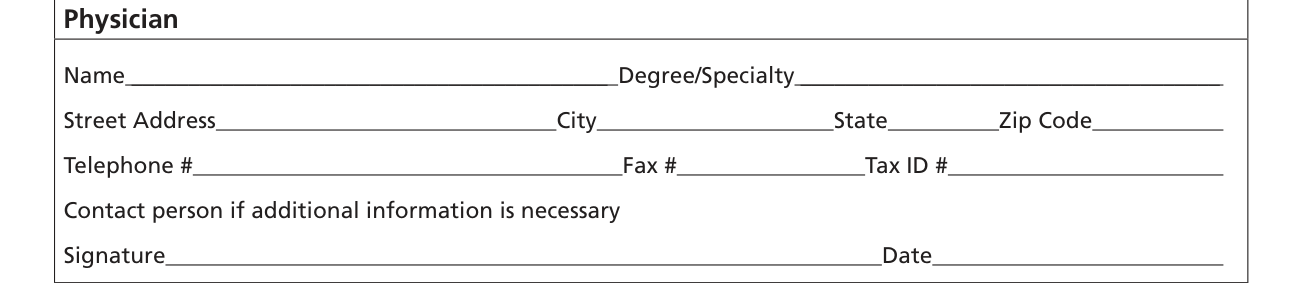
Under Physician, enter Name, Degree/Specialty, Street Address, City, State, Zip Code, Telephone #, Fax # and Tax ID #.
Under Physician, enter the Contact person if additional information is necessary, then sign the Signature line and enter the Date.
More rules for Attending Physician Statement (MetLife, APSLTD 5320)
Complete all applicable areas of the claim form and sign the claim form.
Enter the Name of Employee and the Social Security Number.
Any person who knowingly and with intent to defraud any insurance company or other person files an application for insurance or a statement of claim with materially false information may be guilty of committing a fraudulent insurance act.
Common questions about Attending Physician Statement (MetLife, APSLTD 5320)
Where do I file it?
Fax this claim form to expedite your claim and retain the original for your records: Metropolitan Life Insurance Company, P.O. Box 14590, Lexington, KY 40511-4590, Fax: 1-800-230-9531.
Are there fees?
Any fee for the completion of this form is the patient's responsibility.
Is there a penalty?
In Texas, any person who knowingly presents a false or fraudulent claim for the payment of a loss is guilty of a crime and may be subject to fines and confinement in state prison. In Colorado, it is unlawful to knowingly provide false, incomplete, or misleading facts or information to an insurance company for the purpose of defrauding or attempting to defraud the company; penalties may include imprisonment, fines, denial of life insurance, and civil damages.
Sources
[1] MetLife Attending Physician Statement (APSLTD 5320 (04/09)), as served on the page (the Official source link on this page).