
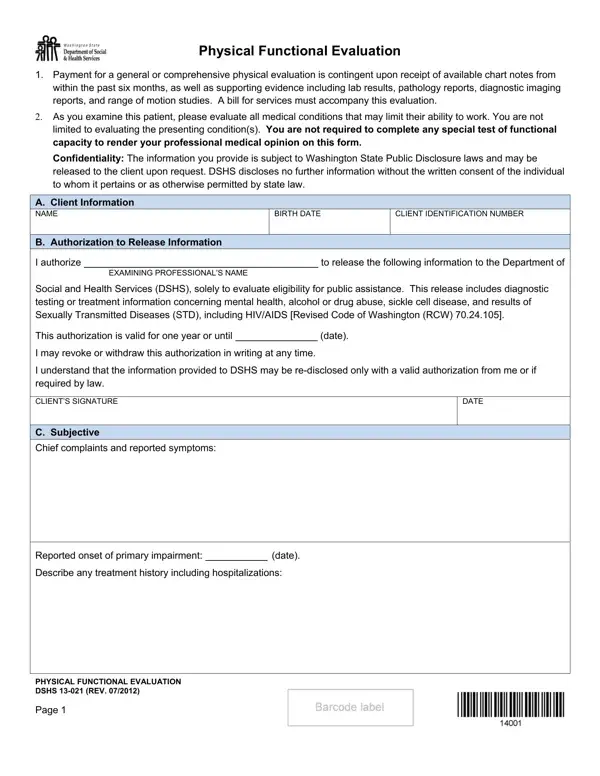

Form DSHS 13-021 at a glance
What it is: Physical Functional Evaluation DSHS 13-021 (REV. 06/2020).
Who signs: The client signs. The examining professional signs on the EXAMINING PROFESSIONAL'S SIGNATURE/TITLE line and enters the DATE.
Payment for a general or comprehensive physical evaluation is contingent upon receipt of available chart notes from within the past six months, as well as supporting evidence including lab results, pathology reports, diagnostic imaging reports, and range of motion studies. You must be enrolled in ProviderOne to claim reimbursements for these services.
As you examine this patient, evaluate all medical conditions that may limit their ability to work. You are not limited to evaluating the presenting condition(s). You are not required to complete any special test of functional capacity to render your professional medical opinion on this form. Confidentiality: The information you provide is subject to Washington State Public Disclosure laws and may be released to the client upon request. DSHS discloses no further information without the written consent of the individual to whom it pertains or as otherwise permitted by state law.
A filled-in Form DSHS 13-021 example: a physician completes the evaluation
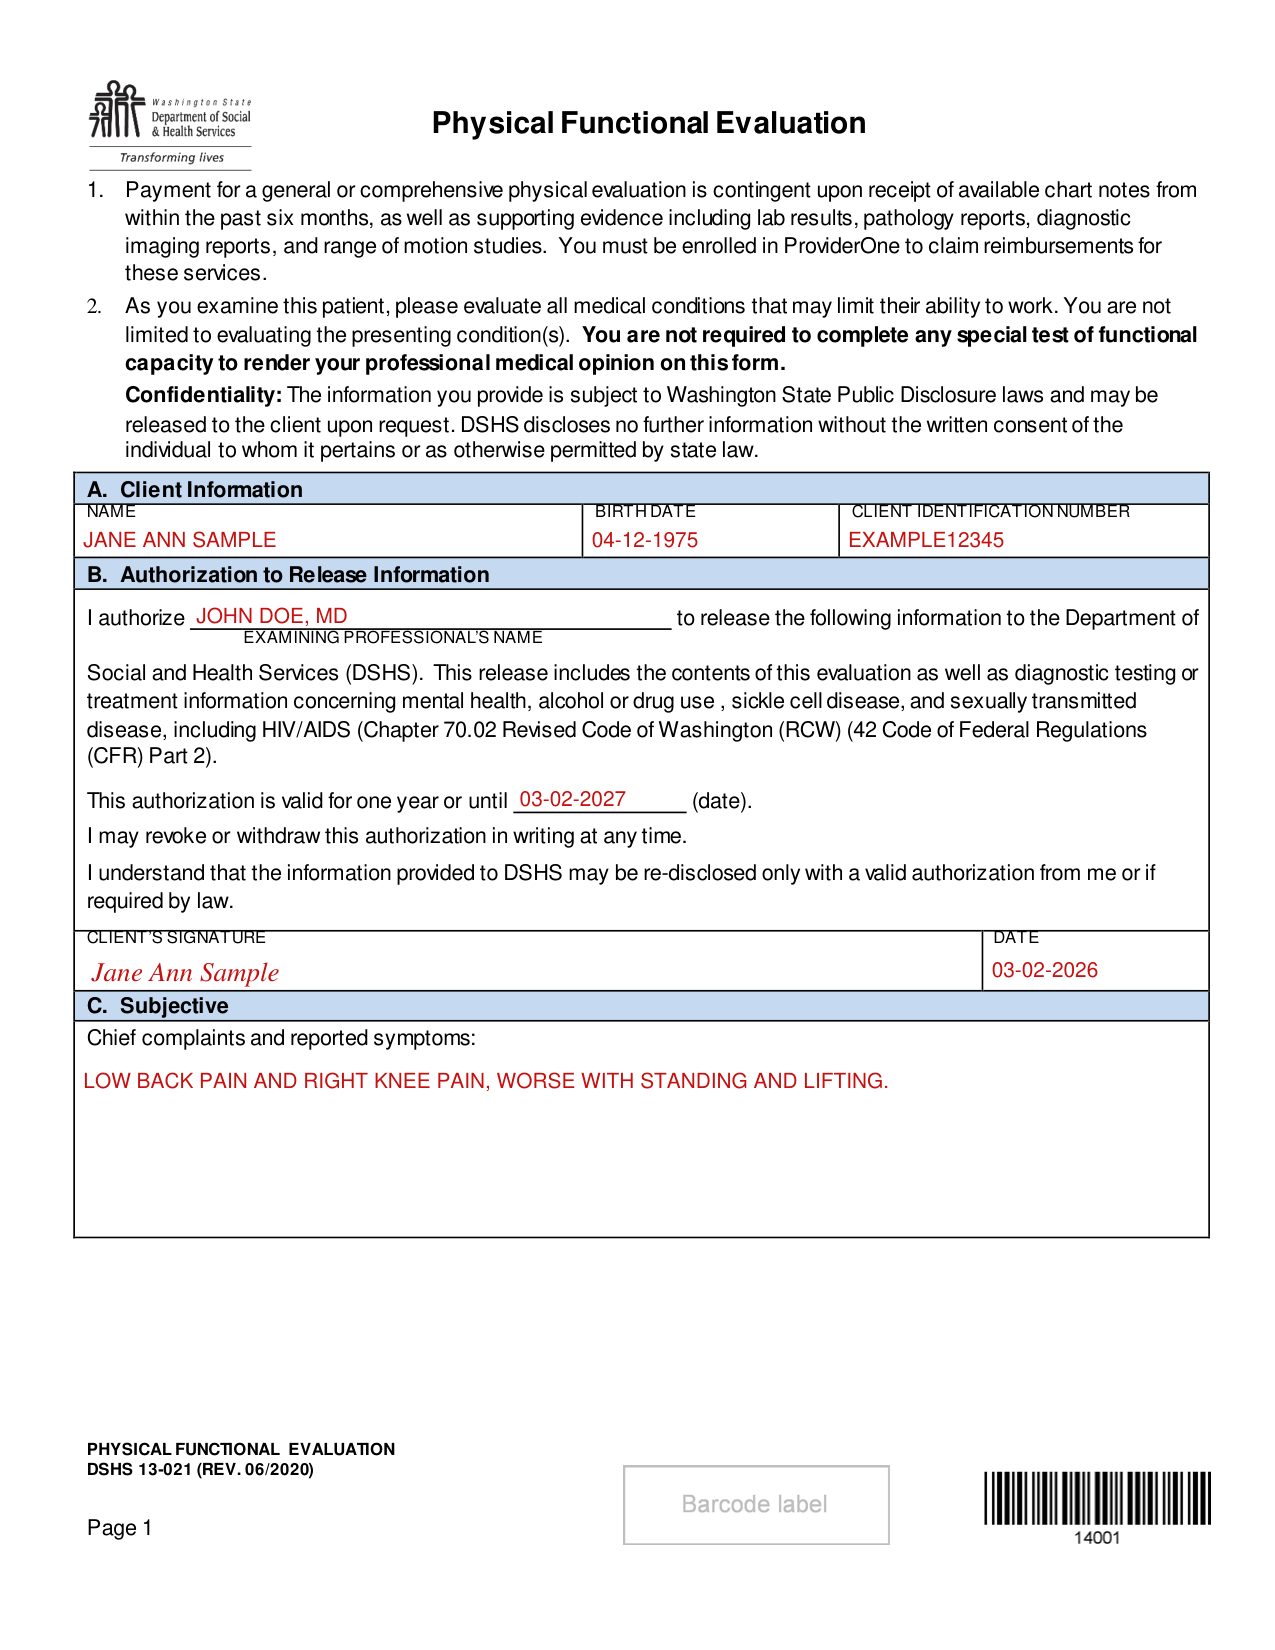
How to fill out Form DSHS 13-021, box by box
A. Client Information
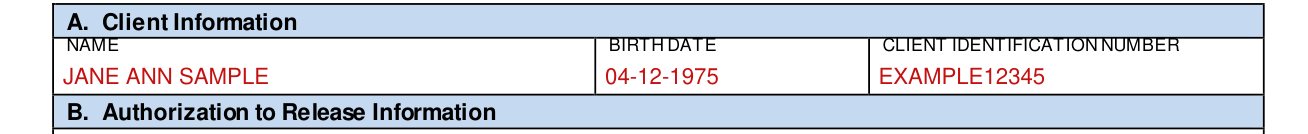
Under A. Client Information, enter the client's NAME, BIRTH DATE and CLIENT IDENTIFICATION NUMBER.
B. Authorization to Release Information

Enter the EXAMINING PROFESSIONAL'S NAME after "I authorize", to release the following information to the Department of Social and Health Services (DSHS). This release includes the contents of this evaluation as well as diagnostic testing or treatment information concerning mental health, alcohol or drug use, sickle cell disease, and sexually transmitted disease, including HIV/AIDS (Chapter 70.02 Revised Code of Washington (RCW) and 42 Code of Federal Regulations (CFR) Part 2).
Enter the date in "This authorization is valid for one year or until (date)".
The client may revoke or withdraw this authorization in writing at any time. The information provided to DSHS may be re-disclosed only with a valid authorization from the client or if required by law. The client signs on the CLIENT'S SIGNATURE line and enters the DATE.
C. Subjective
Under C. Subjective, write the chief complaints and reported symptoms.
Enter the date of the reported onset of primary impairment.
Describe any treatment history including hospitalizations.
D. Objective
Under D. Objective, attach chart notes detailing examination findings.
Describe any non-exertional limitations or workplace restrictions (such as chemical sensitivities or inability to work at heights).
List all laboratory, imaging, range of motion, and other diagnostic test results (attach reports).
E. Assessment: diagnoses, affected work activities and severity ratings
Under E. Assessment, list each diagnosis in Column 1, starting with the primary impairment.
Under AFFECTED WORK ACTIVITY, enter basic work activities, which include (a) sitting, (b) standing, (c) walking, (d) lifting, (e) carrying, (f) handling, (g) pushing, (h) pulling, (i) reaching, (j) stooping, (k) crouching, (l) seeing, (m) hearing, and (n) communicating.
In Column 3, SEVERITY RATING, estimate the severity of the diagnosis based on your professional medical opinion using the following definitions.
None: No interference with the ability to perform one or more basic work-related activities.
Mild: No significant interference with the ability to perform one or more basic work-related activities.
Moderate: Significant interference with the ability to perform one or more basic work-related activities.
Marked: Very significant interference with the ability to perform one or more basic work-related activities.
Severe: Inability to perform one or more basic work-related activities.
Work level the client is capable of performing

Mark the work level the client is capable of performing in a regular predictable manner despite their impairment.
Heavy work: able to lift 100 pounds maximum and frequently lift or carry up to 50 pounds.
Medium work: able to lift 50 pounds maximum and frequently lift and/or carry up to 25 pounds.
Light work: able to lift 20 pounds maximum and frequently lift or carry up to 10 pounds, able to walk or stand six out of eight hours per day, and able to sit and use pushing or pulling arm or leg movements most of the day.
Sedentary work: able to lift 10 pounds maximum and frequently lift or carry lightweight articles. Able to walk or stand only for brief periods.
Severely limited: unable to meet the demands of sedentary work.
In your professional medical opinion, regular* predictable manner means the person is capable of sustaining the work level over a normal workday and workweek on an ongoing, appropriate, and independent basis.
In your professional medical opinion, frequently** means the person is able to perform the function for 2.5 to 6 hours out of an 8 hour day. It is not necessary that performance be continuous.
Duration and substance abuse
Under DURATION, enter in MONTHS how long you estimate the current limitation on work activities will persist with available medical treatment.
Under SUBSTANCE ABUSE, mark Yes or No for "Are the effects on basic work activities primarily the result of substance use disorder?" and fill in Please explain.
Mark Yes or No for "Would the effects on basic work activities persist following 60 days of sobriety?" If not, fill in how they would change.
Mark Yes or No for "Is a chemical dependency assessment of substance use treatment recommended?"
F. Plan
Under F. Plan, list any additional tests or consultations needed.
Write what treatment is recommended.
Return address, examining professional and worker lines

Fill in RETURN THIS REPORT TO.
Enter the print name of the examining professional, the examination date, the specialty area/advanced training and the telephone number.
Enter the STREET ADDRESS, CITY, STATE and ZIP CODE.
The worker signs on the WORKER SIGNATURE line and enters the DATE, TELEPHONE NUMBER and FAX NUMBER.
Signatures of the examining professional and the reviewing and adopting professional

The examining professional signs on the EXAMINING PROFESSIONAL'S SIGNATURE/TITLE line and enters the DATE.
The reviewing and adopting professional signs on the REVIEWING AND ADOPTING PROFESSIONAL'S SIGNATURE line and enters the DATE.
Sources
[1] Form DSHS 13-021 (REV. 06/2020), Physical Functional Evaluation, Washington State Department of Social and Health Services (the Official source link on this page).