
NAVMED 1300/4 at a glance
What it is: NAVMED 1300/4 is an expeditionary medical screening completed for overseas contingency operations, specific temporary additional duty assignments, and mobilizations for the Reserve Component (RC).
Who signs: PART II - RECORD REVIEW (Page 2-4) may be completed by a designated Hospitalman (HM), Medical Assistant (MA), licensed Nurse (i.e., LPN, RN). PART III - DENTAL SCREENING (Page 4) is completed by an authorized dental provider. PART IV - MEDICAL SCREENING (Page 5) is completed by an authorized medical provider. PART V - FINAL REVIEW/ CERTIFICATION (Page 7) must be completed by a Commanding Officer, Officer in Charge, or designee of the Navy Medicine command conducting the screening (e.g., NMRTC, NMRTU, AMMU, etc.).
What to bring and attach to NAVMED 1300/4
This form MUST be completed in conjunction with DD Form 2807-1, Report of Medical History.
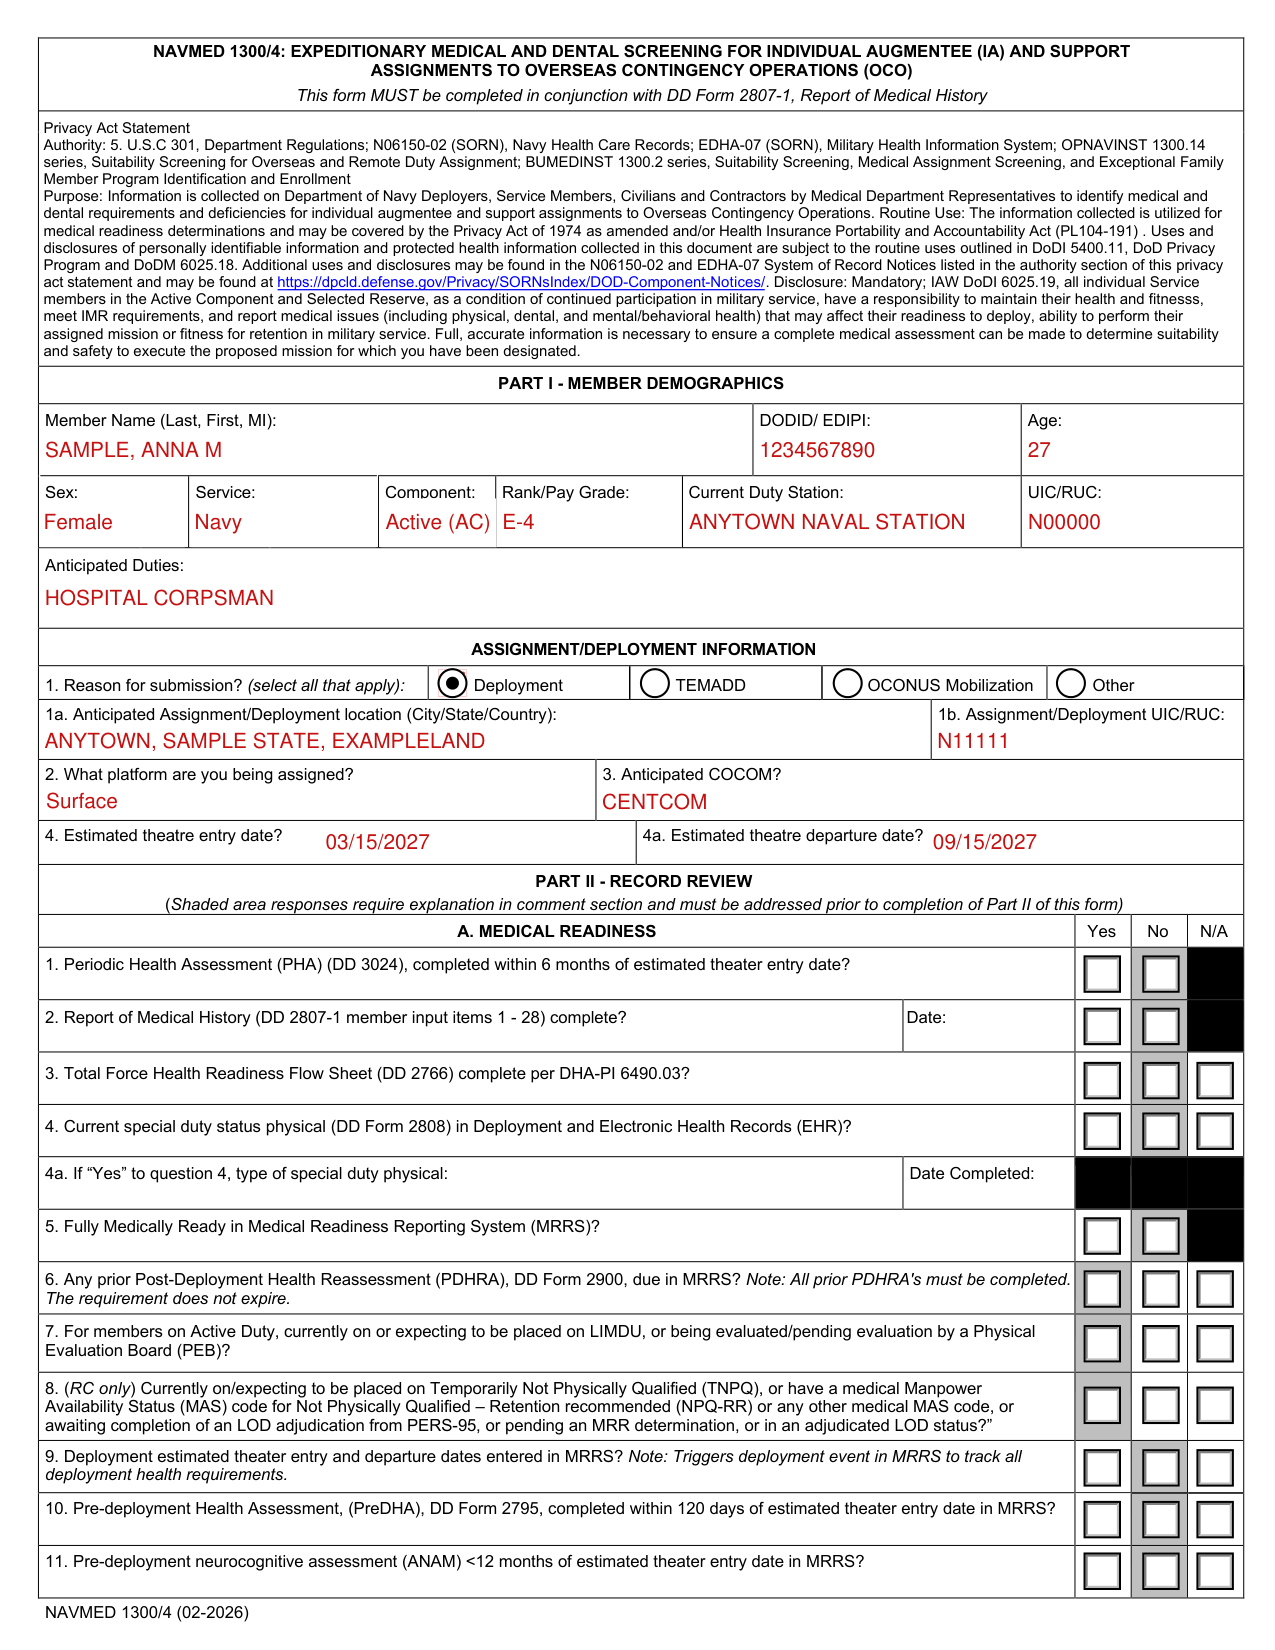
A filled-in NAVMED 1300/4 example: a sailor fills out Part I
How to fill out NAVMED 1300/4, box by box
Part I - Member demographics
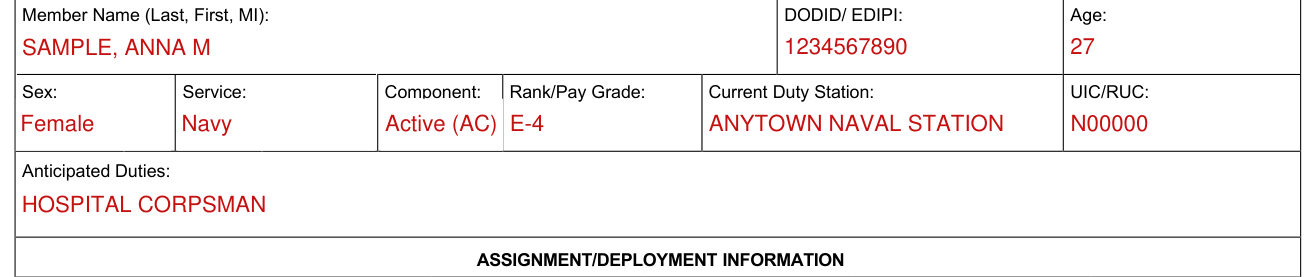
In PART I - MEMBER DEMOGRAPHICS (Page 2), the member will input their demographic information and anticipated assignment information.
Fill in Member Name (Last, First, MI), DODID/ EDIPI, Age, Sex, Service, Component, Rank/Pay Grade, Current Duty Station, UIC/RUC and Anticipated Duties.
Assignment/Deployment information
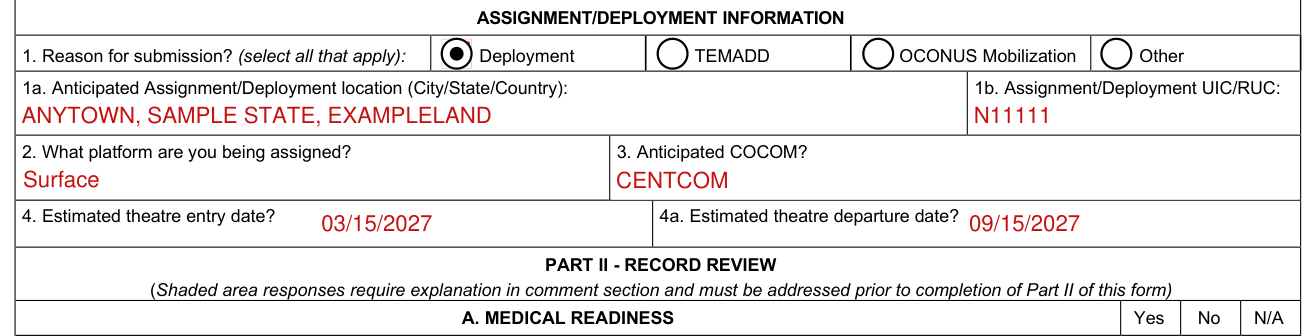
Under ASSIGNMENT/DEPLOYMENT INFORMATION, select all that apply for 1. Reason for submission: Deployment, TEMADD, OCONUS Mobilization or Other.
In 1a, enter the Anticipated Assignment/Deployment location (City/State/Country); in 1b, enter the Assignment/Deployment UIC/RUC.
2. What platform are you being assigned? and 3. Anticipated COCOM?
For platform assignment, specify one of the following: Surface, Air, Submarine, Naval Information, Navy Expeditionary Combat, Special Operations, Fleet Marine Force, Expeditionary Medicine, Other.
Enter the Estimated theatre entry date in 4 and the Estimated theatre departure date in 4a.
Part II - Record review, A. Medical readiness
In PART II - RECORD REVIEW, shaded area responses require explanation in comment section and must be addressed prior to completion of Part II of this form.
A. MEDICAL READINESS Yes No N/A: 1. Periodic Health Assessment (PHA) (DD 3024), completed within 6 months of estimated theater entry date?
2. Report of Medical History (DD 2807-1 member input items 1 - 28) complete? Enter the Date.
3. Total Force Health Readiness Flow Sheet (DD 2766) complete per DHA-PI 6490.03?
4. Current special duty status physical (DD Form 2808) in Deployment and Electronic Health Records (EHR)? If “Yes” to question 4, enter 4a, type of special duty physical, and Date Completed.
5. Fully Medically Ready in Medical Readiness Reporting System (MRRS)?
6. Any prior Post-Deployment Health Reassessment (PDHRA), DD Form 2900, due in MRRS? All prior PDHRA's must be completed. The requirement does not expire.
7. For members on Active Duty, currently on or expecting to be placed on LIMDU, or being evaluated/pending evaluation by a Physical Evaluation Board (PEB)?
9. Deployment estimated theater entry and departure dates entered in MRRS? Triggers deployment event in MRRS to track all deployment health requirements.
10. Pre-deployment Health Assessment, (PreDHA), DD Form 2795, completed within 120 days of estimated theater entry date in MRRS?
11. Pre-deployment neurocognitive assessment (ANAM) <12 months of estimated theater entry date in MRRS?
Part II, B. Audiogram, C. Immunizations and D. Labs
B. AUDIOGRAM: 1. If required, audiogram (DD Form 2215 or DD Form 2216) completed within 12 months of deployment start date? Enter the Exam Date.
C. IMMUNIZATIONS Yes No N/A: 1. Are member's routine readiness immunizations up-to-date and documented in MRRS, to include annual influenza vaccine?
D. LABS: 1. All Service-mandated labs (Blood type and Rh factor, Sickle Cell Trait, DNA, and G6PD) must be completed and documented in MRRS; if any are missing, they must be ordered and confirmed complete prior to deployment.
2. Biennial Human Immunodeficiency Virus (HIV) laboratory test complete and documented in MRRS?
Part II, I. Record review verification and the reviewer's signature
COMMENTS: Provide comment for any shaded area responses in sections A-H.
I. RECORD REVIEW VERIFICATION: 1. Are there any shaded boxes checked in Part II, A through H? if yes, comment on all shaded responses.
Under COMMENTS ON ALL SHADED AREA RESPONSES, attach additional pages as needed, include line number.
Fill in Record Reviewer Name (Last, First, MI), Rank/Pay Grade, Position, NMRTC or Duty Station Name, NMRTC or Duty Station UIC/RUC, Telephone Number (Include Area Code), DSN and E-Mail Address.
By signing you certify that you have reviewed the member's records as the designated medical record reviewer and attest all the information to be true and accurate.
Part III - Dental screening
In PART III - DENTAL SCREENING, shaded area responses require explanation in comment section.
Fill in Dental Provider Name (Last, First, MI), Rank/Pay Grade, NMRTC or Duty Station Name, Telephone Number (Include Area Code), DSN and E-Mail Address.
By signing you certify that you have reviewed the member's records as the designated dental provider and attest all the information to be true and accurate.
Part IV - Medical screening
PART IV - MEDICAL SCREENING Yes No N/A: 1. All current health records (military and/or civilian) reviewed?
Fill in Medical Provider Name (Last, First, MI), Provider Type, Rank/Pay Grade, Duty Station Name, UIC/RUC, Telephone Number (Include Area Code), DSN and E-Mail Address.
By signing you certify that you have reviewed the member's records as the designated medical provider and attest all the information to be true and accurate.
Waiver request
In C. WAIVER REQUEST, copies of waivers must be documented in MRRS and on the DD 2766, with copies in the health record.
Medical waiver approval authority lies at the Combatant Command, delegated to the Combatant Command Surgeon. It may be delegated to the Service component surgeons.
Mark 1. Firearm Carry and Issuance Waiver and 2. Medical Waiver as Approved, Denied or N/A, with Date.
Part V - Final review / certification
PART V - FINAL REVIEW / CERTIFICATION, Navy Medicine Commanding Officer, Officer in Charge, or designee (MC, NC, DC, MSC) Yes No N/A: 1. Based upon a review of the member's medical and dental status and Parts I-IV of this form, the member is suitable for the proposed assignment.
Fill in Name (Last, First, MI), Rank/Pay Grade, Designator, Duty Station Name, UIC/RUC, Telephone Number, DSN and E-Mail Address.
Sign in Signature and enter Date.
Sources
[1] NAVMED 1300/4 (02-2026), Expeditionary Medical and Dental Screening for Individual Augmentee (IA) and Support Assignments to Overseas Contingency Operations (OCO), U.S. Navy Bureau of Medicine and Surgery (the Official source link on this page).