Coventry Medical Prior Authorization Form PDF Details

The Coventry Prior Authorization form is a healthcare document that allows providers to request approval for specific medical services before they are delivered. This process ensures that services meet medical necessity criteria and are covered under the patient's insurance plan.

The form accommodates requests for patients enrolled in multiple plan types, including Commercial/Individual, Medicare, Medicaid, and Healthy Kids. Each submission must include the provider's contact details, the patient's member ID and date of birth, a diagnosis code, and a description of the service or medication being requested. Supporting clinical documentation must accompany every request to facilitate timely review.

Requests are classified by urgency. Stat requests are processed within 24 hours for cases requiring immediate medical attention. Routine requests are reviewed within 4 to 14 days. Incomplete submissions may delay processing, so providers should verify all required fields are completed before submitting.

Note that authorization does not guarantee payment. Healthcare providers must verify member eligibility and benefits before rendering any service. Claims must be submitted following the plan's billing guidelines, and specialty network physicians must follow the procedures outlined in the form instructions.

Frequently Asked Questions

Who needs to complete a prior authorization form? Any healthcare provider requiring pre-approval for services such as specialist visits, prescription medications, durable medical equipment, or elective procedures must submit this form before delivering care to the patient.

What happens if authorization is denied? Providers and patients have the right to appeal a denial. The plan will provide instructions for the appeals process, which may include submitting additional clinical documentation or requesting a peer-to-peer review with the plan's medical director.

How is the form submitted? The form can be submitted by fax, mail, or through the plan's online provider portal, depending on your region and plan type. Contact Coventry Health Care directly for the preferred submission method in your area.

If you work with multiple insurance plans, explore related prior authorization forms: Aetna Pharmacy Prior Authorization Form, Drug Prior Authorization Form, HealthNet Prior Authorization Form, and Ambetter Inpatient Prior Authorization Form.

QuestionAnswer
Form Name Coventry Prior Authorization Form
Form Length 1 pages
Fillable? No
Fillable fields 0
Avg. time to fill out 15 sec
Other names aetna coventry prior authorization form, aetna coventry medicare prior authorization form, coventry prior auth form, coventry health care prior authorization form

How to Fill Out Form 749VMPR

Form 749VMPR at a glance

What it is: Form # 749VMPR is a medical prior authorization request.

Who signs: Sign on the Primary Care Physician Signature line.

A filled-in Form 749VMPR example: a clinic requests an outpatient procedure
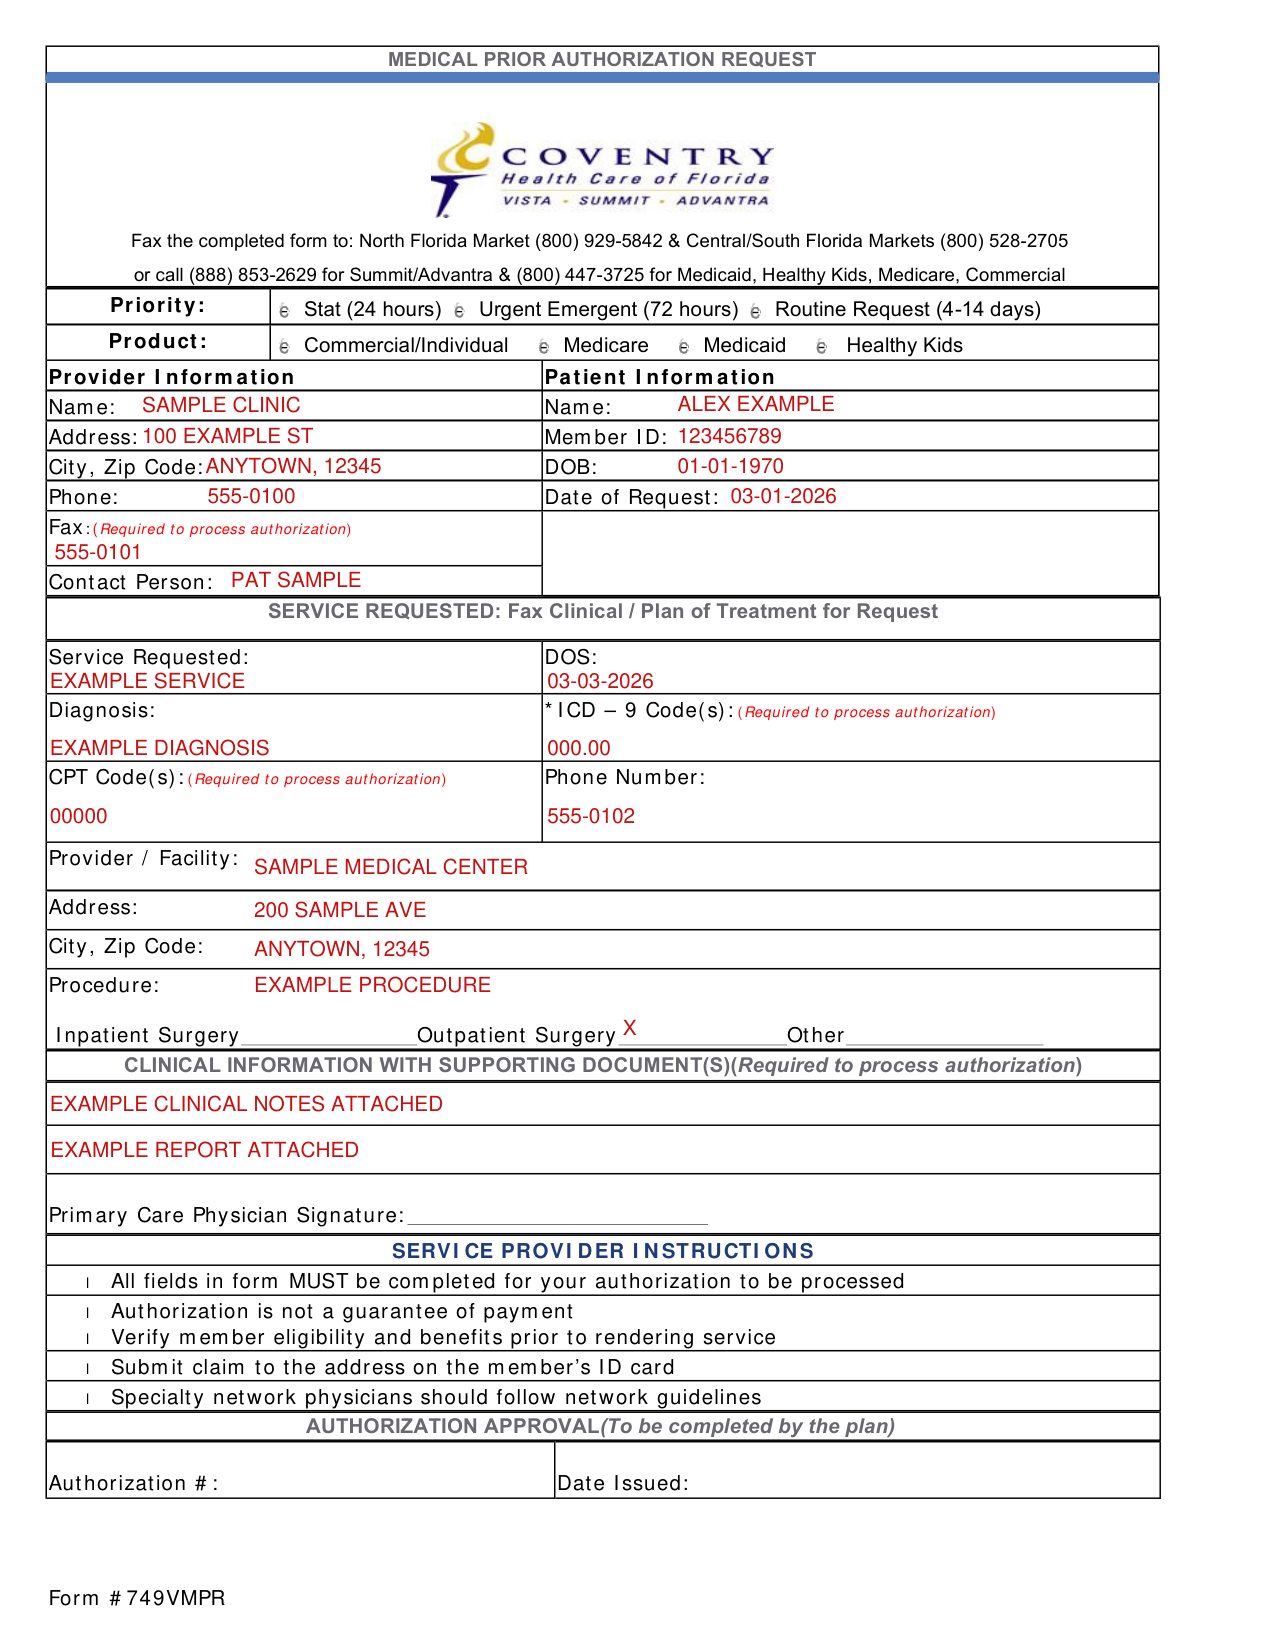
Form 749VMPR example filled out, example: a clinic requests an outpatient procedure
Pat Sample, a clinic contact, fills out the Medical Prior Authorization Request. Pat requests one outpatient procedure for a patient, with a date of service of March 3, 2026. The picture shows page 1, and none of its entries is real. Inpatient Surgery and Other are left blank because the procedure is outpatient. Primary Care Physician Signature is left blank because the physician signs the printed page.

How to fill out Form 749VMPR, box by box

Provider Information and Patient Information
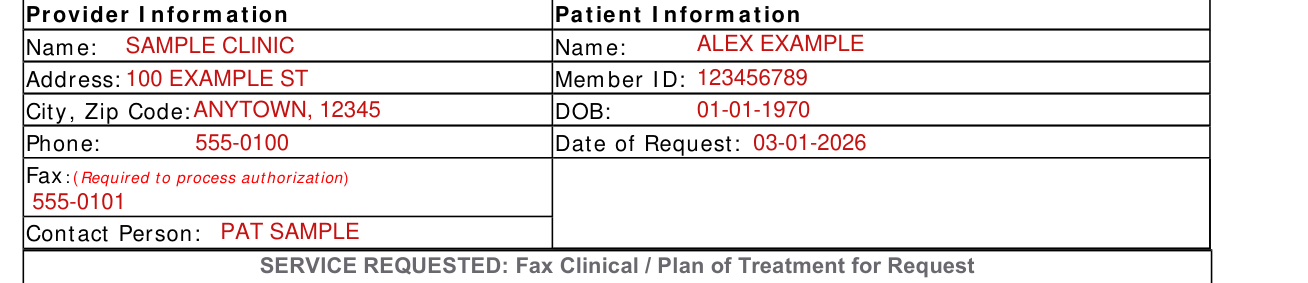
Form 749VMPR example filled out, provider Information and Patient Information

Under Provider Information, fill in Name, Address, City, Zip Code, Phone, Fax and Contact Person; Fax is required to process authorization.

Under Patient Information, fill in Name, Member ID, DOB and Date of Request.

Service Requested

Form 749VMPR example filled out, service Requested

Under SERVICE REQUESTED, fill in Service Requested and DOS.

Enter the Diagnosis and the ICD-9 Code(s) (Required to process authorization).

Enter the CPT Code(s) (Required to process authorization).

Enter the Phone Number.

Provider / Facility
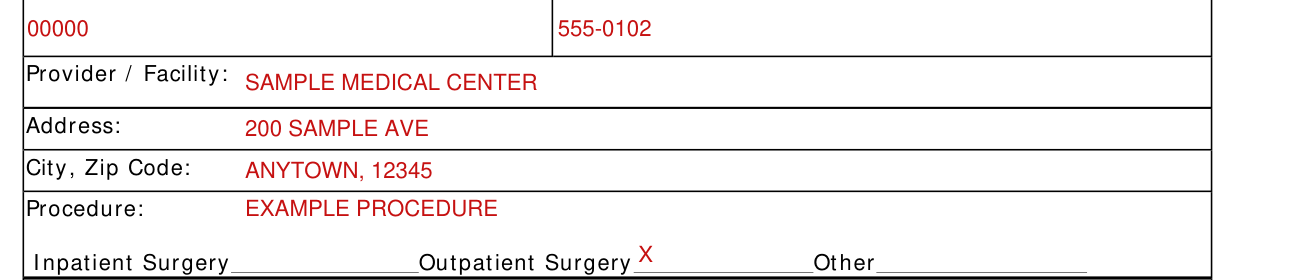
Form 749VMPR example filled out, provider / Facility

Under Provider / Facility, fill in Provider / Facility, Address and City, Zip Code.

Procedure: Inpatient Surgery, Outpatient Surgery, Other

Form 749VMPR example filled out, procedure: Inpatient Surgery, Outpatient Surgery, Other

Procedure: Inpatient Surgery, Outpatient Surgery, Other.

Clinical information and Primary Care Physician Signature
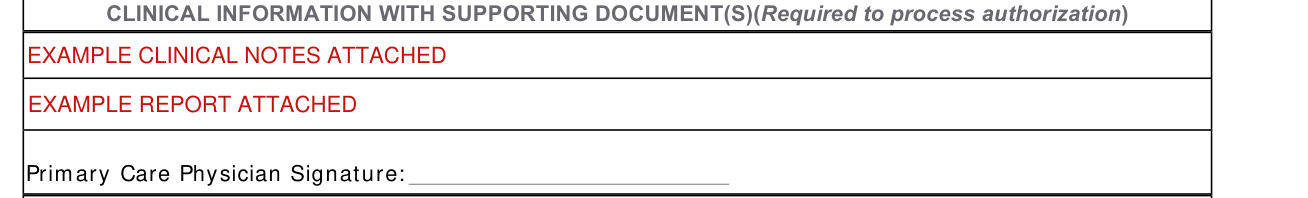
Form 749VMPR example filled out, clinical information and Primary Care Physician Signature

Clinical information with supporting document(s) (Required to process authorization).

Sign on the Primary Care Physician Signature line.

More rules for Form 749VMPR

Priority: Stat (24 hours), Urgent Emergent (72 hours), Routine Request (4-14 days).

Product: Commercial/Individual, Medicare, Medicaid, Healthy Kids.

All fields in the form must be completed for your authorization to be processed.

Authorization is not a guarantee of payment.

Verify member eligibility and benefits prior to rendering service.

Submit claim to the address on the ID card.

Specialty network physicians should follow network guidelines.

AUTHORIZATION APPROVAL (To be completed by the plan): Authorization #, Date Issued.

Common questions about Form 749VMPR

Where do I file it?

Fax the completed form to: North Florida Market (800) 929-5842 and Central/South Florida Markets (800) 528-2705. Or call (888) 853-2629 for Summit/Advantra and (800) 447-3725 for Medicaid, Healthy Kids, Medicare, Commercial.

Sources

[1] Medical Prior Authorization Request (Form # 749VMPR, the served file; no issuer file found) (the Official source link on this page).

Please rate Coventry Prior Authorization Form

1 Votes
If you believe this page is infringing on your copyright, please familiarize yourself with and follow our DMCA notice and takedown process - click here to proceed .