


DD Form 2807-2 at a glance
What it is: DD Form 2807-2 is the Accessions Medical History Report.
Who signs: The Parent or Guardian Authorization signature is mandatory if the applicant is a minor.
Its purpose is to obtain medical data for determination of medical fitness for enlistment, induction, appointment, and retention for applicants and members of the Armed Forces.
What to bring and attach to DD Form 2807-2
Attach copies of all applicable medical records.
Under DENTAL, if you wear braces/aligners, then you must submit a letter from your orthodontist stating that active orthodontic treatment will be completed before beginning active duty.
A filled-in DD Form 2807-2 example: an Army applicant completes page 1
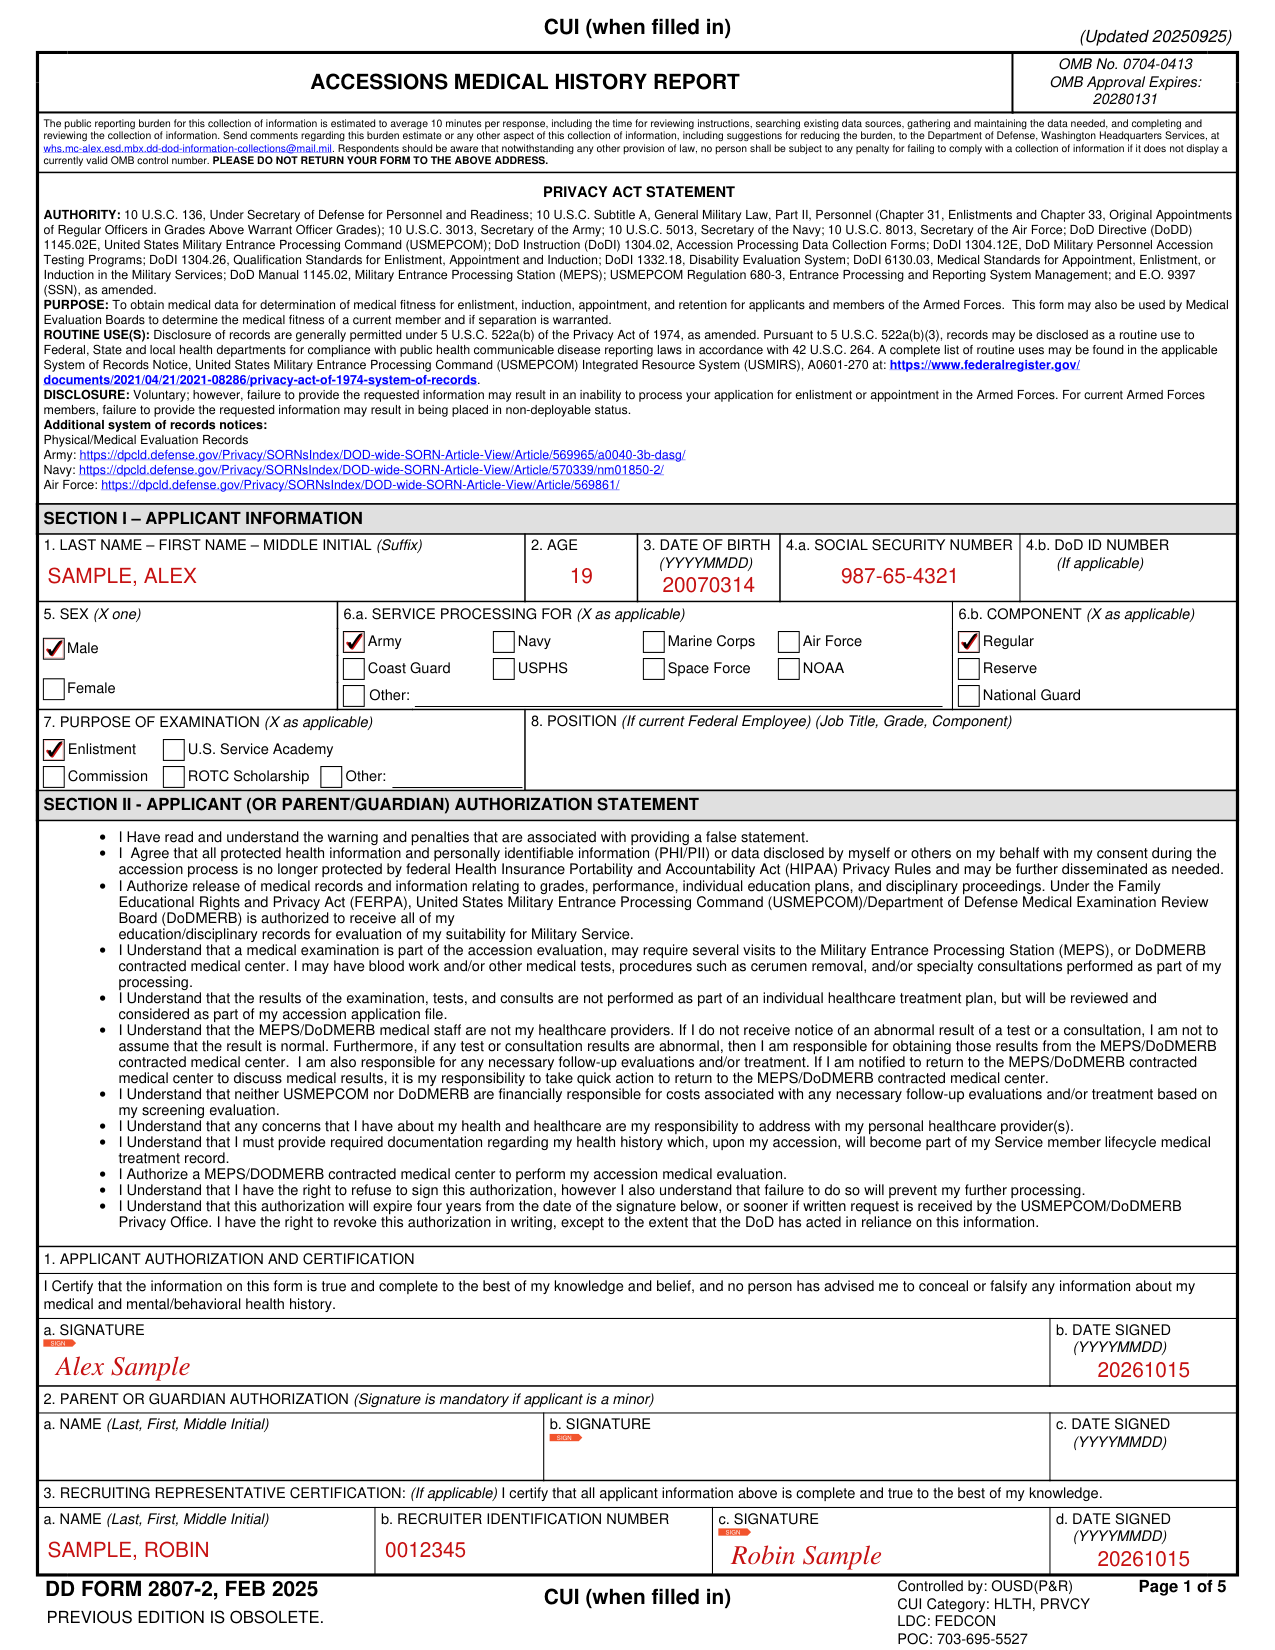
How to fill out DD Form 2807-2, box by box
Last Name, Age, Date of Birth, Social Security Number and DoD ID Number
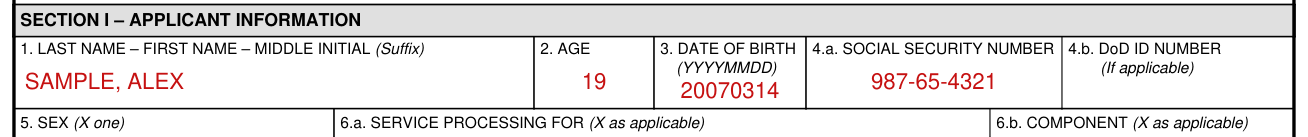
In Box 1, enter the Last Name, First Name and Middle Initial (Suffix); in Box 2, the Age; in Box 3, the Date of Birth (YYYYMMDD).
In Box 4.a, enter the Social Security Number. In Box 4.b, enter the DoD ID Number (If applicable).
Sex, Service Processing For, Component, Purpose of Examination and Position
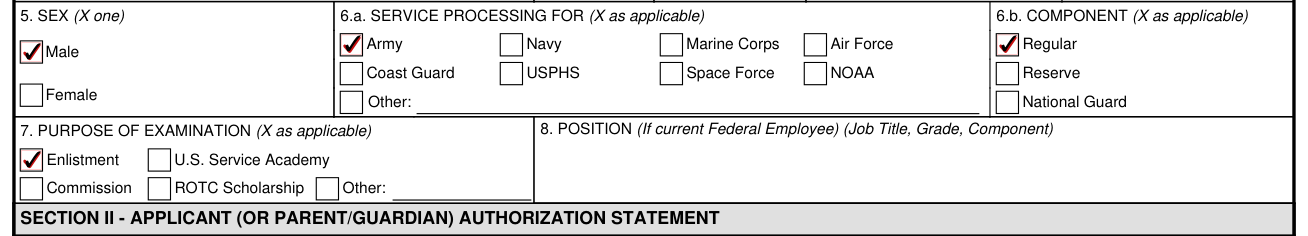
In Box 5, Sex, X one: Male or Female.
In Box 6.a, Service Processing For, X as applicable: Army, Navy, Marine Corps, Air Force, Coast Guard, USPHS, Space Force, NOAA or Other.
In Box 6.b, Component, X as applicable: Regular, Reserve or National Guard.
In Box 7, Purpose of Examination, X as applicable: Enlistment, U.S. Service Academy, Commission, ROTC Scholarship or Other.
In Box 8, enter the Position (Job Title, Grade, Component) if you are a current Federal Employee.
Applicant Authorization and Certification

To certify that the information on this form is true and complete to the best of your knowledge and belief, and no person has advised you to conceal or falsify any information about your medical and mental/behavioral health history, sign in Box 1.a and enter the Date Signed (YYYYMMDD) in Box 1.b.
Parent or Guardian Authorization
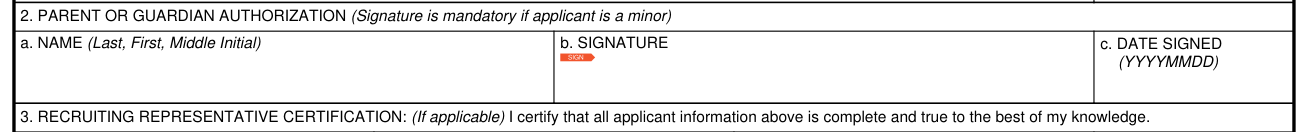
If the applicant is a minor, the parent or guardian enters the Name (Last, First, Middle Initial) in Box 2.a, the Signature in Box 2.b and the Date Signed (YYYYMMDD) in Box 2.c.
Recruiting Representative Certification

Under Recruiting Representative Certification (If applicable), the recruiting representative enters the Name (Last, First, Middle Initial) in Box 3.a and the Recruiter Identification Number in Box 3.b, and signs in Box 3.c and enters the Date Signed (YYYYMMDD) in Box 3.d to certify that all applicant information is complete and true to the best of their knowledge.
Item number, details and status
Write the item number and provide details to include the following: description of the problem/condition, date of onset of the problem/condition, date of treatment, name of health care provider, clinic, center, hospital along with City and State.
Comment on the current status of the problem/condition.
Attach additional sheet(s) if necessary, and sign and date each additional sheet.
More rules for DD Form 2807-2
Read each of the following questions and answer by checking YES or NO. Every question must be answered.
Every YES answer must be explained in SECTION IV. Explain each item to the best of your ability. Your medical records may be requested to clarify your medical history.
Under 1. Medications, list each prescription or over the counter medication(s) taken regularly or as needed and explain in SECTION IV.
Under 2. Allergies, list each reaction to food(s), insect bites/stings, medication(s) or other substances and explain in SECTION IV.
Under FEMALES ONLY, enter the First day of the last menstrual period (YYYYMMDD) at 40.
At 111, Discharge from Military Service for any reason: provide reason, date, and type of discharge.
You state that you have read and understand the warning and penalties that are associated with providing a false statement.
You have the right to refuse to sign this authorization, however failure to do so will prevent your further processing.
This authorization will expire four years from the date of the signature, or sooner if written request is received by the USMEPCOM/DoDMERB Privacy Office.
You have the right to revoke this authorization in writing, except to the extent that the DoD has acted in reliance on this information.
Sources
[1] DD Form 2807-2 (FEB 2025), Accessions Medical History Report, Washington Headquarters Services (the Official source link on this page).